Do Nurses like EHRs?

Join Our Mailing List

Do RNs like using electronic health records?

[A seldom considered POV]

1-darrellpruitt

BY Darrell K. Pruitt DDS

Some Facebook comments:

Big problems when you have unexpected “downtimes”.

July 15 at 3:10pm · Like · 4

It is an absolute train wreck. I haven’t seen one record of mine that is not riddled with mistakes. Especially the allergies, they show me taking meds I’m allergic to and not taking meds I’m actually on. A true mess!! And now the records are all intertwined. I don’t like it at all!!

July 15 at 3:10pm · Like · 2

It is a nightmare!

July 15 at 3:18pm · Like

I retired just in time so I don’t have to deal with this fiasco.

July 15 at 3:19pm via mobile · Like · 2

IT SUCKS

July 15 at 3:19pm · Like

I don’t like them; my doctors don’t like them; how it will affect patient care is still a ‘jury out’ matter, but we can guess it will NOT help.

July 15 at 3:30pm · Like

Our Rural Community Healthcare system is just now switching over to this .. along with our hospital switching over to a totally new computer system .. the 2 systems do not talk to each other..In my personal experience I find that the “computer” world takes us away from Direct Patient Care (to busy playing “ring around the Rosie” on the computer).

July 15 at 3:40pm · Like · 4

I like them, but it is frustrating having “downtime.”

July 15 at 3:41pm · Like

I hear patients stating things like “my doctors don’t know who I am because they don’t look at me they are glued to the computer”. It saddens me patients feel less valued. I’ve worked in places where they’ve had paper charts and places computerized. Seems the computers are redundant and I personally prefer paper charts. Chart one assessment not one assessment 4 different places.

July 15 at 3:44pm via mobile · Like · 3

It looks to me like physicians are cutting and pasting old histories and physicals, complete with the errors. Doctors in a local ER charted complete physicals on me when they did not get closer than 5 feet away. The records are difficult to read, difficult to find information; and it is not number in chronological order.

July 15 at 3:47pm · Like

I dislike it. Besides the down time, I find it very impersonal. I don’t feel as if I am giving my full attention to my pt, nor do I feel my PCP is hearing what I’m saying . They are too busy putting in info on the computer. As for the down time you then have to work late to put in the info gathered while the system is down.

July 15 at 3:47pm via mobile · Like · 2

eHRs

Assessment

https://www.facebook.com/friendanurse/posts/654085127954821

More: On DIgital Deaths

http://www.bloomberg.com/news/2013-06-25/digital-health-records-risks-emerge-as-deaths-blamed-on-systems.html

(50+ other comments)

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Should Doctors Collect Treasures?

Join Our Mailing List

On Investing in Art and Collectibles

By Rick Kahler CFP®

Rick Kahler CFPAlmost everyone has a story about a cousin or an aunt who bought a box of junk at an auction and found in it a diamond ring worth several hundred dollars. Every once in a while a valuable painting by a famous artist turns up in someone’s attic. “Antiques Roadshow” sometimes features odd items that have been sitting around in someone’s house for years and that are appraised for thousands of dollars.

This doesn’t mean buying and selling art or collectibles is a good way to make money.

Collectibles

Buying art, antiques, or collectibles is extremely speculative, in part because values are so subjective. What a given item is worth depends entirely on what a collector might be willing to pay at any given time. A piece of pottery or jewelry might fluctuate considerably in value as trends come and go. Yesterday’s hot collectible (think Beanie Babies or Jim Beam bottles) might be tomorrow’s overpriced embarrassment.

Does this mean you should never buy art or antiques in hopes that they’ll increase in value? Not necessarily. I am suggesting, though, that investment shouldn’t be the primary reason for your purchase.

If you’re going to collect Art Deco jewelry or decorate your home with original artwork, do so because you like those things. Choose a painting because you want it hanging on your wall. Buy a carving or a pot because you want it. Collect iron toys or old books because you have fun searching for them at antique stores and garage sales. If your art or collectibles increase in value, consider it a nice bonus.

If you’re hanging onto a piece of art or an antique that you don’t like because you think it’s valuable and you think of it as an investment, why keep it? You could sell it and put the proceeds into your retirement portfolio. Then your investment wouldn’t be taking up space in your house, and you wouldn’t need to worry about maintaining it or insuring it. Another option would be to use the money to buy something you would enjoy owning.

Do the Research

If you do decide to sell an item, do some serious research and try to find out what it’s really worth. Don’t just stick a price on it for a garage sale or walk into an antiques store and take whatever they offer you. Get at least two or three estimates from dealers or other qualified experts. For something that’s potentially quite valuable, paying for an appraisal might be money well spent.

Finding valuable collectibles at rummage-sale prices is almost always sheer luck. Anyone who consistently makes money buying and selling art or collectibles has invested the time and effort to become an expert. Unless you’re willing to do the same—and you would enjoy it—don’t try to fund your retirement this way.

Making Memories

In the interests of full disclosure, I should confess that not all of my own purchases turn out perfectly. One of my travel memories is of the time I bought two hand-woven carpets at bargain prices. What made the purchase memorable was the experience of stuffing the bulky rolled-up rugs into a taxi and hauling them to the airport, only to find that the baggage handlers had gone on strike.

Those carpets still decorate the floors in our house. Are they worth more than I paid for them? After all the effort it took to get them home, I certainly hope so. But I bought them because I liked them and wanted them in my home.

Assessment

But, if my primary goal had been investing, I would have put the purchase price into several well-diversified mutual funds instead.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

***


Should You Comparison Shop for an Investment Advisor?

Join Our Mailing List

 Consumer’s Repot Not Available

By Rick Kahler CFP® www.KahlerFinancial.com

Rick Kahler CFPYou can spot comparison shoppers a few aisles away at any retail store. They are the ones carrying articles from Consumer Reports, badgering the salesperson with a million and one questions. People who manage money well are usually big fans of comparison shopping.

If comparison shopping is important before choosing a new refrigerator or lawn mower, it’s even more essential before choosing an investment advisor. Unfortunately, there is no easily available consumer’s report on advisors. Even more frustrating, those selling financial products often have incentives not to be forthcoming with the information that is crucial for comparing advisors.

A Focus on Investment Returns

One aspect of shopping for an investment advisor is to know what questions to ask. One common mistake is to focus on investment returns. Shoppers may ask for the average recent returns of the advisor’s portfolios or may want to know whether the advisor’s returns beat the market averages.

Problems:

There are several problems with focusing on returns.

First, the numbers mean nothing without also knowing how much risk the advisor took to produce the return. It’s like someone on a diet focusing only on fat grams without regard to total calories. Consuming ten soft drinks in a day may give you zero fat grams, but you could easily exceed your daily calorie limit before eating one bit of food.

Second, any unscrupulous advisor can put together a portfolio consisting of the hottest investment classes over the past 10 years and show you how fantastically they did.

Third, whether an advisor beats the market is overrated. Why? A whopping 97 percent of all mutual fund managers don’t generate an “average return” over 20 years. Just finding an advisor who has done so means you found someone in the top three percent.

Fourth, some financial advisors may show you a phenomenal track record for the short term (under 10 years). Since wise investing focuses on the long term, beating the averages over a short term isn’t necessarily significant.

Gamesmanship

If so many games can be played around returns, what questions should a savvy comparison shopper ask? Focus on one word: transparency. You want to find out if the returns, costs, and risk (standard deviation) of your portfolio will be clearly displayed and contrasted against appropriate benchmarks.

Transparency

Here is how to accomplish that goal. Most advisors have model portfolios. Ask them to show you the standard deviation and the expense ratio of their model over five and ten years. Ask them to contrast the return of the portfolio against a similar benchmark.

For example, if the portfolio has US stocks, US bonds, and foreign stocks, have them compare it to a benchmark of indexes proportionate to those asset classes.

Next, either ask the advisor to run a similar analysis on your existing portfolio or have one done independently. You may even have done better than the advisor’s model.

Ask the advisor to disclose all fees in addition to the expense ratios charged by mutual fund or sub-account managers. You need to find out how the advisor is paid and how much. Ask whether there are any wrap fees, transaction costs, administrative fees, mortality fees, redemption fees, annual 12b(1) fees, surrender charges, or up-front sales charges.

Referral

Assessment

Don’t be surprised if you get a bit of resistance when you ask for all this information. Brokerage firms, life insurance companies, and many commission-based advisors don’t have much incentive to give you this data and may not even be able to.

If you don’t get clear disclosure on fees and costs, keep asking. If you persist and still don’t get understandable answers, you may need to do more comparison shopping before you choose an advisor.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Why Hospitals Should Use Financial Management Checklists

Join Our Mailing List

Financial Management Strategies for Hospital and Healthcare Organizations [Tools, Techniques, Checklists and Case Studies]

By Neil H. Baum MD

Dr. BaumIt is fitting that ME-P Editor Dr. David Edward Marcinko MBA CMP™ and his fellow experts, have laid out a plan of action in Financial Management Strategies for Hospital and Healthcare Organizations: Tools, Techniques, Checklists and Case Studies that physicians, nurse-executives, administrators and institutional Chief Executive Officers, Chief Financial Officers, MBAs, lawyers and healthcare accountants can follow to help move healthcare financial fitness forward during these unchartered waters.

In medicine – It all began with Dr. Atul Gawande, a surgeon at Massachusetts General Hospital, who reviewed the airline industry and their use of checklists prior to take off of an airplane.

The history of aviation checklists began in 1934 when Boeing was in the final process of testing a U.S. Army fighter plane with a potential contract of nearly 200 planes riding on the final test of the plane. The test aircraft made a normal taxi and takeoff. It began a smooth climb, but then suddenly stalled. The aircraft turned on one wing and fell, bursting into flames upon impact killing two of the test pilots. The investigation found pilot error as the cause. One of the pilots who was unfamiliar with the aircraft had neglected to release the elevator lock prior to take off. The contract with Boeing was in jeopardy.

Thus, the pilots sat down and put their heads together. What was needed was some way of making sure that everything to prevent crashes was being done; that nothing was overlooked. What resulted was a pilot’s checklist developed before takeoff, during flight, before landing, and after landing. These checklists for the pilot and co-pilot made sure that nothing was forgotten and safety of the planes was insured.

Medical Care and Hospitals

So, what does airline safety have to with medical care and hospitals?

There are so many activities that take place in medicine such as the operating room, that are far too complicated to be left to memory of doctors, nurses, anesthesiologists, and others involved in the surgical care of patients.  Dr. Gawande identified the key components of a surgical procedure which include the name of the patient, the procedure to be performed, the estimated length of the procedure, whether the right or left side is the surgical target, how much blood loss is anticipated, whether antibiotics have been given prior to making the incision, and the anesthetic risk of the patient.  This use of a checklist which takes approximately 30 seconds has not only prevented wrong side surgery but also instills a discipline of higher performance.

###

Financial Management Strategies for Hospitals and Healthcare Organizations

Financial Management Strategies for Hospitals and Healthcare Organizations: Tools, Techniques, Checklists and Case Studies

###

From the Clinic to the Boardroom

And so, should [can] we port the clinical checklist example of Atul Gawande for use with non-clinical topics like hospital financial management and administration?

Assessment

Yes – We have a challenge and the Financial Management Strategies for Hospital and Healthcare Organizations: Tools, Techniques, Checklists and Case Studies is a step in the direction to make all of the stakeholders in the healthcare arena become sensitive to reducing and controlling costs and at the same time preserve quality of care.

This can be done.  I suggest you start by reading, using and referring to this excellent book.

And so, what is my final advice? Read the Book!

Some of you who will read this book are CXOs COOs, Chief Medical Officers and maybe even COS. (Chiefs of Staff). But, all of you should become CLOs (Chief Life Officers)!  Read this book and the initials CLO will appear after your name!

Note:

Neil H. Baum MD is a Clinical Associate Professor of Urology at the Tulane Medical School, New Orleans, LA. He is also a thought-leader for this ME-P. 

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Fake Sandwich Drug Concealment

Join Our Mailing List 

Hiding illegal drugs in a plastic “sandwich”

By Anonymous

[Click to View]

Fake Sandwich Concealment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

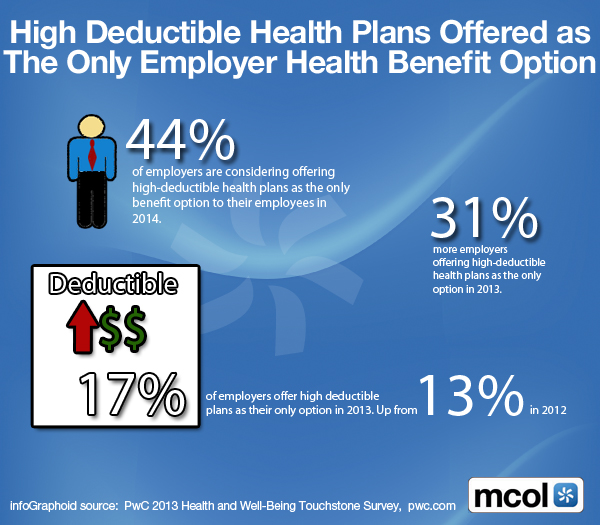
The High Deductible Health Plan Option?

Join Our Mailing List

As the Only Employer Health Benefit Choice!

By www.MCOL.com

###

HDHPs

###

More

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Are Doctors Spenders or Savers?

Join Our Mailing List 

Or … Just Delusional like the Rest of Us!

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPAccording to Scarborough, a market research firm, only 9% of adults in the U.S. label themselves as spenders. This is the percentage that “mostly agrees” with the statement, “I am a spender rather than a saver.” On the opposite side, 29% “mostly disagree” with the statement and are considered savers. Presumably, the 62% in between consider themselves to have well-balanced financial habits that include both spending and saving.

Given these numbers, it would seem that most of the adults in this country ought to have healthy savings accounts. Unfortunately, that’s not the case.

Employee Benefit Research Institute

According to a report released in March 2013 by the Employee Benefit Research Institute, 57% of U.S. workers have less than $25,000 in total household investments and savings, not including the value of their homes. The Social Security Administration’s current figures show 34% of American workers have no savings set aside specifically for retirement.

Something doesn’t quite add up. Either a lot of Americans aren’t willing to admit that they are spenders, a lot of Americans are so poor that they can’t afford to save, or a lot of Americans are delusional.

Habits of Savors

Or maybe a lot of us just have different definitions of “saving.” Here are a few money habits that might encourage people to think of themselves as savers, but that don’t necessarily add up to being successful savers:

1. Buying things on sale. Waiting for discounts on items you need and want is a wise and standard practice for frugal shoppers. But you aren’t a saver if you buy bargains that you don’t need, might not even really want, or can’t afford. Maybe that $150 pair of shoes is half price. Yet if they will just sit in your closet, you haven’t saved $75. You’ve spent $75.

2. Having money in the bank. Yes, putting money into a savings account is the first place to start saving and a great habit to teach your kids. But once you have accumulated an emergency fund, keeping your money in the bank isn’t a good savings habit. Over time, savings accounts and CD’s don’t pay enough to keep pace with inflation. Money in the bank may be safe, but it isn’t really an investment because it isn’t growing. Mutual funds that include a well-diversified range of investments are far better places for your long-term retirement savings.

3. Not spending anything. There are times when choosing not to spend money now will only cost you more money later. Failing to maintain your car or do home repairs are two common non-spending habits that may seem like saving but actually turn into spending.

4. Saving for someone else. The time-tested advice to “pay yourself first” usually means taking money off the top for savings before you spend anything. Yet this has another application, as well. Make saving and investing for your own retirement your first priority. It needs to come ahead of saving for your kids’ college educations, weddings, or first homes. This may seem selfish or greedy, but in fact it’s the opposite. When you provide for your own financial well-being in retirement, your kids won’t end up having to help pay your bills.

###

spendthrift

Assessment

When we’re asked to label ourselves, it’s normal to tend to choose answers that fit the way we would like to think of ourselves. I’m sure most of us would prefer to think of ourselves as savers rather than spenders.

But, if we really want to become successful savers, we can’t settle for the money habits we wish we had. We need to look at the money habits we actually practice.

Psychologists and psychiatrists, please comment. Are doctors the same as the rest of us, or not?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Recommended Readings for Financial Advisors from the No. 1 NBER Bulletin on Aging and Health for 2013

Join Our Mailing List

By Staff Reporters

The 2013 No. 1 Bulletin includes the articles below:

1)  Do Retirement Savings Policies Increase Total Retirement Saving?
by Raj Chetty, John Friedman, Soren Leth-Petersen, Torben Nielsen, and Tore Olsen

http://www.nber.org/bah/2013no1/w18565.html

2)  Behavioral Hazard in Health Insurance
by Katherine Baicker, Sendhil Mullainathan, and Joshua Schwartzstein

http://www.nber.org/bah/2013no1/w18468.html

3)  The Revenue Demands of Public Employee Pension Promises
by Robert Novy-Marx and Joshua Rauh

http://www.nber.org/bah/2013no1/w18489.html

4)  What Makes Annuitization More Appealing?
by John Beshears, James Choi, David Laibson, Brigitte Madrian, and Stephen Zeldes

http://www.nber.org/bah/2013no1/w18869.html

5)  The Prevalence and Economic Consequences of Disability
by Bruce Meyer and Wallace Mok

http://www.nber.org/bah/2013no1/w18575.html

Source: View a printable PDF copy of the at: http://www.nber.org/aginghealth/2013no1/2013no1.pdf

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

On Doctors Passing Wealth to Children

Join Our Mailing List 

Limiting your kid’s ability to tap principal

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPWhen passing wealth to your kids, some medical professionals should consider creating a trust to limit the later generation’s ability to tap into the principal. Several astute readers suggested this strategy after my recent column citing research that shows 90% of inherited wealth is gone by the third generation.

Preserving Wealth

There is no question that a trust, done correctly, can go a long way to preserve wealth after the death of the wealth accumulator. Let’s explore what “done correctly” means.

1. Trust law is complex. Engage an accountant and attorney with strong skills and expertise in trusts.

2. Be sure the assets you intend to go into the trust will actually transfer.

Retirement plans like IRA’s, 401(k)’s, and profit sharing plans will pass to whomever you listed as the beneficiary. This must be the trust. In addition, the trust must include a number of special provisions in order for a retirement plan to be distributed according to your wishes and not as a fully taxable lump sum.

Annuities, insurance policies, and accounts with a TOD (transfer on death) clause will also pass to the named beneficiary.

Assets held in joint tenancy will not pass to the trust. Many married couples jointly own most of their major assets, such as the family home, investment real estate, brokerage accounts, or bank accounts.

3. Be sure there are enough assets in the trust to justify the trustee fees. Most professional corporate trustees charge $3,500 to $10,000 annually, or up to 1% of the trust assets. If a trust with $100,000 incurs an annual fee of $3,500, your hard-earned estate will benefit the trustee as much as your heirs. A trust probably doesn’t make financial sense if the total fees will exceed 2%.

4. If a trust still seems like a good strategy after the above caveats, the next question is how much to limit heirs’ ability to withdraw money. From an actuarial standpoint it’s fairly simple. If you limit annual withdrawals to 3% of the principal, there’s a strong probability of the money lasting several generations with its buying power intact. Provided, that is, the trustees pay close attention to the next point.

5. To generate sufficient returns to pay out up to 3% annually to heirs and also keep up with inflation, the majority of the portfolio must be invested in assets that will grow over time, such as stocks, real estate, and commodities. It needs to be broadly diversified among many asset classes and countries. The trustees must also limit the fees paid to manage the investments. Many corporate trustees have an inherent incentive to use their own bank’s mutual funds, which can have annual fees as high as 1.5%. One way to avoid this conflict of interest is to instruct the trustee to place the funds with a fee-only investment advisor who has a largely passive approach to managing money. This could cut the portfolio fees by 50% or more.

6. Finally, before setting up any trust, pay close attention to taxes. Congress recently increased the top income tax bracket to 39.6% on wealthy taxpayers. Any trust which keeps more than $11,950 of annual income is considered “wealthy.” So here is the problem. If the trust retains enough earnings to increase the principal to offset inflation, it will have to pay substantial income tax and will probably need to restrict withdrawals to 1 or 2%. All of a sudden a multi-million dollar inheritance becomes simply a source of secondary income similar to Social Security.

###

Tax and Financial Strategy 2012

Assessment

Trusts are valuable estate planning tools. But like any other powerful tools, they are best employed by someone with the skills to use them well.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Example Total Expenditures on Health

Join Our Mailing List

International Per Capita Total Spending

By: http://www.MCOL.com

###

costs

###

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Ramadan Greetings 2013

Join Our Mailing List

Ramadan 2013 In Pictures: Muslims Celebrate Around The Globe (PHOTOS)

###

106014

###

[Tuesday July 9th to Wednesday August 7th 2013]

Product DetailsProduct DetailsProduct Details


The Doctor’s Path to Wealth?

And … for us all

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPAfter three decades as a financial planner, working with successful wealth-builders, you’d think I would have a clear idea of the right path for creating wealth.

Instead, what I’ve learned is that there is no such thing. Here are just a few of the paths that aren’t the sure routes to wealth they might seem to be:

Several Paths

1. Education and career choices. Going into a field like law or medicine might seem to guarantee financial success. Not necessarily. I’ve seen many physicians, for example, who have accumulated significant wealth. I’ve seen just as many who live paycheck to paycheck.

2. High earnings. Again, this isn’t the reliable predictor of wealth it would seem to be. True, someone who spends decades in low-wage jobs is unlikely to be able to accumulate much financial security. But a person earning $1 million a year will not necessarily have a larger net worth than someone earning $75,000. I’ve seen people who worked as janitors, nurses, and mechanics become millionaires. I’ve worked with others, earning a hundred times more in careers like sales or entertainment, who reach retirement age with absolutely nothing.

3. Owning your own business. Many hard-working, creative entrepreneurs build successful businesses that provide wealth, not just for themselves, but for their children and grandchildren. Others might see a business or even a series of businesses fail. Still others might work hard all their lives but never achieve more than the equivalent of an average salary in their field.

4. Investment choices. Some people have had great success investing in various types of real estate, businesses, and commodities. Others have lost everything they ever owned investing in those same vehicles.

Some Commonalities

So, sorry, I can’t give you a simple list of the top ways to build wealth. There’s little commonality in how my successful clients have made their money. What I can suggest are a few ways to help you find your own path to accumulating wealth.

1. Define “wealth” in your own way. Maybe you’re willing to live frugally in order to accumulate enough money to feel secure that your needs will be met even if you live to be 100. Maybe wealth to you is living a lavish lifestyle and being willing to work hard to pay for it. You might see wealth as the satisfaction and responsibility of having your own business. Maybe it means being able to give generously. Or perhaps you define wealth as the freedom of owning little and traveling around the world on a bicycle.

2. Know what you are willing to sacrifice—and what you are not—in order to accumulate wealth. There’s nothing wrong with earning a high salary doing work you hate for a time, as part of an overall strategy to get you to doing something you love. But doing so for a lifetime is hardly the road to either happiness or wealth.

3. Think long term. The most reliable way to build lifetime wealth, with the lowest risk, is through a long-term commitment to diversified investing. Yet even those who are successful on riskier paths to wealth take the long view. Business owners may fail more than once before they succeed. And those who have made fortunes in high-risk investments have also lost fortunes. They understand that success is about taking calculated risks.

4. Learn to make conscious financial decisions. I’ve seen many intelligent, capable people stuck in financial chaos and poverty because of emotional pain and dysfunction. Emotional health may not be essential for building financial wealth. It is, however, essential if you want to use that wealth to support a rich and satisfying life.

###

Stock Market

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

***

  Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

***

Invite Dr. Marcinko

***

Some Out-Sourced Medical Humor

Join Our Mailing List

Introducing The Health Scout

By Staff Reporters

We are delighted to refer our ME-P readers to Dalya Munves over at the Wing of Zock.

Dalya is a medical student at The University of Texas at Houston, where she just completed her first year. Before medical school, she earned a B.A. in Literary Studies with a Minor in Philosophy from The University of Texas at Dallas.

Sample

Assessment

Dalya is currently interested in specializing in Internal Medicine or Obstetrics and Gynecology. She blogs at The Health Scout and you can follow her on Twitter @HealthScoutBlog.

So; when you need a chuckle – just give her site a click!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Twelve Steps of Financial Independence for Doctors

Join Our Mailing List

A Basic Guide

By Lon Jefferies  MBA CFP® CMP®

Lon JeffriesWant to get your finances in order? Consider this comprehensive 12-step guide to address each element of your personal financial situation. In most cases, you should not address a step until all previous steps are satisfied.

1. 401(k) 403(b) Match: Without exception, if your employer matches 401(k) contributions, you should maximize whatever they’re offering. If it’s a dollar-for-dollar match, that’s an instant 100 percent return! Even the 50 percent return of a two-for-one match is irresistible.

2. Consumer Debt: Pay off your credit cards and all other unsecured loans, prioritizing the debts with the highest interest rates. Credit cards frequently charge rates as high as 30 percent. Paying off a card with 30 percent APR is comparable to getting a 30 percent investment return. Not completing this step will hamper your entire financial plan.

3. Cash Flow: You can’t develop wealth if you spend more than you make. Construct and follow a written budget to ensure you are living within your means. Your budget should include saving at least 10 percent of your gross income for retirement. Constantly compare actual spending with your budget and hold yourself accountable! Mint.com is an excellent free tool for this step.

4. Emergency Reserve: Develop a liquid savings account consisting of enough money to cover three to six months of expenses. These funds should only be utilized in crisis such as a job loss or medical emergency.

5. Life Insurance: If you have dependent children, you likely need life insurance. Cost-efficient coverage can frequently be obtained via your employer. To calculate the amount of coverage to purchase, first determine how much money your survivors would need to maintain a comfortable lifestyle, and then subtract any income they will generate as well as any savings you’ve accumulated. Alternatively, if you don’t have children in your household and your spouse is self-sufficient, you may not need life insurance coverage.

6. Disability Insurance: Getting hurt can completely derail your financial planning. A loss of income halts your savings and likely leads to increased debt. Obtain enough disability coverage to bridge the gap between earnings and expenses in the event of an injury. Coverage can frequently be purchased through your employer.

7. Estate Planning: Obtain a power of attorney, medical directive and living will. These documents allow you to designate the person you would like to make decisions for you if you become incapacitated. They also specify your preferences regarding life-prolonging medical treatments. Ensure both primary and contingent beneficiaries are assigned to your retirement accounts. Finally, develop a will or trust to ensure all other assets are distributed as you desire when you die.

8. Retirement Contributions: With risk exposures covered, it’s time to return to retirement planning efforts. Again, a 401(k) is an attractive retirement vehicle because it frequently offers an employer match and allows large annual contributions ($18,500 or $25,000 for individuals over age 50). If your employer doesn’t offer a 401(k), you can still contribute up to $6,500 (or $7,000 if over age 50) to an IRA. IRA contributions can be made on behalf of both spouses, even if only one is employed.

9. Traditional or Roth: The type of account that is best for you depends on when you want to pay taxes. A traditional retirement account allows an immediate tax deduction, the investments grow tax deferred, and the money isn’t taxed until the funds are withdrawn from the account. Alternatively, taxes are paid on Roth contributions immediately, but both contributions and growth are completely tax free when withdrawn during retirement. Put simply: will you be in a higher tax bracket now or when you withdraw the funds?

10. Asset Allocation: The most important investment decision you can make is how much of your portfolio will be invested in stocks versus bonds. A higher proportion of stocks leads to increased risk, but the potential for greater returns. The more time you have until the funds are needed, the more risk you can usually afford to take. Consequently, you should reduce the proportion of stocks in your portfolio as you approach retirement in order to minimize your risk factor. Identify an asset allocation that is aggressive enough to accomplish your investment goals while exposing you to an acceptable level of risk.

11. Get Caught Up: According to a recent Fidelity study, your nest egg should be one times your salary by age 35, three times your salary by 45, five times your salary by 55 and seven times your salary by 67.

12. Education Planning: Only after your retirement savings is where it should be can you focus on your children’s college education. At this point, explore a Utah Educational Savings Plan 529 (uesp.org) or a Coverdell Education Savings Account, both of which offer tax advantages if used for schooling.

Assessment

Does this mean you don’t need a financial advisor? Of course not! A qualified, comprehensive financial planner can add value, address shortcomings, and answer questions in each of these areas. Once you have completed each of these steps, you can be confident you have your financial ducks in a row.

###

healthcare-business

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

PP-ACA Physician Ownership Provisions

Join Our Mailing List

Understanding the “whole hospital exception” to the Stark laws

By Dr. David Edward Marcinko MBA CMP®

www.CertifiedMedicalPlanner.org

Dr. David E. Marcinko MBAThis was a big week for healthcare reform, wasn’t it? Some provisions of the PP-ACA requiring the employer mandates were delayed another year; until January 1, 2015.

But, before passage of the ACA in 2010, the “whole hospital exception” to the Stark law allowed physicians to have an ownership interest in a hospital to which those physicians refer patients, provided the physician is invested in the whole hospital and not a subdivision of the hospital, with no limitations as to the amount or extent of physician ownership, on either an aggregate or individual basis.

Prohibitions

Now, according to colleague Robert James Cimasi MHA, AVA, ASA, MCBA, CMP®, of www.HealthCapital.com, The ACA completely prohibits physician-owned hospitals which were not Medicare-certified by December 31, 2010.

[1] The ACA allows hospitals with a provider agreement prior to December 31, 2010 to continue Medicare participation if they meet the following four criteria: (1) located in a county with a population growth rate of at least150% the state’s population growth over the last 5 years; (2) have Medicaid inpatient admission percentage of at least the average of all hospitals in the county; (3) located in a state with below-national-average bed capacity; and, (4) have bed occupancy rate greater than state average. [2]

Grandfathered

A very limited number of physician-owned hospital existing in 2010 met or were close to meeting all 4 of criteria.[3] The Reconciliation Act provided a limited exception to the ACA growth restrictions for grandfathered physician owned hospitals that treat the highest percentage of Medicaid patients in their county (and are not the sole hospital in a county).[4]

###

Financial Management Strategies for Hospitals and Healthcare Organizations: Tools, Techniques, Checklists and…

### 

Assessment

Based on these provisions, the 2010 healthcare reform legislation will likely have a considerable negative impact on physician-owned hospitals, in terms of impeding development of new hospitals and expansion of existing hospitals.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org


[1]       “Section-by-Section Analysis with Changes Made by Title X and Reconciliation included within Titles I-IX,” Democratic Policy Committee, http://dpc.senate.gov/healthreformbill/healthbill96.pdf (Accessed 5/24/2010).

[2]       “Section-by-Section Analysis with Changes Made by Title X and Reconciliation included within Titles I-IX,” Democratic Policy Committee, http://dpc.senate.gov/healthreformbill/healthbill96.pdf (Accessed 5/24/2010).

[3]       “Healthcare Reform: A Brief Analysis on How it Impacts ASCs and Physician-OwnedHospitals – 10 Observations”, By Scott Becker, Leigh Page, and Rob Kurtz, Becker’s Hospital Review, http://www.beckersorthopedicandspine.com/news-a-analysis/legal-a-regulatory/1193-healthcare-reform-abrief- analysis-on-how-it-impacts-ascs-and-physician-owned-hospitals-10-observations (Accessed 5/20/10).

[4]       “Section-by-Section Analysis with Changes Made by Title X and Reconciliation included within Titles I-IX,” Democratic Policy Committee, http://dpc.senate.gov/healthreformbill/healthbill96.pdf (Accessed 5/24/2010).

Product DetailsProduct Details

The Most Common Sites of Automobile Accidents

Join Our Mailing List 

Doctors Be Aware

[By Dr. David Edward Marcinko MBA]

By Nalley Collision Center

Dr. David E. Marcinko jpeg

Even with the latest safety features, the risk of an automobile crash or collision is never far away from the minds of most drivers. This is especially the case for some doctors who may have a proclivity to drive expensive automobiles.

But, where are the most common sites for automobile accidents? With the summer upon us – and the long Independence Day weekend – we may have the answers.

The Sites

One popular old statistic suggested that most accidents occur near the home, and numerous road safety campaigns have encouraged drivers not to be complacent as they drive along the streets in their local neighborhood. But, there are also several more specific places where automobile accidents are most common.

Car Parks

Car parks and lots are confined spaces full of motorists engaging in difficult maneuvers around other vehicles, while pedestrians walk around them. In general, the accidents are minor scrapes and dents, but they are very common indeed.

Junctions

It’s not surprising that intersections between roads are likely to produce more than their fair share of accidents. Whether it’s a rear end crunch for the driver suddenly forced to stop while turning, or a side-impact caused by a momentary loss of concentration, junctions are common crash locations.

The good news is that traffic should normally be moving relatively slowly at intersections, so damage is often limited to little more than scratched paintwork and injured pride.

Stoplights

Although unregulated intersections can pose safety problems for drivers, stoplights themselves bring their own challenges. They regulate traffic flow, and can lead to rear end collisions when drivers have to stop suddenly. Sometimes one rear end impact can result in a pile-up as the cars behind also fail to stop in time in a chain reaction. As many stoplights are associated with pedestrian crossings, these accidents have the potential to be serious.

Country Roads

Driving along an empty country road, a driver could be forgiven for thinking that the risk of auto accidents would be low. Unfortunately this appears not to be the case. Country roads are common accident sites for two reasons.

The fact that they are so quiet, and often straight with little variety in the landscape, means that motorists can find themselves losing concentration (often even falling asleep) for just a couple of moments, which is all it takes for a car to end up in a ditch by the side of the road.

Also, of course, rural highways tend not to be as well maintained as busy urban routes, and potholes and other debris also contribute to accidents.

Busy Roads

But, if quiet country roads are common accident sites, so are busy two (or more) lane roads. The reason why busy roads are dangerous is that with several lanes of traffic in each direction, sometimes with no barrier, drivers have no way of avoiding a head-on collision if, for example, a vehicle drifts towards the road’s center, or if a car pulls out into oncoming traffic to overtake the vehicle in front without checking the road ahead.

###

jaguar

###

DEM's Jaguar

More:

Assessment

Doctors, medical professionals and all motorists, have their work cut out, with quiet roads, busy roads, unregulated junctions, stoplights and car parks all providing rich scope for accidents. What this really illustrates, however, is the extent to which drivers cannot afford to let their attention slip for an instant when behind the wheel.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details


Some Vital Survival Tools for Physicians and their Consulting Advisors

OUR BOOKS, TEXTS AND DICTIONARIES ARE VITAL SURVIVAL TOOLS FOR ALL PHYSICIANS … AND THEIR CONSULTING ADVISORS 

###

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

      Join Our Mailing List

Events Planner: July 2013

ADVERTISEMENT

Events-Planner: JULY 2013

By Staff Writers
Calendar Calculator“Keeping track of important health economics and financial industry meetings, conferences and summits”

Welcome to this issue of the Medical Executive-Post and our Events-Planner. It contains the latest information on conferences, news, and relevant resources in healthcare finance, economics, research and development, business management, pharmaceutical pricing, and physician/entity reimbursement!  Watch for a new Events-Planner each month.

First, a little about us! The Medical Executive-Post is still a relative newcomer. But today, we have almost 500,000 visitors and readers each month from all over the country, in addition to our growing subscriber base. We have been a successful collaborative effort, thanks to your contributions.  As a result, we are adding new resources daily. And, we hope the website continues to provide the best place to go for journals, books, conferences, educational resources, tools, and other things you need to establish the value your healthcare consulting and financial advisory intervention.

So, enjoy the Medical Executive-Post and this monthly Events-Planner with our compliments.

A Look Ahead this Month – And now, the important dates:

  • July 21-24: ASHE Conference. Atlanta, GA
  • July 28-31: AHRMM Conference. San Diego, CA

MarcinkoAdvisors@msn.com

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest E-Ps delivered to your email box each morning? Just subscribe using the link below. It’s free. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Safe Driving Tips all Doctor’s May Learn from Bus Drivers

Join Our Mailing List 

On Physicians Driving Safely

By Dr. David Edward Marcinko MBA

By Nalley Collision Center

Dr. MarcinkoBus drivers take their lives into their hands every day on city streets and interstate highways. Despite challenging traffic conditions and the responsibility of a large vehicle and numerous passengers, bus drivers find ways to stay safe while keeping up with demanding routes and schedules. These unsung heroes of the road universally command respect, but they also offer important lessons to ordinary drivers who share busy roads with buses every day.

So – as summer is upon us – and in the spirit of safe driving – allow our ME-P team at to share a few bus-driver inspired driving tips with you.

Distracted Driving

Modern technology has caused an addiction for many bus drivers as they struggle to communicate while safely driving a bus.

An Italian bus driver was caught on video simultaneously using two cell phones while steering his bus with his elbows. This talent showed the world that cell phone use behind the wheel might not present the extreme danger most people expect.

Seriously, bus drivers can provide some good examples of how not to drive. Although many states have laws in place restricting the use of electronic devices while driving, many states do not. All drivers, and every doctor, should avoid risking their lives and the lives of passengers by reserving cell phone use to emergencies while driving.

Road Rage

A New York City school bus driver named Juan DelValle side-swiped a car on a crowded city street and was subsequently attacked by the offended driver. DelValle was within days of his long-awaited retirement and died from severe injuries to his brain.

This one example shows how a minor traffic incident can quickly escalate into a life-changing event for unprepared drivers. Drivers should exercise extreme caution every time they have an incident with another driver. After an accident, drivers who feel threatened can call police and wait in their cars until help arrives.

Rest                                             

Bus drivers illustrate why no one should sit behind the wheel of a vehicle when fatigued.

Investigators determined that a tour bus crash in New York that killed 15 passengers was caused by a sleepy driver. The bus driver, Ophadell Williams, was charged with criminally negligent homicide. His life might never return to its previous state.

Drivers who spend time getting the sleep they need might arrive late at their destination, but they also arrive with a clear conscience, an alert mind, and living passengers.

Defensive Driving

A Transit bus in Los Osos, California rolled down an embankment after colliding with a car on a dark and wet stretch of road. Bus drivers know they cannot count on the driving skills of other motorists for safety, so they drive defensively. In the Los Osos case, the bus driver managed to stay alive after the Mercedes crossed the center line.

Although the driver of the automobile died in the wreck, all the bus passengers lived.

DEM's Jag XJ-V8-LMore

Assessment

Every driver should periodically take time to review defensive-driving tactics or to attend a defensive driving class to improve their ability to respond to unexpected circumstances on the highway.  

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details


On Inherited Money

Join Our Mailing List 

The “money scripts” of inheritances

By Rick Kahler MS CFP® ChFC CCIM http://www.KahlerFinancial.com

Rick Kahler CFP“I’ve never seen money passed from one generation to another in a manner that actually benefited the recipient.”

When a psychologist said this to me several years ago, I was dumbfounded.

Many parents, like some doctors, scrimp, save, and sacrifice so they can “leave something to the kids” with the intention of doing them good. It’s hard to accept that inheritances may actually do harm instead. Most of us have money scripts that don’t support this idea.

Money Scripts

Typically, I used to hold several money scripts around inheritances. One was that leaving money to your children is a loving thing to do. Another was that parents should always leave their money to their children. A third was that anyone who received an inheritance would invest it wisely, using only the earnings to improve their lives.

Today I know those money scripts were not universal truths. I have more understanding of the problems involved in giving money away in a manner that is beneficial to the receiver. It isn’t as easy as I once thought.

Seed Money?

Many parents envision inheritances for their kids as “seed money” that will be used for the health, education, and welfare of their offspring for many generations. Research shows that is rarely the case; instead, inherited wealth does not last long. Missy Sullivan summarizes some of the research in “Lost Inheritances,” a Wall Street Journal article published online March 7, 2013. According to this article, 70 percent of those who receive an inheritance of any size spend it all in their lifetimes.

http://online.wsj.com/article/SB10001424127887324662404578334663271139552.html

For the 30 percent that do have something left to pass on, 70 percent of their kids also blow everything they get. That means by the end of the third generation, 90% of the money originally passed down is gone.

While it’s easy to understand how an inheritance of $10,000 may evaporate, it’s difficult to understand that inheritances in the hundreds of millions evaporate just as quickly. How is that possible? Is the average American just incompetent at managing money?

The Research

According to Sullivan, a study done by the Williams Group found that poor investment decisions were not the culprit. About 60 percent of large inheritances disappeared because of a lack of trust and communication between family members. Another 25 percent of the time, money evaporated because the parents failed to prepare the next generation to handle their impending inheritance. Poor investment advice and high fees were the cause in less than 15% of cases.

###

Money

Options

If more high net worth parents knew that only 10% of their hard-earned estates would be around at the end of their grandchildren’s lives, I wonder if they might do a few things differently.

One option would be to address the two biggest issues—lack of communication and preparation for heirs—head-on during their lives. Parents wanting their money to benefit their kids could engage the services of a financial therapist who could help the family address their communication and trust issues long before they pass on their wealth. Preparing their children to manage wealth and use it wisely would be the best way to increase the odds of making an inheritance a blessing rather than a burden.

Another option would be to secure their own retirement, then forget all the scrimping and saving and just have fun blowing the money on themselves.

Still another option would be to give their wealth to worthy causes during their lifetimes or upon their deaths.

Assessment

This would leave the kids to make their money by ingenuity, hard work, wise money management, frugality, and a little bit of luck. The same way, in fact, their parents did. Are medical professionals any different?

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details


On the Future of Dentistry?

Join Our Mailing List 

Not good for the profession … as we know it!

By D. Kellus Pruitt DDS

1-darrellpruittIf you have not yet noticed, the future doesn’t look good for the dental profession as we know it.

Like far too many neighborhood primary care physicians who can no longer make a profit on their own, managed care is having its way with dentists as well.

Unfortunately, our patients remain clueless about downsides to discounted care sold by huge, insensitive corporations manned by executives who cannot be held accountable for their favorite providers’ level of care.

Since as a dentist I am somewhat transparent anyway, I would like to share some feelings with friends about an awkward subject that is on the minds of more dentists than one might expect, yet (almost) none feel comfortable revealing it: Regardless of the public’s perception of dentists’ wealth for the last few decades, it does not look like the anticipated economic recovery is likely to include the small dental practice down the street.

Schadenfreud

Not unlike Schadenfreude, I am certain at least some of dentistry’s disappointed customers may find this news addictingly pleasing to savor – up until one needs a dentist for a problem that cannot be handled safely by their designated dental therapist preferred by insurance MBAs.

I watch the dental news closer than most dentists, and sadly, my studied predictions have always proven to be very accurate, even if unpopular. Today I confidently predict that the profitability most dentists enjoyed for decades will not return for years – perhaps a decade or more.

On the other hand, as it becomes increasingly difficult to find dentists who allow time for gentle injections, patients should expect to pay them better than most. When an imbalance in the free market becomes unsustainable by artificial means such as managed care’s pay-for-performance algorithms, this is the way competition regulates quality in a natural way.

Personally, I’ve dealt with the downturn by working part time as an associate of another practice to make ends meet, and I feel fortunate to have found such a wonderful opportunity with a wonderful, patient-centered team. Marci, my wife, seems to be happier as well.

Assessment

Sorry if today’s news was a bummer, Doc. Maybe it is time others spoke up as well. Our leaders’ obvious lack of interaction on the internet exposes a tremendous vacuum, and they are incapable of rescuing the profession with silence… and neither will rushed therapists in huge dental clinics.

It’s up to you and me, Doctor. Come on out. The air is fine.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Will Future Doctors Need a Medical License?

Join Our Mailing List 

Licensing Doctors – Do Economists Agree?

By Dr. David Edward Marcinko MBA CMP™

[Editor-in-Chief]

Dr. MarcinkoChallenging conventional wisdom is something I like to think … that I do.

After all, I am considered a healthcare ‘thought-leader”, and to the extent possible, we publish outside traditional box thinking on this Medical Executive-Post.

It’s all Relative

But, I am a piker compared to Shirley Svorny PhD.

Who is she?

Dr. Shirley Svorny is chair of the economics department at California State University, Northridge, and she holds a PhD in economics from UCLA

Medical Licensure Issues

Now, remember the old saying, “if everyone is thinking alike, then nobody is thinking”.

Well, a while back, Dr. Svorny wondered if a medical degree is a barrier – rather than enabler – of affordable healthcare. Enter the PP-ACA of 2010.

As an expert on the regulation of health care professionals, including medical professional licensing, she has participated in health policy summits organized by Cato and the Texas Public Policy Foundation. She argued that licensure not only fails to protect consumers from incompetent physicians, but, by raising barriers to entry, makes health care more expensive and less accessible.

Institutional oversight and a sophisticated network of private accrediting and certification organizations, all motivated by the need to protect reputations and avoid legal liability, offer whatever consumer protections exist today. Malpractice attorneys, and monetary gain motives, too!

Her Published Abstract

“Despite the wide reach of medical licensing in health care production through its impact on the nature and cost of care, it has been all but ignored in debates over health care reform.

This paper pulls together statements made by economists whose expertise is in the area of health economics or, more specifically, medical licensure and discipline. Economists who have examined the market for physician services in the United States generally view state licensing as a means by which to enforce cartel-like restrictions on entry that benefit physicians at the expense of consumers. Medical licensing is seen as a constraint on the efficient combination of inputs, a drag on innovations in health care and medical education, and a significant barrier to effective, cost efficient health care.”

Full paper link:  2004-08-svorny-reach_concl

jester_hat

Am I Thought-Leader?

Am I a thought leader? Well, I don’t rightly know; that’s for others to decide. But, I do know that this essay was published a decade ago; in 2004, and at a time before the ME-P’s existence.

And so, based on this essay, Dr. Svorny is surely a “thought-leader” in my opinion

More about Dr. Svorny

In 1986-87, Dr. Svorny managed an industry risk group at Security Pacific Bank. She was a Milken Institute Affiliated Scholar and served as director of the San Fernando Valley Economic Research Center at Cal State Northridge. She has published articles in Economics of Education Review, Contemporary Economic Policy, Urban Affairs Review, Public Choice, Regional Science and Urban Economics, Cato Journal, Applied Economics, The Journal of Medical Licensure and Discipline, The Energy Journal, Economic Inquiry, and the Journal of Labor Research. Her opinion articles have appeared in the Los Angeles Times and the Los Angeles Daily News. Her research interests are in the areas of urban, labor, and health economics.

Assessment

Do traditionalists or collective healthcare reform advocates and health economists react rationally; or irrationally on this issue? What do you think?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

***

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Understanding the Impact of Regulations, Laws, and Healthcare Reform

Join Our Mailing List 

Consequences of the Accountable Care Act [PP-ACA]

By Dr. David Edward Marcinko MBA CMP

[Editor-in-Chief]

Dr David E Marcinko MBAThere is a fair amount of activity that will take place in the next 24 months in response to ICD-10 transition, healthcare reform, Accountable Care Act (ACA), meaningful use compliance and its financial incentives, and other regulatory issues that will require system or software upgrades to support the new efforts.

Some ACA Examples

As an example, The Affordable Care Act is sure to significantly alter reimbursement structures and delivery of care.

Below are several areas that will be affected:

  •  With the projected increase in patient volumes, the associated cost of about 62% will emanate from Medicare cuts: $162 Billion through reducing fee-for-service Medicare payments; $136 Billion from setting Medicare Advantage rates based on Fee-for-Service payments; and $36 Billion from cutting hospital Medicare/Medicaid disproportionate share.
  • Compliance reviews will be increased through the Recovery Audit Contractors (RACs) where Centers for Medicare and Medicaid Services (CMS) expect to obtain $2.9 Billion in additional savings. With the RAC in place, hospitals and providers need to increase their focus and attention in improving documentation quality and validating medical necessity to substantiate their reviews.
  • Reduced payments for readmissions and Medicare penalties for poor outcomes can and will affect the bottom line for both hospitals and providers in the future.
  • By 2015, more than 19 million uninsured will receive coverage and in 2016, another 11 Million uninsured will be insured.  This will create more patients per hospital/provider and will require more full-time equivalents to support the revenue cycle process of registration, documentation, billing and collection.
  • With the ICD-10 conversion will create a more complex requirement for documenting diagnoses and will require software modifications for hospitals and providers as well as significant training.

###

Product Details

[Our Forthcoming Book]

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Events Planner: June 2013

Join Our Mailing List

ADVERTISEMENT

Events-Planner: JUNE 2013

By Staff Writers
Calendar Calculator“Keeping track of important health economics and financial industry meetings, conferences and summits”

Welcome to this issue of the Medical Executive-Post and our Events-Planner. It contains the latest information on conferences, news, and relevant resources in healthcare finance, economics, research and development, business management, pharmaceutical pricing, and physician/entity reimbursement!  Watch for a new Events-Planner each month.

First, a little about us! The Medical Executive-Post is still a relative newcomer. But today, we have almost 175,000 visitors and readers each month from all over the country, in addition to our growing subscriber base. We have been a successful collaborative effort, thanks to your contributions.  As a result, we are adding new resources daily. And, we hope the website continues to provide the best place to go for journals, books, conferences, educational resources, tools, and other things you need to establish the value your healthcare consulting and financial advisory intervention.

So, enjoy the Medical Executive-Post and this monthly Events-Planner with our compliments.

A Look Ahead this Month – And now, the important dates:

  • June 16-19: HFMA Institute Meeting. Orlando, FLA
  • June 25-27: AHA Health Forum Summit. San Diego, CA.

MarcinkoAdvisors@msn.com

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest E-Ps delivered to your email box each morning? Just subscribe using the link below. It’s free. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos


Product DetailsProduct Details

Does the U.S. Supreme Court decision resolve the gene-patenting issue?

Join Our Mailing List

Human Genes are NOT Patentable

By Karen Matthias RN MBA

[Vice-President of Marketing]

Hayes, Inc kmatthias@hayesinc.com

Yesterday, the U.S. Supreme Court unanimously agreed that human genes are not patentable, making a distinction between “natural” DNA found in the human body and the laboratory-created “synthetic” DNA. This opinion reinforces those of many in the genetics community who have argued for years that genes are products of nature rather than inventions.

A Resolution?

But, does the Supreme Court decision completely resolve the gene-patenting issue?

Dr. Diane Allingham-Hawkins, Senior Director, Genetic Test Evaluation Program and Technical Editing at Hayes, Inc., doesn’t think so.

“The Justices compromised somewhat in their decision that while human genes as they exist in nature were ruled not patentable, the opinion allowed that synthetic copies – so-called complementary DNA or cDNA – may be”.

The Court did not rule, however, that cDNA meets all requirements of patent eligibility, just that cDNA would not be considered a ’product of nature’.

Issues Not Addressed

In addition, Dr. Allingham-Hawkins points out what the decision does not address.

“Notably, the opinion clearly stated that it was not ruling on any methods patents related to the two genes or on any applications regarding what Myriad had learned about the genes, leaving the door open for narrower genetic testing patents.

Nevertheless, this is a major victory for the plaintiffs in the case and for patients, who will now have choices related to who performs their genetic testing and options to seek second opinions from independent laboratories.”

###

US supreme court building

More 

Our new white paper on the history of gene patenting in the United States can be an excellent resource as you search for background information on this topic.

Download a complimentary copy here:  http://www.hayesinc.com/hayes/resource-center/white-papers/gene-patenting-in-the-united-states/.

Assessment  

Thanks for considering.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Possible Causes of The Military Suicide Epidemic

Join Our Mailing List

Erosion of Protective Factors

By Roy Miller roydotmiller@gmail.com

Hey Dr. Marcinko,

I’m one of the guys that reads you day by day. I come from a family with a military tradition, but unfortunately I couldn’t follow this path due to an eye problem. Instead, I became very passionate about army related stuff and I tend to bookmark and save as much material I can find.

I just came across this worrying material about suicide in the army and I’d like to share it with you, maybe you’ll find it interesting:

It’s quite a huge problem that unfortunately hasn’t made it on the public agenda and it’s continuously ignored, so I’m trying to create some buzz around it.

There are 3 protective factors to prevent suicide:

1. Belongingness:

The cohesion and camaraderie of a military unit can induce intense feelings of belonging for many service members. Time away from the unit, however, may result in a reduced or thwarted sense of belonging, as individuals no longer have the daily support of their units and feel separate and different from civilians. This is especially true for Guardsmen and Reservists.

2. Usefulness:

The responsibility inherent in military service, the importance of tasks assigned to relatively junior personnel and the high level of interaction among unit members establish the importance and usefulness of each unit member, particularly in an operational environment. In contrast, the experience of living in a garrison environment (for active component personnel) or returning to a civilian job (for Guardsmen, Reservists and veterans) or, worse, unemployment, can introduce feelings of uselessness.

3. Aversion to pain or death

Repeated exposure to military training as well as to violence, aggression and death dulls one’s fear of death and increases tolerance for pain. Thus, the very experience of being in the military erodes this protective factor, even for service members who have not deployed or experienced combat, in part because service members experience pain and discomfort from the beginning of their training.

military-suicide

Erosion of moral certainty

Moral injury: “damage to your deeply held beliefs about right and wrong. It might be caused by something that you do or fail to do, or by something that is done to you – but either way it breaks that sense of moral certainty.”

• Failing to protect their ‘brothers’
• Friendly fire
• Deaths of civilians, particularly women and children
• Discharged from the military

Assessment

It is not the fear and the terror that service members endure in the battlefield that inflicts most psychological damage, but feelings of shame and guilt related to the moral injuries they suffer.

Sources:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Contribute to the Medical Executive-Post and Tell Us What You Think

Join Our Mailing List

Call for Guest Medical Executive-Posts!

By Ann Miller RN MHA

[Executive-Director]

MarcinkoAdvisors@msn.com

ME-P

Now that we’ve wrapped up our newest textbook, we thought it would be fun to keep everybody writing to share your best posts and comments with our ever-growing online community.

###

We’re open to all kinds of related subjects on the business of medical practice, healthcare economics and finance, HIT and personal financial planning and investing for doctors and all medical professionals.

###

So, if you’d like to comment or be a featured guest on our blog, or know of a great post we should feature or re-print, just let us know by emailing me! BROADCAST yourself.

Product Details

www.CertifiedMedicalPlanner.org

###

On the “Selling Points” for Whole-Life and Universal-Life Insurance

Join Our Mailing List 

De-Bunking Conventional Sale Wisdom

By Rick Kahler MS CFP® ChFC CCIM http://www.KahlerFinancial.com

Rick Kahler CFP“You need to protect yourself and your family with life insurance that you won’t outlive.”

This is one of the common selling points for whole life or universal life rather than term life insurance. At first glance, it seems to make a lot of sense. Of course you don’t want to outlive your life insurance. Having it pay benefits upon your death is the reason you buy it.

This statement, however, misses one essential fact. Many people don’t need to worry about outliving their life insurance, because they outlive their need for life insurance.

Outliving the Need

We don’t all need life insurance throughout our entire lives, any more than we do auto or homeowners’ insurance. If you no longer drive a car, you don’t need auto insurance. If you no longer own a home, you don’t need homeowners’ insurance.

For example, in circumstances like the following, you may no longer need life insurance:

  • First;  when you and your spouse have accumulated enough assets and income streams to independently care for yourselves.
  • Second;  when your children are self-sufficient adults.
  • Third;  when your estate is too small to owe estate taxes or liquid enough to pay the estate taxes.

Primary Purpose

The primary purpose of life insurance is to replace the future income of a primary breadwinner. Two groups most likely to need it are middle-aged couples saving for retirement and parents of minor children. Ideally, most young families should have over $-1 million in life insurance to provide for the children if either parent should die prematurely.

Yet many of them are unable to afford the higher premiums for this much “permanent” insurance. Their choices are to underfund their needs with a smaller permanent policy or purchase an affordable 30-year term policy.

As we age, the probability of dying becomes greater. Therefore, a $1 million life policy costs much less for a 25-year-old than a 75-year-old. It doesn’t matter if the policy is cash value, whole life, universal life, or level term, the cost of providing the life insurance component increases every year.

Psychological Aversions

Yet most human brains have a psychological aversion to price increases. In order to please their customers with life insurance premiums that didn’t increase every year, insurance companies came out with level term policies. Essentially, the premiums are averaged out by overcharging in the early years of the policy and undercharging in the later years.

insurance

Higher  Premiums

Whole life and universal life insurance policies don’t have that same averaging. To be “permanent,” the premiums must be much higher in order to fund a savings account that grows over time and is often used to offset a significant portion of the death benefit in the later years of the insured’s life. Usually, if the insured cancels the policy, a portion of the premiums will be refunded.

Cash Value

A cash value policy may occasionally be a good estate planning tool, generally for those with substantial wealth. It might be used to fund an irrevocable life insurance trust upon the second spouse’s death, perhaps to pay taxes on an illiquid estate like a family farm or other property. It also can be used for those wanting to leave the bulk of an estate to charity and still provide income to their children. These strategies rarely apply to those whose primary goal is basic income replacement for their families.

Assessment

One of the ironies of insurance in general is that we all know it’s essential and we all hope never to need it. For most people, life insurance is not really an exception to this. Its primary purpose is not to provide us with investment income, but to provide our families with income if we aren’t there.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™
Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Celebrating “National Get Outdoors Day”

Join Our Mailing List

National Get Outdoors Day is June 8th, 2013

By Staff Reporters

National Get Outdoors Day is a new annual event to encourage healthy, active outdoor fun.

Participating partners will offer opportunities for American families to experience traditional and non-traditional types of outdoor activities.

Prime goals of the day are reaching first-time visitors to public lands and reconnecting our citizens and youth to the great outdoors.

###

get_outdoors

Assessment

So, leave the couch behind today.

More: www.NationalGetOutdoorsday.org

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Are Doctors Bad Investors?

Join Our Mailing List

A Longboard Assessment Management Study for Lay Investors

###

stock_investing_cashsherpa-812x1024

Assessment

And so, are doctors and other medical professionals really bad investors?

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Physician-Investors and the “F” Word

Join Our Mailing List

“Fiduciary”

By Rick Kahler MS CFP® ChFC CCIM http://www.KahlerFinancial.com

Rick Kahler CFPOkay, I did it again in a recent column. And, I got into trouble again. That’s what I get for using the F-word.

Mea Culpa

My most recent transgression was to point out the simple fact that insurance agents are compensated by commissions on the products they sell. They have no fiduciary duty to legally act in the best interests of their customers.

Every time I remind readers that sellers of financial products do not have a fiduciary duty to their customers, I get indignant responses from financial salespeople who seem to think I have accused them of being unethical.

Ethics

Not so. Someone who sells financial products may well operate with integrity. In fact, their licenses typically require that they be “fair” and “honest.” These salespeople may care about their customers and be committed to selling only products that they believe will meet their customers’ needs.

But being a fair, honest, and ethical salesperson is not the same thing as having a legal fiduciary duty to the consumer. The word “fiduciary” has a specific meaning in our legal system. It describes those in positions of trust or authority who are required by law to act in the best interests of those they represent. A fiduciary is an advocate for the consumer, who is legally termed a “client.”

Of Doctors and Attorneys

Doctors and attorneys have fiduciary relationships with their patients and clients. The executor of an estate is a fiduciary. So is a trustee, someone acting under a power of attorney, or an agent hired to represent you. Real estate agents can be fiduciaries if they are engaged to represent either buyers or sellers.

Financial planners can also be fiduciaries. Yet those who offer financial advice and services in conjunction with the sale of a financial product are not fiduciaries.

Fiuduciary

Follow the Money

How can you generally tell whether a financial professional is required by law to act in your best interests? Simple. You follow the money. Wherever the professional’s compensation comes from is most likely where the fiduciary responsibility goes.

If you hire a fee-only financial planner, you are directly paying that person for professional advice and services. The planner receives his or her income from you and others like you. You are clients, not customers, and the planner is legally obligated to act on your behalf.

This is not the case if you buy financial investment products or receive financial advice from someone who is compensated by commissions. It doesn’t matter whether this person’s business card says “financial consultant,” “financial planner,” “investment advisor,” or “broker.” Anyone can use those terms.

Commission Sales

But, if someone is paid by commissions from financial companies, he or she is a sales representative whose fiduciary responsibility is to those companies. They may call you their “client,” but in the legal sense, you are not. You are a customer who buys products from a salesperson. Just like those who sell cars, groceries, or shoes, these salespeople owe their primary loyalty to their employers. They are obliged to operate in the best interests of themselves and their companies.

This relationship has a built-in conflict of interest. Because financial salespeople make most of their money from commissions, their recommendations to customers are usually biased toward investments that will be the most profitable for themselves. Their legal responsibilities are to act fairly and honestly. Most either don’t or won’t disclose the amounts and sources of their commissions

More:

Assessment

A financial salesperson who is not a fiduciary certainly can act with integrity. I know many who do. That means they are honest people who want to thrive in business by selling legitimate products in a responsible and ethical way. It does not, however, make them fiduciaries.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Understanding the Spoils of Healthcare Fraud and Abuse

Self Explanatory – Need we say more?

By ME-P Staff Writers

###

Picture1

[Click on image to enlarge]

###

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details

Product DetailsProduct Details

How Volatile Is the Stock Market Today?

Join Our Mailing List

And … Is it Dangerous?

By Lon Jefferies CFP® MBA www.NetWorthAdvice.com

Lon JefferiesBased on conversations with physician and clients, I’d suggest that most investors view the market of the new millennium as more volatile and fragile than it’s been in the past.

JUNE 4, 2013

DOW 15,253.7 +138.1
NASDAQ 3,465.49 +9.58
S&P 1,640.61 +9.87

New concerns that could affect a portfolio are seemingly always coming to light – think of the near-financial collapse of the U.S. economy during the last recession, the U.S. debt downgrade, the potential bailout crises in Europe and the possible devaluation of the euro, domestic unemployment concerns, and the perennial concern about the inflation/deflation of the dollar.

Add to this the idea that the world has become a more unstable place and the reality that supercomputers make thousands of trades every second.

How Valid Are the Concerns?

To determine the validity of these perceptions, Allan Roth analyzed the performance of the Wilshire 5000 (an index of the market value of all stocks actively traded in the United States) since 1980 in the May edition of Financial Planning Magazine. Surprisingly, Mr. Roth found that market swings of more than 30% weren’t much more common during the past 10 years than they were from 1980-2002. In fact, on a monthly basis, market swings of more than 10% actually occur less these days than in the past.

On a daily basis, the mean standard deviation of returns (a measure of volatility) over the entire 32-year period was 1.01%. In other words, during 68% of trading days, the index increased or decreased by less than 1.01%. Further, on 95% of trading days the index went up or down by no more than 2.02% (or two standard deviations). While daily standard deviation hit a record in 2008 of more than 2.5%, last year actually had lower volatility than the overall average. Consequently, while volatility hit a high in 2008, it has been at a very normal level since.

###

Stock_Market

###

Why the Perceptions?

So why do investors perceive more uncertainty in today’s environment? Mr. Roth mentions a few hypotheses:

  • Magnitude Effect – To suffer a 2.5% decrease in 1972, the S&P 500 would have needed to decrease by 2.54 points. To endure a 2.5% decrease today, the index would need to decrease by 41.25 points. Although both represent the same investment loss, we perceive the double digit point swing as larger and more dramatic.
  • Availability Bias – Humans overestimate the probability of events associated with memorable or vivid occurrences. Memorable events are further magnified by excessive coverage in the media.  Because the market crash of 2008 was so remarkable, investors tend to overestimate the probability of a similar crash and underestimate the probability of market appreciation, which historical data says is significantly more likely.
  • Access to Information – Jason Zweig, a columnist for the Wall Street Journal, says “today between websites, Facebook, Twitter, the TV and smart phones, an investor couldn’t escape knowing about a big move in the stock market if he or she tried. Whatever you pay attention to, while you are attending to it, will always seem more significant than it really is.”
  • Simple Fear and Pessimism – Meir Statman, a finance professor at Santa Clara University, suggests “people who think the U.S. is in decline view investing as riskier now than in the past, when they believe the country was better off, and no amount of data showing actual volatility would change their minds.” Similarly, Daniel Kahneman, a Nobel laureate and Princeton professor suggests “people always think the present is more volatile than the past. Because we know that historic crises have resolved themselves, we may simply remember the past as being less volatile than we viewed it at the time.”

More:

Assessment

It’s likely beneficial for physicians and all investors to evaluate their behavior and determine if they exhibit any of these biases. History tells us that the most dominate factor leading to investment success is to keep your asset allocation steady. Being aware of tendencies that might encourage us to make rash investment decisions could save us a lot of stress during critical market movements.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product DetailsProduct Details

The Chiropractic Fad?

Join Our Mailing List

Now those hieroglyphics make sense!

By Anthony Narushka DC945457_573594136020162_1396079168_nAssessment

Chiropractic, it’s no fad!

Polish Chiropractic Association

New PCA BOD Members

[2009 Polish Chiropractic Association  BOD Members]

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

What Physician-Investors Need to Know about the Shiller PE Ratio

Join Our Mailing List 

What it is – How it works

By Michael Zhuang MS www.MZCap.com

This Shiller PE index is a stock market metric invented by Yale University Professor Robert Shiller, PhD.

Basically, it is the average PE ratio of all S&P 500 stocks for the last ten years. The Shiller PE is also called PE10. Professor Shiller found it to be a reasonably good measure of valuation of the whole market.

IOW: The higher the Shiller PE, the more expensive the market. So, with Shiller PE at 24, we can call this market relatively expensive.

Assessment

Here is what I know currently.

  1. The  higher the Shiller PE – the lower the one-year and three-year return propensity.
  2. Return variability is so high as to render the Shiller PE’s predictive power very weak.
  3. Only when Shiller PE is over 35 are the three-year forward returns overwhelmingly negative.

So, the market may or may not be headed for a fall immediately, but we do need to temper our expectation of future returns.

About the Author

Michael Zhuang is founder and principal of MZ Capital, a fee-only registered investment advisor firm located in the Greater Washington D.C. metropolitan area.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Cell Phone Usage In Car Crashes Massively Underreported

Join Our Mailing List

Are You Guilty – Doctor?

[An NSC Infographic]

COM-Cell-Phone-Crash-Underreporting

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Are Doctors NOW Members of the Middle Class?

In OR Out?

By Dr. David Edward Marcinko MBA CMP®

By Rick Kahler MS CFP® ChFC CCIM

Rick Kahler CFPThe middle class Marketers target it. Politicians champion it. Economists talk about it. Most of us consider ourselves part of it. FAs want to serve it.

Yet, when I’ve asked for a clear definition, I have not found anybody yet that really can tell me what “middle class” is.

Definition

I recently posted on Twitter that $90,000 was a middle-class household income and that it would take a nest egg of $3 million to generate that income in retirement.

A couple of my colleagues responded that my figures were way too high and accused me of being out of touch. As a lifelong South Dakotan, I’m used to being seen as “out of touch,” but the idea that $90,000 was beyond a middle-class income intrigued me.

I figured a few minutes with Google would point me to a definition of “middle class.” It wasn’t that simple. I soon discovered that neither politicians, nor economists, sociologists, nor financial advisors can agree on what makes someone middle class. It is a little easier to define a middle class income.

USA Today

I did find an excellent article in USA Today by Dan Horn of the Cincinnati Inquirer. He cited three surveys that attempted to define the middle class by income. The Pew Charitable Trust describes it as the middle 20%, an income range from $32,900 to $64,000. The U.S. Census Bureau disagrees.

They say a middle class income is the middle 60%, an income range of $20,600 to $102,000. The U.S. Department of Commerce begs to differ with both and says an income between $50,800 and $122,000 puts you in the middle class. Combining the income range of the three studies ($20,600 to $122,000) puts two-thirds of all income earners in the middle class.

My Personal POV

For me, defining middle class with such a broad income range just raises more questions than it answers.

First of all, the same income that will provide a comfortable middle-class lifestyle in a place like the Black Hills of South Dakota won’t necessarily do the same in San Francisco or Boston.

Second, if you want to assure yourself of a middle-class income throughout your lifetime, you apparently have to get rich.

Concept of expensive education - dollars and diploma

Case Model

Let’s assume a young couple, both allied healthcare professionals, earn $45,000 each for a household income of $90,000. Let’s assume they want to save enough to provide a similar income in retirement without counting on Social Security. To generate that income, with a 99% certainty they will never run out of money, how much will they need to save?

While financial advisors’ responses will vary, most will agree this couple would need between $2 million and $4 million in today’s dollars. Let’s settle on $3 million. If they each saved $1,000 monthly to 401k’s (about 25% of their salaries), our young couple could save $6,600,000 million ($3 million in today’s dollars adjusted for inflation) by the time they reached age 65.

However, while a couple needs $3 million to produce a middle-class income, someone with a net worth of $3 million is in the financial top 2% of Americans. That’s hardly middle class.

And to complicate things further, Gallup polls have shown that most Americans think anyone with a net worth of $1 million is rich. Yet having $1 million when you retire will generate a secure lifetime income of $30,000. So the net worth that we define as wealthy provides an income that we define as barely middle class.

More:

Assessment

Confused yet? I certainly am. There’s just one thing I’m still sure of. If you want a middle-class lifestyle after you retire, what you’d better do now is live a modest middle-class lifestyle so you can save enough to qualify as rich.

Conclusion

And so, are doctors members of the middle class – in potential retirement income under this model? Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Product DetailsProduct Details

A Hospital Industry Outlook for 2013

Join Our Mailing List

One Expert’s Opinion

By Ann Miller RN MHA

[Managing Editor]

The ME-P and nation recently celebrated National Hospital Week for 2013. And so, what better time than now to ask health economist and financial expert Robert James Cimasi MHA, ASA, AVA, CMP for his take on the industry outlook. www.HealthCapital.com

cimasiHistory Background and Overview

The U.S. Healthcare Delivery System is facing what is perhaps its greatest challenge in the expected demand for increased health services from the aging of the “baby-boom” generation, the fastest-growing segment of the population.

The enactment of healthcare reform in March 2010, requiring increased insurance coverage requirements for individuals and employers, will also increase patient demand for hospital inpatient and outpatient services in the coming years.

Hospital Industry 

The hospital industry continues to face many challenges in the changing healthcare environment, including workforce shortages, rising healthcare costs to provide care, and difficulty acquiring needed capital. With consistent financial stresses, hospitals in some areas appear to be struggling.

However, general acute-care hospitals recorded record high profits of $35.2 billion in 2006, an increase of over 20% from 2005.  Total net revenues for general acute-care hospitals were $587.1 billion, resulting in an average profit margin of 6% (the highest since 1997, when the average profit margin was 6.7%).

While the demand for healthcare continues to rise, the site of service also continues to evolve as more procedures are performed on an outpatient basis and by freestanding facilities rather than by inpatient acute care hospitals.  As evidence of this trend, the number of freestanding ambulatory care surgery centers increased from 2,864 in 2000 to 5,197 in 2006.

U.S. healthcare costs are again increasing after their rate of growth slowed in the mid-1990s.

In 2009, total national health expenditures (NHE) in the U.S. grew to $2.5 trillion, a 5.7% increase from 2008.  Meanwhile, the nation’s gross domestic product (GDP) shrank by 1.1%, and as a result, NHE increased from 16.2% to 17.3% of the GDP: the largest one-year increase-in history. Additionally, healthcare spending has been projected to grow to 19.6% by 2016. The potential impact of the 2010 healthcare reform legislation to reduce rising healthcare expenditures is yet uncertain.

According to a 2002 study conducted by the Blue Cross and Blue Shield Association (BCBSA), inpatient costs are responsive to hospital market organization.  Each 1% increase in for-profit hospital market share is associated with a 2% increase in inpatient expenditure per person.  Conversely, each 1% increase in network hospital market share corresponds to a 1% decrease in inpatient expenditures.

Risk Sharing

As healthcare costs again continue to rise faster than inflation in the overall economy in 2013, driven by advances in technology and treatment (as well as the growing baby-boomer population), pressures to reduce costs, such as those included in the ACA will result in a changed paradigm for healthcare delivery.

Reimbursement mechanisms are increasingly designed to control costs and access, and hospitals must continually adjust to deal with increasing pressure to contain reimbursement and utilization levels; ie., share financial risks.

The Marketplace

The healthcare marketplace continues to experience dramatic change as the business of healthcare becomes increasingly competitive, particularly in the outpatient ancillary services arena.  Providers and payors continue to seek to control costs and markets. Legal and regulatory issues also affect change as providers adapt to new opportunities and restrictions.

In particular, there are a wide variety of cost, operational, and regulatory pressures impacting the specialty and surgical hospital industry.

Of course, these pressures are offset by the stable and increasing demand for hospital services, particularly for those hospitals already in operation.

national-hospital-week

Assessment

Bob feels that hospitals that are operationally efficient will continue to be successful within this environment; others will not. How about you?

More: Financial Management Strategies for Hospitals and Healthcare Organizations : Tools, Techniques, Checklists and Case Studies

More: Arkansas Medical News Interviews Dr. Marcinko

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details

Doubting the Accountable Care Organization B-Model

New Healthcare Business Model or Edsel Model?

Join Our Mailing List 

By David Edward Marcinko MBA http://www.CertifiedMedicalPlanner.org

[Publisher-in-Chief]

Dr. Marcinko with ME-P FansDefined by Professor Michael Porter at Harvard Business School, value is defined as a function of outcomes and costs. Therefore to achieve high value we must deliver the best possible outcomes in the most efficient way, outcomes which matter from the perspective of the individual receiving healthcare and not provider process measures or targets.

Sir Muir Gray expanded on the idea of technical value (outcomes/costs) to specifically describe ‘personal value’ and ‘allocative value’, encouraging us to focus also on shared decision making, individual preferences for care and ensuring that resources are allocated for maximum value.

Healthcare Value and ACOs

According to our Medical Executive-Post Health Dictionary Series of administrative terms http://www.HealthDictionarySeries.org  and health economist and colleague Robert James Cimasi MHA, ASA, AVA CMP™ of www.HealthCapital.com; an ACO is a healthcare organization in which a set of providers, usually large physician groups and hospitals, are held accountable for the cost and quality of care delivered to a specific local population.

ACOs aim to affect provider’s patient expenditures and outcomes by integrating clinical and administrative departments to coordinate care and share financial risk.

ACO Launch

Since their four-page introduction in the PP-ACA of 2010, ACOs have been implemented in both the Federal and commercial healthcare markets, with 32 Pioneer ACOs selected (on December 19, 2011), 116 Federal applications accepted (on April 10, 2012 and July 9, 2012), and at least 160 or more Commercial ACOs in existence today.

Federal Contracts

Federal ACO contracts are established between an ACO and CMS, and are regulated under the CMS Medicare Shared Savings Program (MSSP) Final Rule, published November 2, 2011.  ACOs participating in the MSSP are accountable for the health outcomes, represented by 33 quality metrics, and Medicare beneficiary expenditures of a prospectively assigned population of Medicare beneficiaries.

If a Federal ACO achieves Medicare beneficiary expenditures below a CMS established benchmark (and meets quality targets), they are eligible to receive a portion of the achieved Medicare beneficiary expenditure savings, in the form of a shared savings payment.

Commercial Contracts

Commercial ACO contracts are not limited by any specific legislation, only by the contract between the ACO and a commercial payor.

In addition to shared savings models, Commercial ACOs may incentivize lower costs and improved patient outcomes through reimbursement models that share risk between the payor and the providers, i.e., pay for performance compensation arrangements and/or partial to full capitation.

Although commercial ACOs experience a greater degree of flexibility in their structure and reimbursement, the principals for success for both Federal ACOs and Commercial ACOs are similar.

###

Eidsel

Dr. David E. Marcinko with 1960 Ford Edsel

[© iMBA, Inc. All rights reserved, USA.]

[The Edsel was an automobile marque that was planned, developed, and manufactured by the Ford Motor Company during the 1958, 1959, and 1960 model years. With the Edsel, Ford had expected to make significant inroads into the market share of both General Motors and Chrysler and close the gap between itself and GM in the domestic American automotive market. But, contrary to Ford’s internal plans and projections, the Edsel never gained popularity with contemporary American car buyers and sold poorly. The Ford Motor Company lost millions of dollars on the Edsel’s development, manufacturing and marketing].

More:


Update

Junking the Merit-Based Incentive Payment System (MIPS) would undoubtedly let the proverbial air out of the MACRA balloon, dealing a significant blow to the value-based reimbursement shift; right?

Assessment

Although nearly any healthcare enterprise can integrate and become an ACO, larger enterprises, may be best suited for ACO status.

Larger organizations are more able to accommodate the significant capital requirements of ACO development, implementation, and operation (e.g., healthcare information technology), and sustain the sufficient number of beneficiaries to have a significant impact on quality and cost metrics.

Conclusion

But, will this new B-Model work? Isn’t leading doctors in a shared collaborative effort a bit like herding cats? And, what about patients, HIEs, outcomes management, data analytics and … Population Health via our colleague David B. Nash MD MBA of Thomas Jefferson University, often considered the “father” of Pop Health?

OR, what about the developing IRS scandal and full PP-ACA launch in 2014? Will it affect federal funding, full roll-out, or even repeal of the entire Act?

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Purchase ME-P Textbooks, Handbooks and Dictionaries to Thrive

 Our Library is Growing … thanks to you

Join Our Mailing List

By Ann Miller RN MHA

[ME-P Executive-Director]

We have been publishing the Medical Executive-Post for more than eight years now. And, with almost 3,000 formal posts, by the nation’s brightest experts, we have a treasure trove of information available to you.

So now, for the first time, all this information – and more – has been codified, updated, copy-righted and copy-protected in print form for your purchase and use. All have been edited by our Publisher – Dr. David Edward Marcinko and Professor Hope Rachel Hetico.

Just click on an image below to order.

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Assessment

Purchase our white papers, too: https://medicalexecutivepost.com/white-papers/

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Business%20Optimization

Finding Emotional Freedom [Access the Truth Your Brain Already Knows]

Join Our Mailing List

Book Review

By Rick Kahler MS CFP® ChFC CCIM http://www.KahlerFinancial.com

Rick Kahler CFP“It’s not about the money.” This saying has become almost a cliché among financial planners and therapists who help clients address the emotional aspects of their relationships with money.

We keep using this phrase because it is so true. Overspending, taking unreasonable risks, money conflicts that strain marriages, failing to learn from money mistakes, and a host of other problematic money patterns are not about money. They are about emotions. And since brain researchers tell us that 90% of all decisions are made emotionally, it literally “pays” to pay attention to your emotions.

Because money affects so many aspects of our lives, it’s only natural that destructive behavior around money is one of the ways people try to cope with emotional pain. Money dysfunction is really no different from other destructive behaviors like addiction or codependency. Like them, it can have high physical, emotional, relationship, and financial costs.

The more I learn about the relationship between our emotions and our money choices, the more I understand why financial knowledge alone isn’t enough to help people change unhelpful behaviors that keep them stuck. I am convinced of the value of financial therapy and other forms of counseling to help people create financial and emotional balance in their lives. It’s clear to me that psychotherapy offers clear financial benefits as well as emotional ones.

The Book

A new book by Dave Jetson, Finding Emotional Freedom: Access the Truth Your Brain Already Knows, addresses these issues in one of the more clear and succinct manners I’ve encountered.

Dave is one of the few counselors in the nation who understands and practices financial therapy. In his practice and workshops, he uses experiential therapy techniques that access both the conscious and unconscious parts of the brain to help people recover from any type of abuse and trauma, including financial. I’ve seen first-hand how effective this work is.

I also know that Dave is one of those rare guides who’s actually done and succeeded at what he teaches. He is one of those who walks the walk. Now he has written a book describing that walk.

Finding Emotional Freedom includes a clear, readable description of how our brains process emotions. This is useful, even critical information for anyone who wants to make wiser money choices.

Finding Emotional Freedom: Access the Truth Your Brain Already

Co-Dependency

Dave also describes how codependency develops and some of the patterns it takes. Many of these patterns—from addictions, to shopping as “retail therapy,” to excessive taking care of others—have financial as well as emotional costs.

Even though Dave offers financial therapy and has created a workshop on Financial Recovery, he doesn’t specifically discuss financial codependency in this book. This doesn’t mean the issue is not important. In fact, it serves to underscore the principle that that many money issues really are not about the money.

Assessment

Finally, this book explains how experiential therapy works and the deep changes it can make. Finding Emotional Freedom shows the possibilities for not only healing emotional wounds, but for increasing your emotional intelligence. It’s a powerful book, and I highly recommend it.

When I was starting out as a financial planner 30 years ago, I wouldn’t necessarily have even picked up a book like this, much less have felt comfortable recommending it to clients. Now I know better.

What I have learned over those years is that real financial planning is about much more than just the money. Providing investment advice that helps people achieve financial health is certainly important. But the larger role of a financial planner is to help clients prosper. Real prosperity includes not only financial health, but also emotional health and happiness.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

How the IRS’s Nonprofit Division Got So Dysfunctional

Join Our Mailing List

The IRS Controversy

By Kim Barker and Justin Elliott

ProPublica, May 17, 2013, 5:14 p.m.

The IRS division responsible for flagging Tea Party groups has long been an agency afterthought, beset by mismanagement, financial constraints and an unwillingness to spell out just what it expects from social welfare nonprofits, former officials and experts say.

The controversy that erupted in the past week, leading to the ousting of the acting Internal Revenue Service commissioner, an investigation by the FBI, and congressional hearings that kicked off Friday, comes against a backdrop of dysfunction brewing for years.

Moves launched in the 1990s were designed to streamline the tax agency and make it more efficient. But they had unintended consequences for the IRS’s Exempt Organizations division.

Checks and balances once in place were taken away. Guidance frequently published by the IRS and closely read by tax lawyers and nonprofits disappeared. Even as political activity by social welfare nonprofits exploded [1] in recent election cycles, repeated requests for the IRS to clarify exactly what was permitted for the secretly funded groups were met, at least publicly, with silence.

All this combined to create an isolated office in Cincinnati, plagued by what an inspector general this week described [2] as “insufficient oversight,” of fewer than 200 low-level employees responsible for reviewing more than 60,000 nonprofit applications a year.

A Major Mistake

In the end, this contributed to what everyone from Republican lawmakers to the president says was a major mistake: The decision by the Ohio unit to flag for further review applications from groups with “Tea Party” and similar labels. This started around March 2010, with little pushback from Washington until the end of June 2011.

“It’s really no surprise that a number of these cases blew up on the IRS,” said Marcus Owens, who ran the Exempt Organizations division from 1990 to 2000. “They had eliminated the trip wires of 25 years.”

Of course, any number of structural fixes wouldn’t stop rogue employees with a partisan ax to grind. No one, including the IRS [3] and the inspector general [4], has presented evidence that political bias was a factor, although congressional and FBI investigators are taking another look.

But what is already clear is that the IRS once had a system in place to review how applications were being handled and to flag potentially problematic ones. The IRS also used to show its hand publicly, by publishing educational articles for agents, issuing many more rulings, and openly flagging which kind of nonprofit applications would get a more thorough review.

All of those checks and balances disappeared in recent years, largely the unforeseen result of an IRS restructuring in 1998, former officials and tax lawyers say.

“Until 2008, we had a dialogue, through various rulings and cases and the participation of various IRS officials at various ABA meetings, as to what is and what is not permissible campaign intervention,” said Gregory Colvin, the co-chair of the American Bar Association subcommittee that dealt with nonprofits, lobbying, and political intervention from 1991 to 2009.

“And there has been absolutely no willingness in the last five years by the IRS to engage in that discussion, at the same time the caseload has exploded at the IRS.”

IRS

Stone Walling

The IRS did not respond to requests for comment on this story.

Social welfare nonprofits, which operate under the 501(c)(4) section of the tax code, have always been a strange hybrid, a catchall category for nonprofits that don’t fall anywhere else. They can lobby. For decades, they have been allowed to advocate for the election or defeat of candidates, as long as that is not their primary purpose. They  also do not have to disclose their donors.

Social welfare nonprofits were only a small part of the exempt division’s work, considered minor when compared with charities. When the groups sought IRS recognition, the agency usually rubber-stamped them. Out of 24,196 applications for social welfare status between 1998 and 2009, the exempt organizations division rejected only 77, according to numbers compiled from annual IRS data books.

Into this loophole came the Supreme Court’s Citizens United decision in January 2010, which changed the campaign-finance game [5] by allowing corporate and union spending on elections.

Sensing an opportunity, some political consultants started creating social welfare nonprofits geared to political purposes. By 2012, more than $320 million in anonymous money poured into federal elections.

A couple of years earlier, beginning in 2010, the Cincinnati workers had flagged applications of tiny Tea Party groups, according to the inspector general, though the groups spent almost no money in federal elections.

Main Question

The main question raised by the audit is how the Cincinnati office and superiors in Washington could have gotten it so wrong. The audit shows no evidence that these workers even looked at records from the Federal Election Commission to vet much larger groups [6] that spent hundreds of thousands and even millions [7] in anonymous money to run election ads.

The IRS Exempt Organizations division, the watchdog for about 1.5 million nonprofits, has always had to deal with controversial groups. For decades, the division periodically listed red flags that would merit an application being sent to the IRS’s Washington, D.C., headquarters for review, said Owens, the former division head.

In the 1970s, that meant flagging all applications for primary and secondary schools in the south facing desegregation. In the 1980s, during the wave of consolidation in the health-care industry, all applications from health-care nonprofits needed to be sent to headquarters. The division’s different field offices had to send these applications up the chain.

“Back then, many more applications came to Washington to be worked — the idea was to have the most sensitive ones come to Washington,” said Paul Streckfus, a former IRS lawyer who screened applications at headquarters in the 1970s and founded the industry publication EO Tax Journal [8] in 1996.

Because this list was public, lawyers and nonprofits knew which cases would automatically be reviewed.

“We had a core of experts in tax law,” recalled Milton Cerny, who worked for the IRS, mainly in Exempt Organizations, from 1960 to 1987. “We had developed a broad group of tax experts to deal with these issues.”

In the 1980s, the division issued many more “revenue rulings” than issued in recent years, said Cerny, then head of the rulings process. These revenue rulings set precedents for the division. Revenue rulings along with regulations are basically the binding IRS rules for nonprofits.

“We would do a revenue ruling, so the public and agents would know,” Cerny said. “Over the years, it apparently was felt that a revenue ruling should only be published at an extraordinary time. So today you’re lucky if you get one a year. Sometimes it’s less than that. It’s amazing to me.”

Other checks and balances had existed too. Not only were certain kinds of applications publicly flagged, there was another mechanism called “post-review,” Owens said. Headquarters in Washington would pull a random sample every month from the different field offices, to see how applications were being reviewed. There was also a surprise “saturation review,” once a year, for each of the offices, where everything from a certain time period needed to be sent to Washington for another look.

So internally, the division had ways, if imperfect, to flag potential problems. It also had ways of letting the public know what exactly agents were looking at and how the division was approaching controversial topics.

For instance, there was the division’s “Continuing Professional Education,” or CPE, technical instruction program. These articles were supposed to be used for training of line agents, collecting and putting out the agency’s best information on a particular topic — on, say, political activity [9] by social welfare nonprofits in 1995.

“People in a group would write up their thoughts: ‘Here’s the law,’” said Beth Kingsley, a Washington lawyer with Harmon, Curran, Spielberg & Eisenberg who’s worked with nonprofits for almost 20 years. “It wasn’t pushing the envelope. It was, ‘This is how we see this issue.’ It told us what the IRS was thinking.”

The system began to change in the mid-1990s. The IRS was having trouble hiring people for low-level positions in field offices like New York or Atlanta — the kinds of workers that typically reviewed applications by nonprofits, Owens said.

In Cincinnati

The answer to this was simple: Cincinnati.

The city had a history of being able to hire people at low federal grades, which in 1995 paid between $19,704 and $38,814 a year — almost the same as those federal grades paid in New York City or Chicago. (Adjusted for inflation, that’s between $30,064 and $59,222 now.)

“That was well below what the prevailing rate was in the New York City area for accountants with training,” Owens said. “We had one accountant who just had gotten out of jail — that’s the sort of people who would show up for jobs. That was really the low point.”

So in 1995, the Exempt Organizations division started to centralize. Instead of field offices evaluating applications for nonprofits in each region, those applications would all be sent to one mailing address, a post-office box in Covington, Ky. Then a central office in Cincinnati would review all the applications.

Almost inadvertently, because people there were willing to work for less than elsewhere, Cincinnati became ground zero for nonprofit applications.

For the time being, the checks remained in place. The criteria for flagged nonprofits were still made public. The Continuing Professional Education text was still made public. Saturation reviews and post reviews were still in place.

But by 1998, after hearings in which Republican Senator Trent Lott accused the IRS of “Gestapo-like” tactics, a new law mandated the agency’s restructuring. In the years that followed, the agency aimed to streamline. For most of the ‘90s, the IRS had more than 100,000 employees. That number would drop every year, to slightly less than 90,000 [10] by 2012.

Change Will Come

Change also came to the Exempt Organizations division.

The IRS tried to remove discretion from lower-level employees around the country by creating rules they had to follow. While the reorganization was designed to centralize power in the agency’s Washington headquarters, it didn’t work out that way.

“The distance between Cincinnati and Washington was such that soon Cincinnati became a power center,” said Streckfus, the former IRS lawyer.

Following reorganization, many highly trained lawyers in Washington who previously handled the most sensitive nonprofit applications were reassigned to focus on special projects, he said.

Owens, who left the IRS in 2000 but stayed in touch with his old division, said the focus on efficiency meant “eliminating those steps deemed unimportant and anachronistic.”

In 2003, the saturation reviews and post reviews ended, and the public list of criteria that would get an application referred to headquarters disappeared, Owens said. Instead, agents in Cincinnati could ask to have cases reviewed, if they wanted. But they didn’t very often.

“No one really knows what kinds of cases are being sent to Washington, if any,” Owens said. “It’s all opaque now. It’s gone dark.”

By the end of 2004, the Continuing Professional Education articles stopped [11].

Recommendations [12] from an ABA task force for IRS guidelines on social welfare nonprofits and politics that same year were met with silence.

Even the IRS’s Political Activities Compliance Initiative, which investigated [13] complaints of charities engaged in politics — primarily churches — closed up shop in early 2009 after less than five years, without any explanation.

Both before and after the changes, the Exempt Organizations division has been a small part of the IRS, which is focused on collecting money and chasing delinquent taxpayers.

US capitol

IRS Employee Count in 2012

Rulings and Agreements, the division that handles applications of all nonprofits, accounted for less than 0.5 percent of all IRS employees in 2012.

Source: IRS Data Books [14], IRS Exempt Organizations Annual Report [15]

Of the 90,000 employees at the agency last year, only 876 worked in the Exempt Organizations’ division, or less than 1 in 1,000 employees.

Of those, 335 worked in the office that actually handles applications of nonprofits.

Most of those — about 300 — worked in Cincinnati, Streckfus estimates. The rest were at headquarters, in Washington D.C.

In Cincinnati, the employees’ primary job was sifting through the applications of nonprofits, making determinations as to whether a nonprofit should be recognized as tax-exempt. In a press release [16] Wednesday, the IRS said fewer than 200 employees were responsible for that work.

In 2012, these employees received 60,780 applications. The bulk of those — 51,748 — were from groups that wanted to be recognized as charities.

But the number of social welfare nonprofit applications spiked from 1,777 in 2011 to 2,774 in 2012. It’s impossible to say how many of those groups indicated whether they would engage in politics, or why the number of applications increased. The IRS said Wednesday that it “has seen an increase in the number of tax-exempt organization applications in which the organization is potentially engaged in political activity,” including both charities and social welfare nonprofits, but didn’t specify any numbers.

Total 501(c)(4) [17] Nonprofit Applications from 2002 to 2012

From 2011 to 2012, applications increased by more than 50 percent.

Source: IRS Data Books [14]

On average, one employee in Cincinnati would be responsible for going through roughly one application per day.

Some would be easy — say, a local soup kitchen. But to evaluate whether a social welfare nonprofit has social welfare as its primary purpose, the agent is supposed to use a “facts and circumstances” test. There is no checklist. Reviewing just one social welfare nonprofit could take days or weeks, to look through a group’s website, track down TV ads and so forth.

“You’ve got 60,000 applications coming through, and it’s hard to do that with the number of agents looking at them,” said Philip Hackney [18], who was in the IRS’s chief counsel office in Washington between 2006 and 2011 but said he wasn’t involved in the Tea Party controversy. “The reality is that they cannot do that, and that’s why you’re seeing them pick stuff out for review. They tried to do that here, and it burned them.”

As we have previously reported, last year the same Cincinnati office sent ProPublica [19] confidential applications from conservative groups. An IRS spokeswoman said the disclosures were inadvertent.

The Commissioner Speaks

Mark Everson, IRS commissioner for four years during the George W. Bush administration, said he believed the fact that the division is understaffed is relevant, but not an excuse for what happened. “The whole service is under-funded,” he pointed out.

And Dan Backer, a lawyer in Washington who represented six of the groups held up because of the Tea Party criteria, said he doesn’t buy the notion that low-level employees in Cincinnati were alone responsible.

“It doesn’t just strain credulity,” Backer said. “It broke credulity and left it laying on the road about a mile back. Clearly these guys were all on the same marching orders.”

The inspector general’s audit was prompted last year after members of Congress, responding to complaints by Tea Party groups, asked for it.

Like former officials interviewed by ProPublica, the audit suggests that officials at IRS headquarters in Washington were unable to manage their subordinates in Cincinnati. When Lois Lerner, the Exempt Organizations division director in Washington, learned [20] in June 2011 about the improper criteria for screening applications, she instructed that they be “immediately revised.”

But just six months later, Cincinnati employees changed [21] the revised criteria to focus on “organizations involved in limiting/expanding government” or “educating on the Constitution.” They did so “without executive approval.”

“The story people are overlooking is: Congress is complaining about underpaid, overworked employees who are not adequately trained,” said Bryan Camp, a former attorney in the IRS chief counsel’s office.

Assessment

In the end, after all the millions of anonymous money spent by some groups to elect candidates in 2012, after all [22] the groups [23] that said in their applications that they would not spend money to elect candidates before doing exactly that, after the Cincinnati office flagged conservative groups, the IRS approved almost all the new applications. Only eight applications were denied.

Source: http://www.propublica.org/article/how-irs-nonprofit-division-got-so-dysfunctional

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details


Need a Manager of Surgical Nurses and Operating Rooms

Join Our Mailing List 

Seeking A Direct Hire in Kansas

By Kathy Williams kathyw@thorgroup.com
Resource Manager
Thor Group, Inc.

Dear Dr. David E Marcinko,

Hello!  We are looking for a Manager of Surgical Nurses and Operating Rooms.

Our client has a wonderful opportunity to have a work balance life style.  If one of your ME-P readers would like the peace and quiet of a small town plus a great opportunity for your career, this opportunity is for them!

This position will manage and supervise functions related to patient care in the operating rooms; ensure effective delivery of patient care and compliance with administrative and facility policies and procedures.  This position will pay $60-75K depending in experience.  Direct Hire in Kansas.

Responsibilities:

• Guides and directs nursing staff regarding safe, effective patient care, problem-solving and decision making according to patient needs, staff capabilities and facility resources.
• Maintains up-to-date knowledge of new procedures, products and equipment used in the OR.
• Interviews, orients, assigns work schedules, conducts and reviews evaluations and disciplines personnel to manage performance.  Oversees OR staff in conducting annual performance evaluations and competency documentation.
• Ensure proper daily staffing levels in all operating rooms.
• Assist in investigating and initiating follow-up and corrective action when necessary in response to complaints and/or concerns from patients, families, physicians or employees.  Develops, implements and monitors, methods and strategies to achieve high patient satisfaction results.
• Is familiar with, and maintains compliance within the OR Department, on all regulatory agency requirements.
• Maintains compliance with accreditation/licensure requirements.
• Identify operational needs; manage appropriate level of equipment and supplies and monitors equipment maintenance.  Assess the environment and make recommendations to ensure optimal patient comfort, safety and compliance with various regulatory bodies.

Qualifications:

• Diploma from accredited nursing program.
• Current Licensure as Registered Nurse and able to obtain a Kansas license.
• Minimum of 3 years management experience in hospital setting preferred.
• Certification in area of specialization.
• Demonstrated excellent communication skills.

###

Healthcare Jobs

Assessment

THOR, Inc. is a cutting-edge business solutions firm that has been working with some of the top companies throughout the United States for nearly 40 years.

If you are interested in the Manager of Surgical Nurses and Operating Rooms position, please send your updated resume along with salary history to kathyw@thorgroup.com. If you are not interested in this opportunity, perhaps you know someone who might be, please have them forward their resume to me!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details


A Red-Neck Doctor

Join Our Mailing List

You know you are a red-neck doctor, when ….?

By Dr. David Edward Marcinko MBA CMP

[Editor-in-Chief]

Recently, an ME-P subscriber who knows of my vintage Jaguar restoration project, sent me this photograph. We do not own it or have copyrights to it; still it is presented here in the interest of humor and collegiality.

###

Jaguar

Assessment

With all due respect to my Atlanta neighbor, and comedian, Jeff Foxworthy.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Healthcare Promises [aka ACA]

Join Our Mailing List

On the Affordable Care Act

By Rick Kahler MS CFP® ChFC CCIM www.KahlerFinancial.com

Rick Kahler CFP“I’m not sure what’s wrong or what kind of surgery you need, but we have to operate right now.”

If you heard this from your doctor, you’d jump off the examination table and run for the door. Yet that’s essentially the approach the President and Congress used three years ago to pass a bill, optimistically called the Affordable Care Act, which was the largest transformation of the U.S. health care system in our lifetime.

The Debate

During the frenzied debate our elected leaders made many promises as to the amazing benefits this legislation would bestow on Americans. After listening to speeches from President Obama, Speaker of the House Nancy Pelosi, and President of the Senate Harry Reid, I recounted those promises in this blog on March 21, 2010.

The Promises

Let’s revisit those promises.

  1. All Americans will now receive affordable, or free, quality health care.
  2. No one will ever be denied coverage.
  3. No one will ever go into bankruptcy because of the costs of health care.
  4. There will be increased access to health care for 95% of Americans.
  5. There will be no decline in the quality of health care.
  6. Health care costs will go down.
  7. Health insurance coverage will be affordable to the middle class.
  8. There will be no decline in Medicare benefits.
  9. Insurance premiums will decline for the middle class.
  10. It will unleash unprecedented entrepreneurial opportunity for the economy.
  11. The deficit will decline, saving taxpayers $1.3 trillion.
  12. It will cut $500 billion of waste, fraud, and abuse out of Medicare.
  13. No government funds will be used to fund abortion.

Are these promises coming true? Many of them are pending full implementation of the act in 2014. Others have fallen flat or encountered the law of unintended consequences.

Obama Care

Business Owner’s

I’ve heard recently from several owners of small businesses about their increased health insurance costs. In addition to premium increases of nearly 50% over the past two years, they are seeing increased administrative costs from what one person called the “insanity and complexity” of the new regulations.

Businesses with fewer than 50 employees aren’t required to provide health insurance. The incentive for owners of businesses close to that threshold is to keep employee numbers below 50, which means curtailing growth or even laying people off.

Those without employer-provided insurance are supposed to be able to shop for coverage in new health care exchanges, beginning this October. However, half the states have chosen to rely on the federal government instead of setting up their own exchanges.

This has brought criticism even from former supporters like Democratic Senator Max Baucus of Montana, who helped write the health care bill. He is concerned that the exchanges will not open on time and consumers won’t have the information they need to use them. He told the Huffington Post that Obamacare is headed for a “train wreck.”

ACA Cost Estimates

The proponents said the ACA would cost $938 billion over 10 years. In addition to the promised Medicare savings, this was to be covered by a total tax increase of $562 billion over 10 years. This included a Medicare tax of 3.8% on dividends, rents, interest, and investment income on individuals and small business earning over $250,000.

The Office of Management and Budget, however, places the cost at $1.8 trillion over 10 years, resulting in a shortfall of around $900 billion.

Assessment

Whether Obamacare becomes the wild success the proponents guaranteed is yet to be seen. However, what we’ve seen so far isn’t promising. We as consumers would be well advised to pay close attention and ask tough questions before we accept this drastic surgery.

More

Conclusion

Are these promises coming true? Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details


When did you last Review your Insurance Coverage – Doctor?

Join Our Mailing List 

Why shopping around periodically is a smart move

By Lon Jefferies, MBA CFP™  http://www.NetWorthAdvice.com

Lon JeffriesWhen is the last time you compared rates on your home and auto insurance policies – doctors and all ME-P readers? Unfortunately, a stellar safety record doesn’t always translate into lower insurance rates. Even if you think you have a good rate, shopping around periodically is smart.

A Reader’s Query

After attempting to follow my advice of maintaining an umbrella insurance policy, one of our ME-P readers contacted his insurer to add coverage. This reader was shocked when his insurer informed him that he didn’t qualify for an umbrella policy because he didn’t carry sufficient liability insurance on his auto policy. (Minimum auto liability insurance – frequently $500,000 – is required in order to purchase umbrella coverage.) Although this individual had owned his policy for eight years, he was unaware that the policy only provided $50,000 of liability coverage. This amount was clearly insufficient for an individual approaching retirement.

In addition to realizing that he was severely under-insured, this individual discovered he was also paying excessive premiums. For only $50,000 of auto liability coverage, this person was paying $914 per year. Moreover, the individual realized he was paying $351 per year for the $350,000 of liability coverage the individual had on his condo. Consequently, in total, this person was paying $1,265 per year for $50,000 of auto liability and $350,000 of home liability coverage.

Case Model

This individual then spoke with an independent insurance agent to increase auto liability coverage to an amount that enabled him to obtain an umbrella policy. This was critical, as it dramatically decreased the individual’s liability exposure, a risk an individual with accumulated assets clearly shouldn’t have. Even better, the individual was able to obtain dramatically improved rates on his policies. For a total of $1,207 (less than he was previously paying!), the individual was able to secure $1,000,000 of auto liability coverage, $350,000 of home liability, and an additional $1,000,000 umbrella policy.

policy insurance

Assessment

Clearly, it can be beneficial to occasionally review and compare rates on your insurance policies. People tend to believe that policies that have been owned for extended periods of time are efficiently priced, but it may be the opposite. If you haven’t verified that you are adequately insured and conducted a cost comparison recently, speak to an independent insurance agent and minimize your exposure with cost-effective policies.

More

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

ProPublica Launches Prescriber Checkup [Interactive Database]

Join Our Mailing List

The Doctors and Drugs in Medicare Part D

By Jeff Larson, Jennifer LaFleur, Charles Ornstein, Tracy Weber and Lena Groeger

ProPublica, Updated at May 10, 2013

Medicare’s popular prescription-drug program now serves more than 35 million people, but the names of prescribers and the drugs they choose have never previously been public … Until now.

###

Medicare and Medicaid drug capsules
Assessment

Use this tool to find and compare doctors and other top prescribers in 2010.

Link: http://projects.propublica.org/checkup/

More:

Conclusion
Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.
****
Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Product DetailsProduct Details

Seeking Director of Hospital Accounting

Join Our Mailing List 

For an East Coast Facility

By Kathy Williams kathyw@thorgroup.com
Resource Manager
Thor Group, Inc

Dear Dr. David E Marcinko,

Hello!  We are looking for a Director of Accounting for Hospital client located on East Coast. This is a Direct Hire position.  The position will oversee 3 Managers and 15 FTE’s.  This position will report to the VP of Accounting.

POSITION SUMMARY

The purpose of the position is to provide primary oversight, supervision and strategic direction to the General Accounting Department. This position ensures the accuracy of hospital’s consolidated financial statements in accordance with Generally Accepted Accounting Principles (GAAP) and system-wide policy.

Job Requirements

1. Previous Director / Manager experience in Hospital / Healthcare Accounting role
2. CPA or MBA required.
3. 7 to 10 years of experience.
4. The knowledge and ability to direct, control and supervise the activities of the General Accounting Department at a level generally acquired through 7 to 10 years of progressive experience in healthcare accounting
5. Experience formulating business and accounting policies and procedures
6. Extensive experience using computerized accounting systems and Microsoft Office.

###

jobs

Assessment

If any ME-P reader is interested in this Director of Accounting position, please forward their resume to me at kathyw@thorgroup.com.  If you are not interested in this opportunity, perhaps you know someone who might be … please have them forward their resume to me!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Events Planner: May 2013

ADVERTISEMENT

Events-Planner: MAY 2013

By Staff Writers
Calendar Calculator“Keeping track of important health economics and financial industry meetings, conferences and summits”

Welcome to this issue of the Medical Executive-Post and our Events-Planner. It contains the latest information on conferences, news, and relevant resources in healthcare finance, economics, research and development, business management, pharmaceutical pricing, and physician/entity reimbursement!  Watch for a new Events-Planner each month.

First, a little about us! The Medical Executive-Post is still a relative newcomer. But today, we have almost 175,000 visitors and readers each month from all over the country, in addition to our growing subscriber base. We have been a successful collaborative effort, thanks to your contributions.  As a result, we are adding new resources daily. And, we hope the website continues to provide the best place to go for journals, books, conferences, educational resources, tools, and other things you need to establish the value your healthcare consulting and financial advisory intervention.

So, enjoy the Medical Executive-Post and this monthly Events-Planner with our compliments.

A Look Ahead this Month – And now, the important dates:

  • NAPFA National Meeting: Paris Hotel, Las Vegas, NV.
  • FRA Advisor Forum: Harvard Club, Boston, MA.
  • May 08: Public Safety Congress: New Orleans, LA.
  • May 16: Hospital Medicine: National Harbor, MD.

MarcinkoAdvisors@msn.com

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest E-Ps delivered to your email box each morning? Just subscribe using the link below. It’s free. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details