
10‑Year Exit Planning for Physicians in an Era of Consolidation

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

http://www.DavidEdwardMarcinko.com

***

***

Medicine is experiencing a significant structural shift in its history. Independent practices—once the primary model—is increasingly being absorbed into super groups, corporate entities, private equity groups, multispecialty organizations, healthcare facilities and hospital systems. Consolidation is reshaping referral patterns, reimbursement and competitive dynamics. For physicians who expect to retire or transition out of practice within the next decade, this environment demands a long‑range strategic exit plan. A 10‑year horizon provides the time needed to strengthen practice value, expand options and ensure a smooth transition for patients, staff and the physician.

A decade before exit, the most important step is under standing the market. Consolidation has created active buyers for medical practices, but it has also raised expectations. Groups now evaluate practices with a level of sophistication that goes far beyond revenue. They look at payer mix, surgical volume, ancillary services, compliance infrastructure, the stability of referral sources and other key performance indicators [KPIs]. They want practices that are scalable, efficient and not overly dependent on the owner. For physicians, this means the first years of a 10‑year plan should focus on building a systems‑driven practice. Standardizing workflows, strengthening documentation, modernizing technology and delegating authority all increase the practice’s attractiveness and valuation.

By year seven or eight, physicians should begin evaluating succession pathways. Internal succession—selling to an associate or partner—remains a strong option, but it requires long lead times. Recruiting a younger physician, mentoring them, and structuring a buy‑in that is financially realistic can take years because of student school, home mortgage and automobile debt. A 10‑year window allows the owner to identify the right candidate, build trust and gradually shift responsibilities. For practices in competitive markets, this timeline also provides flexibility to adjust if an associate leaves, or dies or if the practice needs to recruit more than one physician.

***

***

At the same time, physicians should stay informed about external buyers. Private equity platforms and large groups often operate on multi‑year acquisition cycles. Understanding their deal structures, compensation models and expectations helps physicians determine whether an external sale aligns with their goals. A decade‑long plan allows physicians to time the market, negotiate from a position of strength and avoid rushed decisions. It also gives them the opportunity to improve key metrics—such as earnings before interest, taxes, and amortization [EBITDA], surgical mix or ancillary revenue—that directly influence valuation.

Financial exit planning becomes increasingly important as the time approaches. Ten years out, physicians should begin coordinating with financial advisors who understand healthcare transactions. Decisions about retirement accounts, tax strategy and investment planning can significantly affect the net proceeds of a sale, according to Dr. Gary Bode CPA MSA. The structure of the eventual transaction—asset sale versus stock sale, earn‑out versus upfront payments—will have long‑term implications. Early planning allows physicians to optimize their financial position and avoid surprises.

***

***

Operationally, the middle years of the 10‑year plan should focus on strengthening the practice’s infrastructure. Buyers value practices with clean financials, consistent coding patterns, strong compliance programs and efficient staffing models. Investing in staff development, updating equipment and improving patient experience all contribute to long‑term value. Physicians should also consider expanding services—such as wound care, biomechanics or in‑office surgical procedures—if they align with the practice’s strengths. These additions can diversify revenue and make the practice more attractive to both internal and external successors.

As the final three to four years approach, physicians should begin formalizing their exit strategy. This includes obtaining a professional valuation, reviewing legal documents, and preparing the practice for due diligence. It also means developing a communication plan for staff and patients. Physicians often underestimate the emotional impact of leaving a practice they built over decades. A thoughtful transition plan helps maintain continuity of care and preserves the practice’s reputation.

In the final year or two, the focus shifts to execution. Whether the physician chooses an internal sale, an external acquisition, or a hybrid model, the groundwork laid over the previous decade ensures a smoother process. The physician can negotiate confidently, knowing the practice is well‑positioned and the transition is aligned with personal and professional goals.

***

***

ASSESSMENT       

A 10‑year exit plan is not simply a financial strategy—it is a roadmap for preserving legacy, maximizing value and ensuring continuity for patients and staff. In an era of consolidation, physicians who plan early gain more control, more options, more money and more leverage. They can shape the future of their practice rather than reacting to market pressures.

CONCLUSION

With foresight and intentional preparation, physicians can develop a practice exit plan and navigate this changing landscape with confidence in the current era of consolidation.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

(©) Copyright USA. All rights reserved.

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

PLUMMETING & PLUNGING: Global Stock Markets

By Dr. David Edward Marcinko; MBA MEd

http://www.DavidEdwardMarcinko.com

SPONSOR: http://www.MarcinkoAssociates.com

****

***

The Mechanics of Momentum: Political Shift and the Tech Realignment

The dramatic plunge in global financial markets today stands as a stark reminder of how rapidly optimism can transform into panic when political realignment collides with systemic valuation anxieties. Just twenty-four hours after celebrating a historic post-midterm election rally, Wall Street experienced a severe reversal, wiping out trillions of dollars in market value. The absolute epicenter of this rout was the technology sector, specifically the high-flying semiconductor and artificial intelligence trades that have propelled equity benchmarks to record heights over the past year. Analyzing why the market suffered such a swift breakdown requires looking at a volatile confluence of political shockwaves, immediate regulatory fears, and underlying skepticism regarding corporate capital expenditures.

The fundamental catalyst for the panic stems directly from the shifting balance of power following the midterm congressional elections. Financial markets inherently dislike uncertainty, yet they often overreact to changes in governance. When early post-election headlines initially brought a wave of certainty, equity futures soared on the assumption that a stable political environment would preserve corporate momentum. However, as the finality of a decisive Democratic legislative sweep crystallized, institutional investors abruptly shifted their focus toward the policy implications of the incoming Congress.

For the past several quarters, the market has operated under the assumption of an uninhibited buildout of artificial intelligence data centers, buoyed by promises of continuous federal deregulation. The incoming legislative majority campaigned heavily on platforms critical of massive data center expansion, citing mounting concerns over rising electricity prices and strain on the domestic power grid. Consequently, traders rapidly priced in a reality where the expansion of AI hardware would face strict oversight, potential moratoriums on data center construction, and heightened environmental mandates. This sudden policy threat fundamentally disrupted the growth models used to justify premium stock valuations, prompting a mass exodus of capital from the year’s most crowded trades.

The ensuing correction in technology indices exposes a deeper, pre-existing vulnerability: growing skepticism over the artificial intelligence revenue model. For months, hyperscale technology companies and major cloud providers have deployed hundreds of billions of dollars globally to construct computing infrastructure. Institutional investors were already quietly questioning the timeline required for these massive capital deployments to generate substantial financial returns. The threat of regulatory restrictions served as the ultimate trigger, converting structural skepticism into an active panic. Investors concluded that if data center construction becomes slower and more expensive due to legislative oversight, the return on investment will stretch even further into the future. This realization triggered a wave of profit-taking, which rapidly escalated into a full-scale liquidation across prominent chip manufacturers and software developers.

Crucially, the sheer speed of the downturn was exacerbated by technical market factors and herd behavior. In modern financial markets, automated algorithms and quantitative trading strategies react instantaneously to specific policy shifts and volatility spikes. As major indices broke below key moving averages, automated sell programs activated, placing downward pressure on prices. Wall Street’s prominent volatility gauge spiked significantly, reflecting a dramatic premium on downside protection. Seeing institutional entities aggressively derisking, retail traders panicked, executing their largest single-day equity liquidation in years. This cascading effect meant that selling was no longer restricted to technology firms; all primary market sectors closed lower as asset managers sold liquid positions across financial, manufacturing, and consumer industries to balance portfolio risk.

***

***

The broader macroeconomic environment provided the dry tinder for this sell-off. Elevated borrowing costs had already left corporations sensitive to structural friction. When geopolitical risks flared alongside localized energy infrastructure disruptions, commodity markets reacted defensively, immediately reigniting fears of inflation. Higher energy input costs complicate the expansion of any power-dependent industry, intensifying the pressure on tech corporations facing regulatory scrutiny. Faced with the prospect of sticky inflation, rising capital costs, and a decelerating infrastructure buildout, investors chose to flee toward safe-haven assets, prompting a flight to quality in the government bond market.

Ultimately, the market collapse is a classic narrative of a technical correction colliding with systemic repricing. The midterm election did not change corporate earnings overnight, but it decisively shifted future growth expectations. The speculative premium that had built up around technology infrastructure dissolved the moment investors realized that political and environmental realities could slow the pace of commercial expansion. Wall Street proved once again that when long-term assumptions are challenged by immediate structural hurdles, capital prioritizes safety over speculation, prompting a swift revaluation of global equity values.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

(©) Copyright USA. All rights reserved.

SEND IN YOUR ME-Ps & TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

WEALTH Effect

By Dr. David Edward Marcinko; MBA MEd

http://www.DavidEdwardMarcinko.com

Sponsor: http://www.MarcinkoAssociates.com

***

***

The wealth effect describes how changes in people’s perceived wealth can influence their spending. When households feel wealthier, they may be more willing to buy goods and services; when they feel poorer, they may cut back. The effect can arise from changes in the value of homes, stocks, retirement accounts, or other assets. It is important because household consumption makes up a large share of economic activity, so shifts in spending can affect businesses, employment, and growth.

A simple example is a homeowner whose property rises in value. Even if the homeowner’s income stays the same, the increase may create a sense of greater financial security. They might renovate the house, replace a car, travel, or feel more comfortable spending rather than saving each extra dollar. Some may also borrow against their home’s increased value, turning part of that paper gain into cash. Similarly, someone whose investment portfolio grows may be more confident about their future finances and spend more in the present.

The reverse can happen when asset values fall. A decline in home prices can leave owners feeling less secure, especially if they owe nearly as much as their homes are worth. A drop in stock prices can shrink retirement savings and lead investors to postpone major purchases. Even people who do not own many financial assets may be affected indirectly: falling demand can reduce company sales, slow hiring, or weaken confidence in the broader economy.

The wealth effect is not the same as an increase in income. Income is money received through work, investments, or other sources; wealth is the value of assets a person owns minus debts. A person can become wealthier on paper without receiving additional cash. That distinction matters because asset gains do not automatically pay for everyday expenses. A homeowner whose property value rises may still have the same monthly wages and mortgage payment. To spend more, they may need to sell an asset, refinance, borrow, or use income they already have.

***

***

The effect also differs across households. People with substantial assets may respond more strongly to changes in stock and property prices because they own more investments and have greater flexibility to adjust their spending. Other households may be more concerned with wages, rent, food, and debt payments than with market valuations. Age, debt, job security, access to credit, and expectations about the future all influence how a person reacts. For someone approaching retirement, a falling portfolio may prompt caution; for a young worker with steady income, the same market decline may have little immediate effect.

The wealth effect can reinforce economic booms and downturns. During a period of rising asset prices, increased confidence and spending can support businesses and employment. In turn, a stronger economy may encourage further investment and optimism. But this cycle can reverse. Falling prices may weaken confidence, reduce spending, and put pressure on businesses. If households and firms become more cautious at the same time, the slowdown can deepen.

However, the wealth effect should not be overstated. Not every increase in asset prices causes a large rise in consumer spending, and people may save gains rather than spend them. Some households may treat a temporary market rise as uncertain, while others may use extra resources to pay down debt. The effect also depends on whether people believe their gains will last. A brief stock-market surge may not change spending much if consumers expect prices to fall again.

Economic policymakers pay attention to the wealth effect because it can influence demand, inflation, and financial stability. Central banks, for example, monitor asset markets alongside employment, prices, and borrowing. Yet rising asset prices do not necessarily signal broad prosperity: gains may be concentrated among people who already own homes or investments. If housing becomes more expensive, existing owners may feel richer while renters and first-time buyers face higher costs.

Ultimately, the wealth effect is a link between balance sheets and everyday choices. Changes in the value of assets can shape confidence and spending, even when paychecks have not changed. Its strength varies across people and circumstances, and it is only one influence on the economy. Still, understanding it helps explain why financial markets and property prices can matter beyond investors: they can alter how households plan, consume, save, and prepare for the future.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

(©) Copyright USA. All rights reserved.

SEND IN YOUR ME-Ps & TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

GLOSSARY OF TERMS: Investment Portfolio

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

http://www.DavidEdwardMarcinko.com

***

***

Key Terms and Definitions

Portfolio Insights: A feature that connects your portfolio to what’s happening in the market by reviewing your holdings and surfacing relevant market news and activity.

Portfolio: For the purposes of insights, a portfolio includes all accounts selected for inclusion in the total value displayed.

As-of-now: A time stamp.

Included accounts: Accounts shown in your Summary that contribute to your (for example, brokerage, retirement, linked external accounts, bank accounts, and assets such as real estate shown in Summary).

Total value: The combined value of accounts included in your summary. Total Value is not a measure of investment performance. Accounts included may vary based on your total value settings

Total Day Change: The overall dollar change in your total value for the day. This can include changes from accounts that don’t hold tradable securities.

Account Day Change: Account day change indicates the change in account value from the previous trading day’s close. This includes your trading activity, as well as deposits and withdrawals.

Top Movers: Securities with the largest impact on your portfolio’s daily movement, based on a combination of price change and portfolio weighting.

Benchmark: A standard reference (such as the S&P 500) used for performance comparisons.    

S&P 500: An index of 500 large U.S. companies that may be used as the standard benchmark for comparisons.

***

***

Current market conditions: Market activity relevant to today’s trading, such as same‑day market movement and recent news and events affecting today’s trading activity.

CFR (Center for Financial Research): A research organization that provides general market commentary and research updates used to identify notable market events, trends, and news.

Market news: Selected news and information that may be relevant to your investments.

Summary view: A summary page is where your accounts and total value are shown.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

(©) Copyright USA. All rights reserved.

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

CONCENTRATION RISK: When Your Medical Practice is 80% of Your Net Worth

By Dr. David Edward Marcinko; MBA MEd

http://www.DavidEdwardMarcinko.com

***

***

SPONSOR: http://www.MarcinkoAssociates.com

When a medical practice grows into 80% of your net worth, you’re no longer just running a medical business—you’re carrying a level of concentration risk that can shape every financial, professional and personal decision you make. The core issue is simple: when most of your wealth is tied to a single, illiquid, operationally demanding asset, the downside scenarios multiply while your flexibility shrinks. Understanding what actually happens in this situation—financially, psychologically and strategically—helps clarify why many practice owners eventually seek ways to rebalance their financial life.

What concentration risk means in a medical practice

Concentration risk may occur in solo and small group practices when too much of your wealth depends on this one income stream. In a medical practice, this usually means:

  • Your practice equity makes up the majority of your net worth.
  • Your income is tied to the same asset that represents your wealth.
  • Your retirement plan depends on the future sale of that practice.

This creates a single point of failure. If anything disrupts the practice—reimbursement changes, health issues, staffing shortages, local competition or regulatory shifts—your income and your wealth decline at the same time.

How this level of concentration affects your financial life

1. Your net worth becomes illiquid

A medical practice isn’t like a stock portfolio. You can’t sell 5% of it to raise cash. Most of your wealth is locked in:

  • patient relationships
  • professional referring relationships
  • intangible goodwill
  • equipment
  • electronic medical records
  • leasehold improvements
  • real estate holdings
  • staff and systems

This means you may feel “wealthy on paper” but still experience cash‑flow pressure, especially during slow months [January, February and March] or unexpected expenses.

2. Your retirement timeline becomes fragile

When 80% of your net worth is the practice, your retirement depends on:

  • your health
  • finding a qualified buyer
  • receiving a fair valuation
  • getting paid over time (often 5-7-10 years)
  • the buyer successfully running the practice

If the buyer struggles, or dies, your retirement income may be at risk. Many owners underestimate how much of their retirement plan depends on someone else’s future health and performance.

3. Your income and wealth move together

If the practice has a bad year, you don’t just earn less—you’re also worth less. That double exposure amplifies volatility. A, insurance or insurer reimbursement cut, local industry or job slow down  or  key staff departure can simultaneously hit:

  • your salary
  • your distributions
  • the practice’s valuation
  • your retirement saving plans

This is similar to a single stock risk problem and the opposite of diversification where an investor spreads investments across various assets to reduce risk and optimize positive returns so that an asset decline is offset by another’s advance.

***

***

1. You may feel professionally trapped in the practice

When most of your wealth is tied to the practice, stepping back becomes difficult. Owners often feel pressure to:

  • work longer hours
  • delay retirement
  • avoid taking vacations or extended time off
  • personally handle tasks that could be delegated

The practice becomes not just a job, but the anchor of your financial identity.

2. Decision‑making becomes overly cautious

High concentration risk can make you hesitant to:

  • invest in new technology
  • expand or relocate the practice
  • hire additional providers
  • take on debt
  • experiment with new service lines

When the stakes feel enormous, even smart risks can feel unsafe.

3. Burnout risk increases

The emotional weight of knowing that your family’s financial security depends on your daily performance can compound stress. Many podiatrists report that the practice begins to feel like a burden rather than an asset.

4. Your financial resilience weakens

Unexpected life events—illness, disability, divorce, or family needs—can force decisions at the worst possible time. With most wealth tied up in the practice, options are limited.

5. Your lifestyle becomes tied to practice performance

If the practice has a downturn, your personal spending may need to adjust quickly. This creates a sense of anxiety and instability even when the business is fundamentally healthy.

6. Your long‑term goals become uncertain

Major goals—college funding, second homes, early retirement—become dependent on the practice’s future value, which is influenced by factors you can’t fully control.

Now, once podiatrists realize how concentrated their wealth is, they often pursue one or more strategies:

  • Gradual de‑risking through retirement plan contributions, brokerage investing, or real estate.
  • Bringing in associates or partners to share operational load and diversify income.
  • Joining a larger medical group practice
  • Partial sale or recapitalization to convert practice equity into liquid assets.
  • Building ancillary income streams such as real estate ownership, consulting, or ancillary services
  • Private equity association.

The goal isn’t to abandon the practice—it’s to prevent it from being the only pillar holding up your financial life.

ASSESSMENT

When 80% of your net worth is tied to your medical practice, you’re not just exposed to financial volatility—you’re exposed to identity volatility as your wealth, your work and your sense of overall self and security becomes intertwined.

CONCLUSION

And so, reducing practice net worth concentration risk isn’t just an economic strategy; it’s a way to reclaim flexibility, reduce stress and create a more stable foundation for your career. More importantly, how well do you actually execute office net worth risk reduction in your own medical practice?

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

(©) Copyright USA. All rights reserved.

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

Democrats V. Republicans V. Independents

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

****

***

Democrats

Democrats are typically associated with liberal or progressive ideologies, advocating for a larger role of government in society to promote equality and social welfare. They support policies such as expanded healthcare access, environmental protection, renewable energy, civil rights, and social safety nets like Medicaid and food assistance programs. Democrats often favor higher taxes on high-income earners to fund public programs and emphasize regulation of the economy to ensure fairness and protect workers’ rights. They also generally support balanced immigration enforcement with reform and expanded voting access.

Republicans

Republicans are generally associated with conservative ideologies, emphasizing limited government, free-market principles, and individual responsibility. They advocate for lower taxes, fewer regulations, and reduced government spending on social programs. Republicans prioritize traditional social values, strong national defense, and strict border enforcement, and they often support energy independence through oil, gas, and nuclear power rather than focusing on renewable energy. Their policies favor market-based healthcare systems and emphasize states’ rights over federal intervention.

Independents

Independents are voters or politicians who do not formally affiliate with either major party. They make up roughly 40–45% of Americans, though many lean toward one party when voting. Independent politicians, such as Senators Bernie Sanders and Angus King, often caucus with Democrats but maintain a degree of autonomy. Independents can influence elections by swinging votes in closely contested races, and they often represent moderate or mixed policy positions that do not fully align with either party.

Summary

The main difference lies in ideology and policy approach: Democrats favor progressive policies and government intervention, Republicans favor conservative policies and limited government, and Independents remain unaffiliated, often acting as a moderating or swing influence in the political system. Understanding these distinctions helps explain the policy debates, election dynamics, and legislative priorities in the United States.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

****

PARADOX: Accounting Tax Planning

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

http://www.DavidEdwardMarcinko.com

***

***

The Accounting Tax Planning Paradox stands as a cornerstone of sound financial and accounting prospecting and emphasizing the importance of Roth accounts for their tax-free withdrawals and control over assets. Preparing for future tax uncertainties by allocating retirement assets into tax-free accounts can safeguard financial stability and autonomy.

Example: The Accounting Tax Planning Paradox lies in the instinctive desire to minimize taxes now versus the strategic advantage of preparing for future tax uncertainties. While the immediate gratification of saving on taxes today can be appealing to sales prospects, the true wisdom in tax planning comes from the foresight to manage future financial stability and autonomy. By allocating a portion of retirement assets into tax-free accounts like Roth IRAs, individuals can enjoy tax-free withdrawals and maintain control over their financial assets, thereby safeguarding against the unpredictability of future tax rates and regulations.

This approach underscores the delicate balance between immediate tax benefits and the long-term goal of securing financial freedom and stability, illustrating the nuanced strategy required in effective financial planning, accounting and risk management client prospecting, .

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

MICRO-ECONOMICS: Propensity to Pay for Goods & Services

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Propensity to pay is an important concept in microeconomics that describes an individual’s willingness and ability to spend money on goods and services. It reflects how much a consumer is prepared to pay for a particular product, depending on factors such as income, preferences, the price of the product, prices of related goods, expectations, and the perceived value of the product. Understanding propensity to pay helps economists explain consumer behavior and how individuals make choices when resources are limited.

In economics, consumers generally have unlimited wants but limited income. Because of this scarcity, they must decide how to allocate their available income among different goods and services. A consumer’s propensity to pay for a product depends largely on the satisfaction or utility expected from consuming it. If a consumer believes that a product provides significant benefits, they may be willing to spend more on it. On the other hand, if the perceived benefit is low, their willingness to pay may be limited.

Propensity to pay is closely related to the concept of willingness to pay. Willingness to pay refers to the maximum amount a consumer is prepared to give up to obtain a particular good or service. For example, suppose a student is willing to pay $30 for a textbook because the book is necessary for an important course. If the textbook is offered for $25, the student may purchase it because the price is below the maximum amount they are willing to pay. However, if the price rises to $40, the student may decide not to buy it. This example demonstrates how a consumer’s willingness to pay influences purchasing decisions.

Several factors determine a person’s propensity to pay. Income is one of the most important factors. Consumers with higher incomes generally have greater purchasing power and may be able to spend more on goods and services. However, the relationship between income and spending varies depending on the type of product. For necessities such as food and basic clothing, spending may increase only moderately as income rises. For luxury goods, spending may increase considerably when consumers become wealthier.

The price of a product also has a significant influence on propensity to pay. According to the law of demand, consumers generally purchase less of a good when its price increases, assuming other factors remain unchanged. A lower price may encourage consumers to purchase a product because it becomes more affordable relative to their income. However, price is not the only consideration. Consumers may be willing to pay a higher price for products they perceive as having superior quality, greater convenience, stronger brand reputation, or unique features.

Consumer preferences also influence propensity to pay. Different individuals value the same product differently. For example, one consumer may be willing to pay a high price for a particular brand of smartphone because of its design and features, while another consumer may prefer a cheaper alternative. These differences arise from individual tastes, needs, experiences, and priorities. Therefore, propensity to pay is not identical across all consumers.

The availability and prices of substitute and complementary goods can also affect consumers’ willingness to pay. If several close substitutes are available, consumers may be less willing to pay a high price for a particular product because they can easily switch to another option. In contrast, when a product has few substitutes, consumers may have a higher propensity to pay, particularly if the product is considered necessary. Complementary goods can have a similar effect. For example, the demand for printers may be influenced by the price of ink cartridges because the two products are used together.

Expectations about the future can also influence current propensity to pay. If consumers expect prices to rise in the future, they may be more willing to purchase a product immediately. Conversely, if they expect prices to fall, they may postpone their purchases. Expectations about future income can have a similar effect. A consumer who expects an increase in income may feel more comfortable making a large purchase, while someone expecting financial difficulties may reduce spending.

***

***

Propensity to pay is also useful for understanding consumer surplus. Consumer surplus is the difference between the maximum amount a consumer is willing to pay for a good and the actual price paid. For instance, if a consumer is willing to pay $100 for a product but purchases it for $70, the consumer obtains a surplus of $30. This concept helps economists analyse the benefits consumers receive from market transactions.

Businesses also pay close attention to consumers’ propensity to pay when setting prices. Firms can use information about customer preferences, purchasing behaviour, and perceived value to determine appropriate pricing strategies. If a business sets its price too high, it may lose customers. If it sets the price too low, it may fail to capture the full value that consumers place on the product. Understanding willingness to pay can therefore contribute to decisions concerning pricing, product design, marketing, and market segmentation.

In conclusion, propensity to pay is an important aspect of consumer behavior in microeconomics. It reflects the extent to which consumers are willing and able to spend their limited resources on particular goods and services. Income, prices, preferences, substitutes, complementary goods, expectations, and perceived value all influence this behavior. The concept is closely connected to willingness to pay and consumer surplus and provides useful insights into how consumers make economic choices. By examining propensity to pay, economists and businesses can better understand demand and the factors that influence decisions in markets!

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Expert Witness

***

***

What Exactly is an Expert Witness?

At D.E. Marcinko & Associates an “expert witness” possesses specialized knowledge in a particular field and is qualified to provide deposition or testimony in court and under oath. This testimony can be based on their personal experience, education, training and/or research. The role of an expert witness is to provide objective and unbiased opinions, analysis, and insights to help a lawyer, judge and/or jury understand technical or complex issues related to the case.

email: MarcinkoAssociates1738@outlook.com

An expert witness can be called by either the prosecution or the defense in a legal case. The expert witness may be required to provide a written report or affidavit detailing their opinions, analyses and conclusions, and they may be asked to testify in court to provide oral testimony and answer questions from the judge and lawyers.

MORE: https://marcinkoassociates.com/expert-witness/

COMMENTS APPRECIATED

EDUCATION: Books

***

Fact Witness vs. Expert Witness | Intellex

***

PARADOX: Edward Simpson

By Dr. David Edward Marcinko; MBA MEd

***

***

Classic Definition: Simpson’s Paradox is a phenomenon in probability and statistics in which a trend appears in several different groups of data but disappears or reverses when these groups are combined. This result is often encountered in social-science and medical-science statistics and is particularly problematic when frequency data is unduly given causal interpretations.

Modern Circumstance: The paradox can be resolved when causal relations are appropriately addressed in the statistical modeling. Simpson’s paradox has been used as an exemplar to illustrate to the non-specialist or public audience the kind of misleading results misapplied statistics can generate. The name Edward Simpson’s paradox was introduced by Colin R. Blyth in 1972.

Paradox Example: Simpson’s paradox is a recurring nightmare for all statisticians overseeing a clinical trial for a medicine. It is possible that if they leave out a certain “confounding” variable from a study, the study’s conclusion on whether a medicine is effective or not, might be, without measuring that confounding variable, the opposite of what it would have been had that variable been measured. Statisticians have to enlist expert knowledge to assure them-selves that no influential variables are left out.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BF SKINNER: On Finance

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

B.F. Skinner did not write a textbook on modern finance, but his core theories on behaviorism and reinforcement heavily influence how experts analyze B.F. Skinner and Operant Conditioning: A Primer for Traders and understand B.F. Skinner And The Psychology Of The Markets.

Operant Conditioning and Investing

  • Hidden re-inforcers: Financial decisions are often driven by subconscious rewards like seeking approval, looking smart, or gaining power rather than an honest look at reality.
  • Costly mistakes: In investing, being wrong has tangible financial consequences. Traders must recognize when their behavior is conditioned by bad habits rather than factual truth.

Central Banks and Market Behavior

  • Conditioning investors: Federal Reserve policies act as a form of behavioral modification. Long periods of low interest rates and interventions train investors to react predictably to central bank signals.
  • Rewarding risk: When markets are consistently rewarded for specific risky behaviors, they adapt and behave exactly how policymakers condition them to act.

Economic Control and Gambling

  • Variable-ratio schedules: In his foundational writings, Skinner described gambling as a system of economic control where payoffs happen at random intervals.
  • Driven by payoffs: This unpredictable schedule keeps people turning over money because the rare, random reward is powerful enough to maintain the habit.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

FOURTH: Industrial Revolution

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

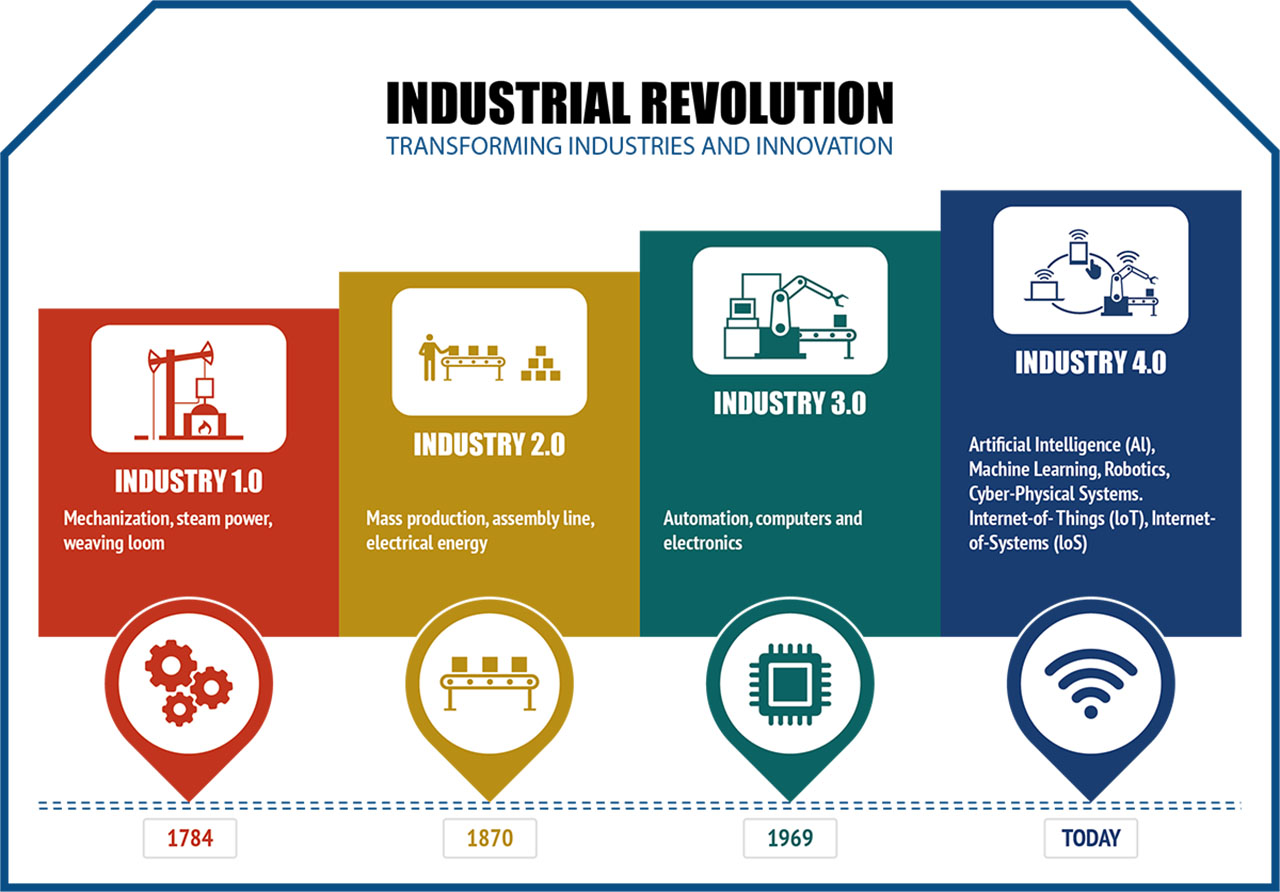
The Fourth Industrial Revolution, often called Industry 4.0, refers to the current period of rapid technological change in which digital technologies are becoming deeply integrated with industries, economies, and everyday life. Unlike previous industrial revolutions, which were driven mainly by mechanization, electricity, and mass production, the Fourth Industrial Revolution is characterized by the combination of digital, physical, and biological technologies. Artificial intelligence, robotics, the Internet of Things, big data, cloud computing, biotechnology, and advanced manufacturing are among the major technologies shaping this transformation. These developments are changing how people work, communicate, produce goods, and solve problems.

The First Industrial Revolution began in the eighteenth century with the use of steam power and mechanized production. The Second Industrial Revolution followed with electricity, assembly lines, and mass production. The Third Industrial Revolution introduced computers, electronics, and information technology, allowing many processes to become automated and digitally connected. The Fourth Industrial Revolution builds upon these earlier developments by connecting machines, data, people, and intelligent systems in increasingly sophisticated ways. Its defining feature is not simply the existence of new technologies but the way these technologies interact and reinforce one another.

Artificial intelligence is one of the most important elements of the Fourth Industrial Revolution. AI systems can analyze enormous quantities of information, recognize patterns, generate content, assist with decision-making, and perform tasks that previously required human judgment. Businesses are increasingly using AI to improve customer service, detect fraud, optimize supply chains, and automate routine activities. In healthcare, AI can support the analysis of medical images and help researchers identify potential treatments. In education, intelligent technologies can provide personalized learning experiences. These applications demonstrate how digital intelligence can influence many areas of society.

Robotics and automation are also transforming production. Modern robots are capable of performing precise and repetitive tasks quickly and consistently. Factories can use interconnected machines to monitor production and identify problems with minimal human intervention. This can increase productivity, reduce waste, and improve workplace safety in certain situations. However, automation can also change the nature of employment. Jobs involving repetitive tasks may decline, while demand for workers with technical, analytical, creative, and interpersonal skills may increase. As a result, education and lifelong learning are becoming increasingly important.

Another major feature of the Fourth Industrial Revolution is the Internet of Things, in which everyday objects and industrial equipment are connected through digital networks. Sensors can collect information about machines, vehicles, buildings, and other physical objects and transmit that information for analysis. Smart homes can automatically adjust lighting and temperature, while connected industrial systems can identify equipment problems before they cause major failures. Cities can also use connected technologies to manage transportation, energy consumption, and public services more efficiently.

The Fourth Industrial Revolution has significant potential benefits for society. New technologies can increase productivity, encourage innovation, reduce production costs, and create new industries. Digital tools can improve communication and provide access to information on an unprecedented scale. Technological advances may also contribute to solutions for major challenges such as climate change, disease, food production, and energy efficiency. For businesses, digital transformation can make it easier to develop new products and reach customers across geographical boundaries.

At the same time, this transformation creates important challenges. One concern is the potential displacement of workers whose jobs can be automated. Although technological progress can create new employment opportunities, the transition may be difficult for people whose existing skills become less valuable. Another concern is inequality. Individuals, businesses, and countries with greater access to technology, education, and investment may benefit more quickly than those without such resources. This could increase economic and social divisions if the benefits of technological development are not broadly distributed.

Privacy and cybersecurity are additional concerns. As more devices collect and exchange personal information, the amount of data available to companies and governments continues to grow. Protecting this information from misuse, theft, and unauthorized access is therefore essential. Cyberattacks against businesses, governments, hospitals, and critical infrastructure can cause serious economic and social consequences. Responsible management of data and strong cybersecurity practices are consequently important parts of the digital transformation.

The Fourth Industrial Revolution also raises ethical questions about the role of technology in human life. Decisions made with the assistance of artificial intelligence can affect employment, healthcare, education, finance, and other important areas. It is therefore necessary to consider issues such as fairness, accountability, transparency, and human oversight. Technology itself is neither automatically beneficial nor harmful; its consequences depend largely on how people design, regulate, and use it.

In conclusion, the Fourth Industrial Revolution represents a major transformation in the relationship between technology, society, and the economy. Artificial intelligence, robotics, connected devices, biotechnology, and advanced digital systems are changing how people live and work. These technologies offer significant opportunities for economic growth, innovation, and improved quality of life, but they also create challenges involving employment, inequality, privacy, cybersecurity, and ethics. The success of the Fourth Industrial Revolution will therefore depend not only on technological innovation but also on society’s ability to prepare people for change and ensure that technological progress is used responsibly. Education, adaptability, ethical decision-making, and inclusive access to technology will be essential as humanity enters an increasingly interconnected and automated future.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BUSINESS SCHOOL: The High Cost

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The High Cost of Business School has long been viewed as a pathway to professional success, higher salaries, and leadership opportunities. Many students pursue business degrees, such as a Master of Business Administration (MBA), because they believe these qualifications will help them advance their careers and achieve financial stability. However, the rising cost of business education has become a significant concern. Tuition, housing, textbooks, and other expenses can place a tremendous financial burden on students and their families. Although business school can provide valuable knowledge and career opportunities, its high cost raises important questions about affordability, accessibility, and whether the financial investment is truly worthwhile.

One of the most significant expenses associated with business school is tuition. Many business programs charge substantially more than other graduate programs, particularly those offered by well-known universities. Students attending prestigious business schools may spend tens of thousands of dollars annually on tuition alone. For those pursuing full-time MBA programs, the total cost can reach well over one hundred thousand dollars when all academic expenses are included. Even students attending less expensive institutions may struggle to afford their education. These high tuition rates can discourage qualified individuals from applying, especially those from low-income backgrounds who lack sufficient financial resources.

In addition to tuition, students must consider the cost of living while attending business school. Housing, transportation, food, health insurance, and utilities can significantly increase the overall expense. Students who attend schools in major cities often face particularly high living costs. Furthermore, full-time business programs may require students to reduce their working hours or leave their jobs entirely. As a result, they lose income while simultaneously taking on additional expenses. The combination of tuition payments and lost wages makes business school an even more expensive commitment than the published price might suggest.

Student loans are another major concern for individuals pursuing business degrees. Because many students cannot afford tuition and living expenses through savings alone, they rely on borrowed money to finance their education. Although student loans make higher education possible, they can create long-term financial obligations. Graduates may spend years repaying their loans, limiting their ability to purchase homes, start families, save for retirement, or invest in businesses of their own. The pressure to repay educational debt may also influence career choices. Instead of pursuing meaningful work or starting a company, graduates might feel compelled to accept high-paying positions simply to meet their monthly financial obligations.

***

***

The high cost of business school also raises concerns about equal access to professional opportunities. Students from wealthy families may have greater freedom to attend prestigious institutions without accumulating substantial debt. In contrast, students from lower-income households may avoid applying because they fear the financial consequences. Even when scholarships and financial aid are available, they may not cover the full cost of attendance. This situation can reinforce existing economic inequalities by giving wealthier individuals an advantage in obtaining valuable credentials, professional connections, and access to competitive career opportunities. Education should help people improve their circumstances, but excessive costs can make that goal more difficult to achieve.

Despite these concerns, business school offers several potential benefits. Students can develop important skills in management, finance, marketing, entrepreneurship, and strategic decision-making. They may also gain access to internships, career counseling, alumni networks, and employers who actively recruit graduates. For some individuals, an MBA can lead to promotions, higher earnings, or opportunities to transition into new industries. The value of a business degree, however, depends on factors such as the student’s career goals, previous experience, chosen institution, and expected salary after graduation. A degree that produces substantial career advancement for one student may offer a much smaller financial return for another.

To address the high cost of business education, universities should explore ways to make their programs more affordable. Institutions could increase need-based financial aid, offer more scholarships, expand flexible part-time programs, and provide lower-cost online options. Universities should also be more transparent about the total cost of attendance, including fees and estimated living expenses. Prospective students, meanwhile, should carefully compare programs before making a decision. They can evaluate tuition rates, graduation outcomes, employment opportunities, and potential salary increases to determine whether a particular degree justifies its cost. Alternatives such as professional certifications, specialized courses, and practical work experience may also provide valuable skills at a fraction of the price.

In conclusion, the high cost of business school presents a serious challenge for students seeking professional growth and financial success. Expensive tuition, living expenses, lost income, and student loan debt can create lasting financial difficulties. Although business education can provide valuable skills, professional networks, and career advancement opportunities, these benefits do not guarantee that every graduate will receive a sufficient financial return. Universities must work toward greater affordability, while students should make informed decisions based on their individual circumstances and long-term goals. Ultimately, business education should be an investment that expands opportunities rather than a financial burden that limits them. Making business school more accessible would allow a wider range of talented individuals to develop their abilities, contribute to the economy, and pursue successful careers without sacrificing their financial futures

***

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: FOMC Leaves Its Benchmark Interest Rate Unchanged

***

***

The Federal Reserve left its benchmark interest rate unchanged at 3.75% to 4.00% following its October 28th, 2026 meeting.

Key Details

  • The Decision: The Federal Open Market Committee (FOMC) opted to pause after raising rates by a quarter-percentage-point in September.
  • Current Rate Range: The federal funds rate remains at 3.75%–4.00%.
  • Context & Outlook: Policymakers adopted a wait-and-see stance amid persistent inflation and economic uncertainty, though financial markets continue to price in a high probability of another rate hike at the final meeting of the year in December.

COMMENTS APPRECIATED

EDUCATION: Books

***

When to Put the KIBOSH on Your Bank?

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Choosing where to keep your hard-earned money is one of the most critical financial decisions you can make. Your bank should function as a secure, efficient partner that helps you grow your wealth and manage your daily life. However, many people stay with the same financial institution for years out of habit or fear of the administrative hassle of switching. This loyalty is rarely rewarded. When a bank stops serving your best interests, introduces predatory fee structures, or falls behind technological standards, it is time to cut ties. Recognizing the signs that you need to “put the kibosh” on your bank is essential for protecting your peace of mind and your financial future.

The most immediate catalyst for leaving a bank is the sudden appearance or inflation of predatory fees. A healthy banking relationship should not cost you a premium just to access your own money. When institutions begin quietly raising monthly maintenance fees, escalating out-of-network ATM penalties, or charging exorbitant overdraft fees, they are demonstrating that their profit margins matter more than customer retention. Many modern institutions now offer completely free checking and savings accounts with no minimum balance requirements. If your current bank forces you to jump through administrative hoops or maintain a high balance just to waive a monthly fee, they are actively draining your resources. Paying to look after your own capital is a clear sign to walk away.

Beyond direct costs, look at what your money is actively earning. In a fluctuating economic landscape, interest rates on savings accounts are highly competitive. If your bank is still offering a microscopic yield—such as a fraction of a percent—while high-yield savings accounts elsewhere offer significantly more, you are losing money to inflation every single day. A bank that refuses to adjust its interest rates to reflect competitive market standards is taking advantage of your inertia. Failing to switch means you are essentially giving the bank a free loan while robbing yourself of passive compound growth.

Another unmistakable red flag is stagnant or frustrating technology. In today’s digital ecosystem, your bank’s mobile app and online portal are the primary gateways to your funds. If you regularly encounter system outages, glitchy interfaces, slow check-deposit processing, or a lack of basic security features like two-factor authentication, your bank is failing to invest in its infrastructure. A substandard digital experience is more than an annoyance; it is a direct threat to your financial agility. If an app prevents you from transferring money or monitoring fraudulent activity in real time, the institution is a liability to your daily life.

***

***

Furthermore, consider the human element: customer service. You truly discover the value of your bank when something goes wrong. If you are met with long hold times, automated phone trees that lead nowhere, unhelpful branch staff, or a refusal to waive an unfair fee, the relationship is broken. A bank should offer transparent, empathetic, and rapid support, especially when dealing with urgent matters like identity theft or erroneous charges. If trying to resolve a simple issue feels like a grueling battle against corporate bureaucracy, it is a sign that the institution does not value your business.

Finally, alignment with personal ethics and corporate stability cannot be ignored. A bank’s public reputation matters. If your institution is consistently making headlines for corporate scandals, data breaches, discriminatory lending practices, or investments that conflict with your personal values, you have every right to vote with your wallet. Your deposits provide the capital these institutions use to fund their broader initiatives. If you no longer trust management or approve of their corporate behavior, pulling your funds is the ultimate form of accountability.

Putting the kibosh on your bank can feel daunting due to the logistics of moving direct deposits and updating automatic bill payments. However, the long-term benefits far outweigh the temporary inconvenience. You deserve a financial partner that offers robust digital tools, competitive interest rates, transparent pricing, and stellar customer support. When a bank stops checking these boxes, do not let complacency hold you back. Transition your funds to an institution that respects your money and your time, and take control of your financial journey.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

NURSES: Leaving the Profession?

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Nurses are leaving the profession today in numbers that should concern anyone who cares about the stability of modern healthcare. The trend isn’t driven by a single cause but by a convergence of pressures that have made the work emotionally heavier, physically harder, and professionally less sustainable. What’s striking is that nurses still overwhelmingly love patient care; what they’re walking away from is everything that has grown around it—administrative burdens, unsafe staffing, stagnant pay, and a sense that the system depends on their sacrifice rather than their well‑being.

The most immediate driver is chronic understaffing. Hospitals and clinics have operated for years with lean staffing models that look efficient on paper but feel punishing in practice. When a unit is short even one nurse, the workload doesn’t shrink; it simply gets redistributed. That means more patients per nurse, more tasks squeezed into the same shift, and more opportunities for mistakes. Over time, this constant pressure erodes confidence and heightens stress. Many nurses describe feeling like they’re always one crisis away from being overwhelmed, and that sense of perpetual strain becomes unsustainable.

Burnout is another powerful force pushing nurses out. Burnout isn’t just exhaustion; it’s the emotional depletion that comes from caring deeply while feeling unable to provide the level of care patients deserve. Nurses often enter the profession with a strong sense of purpose, but when they’re forced to rush through assessments, skip breaks, or stay late to finish charting, that purpose starts to feel compromised. The emotional toll of witnessing suffering—especially without adequate support—adds another layer. Over time, burnout can turn even the most dedicated nurse into someone who feels detached, discouraged, or defeated.

Workplace violence has also become a disturbing reality. Nurses today face rising incidents of verbal abuse, threats, and physical aggression from patients or visitors. While healthcare has always involved challenging interactions, the frequency and intensity of these episodes have grown. When nurses don’t feel safe at work, or when incidents are brushed aside as “part of the job,” it sends a clear message that their well‑being is secondary. Many decide they’d rather leave than continue working in an environment where they feel vulnerable.

Compensation plays a role too. Despite being highly skilled professionals who shoulder enormous responsibility, many nurses feel their pay doesn’t reflect the complexity or intensity of their work. Wage growth has lagged behind rising living costs, and the gap between what nurses give and what they receive has widened. Travel nursing briefly offered higher pay and more flexibility, but even that has become less reliable as contracts shrink and rates fall. For some, leaving the profession entirely feels more rational than staying in a job where the financial rewards don’t match the demands.

Administrative overload is another frustration. Nurses spend a significant portion of their shifts documenting, clicking through electronic health records, and complying with layers of regulatory requirements. Documentation is essential, but the volume has ballooned to the point where it often competes with direct patient care. Many nurses feel like they’re drowning in paperwork, and that the human connection—the part of nursing that drew them in—is being squeezed out.

***

***

Generational shifts are also shaping the landscape. Younger nurses are less willing to tolerate the “martyrdom culture” that older generations endured. They expect work‑life balance, mental health support, and reasonable workloads. When those expectations aren’t met, they leave. Meanwhile, many experienced nurses are retiring early, taking decades of expertise with them. The profession is losing both its seasoned mentors and its new recruits, creating a dangerous gap.

Finally, nurses are increasingly exploring alternative career paths. Their skills translate well into roles in telehealth, case management, consulting, education, and even non‑clinical industries. When these options offer better hours, less stress, and more respect, the decision becomes easier.

What’s happening today isn’t a temporary fluctuation; it’s a signal. Nurses aren’t abandoning their calling—they’re rejecting a system that has made fulfilling that calling too difficult. If healthcare leaders want to reverse the trend, they’ll need to address the root causes with seriousness and urgency. Until then, nurses will continue to walk away, not because they don’t care, but because caring has become too costly.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

QUESTION: Should Elon Musk Merge Tesla and SpaceX?

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The question of whether Elon Musk should merge Tesla and SpaceX into a single industrial titan is one of the most provocative thought experiments in modern business. Together, the companies command a combined valuation deep into the trillions, dominating electric vehicles (EVs) and aerospace respectively. While a consolidation could theoretically create an unrivaled technological superpower, the operational realities, financial risks, and strategic misalignments suggest that Elon Musk should keep Tesla and SpaceX as separate entities. Splitting the companies protects their individual missions, shields them from cross-contamination of financial risk, and respects their vastly different corporate governance structures.


The Allure of the Conglomerate: Synergy and Shared Intellect

Proponents of a merger point to the undeniable technological overlap between the two firms. Tesla is an AI and robotics company disguised as an automaker. SpaceX is an advanced manufacturing powerhouse disguised as a rocket company.

  • Materials and Engineering: The two companies already share knowledge. Tesla’s Cybertruck utilizes an ultra-hard stainless-steel alloy reminiscent of SpaceX’s Starship.
  • The “Master Plan” Synergy: A combined entity could seamlessly blend SpaceX’s Starlink satellite network with Tesla’s Full Self-Driving (FSD) ecosystem, ensuring global autonomous vehicle connectivity even in the most remote areas.
  • Talent Magnets: Merging would allow Musk to fluidly deploy elite engineering talent across automotive, robotics, and aerospace projects without navigating complex inter-company consulting agreements.

While these synergies look highly attractive on paper, the practical execution of a formal corporate merger introduces severe systemic vulnerabilities.


The Capital Structure Chasm: Public vs. Private

The structural incompatibility of Tesla and SpaceX presents the most formidable barrier to a merger.

FeatureTeslaSpaceX
Market StatusPublicly traded (NASDAQ)Privately held
Primary PressureQuarterly earnings and marginsMulti-decade capital deployment
Investor MandateNear-term profitability & scaleLong-term capital appreciation

Tesla answers to public shareholders, index funds, and stringent regulatory bodies like the SEC. Its stock price is highly volatile, driven by quarterly delivery numbers and retail investor sentiment.

Conversely, SpaceX operates out of the public eye. This privacy is essential because building a multi-planetary civilization requires massive, upfront capital expenditures with no guarantee of near-term returns. If SpaceX were absorbed into public Tesla, the immense costs and spectacular, fiery testing failures of the Starship program could trigger panic on Wall Street, cratering the combined company’s stock.


Mission Drift and Execution Risk

Both companies are attempting to solve some of the hardest engineering problems in human history. Forcing them into a single corporate structure risks catastrophic mission drift.

  • Tesla’s Mission: Accelerate the world’s transition to sustainable energy.
  • SpaceX’s Mission: Make humanity a multi-planetary species.

Managing a global automotive supply chain, launching gigafactories, and achieving level-5 vehicle autonomy require intense, undivided operational focus. Simultaneously, building reusable moon rockets and colonizing Mars requires an entirely different risk tolerance and regulatory framework.

Consolidating these distinct corporate cultures into an omnibus “Musk Industries” would create an bureaucratic nightmare. The executive bandwidth required to oversee a combined entity would overextend leadership, dulling the fast-moving agility that made both startups successful in the first place.


The Contagion of Risk

In corporate finance, keeping entities separate acts as a firewall. If one company faces a severe crisis, the other remains insulated. Merging Tesla and SpaceX removes this firewall, exposing both to existential contagion.

If a systemic battery defect or an autonomous driving lawsuit heavily penalized Tesla’s balance sheet, a merged entity would have to divert capital away from rocket development to save the automotive division. Conversely, a catastrophic failure in SpaceX’s launch business could tie up the assets of the entire conglomerate, choking Tesla’s ability to fund its next-generation vehicle platforms.

By remaining independent, SpaceX can utilize private funding rounds to weather aerospace downturns, while Tesla can leverage public equity markets to scale its energy and robotics businesses.


Conclusion: Independent but Aligned

Elon Musk should not combine Tesla and SpaceX. The current model—where the companies exist as separate legal entities but maintain an informal, collaborative relationship—is highly effective. It yields all the benefits of cross-pollinated engineering and shared vision without any of the regulatory friction, public market panic, or structural liability of a formal merger.

Tesla must remain a lean, public powerhouse dedicated to transforming Earth’s energy landscape. SpaceX must remain a agile, private pioneer focused on the stars. Keeping them separate ensures that a setback in an automotive factory won’t ground a mission to Mars, and a rocket failure won’t stall the transition to clean energy.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

MY TAKE ON PRIVATE EQUITY AND VENTURE CAPITAL

By Lon Jefferies; MBA CMP™ CFP®

***

***

Private equity and venture capital investments typically involve ownership of shares in a company and represent title to a portion of the company’s future earnings. However, private equity is an equity interest in a company or venture whose stock is not yet traded on a stock exchange.

Venture capital is typically a special case of private equity in which the investment is in a company or venture that has little financial history or is embarking on a high risk/high potential reward business strategy.

Like real estate, private equity and venture capital investments generally share a general lack of liquidity and a lack of comparability across different individual investments. The lack of liquidity comes from the fact that private equity and venture capital investments are typically not tradable on a stock exchange until the company has an IPO.

The lack of comparability is due to the fact that most private equity and venture capital investments are the result of direct negotiation between the investor/venture capitalist and the existing owners of the company  /venture.

With widely divergent terms and provisions across different investments, it is difficult to make general claims regarding the characteristics of private equity and venture capital investments.

Thank You.

Lon Jefferies MBA CMP™ CFP®

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

POLITICIANS: Why So Few Doctors?

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Physicians are noticeably rare in the halls of political power, a stark contrast to the high numbers of lawyers, business executives, and career politicians who dominate legislative bodies worldwide. While medicine and politics both fundamentally aim to improve human welfare, the transition from the clinic to the capitol is infrequent. This scarcity stems from systemic friction between medical training and political life, including divergent thinking paradigms, demanding professional tracks, financial trade-offs, and contrasting ethical frameworks.

The primary barrier is the fundamental divergence in how physicians and politicians think and solve problems. Medical training instills a rigid adherence to the scientific method, evidence-based decision-making, and objective data. Physicians are conditioned to diagnose an ailment based on empirical evidence and apply a targeted, proven treatment. Politics, conversely, operates on compromise, ideological negotiation, and public opinion. Policy decisions are rarely black-and-white, and what is politically viable often clashes with what is scientifically optimal. For a clinician accustomed to objective truths, the world of political spin, partisan loyalty, and incremental policy concessions can be deeply frustrating and counterproductive.

***

***

Furthermore, the grueling timeline of a medical career leaves very little room for political aspiration. Becoming a physician requires a decade or more of intensive, all-consuming training, including medical school, residency, and fellowships. By the time a doctor establishes a stable practice, they are often in their mid-thirties or forties, deeply embedded in patient care and institutional responsibilities. Building a political career requires an equally demanding, decade-long commitment to local networking, fundraising, and campaigning. Because both fields require absolute devotion, choosing one almost entirely precludes the other during a person’s most energetic professional years.

Financial considerations also create a significant disincentive for doctors considering public office. Physicians invest massive amounts of capital into their education and often carry substantial student loan debt well into their careers. Once practicing, they earn high salaries that reflect their specialized skill sets. Stepping away from medicine to run for office introduces immense financial risk. Campaigns are expensive and offer no guarantee of success. Even if elected, legislative salaries—particularly at the state or local level—frequently pale in comparison to a physician’s earning potential. For many, the financial sacrifice of abandoning a medical practice is simply too steep.

The core ethical frameworks of the two professions also stand in direct opposition. Physicians swear the Hippocratic Oath, which dictates a primary, uncompromising duty to the individual patient sitting in front of them. This creates a deeply personalized relationship rooted in trust and immediate advocacy. Politicians, however, must focus on utilitarian ethics, making decisions that affect thousands or millions of people simultaneously. In politics, benefiting the majority often means compromising the interests of a minority. This macro-level trade-off can feel intensely uncomfortable for a physician trained to view every single human life as an absolute priority.

***

***

Additionally, the public nature of modern politics acts as a powerful deterrent. Physicians operate in private, highly confidential environments protected by strict legal and ethical boundaries. They are respected authorities within their communities, viewed through a lens of clinical objectivity. Entering the political arena subjects an individual to intense public scrutiny, hyper-partisan vitriol, and the deliberate distortion of their character or past statements. Many doctors are unwilling to jeopardize their hard-earned professional reputation and private family life for the polarizing chaos of public campaigns.

Ultimately, the scarcity of physician-politicians is a structural issue rather than a lack of civic interest. The institutional pathways of medicine and governance pull individuals in entirely opposite directions. While society misses out on valuable scientific literacy and public health expertise in its legislatures, the demanding nature of healing individual patients keeps most doctors firmly rooted in the clinic rather than the campaign trail.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

POLITICIANS: Why So Many Attorneys?

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The connection between the legal profession and political leadership is as old as modern democracy itself. Across the globe, and particularly in nations like the United States, a disproportionately high number of legislators, governors, and heads of state hold law degrees. While critics sometimes view this relationship with skepticism, the dominance of attorneys in politics is neither accidental nor purely driven by ambition. Instead, it is the natural byproduct of a shared foundational architecture: both fields revolve around the creation, interpretation, and application of the rules that govern human society.

At its core, politics is the art and science of making laws. Therefore, the most direct explanation for why so many politicians are lawyers is that law school provides the exact technical training required for governance. Legislators are tasked with drafting statutes, evaluating constitutional boundaries, and closing regulatory loopholes. An individual without legal training may understand the broad social intent of a policy, but an attorney understands how that policy will interact with existing judicial frameworks. They can anticipate how a judge might interpret a specific clause or how a corporate entity might exploit a loosely worded sentence. This technical literacy makes lawyers uniquely equipped to step into a legislative role and become immediately effective.

Beyond technical knowledge, the day-to-day skills developed in legal practice translate perfectly to political campaigning and governance. Lawyers are professional advocates trained in the art of persuasion. Whether standing before a jury or a room full of voters, an attorney’s job is to take a complex set of facts, build a compelling narrative, and convince an audience to agree with their position. This mastery of rhetoric is invaluable in politics. Furthermore, legal training emphasizes analytical thinking and the ability to argue both sides of an issue. This structured approach to problem-solving allows lawyer-politicians to dissect public policy debates, anticipate their opponents’ counterarguments, and navigate intense public scrutiny with composure.

***

***

The structure of the legal career itself also creates a natural pathway to public office. Unlike professions that require rigid hours or constant physical presence—such as medicine, engineering, or corporate management—the legal profession offers the flexibility and institutional support necessary to run for office. Many law firms view having a partner or associate in public office as a prestigious asset that elevates the firm’s profile and expands its network. Consequently, firms are often willing to accommodate a lawyer’s political aspirations by granting leaves of absence or allowing part-time schedules during campaign seasons. Additionally, practicing law naturally exposes individuals to local community leaders, business owners, and civic organizations, providing a ready-made network of potential donors and supporters.

From a historical perspective, the legal path has long been established as the traditional route to societal leadership. Historically, the law was one of the few fields that granted individuals a deep understanding of state mechanisms and civil rights. This legacy has created a self-perpetuating cycle. Young, politically minded individuals frequently choose to attend law school precisely because they see it as the proven credential for a political career. As a result, the legal field constantly attracts highly ambitious, civic-minded talent, ensuring a steady pipeline of lawyers entering the political arena.

Ultimately, the heavy concentration of attorneys in politics stems from a fundamental alignment of purpose. Politics is the mechanism through which society debates its values, and the law is the tool used to enforce them. While a healthy democracy benefits from a diverse legislature comprising scientists, educators, and business owners, the structural advantages of a legal background ensure that attorneys will remain central to public governance. Their training in systemic thinking, persuasive communication, and institutional mechanics makes them uniquely suited to navigate the complex machinery of modern government.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR ESSAYS AND TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BOOK REVIEW: Financial Planning for Doctors

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

“COMPREHENSIVE FINANCIAL PLANNING STRATEGIES FOR DOCTORS AND ADVISORS”

This is an excellent major 800 page text book on financial planning for physicians, health professionals and their financial advisors. It is all inclusive yet very easy to read with much valuable information. And, I have been expanding my business knowledge with all of team Marcinko’s prior books.

I highly recommend this one, too. It is a fine and specific educational tool for all physicians and medical professionals.

Thank You.

David B. Lumsden MD MS MA

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR POSTS & TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

UNIVERSITY PROFESSORS: Who Dislike Teaching?

By Dr. David Edward Marcinko; MBA MEd

By Professor Eugene Schmuckler: PhD MBA MEd CTS

SPONSOR: http://www.MarcinkoAssociates.com

***

***

While university professors are often envied for their intellectual freedom, flexible schedules, and perceived ivory-tower prestige, a stark reality has emerged in modern academia: an increasing number of professors actively dislike teaching. While most entering the profession are fueled by a genuine love for their discipline, the structural, cultural, and financial shifts in higher education have transformed the classroom from a sanctuary of learning into a major source of professional burnout.

The primary driver of this dissatisfaction is the “publish or perish” culture that dominates modern universities. At most major institutions, tenure, promotions, institutional funding, and professional respect are tied almost exclusively to research output, grant acquisition, and journal publications. Teaching, by contrast, is rarely rewarded. This creates a severe misalignment of incentives. A professor who spends dozens of hours crafting an innovative syllabus, mentoring struggling students, and providing detailed feedback on essays receives no structural rewards. In fact, devoting too much time to teaching can actively jeopardize their career advancement. Consequently, teaching is frequently viewed not as a core mission, but as a burdensome distraction from the research that actually secures their livelihood.

Furthermore, the dramatic shift toward corporate-style university administration has changed how students and classes are viewed. Higher education increasingly operates on a consumer model, where the student is the customer and the degree is a purchased commodity. This consumer mentality degrades the traditional professor-student dynamic. Professors find themselves dealing with an unprecedented rise in entitlement, grade inflation pressures, and demands for constant accommodations. When a student views a course as a transaction rather than an intellectual challenge, the professor is reduced to a service provider. Administrative pressure to maintain high retention rates and positive student evaluations further compromises academic rigor. Professors are often forced to choose between lowering their standards to keep students happy or maintaining rigor and risking administrative reprimand.

***

***

This problem is compounded by a perceived decline in student engagement and preparation. Many professors express profound frustration with a shifting classroom culture defined by technological distractions and systemic apathy. Competing with smartphones, laptops, and artificial intelligence for a student’s attention has made lecturing an exhausting uphill battle. Additionally, many educators note that incoming students frequently lack basic critical thinking, reading comprehension, and writing skills, requiring professors to spend valuable lecture time on remediation rather than advanced concepts. Teaching becomes deeply demoralizing when a professor realizes that a significant portion of the class is physically present but intellectually absent.

The situation is even more acute for the vast, invisible army of adjunct and non-tenure-track faculty, who now teach the majority of undergraduate courses. For these instructors, the dislike of teaching is tied directly to systemic exploitation. Adjuncts are paid poverty-level wages per course, receive no health benefits, and have zero job security from one semester to the next. Many are forced to “freeway fly,” juggling teaching loads across multiple campuses just to pay rent. When teaching is tied to extreme financial anxiety, substandard working conditions, and a total lack of institutional support, it inevitably transforms from a calling into an exhausting chore.

Finally, the administrative burden placed on educators has skyrocketed. Teaching a class no longer means just lecturing and grading. It now involves navigating complex learning management systems, responding to a relentless deluge of emails at all hours of the night, filing extensive assessment reports for accreditation, and managing fraught interpersonal dynamics. The actual act of teaching—the joyful exchange of ideas—has been completely overshadowed by bureaucratic paperwork and digital maintenance.

In conclusion, college professors do not dislike teaching because they lack passion for education. They dislike teaching because the modern university system has devalued, bureaucratized, and stripped the joy out of the classroom experience. When research is the only currency that matters, students behave like consumers, and administrative red tape multiplies, teaching ceases to be an intellectual pursuit. Until higher education rebalances its priorities to genuinely value and support pedagogical excellence, the classroom will continue to be a place of frustration rather than inspiration.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

DIS-ECONOMIES of Scale

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

****

Diseconomies of scale occur when a business grows beyond a certain size and its average cost of production begins to increase. In the early stages of expansion, firms often benefit from economies of scale because producing more goods can reduce the average cost per unit. However, continued growth does not always lead to greater efficiency. When an organization becomes too large, managing its resources, employees, and operations can become difficult and expensive. The resulting increase in average costs is known as diseconomies of scale.

One major cause of diseconomies of scale is the difficulty of managing a large organization. As a business expands, it usually requires more managers and supervisors. The organizational structure can become complicated, with several levels of management between senior leaders and ordinary employees. This can slow down decision-making because information has to pass through many departments and levels of authority. As a result, decisions that could be made quickly in a small firm may take much longer in a large organization. Delays can increase costs and reduce the firm’s ability to respond to changes in the market.

Another important cause is communication problems. In a small business, employees can often communicate directly with owners and managers. In a large business, communication may involve different departments, offices, and management levels. Important information can be misunderstood, delayed, or lost as it moves through the organization. Poor communication may lead to mistakes, duplication of work, and inefficient use of resources. The larger the organization becomes, the more difficult it may be to maintain clear and effective communication.

Diseconomies of scale can also result from reduced employee motivation. In a small firm, workers may feel that their contribution has a direct impact on the success of the business. They may have closer relationships with managers and receive more personal recognition. In a very large organization, employees can sometimes feel that their individual efforts are less important. This may reduce motivation and productivity. If workers become less productive, the cost of producing each unit of output may increase.

Another factor is the difficulty of controlling operations. Large firms often operate across several factories, offices, or locations. Coordinating these different activities requires additional systems, technology, managers, and administrative staff. The business may also need to spend more money on monitoring employees and maintaining consistent standards. Although these systems can be necessary for a large organization, they can increase operating costs.

Diseconomies of scale may also arise because of limited resources. As a firm expands, it may place greater pressure on its suppliers, transportation systems, machinery, and other resources. For example, a company that rapidly increases production may experience shortages of raw materials or difficulties transporting finished products. These problems can cause delays and increase production costs. In some industries, rapid expansion may also lead to higher wages because the firm must compete for skilled workers.

The effects of diseconomies of scale can be significant. When average costs increase, a firm’s profitability may decline if it cannot increase its prices without losing customers. Higher costs can also make the business less competitive. In addition, inefficient management can reduce the quality of products and services. If customers become dissatisfied, the firm may lose sales and market share.

****

***

However, diseconomies of scale do not mean that large businesses are always inefficient. Many large firms develop methods to control the problems associated with growth. They may divide the organization into smaller departments or business units, improve communication systems, delegate decision-making, and use technology to coordinate operations. Effective management can therefore reduce the impact of diseconomies of scale.

In conclusion, diseconomies of scale occur when the expansion of a firm causes its average cost per unit to rise. They are mainly associated with problems such as complex management structures, communication difficulties, reduced employee motivation, weak coordination, and increasing administrative costs. While growth can provide many advantages, excessive expansion can create inefficiencies that make production more expensive. For this reason, businesses need to balance the benefits of growth with the challenges that come with becoming too large. Efficient organization, effective communication, and appropriate management are essential for controlling costs and maintaining productivity as a business expands.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE: Financial Planning for Physicians and Advisors

INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

PHYSICIANS: Why Some May Practice for Free

By Dr. David Edward Marcinko; MBA MEd

By Eugene Schmuckler; PhD MBA MEd CTS

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The phenomenon of physicians choosing to provide medical care without financial compensation is one of the most profound expressions of altruism within modern society. In an era where healthcare is increasingly institutionalized, commercialized, and driven by complex insurance reimbursement models, the decision of a doctor to work for free stands as a stark contrast. This practice manifests in various forms, including local community free clinics, international humanitarian missions, disaster response efforts, and pro bono care within private practices. Understanding why physicians willingly forgo financial reward requires looking beyond economic incentives to explore the deeply rooted ethical, psychological, systemic, and historical motivations that define the medical profession.

At the core of a physician’s decision to work for free is the foundational ethos of medicine itself: the historical and moral commitment to heal. When entering the profession, doctors take an oath—most traditionally the Hippocratic Oath—which binds them to a duty of service and the preservation of human life. For many practitioners, this oath is not a mere formality or a historical artifact; it is a living moral compass. In daily modern practice, however, systemic pressures can obscure this primary purpose. Administrative burdens, electronic health record charting, and billing negotiations often distance doctors from direct patient care. Offering free care allows physicians to strip away these bureaucratic layers and return to the purest form of the doctor-patient relationship, where the sole objective is to alleviate suffering regardless of a patient’s financial status.

Furthermore, providing free care serves as a powerful mechanism to combat healthcare disparities and systemic failures. In many nations, despite legislative efforts, large segments of the population remain uninsured, underinsured, or marginalized due to socioeconomic status, legal status, or geography. Physicians working in free clinics or community health centers witness firsthand the devastating consequences of untreated chronic conditions and delayed care. Driven by a sense of social justice, these doctors view their medical skills not just as a source of income, but as a public resource. By volunteering their time, they attempt to patch the holes in a fractured safety net, ensuring that vulnerable populations—such as the homeless, undocumented immigrants, and the working poor—receive the dignity of medical attention.

***

***

The motivation to work without pay is also deeply linked to the psychological and emotional well-being of the physicians themselves. Professional burnout is a pervasive crisis in contemporary healthcare, characterized by emotional exhaustion, depersonalization, and a reduced sense of personal accomplishment. Many doctors report that the commercial pressures of productivity metrics, such as seeing a specific number of patients per hour, erode their sense of professional fulfillment. Engaging in volunteer medical work often acts as an antidote to this burnout. Free from the constraints of insurance guidelines and time clocks, physicians can practice medicine at a slower, more compassionate pace. The gratitude of a patient who has been ignored by the formal healthcare system provides a profound psychological reward that financial compensation cannot replicate, effectively reigniting the doctor’s original passion for the calling.

On a global scale, international humanitarian work draws physicians to volunteer in conflict zones, refugee camps, and developing countries. Organizations like Doctors Without Borders or various surgical missions rely entirely on the willingness of medical professionals to donate their expertise under hazardous and resource-limited conditions. The drive to participate in these initiatives often stems from a desire to face unique clinical challenges and to make a high-impact difference where medical infrastructure is non-existent. In these environments, a single surgical procedure or a basic course of antibiotics can be entirely life-altering. The chance to save lives on such a fundamental level provides an intense sense of purpose and perspective that alters a clinician’s outlook for the rest of their career.

Finally, the culture of mentorship and education within medicine encourages volunteering. Senior physicians frequently work for free in teaching clinics to train medical students and residents. Through this practice, they model empathetic care and instill a sense of civic responsibility in the next generation of healers. This legacy of giving back ensures that the tradition of humanitarian medicine is passed down, reinforcing the idea that a doctor’s worth is measured by their impact on human health rather than their financial accumulation.

In conclusion, physicians work for free because medicine, at its heart, remains a vocation rather than merely a career. While financial compensation is necessary to sustain the infrastructure of healthcare and reward years of rigorous training, it is the intangible rewards that sustain the soul of the practitioner. Whether driven by ancient ethical vows, a pursuit of social justice, a desire to reconnect with the pure joy of healing, or a urge to help global populations in crisis, these doctors demonstrate that the true currency of medicine is compassion. In doing so, they provide a vital reminder of the enduring humanity that underpins the art of healing.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

COMPENSATION: Physicians, Dentists, Podiatrists and Chiropractors

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The healthcare sector comprises a diverse ecosystem of professionals, each dedicated to diagnosing, treating, and managing human ailments. Among these, allopathic and osteopathic physicians (MDs/DOs), dentists (DDS/DMDs), podiatrists (DPMs), and chiropractors (DCs) represent distinct pathways of specialized care. While all these professionals undergo rigorous doctoral-level training, their economic realities diverge significantly. The differences in their average annual salaries, starting compensation, and lifetime earning potential are shaped by a complex interplay of educational investment, clinical specialization, practice ownership models, insurance reimbursement structures, and market demand.

Physicians consistently command the highest compensation within this cohort, reflecting their extensive training and broad clinical responsibility. After completing four years of medical school, physicians must undergo three to seven years of residency training, and often additional fellowships. This massive investment of time yields substantial financial returns. Primary care physicians, including family medicine and pediatric specialists, typically earn highly competitive six-figure salaries. However, the true divergence in medical compensation appears within surgical and procedural specialties. Specialists such as orthopedic surgeons, cardiologists, and neurosurgeons often command salaries that double or triple those of their primary care peers. This premium is driven by the high complexity of their procedures, the intense nature of their on-call responsibilities, and the heavy reliance on hospital-based reimbursement systems.

Dentists occupy a unique and highly lucrative niche within healthcare economics. Graduating after four years of dental school, general dentists have the option to enter private practice immediately without mandatory residency training. General dentists earn robust salaries that position them firmly in the upper echelons of high-earning professionals. The financial trajectory climbs even higher for dental specialists, such as oral and maxillofacial surgeons, orthodontists, and periodontists, who complete additional years of residency. A major driver of dental compensation is the business model; a high percentage of dentists own or partner in private practices. This allows them to capitalize on business equity and profit margins, rather than relying solely on a fixed salary. Furthermore, dentistry benefits from a more favorable insurance environment, featuring higher cash-pay rates and less administrative friction than traditional medical billing.

***

***

Podiatrists, specialized physicians focusing exclusively on the foot, ankle, and lower extremity structures, earn salaries that generally align comfortably with primary care medical doctors. Their training paradigm is remarkably similar to traditional physicians, requiring four years of podiatric medical school followed by a mandatory three-year surgical residency. Despite this intensive surgical training, average podiatric compensation tends to lag behind mainstream medical specialties like orthopedic surgery. This disparity is often attributed to a narrower scope of practice and historical differences in how healthcare systems and insurance providers value podiatric services compared to general orthopedic care. Nevertheless, podiatrists who establish successful private surgical practices or integrate into large, multidisciplinary orthopedic groups can significantly outpace average salary benchmarks.

Chiropractors, who focus on non-invasive, neuromusculoskeletal care through spinal adjustments and holistic therapies, occupy a markedly different economic tier. Completing a four-year doctor of chiropractic program, these professionals typically do not undergo mandatory post-graduate residency. The average salary for chiropractors is notably lower than that of physicians, dentists, and podiatrists. Chiropractors operate heavily within a cash-pay or limited-insurance reimbursement framework, as major health insurance plans and government programs provide more restricted coverage for chiropractic care compared to medical or dental procedures. Because the vast majority of chiropractors are solo practitioners or independent contractors, their income is directly tied to patient volume, marketing efficacy, and local competition, leading to a much wider variance in earnings from low-income earners to highly successful clinic owners.

***

***

The foundational driver of these salary differences is the structure of insurance reimbursement. Physicians and podiatrists rely heavily on complex insurance networks, Medicare, and Medicaid, where reimbursement rates are strictly regulated and heavily favor procedural or surgical interventions over diagnostic care. Dentists operate on a hybrid model, utilizing specialized dental insurance that frequently requires significant out-of-pocket patient co-pays, granting providers greater pricing flexibility. Chiropractors face the most stringent insurance limitations, forcing them to adopt retail-style business models where income is generated directly from consumer wallets.

Ultimately, while all four professions demand a high level of dedication and doctoral education, their financial landscapes are far from uniform. Physicians and dentists remain the financial anchors of the healthcare industry, leveraging deep systemic integration and ownership models to secure top-tier compensation. Podiatrists maintain a steady, highly specialized mid-to-high income tier, while chiropractors experience the highest income volatility, dependent on entrepreneurial skill rather than institutional salary structures. Each field presents a distinct trade-off between the years of training required, the autonomy of practice, and the ultimate financial reward.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Speaker’s Bureau

****

***

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner.

All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

EDUCATION: Books

***

***

THEORY: Economic Relativity

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The theory of economic relativity is a conceptual lens that treats economic behavior, value creation, and market outcomes as dependent on the observer’s position, incentives, and temporal perspective. It borrows the spirit—not the mathematics—of Einstein’s relativity to explain why economic truths shift across individuals, institutions, and nations. In this framework, there are no absolute economic constants. Instead, every economic variable—growth, scarcity, productivity, even rationality—changes depending on who is measuring it, when they are measuring it, and what constraints shape their world.

Relativity of Economic Perspective

Economic relativity begins with a simple premise: economic reality is not uniform. A policy that benefits one group may burden another. A price change that signals opportunity for one business may signal crisis for another. The same economic environment produces different lived experiences depending on the observer’s position within it.

A household earning $40,000 interprets inflation as a direct threat to survival. A corporation with global supply chains interprets inflation as a strategic variable to be hedged or exploited. A government interprets inflation as a macroeconomic force to be managed through policy. Each observer is responding to the same phenomenon, but their conclusions differ because their frames of reference differ.

Economic relativity argues that these differences are not noise—they are the system. To understand any economic outcome, one must first understand the observer’s position.

***

***

Time as an Economic Dimension

In physics, relativity reshapes our understanding of time. In economics, time is the most powerful determinant of value, cost, and opportunity. Every economic decision is shaped by the time horizon of the decision-maker.

Short-term actors—day traders, gig workers, small businesses—experience the economy as volatile, fragile, and dominated by immediate constraints. Long-term actors—governments, pension funds, multinational corporations—experience the economy as cyclical, structural, and governed by slow-moving forces.

The same investment can be reckless for a short-term actor and prudent for a long-term one. The same policy can be painful in the short run but beneficial over decades. Economic relativity asserts that time does not merely influence economic outcomes; it defines them.

Relativity of Scarcity and Abundance

Scarcity is often treated as an objective condition, but economic relativity reframes it as contextual and observer-dependent. What is scarce for one group may be abundant for another.

A developing nation may experience capital scarcity, while a wealthy nation experiences capital surplus. A rural community may experience labor scarcity, while an urban center experiences labor oversupply. A startup may experience attention scarcity, while a celebrity brand experiences attention abundance.

Scarcity is not a universal constant. It is relative to geography, technology, institutions, and social structure. This relativity explains why economic strategies that succeed in one environment fail in another.

Incentives as Economic Gravity

In Einstein’s universe, gravity bends space-time. In economics, incentives bend behavior. They shape how individuals and institutions interpret information, allocate resources, and respond to uncertainty.

Workers respond to wage incentives. Firms respond to profit incentives. Governments respond to political incentives. Investors respond to return incentives. These incentive structures create “economic gravity wells” that pull decisions in predictable directions.

Economic relativity argues that no economic model is complete without mapping these incentive fields. They distort economic space just as gravity distorts physical space.

***

***

Information and the Observer Effect

Economics is filled with feedback loops. Expectations influence behavior, and behavior influences outcomes. In this sense, the theory of economic relativity incorporates an observer effect: the act of observing or predicting economic conditions changes those conditions.

If consumers expect prices to rise, they buy more today, causing prices to rise. If investors expect a recession, they reduce risk, increasing the likelihood of recession. If businesses expect demand to fall, they cut production, causing demand to fall.

Economic systems are not passive—they react to observation. This relativity of expectation explains why forecasting is both essential and inherently destabilizing.

Relativity of Value and Productivity

Value is often treated as intrinsic, but economic relativity argues that value is relational. It depends on the observer’s needs, alternatives, and constraints.

A piece of land may be valuable to a farmer but worthless to a software company. A patent may be priceless to a pharmaceutical firm but irrelevant to a restaurant. Productivity itself is relative: a worker’s output depends on tools, training, environment, and institutional support.

Economic relativity reframes value as a dynamic relationship rather than a fixed property.

Implications for Economic Decision-Making

The theory of economic relativity encourages a more nuanced approach to economic analysis:

  1. Identify the observer’s frame of reference. Economic behavior cannot be understood without understanding the actor’s incentives, constraints, and time horizon.
  2. Recognize that economic truths are not universal. What is rational, efficient, or optimal depends on the observer’s position.
  3. Avoid one-size-fits-all policies. Policies must be tailored to the relative conditions of different groups and regions.
  4. Embrace dynamic interpretation. As conditions change, economic truths shift. Flexibility is essential.

Conclusion

Economic relativity reframes the economy as a system without absolute constants. Value, scarcity, risk, and opportunity shift depending on the observer’s position, just as time and space shift in Einstein’s universe. This perspective does not replace traditional economics—it enriches it. It reminds us that economic systems are human systems shaped by differing goals, incentives, and constraints. To understand the economy, we must first understand the observer.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

DE-BANKING: Defined

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Debanking is the practice where banks close accounts of individuals or organizations they perceive as posing financial, legal, regulatory, or reputational risks. This can lead to significant consequences, including loss of access to essential financial services.

Understanding De-Banking

Debanking refers to the closure of bank accounts by financial institutions that perceive the account holders as posing various risks. These risks can be financial, legal, regulatory, or reputational. The practice can have severe consequences for individuals and organizations, often leading to a loss of access to essential financial services.

Types of Debanking

Debanking can be categorized into two main types:

TypeDescription
Operational DebankingThis occurs when a bank decides to close an account based on its internal policies or customer behavior, such as repeated overdrafts or contract violations.
Governmental DebankingThis happens when banks are pressured by government entities to close accounts, either through direct orders or regulatory pressures.

Consequences of Debanking

The impact of debanking can be significant:

  • Loss of Access: Individuals may suddenly find themselves unable to make payments or receive funds.
  • Reputational Damage: Being debanked can harm an individual’s or organization’s reputation, making it difficult to secure banking services elsewhere.
  • Financial Exclusion: Those affected may struggle to access basic banking services, leading to broader financial instability.

Recent Developments

In recent years, there has been increased scrutiny of debanking practices, particularly regarding accusations of discrimination based on political or religious beliefs. For instance, investigations in the UK revealed that banks were closing accounts at an alarming rate, prompting calls for regulatory reforms to ensure fair treatment of all customers.

In the United States, an executive order was issued to protect individuals from being debanked for their political affiliations, aiming to curb what is seen as politicized debanking practices. This order mandates that banks provide clear reasons for account closures and prohibits using reputational risk as a justification.

Understanding debanking is crucial as it highlights the balance between risk management for banks and the need for fair access to financial services for all individuals.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

PARADOX: Money Stress

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The Money Stress Paradox suggests that 70% of participants believe not having to stress out and be anxious over money is more important than having more money than most people they know.

Example: The long-term median saving rate in America is only 5%. If Americans truly believed wealth is not having be anxious and to stress over money, Americans would save a greater percentage of their income. All prospecting must understand this dilemma.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Kevin Warsh Speaks

***

***

  • Fed Chair Kevin Warsh, in his speech Friday in Bangkok, declined to offer clues on whether there will be an interest rate hike again this month.
  • He acknowledged a “synchronous tightening” by central banks around the world, saying there are “no free riders.”
  • He expressed optimism that artificial intelligence will make economies that use it well more productive and wealthier, warning the road there will be “very bumpy.”

COMMENTS APPRECIATED

EDUCATION: Books

***

INVESTING: Don’t Make These Financial Mistakes

By Dr. David Edward Marcinko; MBA MEd

***

SPONSOR: http://www.MarcinkoAssociates.com

***

Don’t make these top ten investing mistakes

The days of fat profit margins for physicians are over. Medical cost containment policies in some form or another are here to stay. You’re working harder than ever, so there’s more at stake now in ensuring you don’t make investment mistakes. And, of course, physicians do make them.

Case in point: the sad tale of Debasis Kanjilal, a New York pediatrician who put more than $500,000 into the dot-com company InfoSpace upon the advice of Merrill Lynch’s star analyst Henry Blodget. The company crashed, the analyst was sued, and Merrill settled out of court. Other analysts were involved in similar public fiascos.

Kanjilal committed two common investing mistakes — trusting Wall Street and trusting one’s financial adviser implicitly. They are among the 10 most common investment mistakes made by physicians, according to Eugene Schmuckler, PhD, director of behavioral finance for the Institute of Medical Business Advisors, Inc. They are outlined here, with a treatment plan for preventing each one.
 
Not having an Investment  Policy Statement

Just as we physicians wouldn’t think of treating a patient without a careful history and physical examination, you should not invest your hard-earned capital without an Investment Policy Statement (IPS).

An IPS details what you want your money to do for you, and who is responsible for achieving those goals. It may be three to five pages for an individual physician, 10 to 15 pages for a small medical group retirement plan, or dozens of pages for a clinic or hospital endowment fund.

A properly written IPS should contain the following parts:

  • Statement of purpose
  • Statement of responsibilities
  • Investment goals and objectives
  • Proxy voting policy
  • Trading and execution guidelines
  • Asset mix guidelines 
  • Social policies or other restrictions
  • Portfolio limitations
  • Performance review benchmarks
  • Administration and fee policy
  • Communication policy
  • Reporting policy

Most stockbrokers, insurance salesmen, full service, discount, or Internet brokerage firms do not create IPSs. This is a document you can develop with your financial adviser.

Recommendations tailored to you

Not diversifying/losing sight of portfolio objectives

Although the media frenzy of a few years ago has subsided with the more recent slowdown on Wall Street, anecdotes of easy money are still out there and doctors may forget that investment portfolios serve a specific purpose (e.g., retirement, college funding, etc.) within the context of a broader financial plan. Moreover, a single investment may become too large or too small a portion of the portfolio as a result of market growth in one component or slack in another.

Diversify, monitor your holdings, and select components with your risks and goals in mind. Diversification can reduce portfolio risk. Consider investing in sectors such as basic materials, capital goods, communications and services, technology, consumer cyclicals and noncyclicals (such as pharmaceuticals, alcohol, and cigarettes), healthcare, energy, financial services, and utilities. Do not forget about cash equivalents, treasuries, zero coupon and municipal bonds, and international securities.

Forgetting the investing risk/return tradeoff

Some physicians fall into the trap of chasing “hot” investment products promising the highest returns.

Beware of projecting forward historical averages. The stock market is inherently volatile and, while it is easy to rely on past historical averages, there are long periods of time when returns regress from their long-term historical mean. But don’t let that discourage you. Slumps eventually self-correct, so you should continue a prudent investing plan.

Also, do not confuse investing with trading or speculation. There are momentum-driven market periods when investors start to believe that profits are easy and that there is always a “greater fool” to buy at a higher price. Such trading and speculation are high-risk propositions that have more in common with gambling than investing. Avoid market timing and the urge to jump in or out of the market at every economic hiccup.

Failure to recognize the effect of taxes

An attractive investment and a slick sales pitch sometimes hide the underlying tax costs of the investment. Pay your taxes and do not let the “tax tail wag the investing dog.” Strive for legitimate tax reductions and avoidance.

Failure to recognize the effect of fees and expenses

Front-end loads, back-end loads, disappearing loads, commissions, advertising, and sales expenses can all have significant impact on your investment program.

Monitor the costs of your investment program to ensure that total costs are known, reasonable for the services provided, and are not consuming a disproportionate amount of the investment returns. Carefully consider full-service versus discount brokerages.

Take care using so-called discretionary “Assets Under Management” (AUM) accounts where you pay some percentage for personalized money management. More often than not, these one-size-fits-all accounts are aggregated under a larger umbrella to automatically harvest economies of scale, so the notion that the adviser is sitting on the same side of the investment table as you begins to deteriorate upon critical reflection.

For example, in a 2 percent AUM program of $1 million, you may pay $20,000 annually that is automatically deducted from the account. So are these “perks” worth, say, $200,000 over the course of a single decade? During the “golden age of medicine” in the ’80s, or the raging bull market of the ’90s, some doctors may have said yes. But what about during a bear market, or the projected market of lower-than-average returns that may be upon us?

Avoiding appropriate risk-management techniques/equating insurance products with investment vehicles

Traditionally, physicians protected their families and practices with whole life, disability, malpractice, and business interruption insurance. But insurance products are not investment vehicles; they merely indemnify against catastrophic economic losses that typically are extinguished over time.

Behavioral economists suggest we tend to experience financial losses more intensely than gains. Physicians might prefer vehicles like the guaranteed minimum death benefit of variable annuities, the certainty that comes with disability or long-term care insurance, or traditional cash-value life insurance policies. But be alert to the associated higher costs, huge commissions, and lower returns. And beware of fear-mongering insurance salesmen.

Be open to new ideas that identify and provide solutions to the insurance problems of physicians. One chilling thought suggested by Yale University economist Robert J. Shiller, PhD, in his classic book, The New Financial Order: Risk in the 21st Century, is protection from the “gratuitous random and painful inequality” of selecting the wrong profession. The solution? “Livelihood insurance,” framed as a risk management contract.

Trusting Wall Street

Some stockbroker salesmen and big brokerage houses that underwrite and recommend stocks may have credibility problems, and physicians can get burned with the adrenaline rush of “self-directed” portfolios. Think tech stocks, Enron, WorldCom, HealthSouth. But for some previously “burned” physicians, it is almost as difficult to go it alone as it is to secure professional advice.

Be aware of the four most dangerous words on Wall Street: “This time it’s different.” We recommend using an independent financial adviser, fee-based, or fee-only adviser who charges by the hour, engagement, or pro re-nata for advice.

***

***

Not developing a comprehensive financial plan

While many doctors have an investment portfolio, few have a comprehensive personal financial plan, especially one designed for medical professionals. Typically such plans consider the risk-tolerance and timeframe of several standard components, such as insurance, taxation, investing, retirement, and estate planning. For today’s practicing physicians however, attention should also be directed toward medical practice enhancement activities, contemporaneous risk management concepts, practice appraisal determinations, and medical practice succession planning. All should be interrelated in an economically sound manner not counterproductive to individual components of the plan.

Trusting your financial adviser carte blanche

Just as the prime duty of a physician is to his patients, the prime duty of a financial adviser should be to clients. Yet the very terms financial adviser, financial planner, or investment adviser have no real academic or consistent meaning in the industry. The only hurdle to becoming one is passing a simple securities industry, or state insurance sales licensing examination. Commissioned stockbrokers are fine to use if their fees and intentions are transparent, and they offer value to you.

If you receive advice from a stockbroker, he should be responsible for it, just as we physicians are liable for our medical diagnosis and treatment plan. Perhaps the ancient medical motto omnia pro aegroto should become the new financial services credo omnia pro doctor (all for the doctor-client)?

Selecting the wrong financial or investment adviser

Worry and depression from high management fees, poor investing results, unreturned phone calls, generic advice and sales forms, cold-calls and seminars, high-pressure sales tactics, rapid financial adviser turnover, etc. You deserve better.

Select a financial adviser who takes pride in his fiduciary responsibility, knows the medical profession, and eschews product sales commissions whenever possible. To determine if your current adviser is working for you, just ask to see the documents below:

  • Form ADV Parts I and II for state and/or SEC registration and cost transparency.
  • Sample Investment Policy Statement.
  • Registered Investment Advisor or Series # 65 investment advisory license, which shows fiduciary responsibility.
  • Certified Financial Planner license number, which will show completion of a 24-month course of study at an accredited institution and successful passage of the two-day, comprehensive Certified Financial Planner Board of Standards Examination. This test encompasses all aspects of the financial planning process, including economics, insurance, taxation, investments, and retirement benefits planning. For more information, go to www.FPANet.org.
  • Certified Medical Planner license number, which will show completion of a 500-hour program that integrates healthcare-specific financial planning material with medical practice management principles like leadership skills and organizational behavior; valuations and succession planning; office expense analysis, profit augmentation and benchmarking; HR and recruitment; marketing; and a host of other medical management topics. Like the CFP designation, an ethics and continuing education requirement is also mandated for this charter designation.

Certified Financial Planners, Certified Medical Planners, some fee-based and fee-only financial advisers, and some independent financial advisers possess these licenses and certifications, as required. Stockbrokers, salesmen, intermediaries, insurance agents, or other financial “consultants” and “advisers” may not. All monikers suggest, but do not guarantee, impartiality and a lack of bias.

Often, successful investing is simply a matter of avoiding mistakes, rather than possessing investing acumen. A good rule of thumb is to pursue fundamentals over fads, seek wise counsel when required, and always remember, caveat emptor.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

MEDICINE: Social-Psychiatric Aspects

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Psychiatry is the branch of medicine concerned with prevention, diagnosis and treatment of mental disorders. Its domain includes disorders of thought, emotion, intellect and conduct. The overall prevalence of psychiatric illness is one-fourth to one-third of the total population, and 30-60% of general hospital patients. A percentage of patients may thus be expected to display a variety of mental difficulties associated with, or independent from, their primary complaints.

For example, in 1984, Marcinko documented a report that stated that one-third of all surgical patients encountered difficulty with psychological adjustments before and after surgery. Therefore, understanding human behavior can contribute to the medical practitioner’s success

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Urban Consumer Price Index

***

***

In September, the Consumer Price Index for All Urban Consumers rose 0.6 percent, seasonally adjusted (SA), and rose 3.7 percent over the year, not seasonally adjusted (NSA). The index for all items less food and energy rose 0.3 percent in September (SA), up 2.6 percent over the year (NSA).

Next Release

The Consumer Price Index for October 2026 is scheduled to be released on November 10, 2026, at 8:30 A.M. Eastern Time.

COMMENTS APPRECIATED

EDUCATION: Books

***

***

CHAOS THEORY: In Micro-Economics

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Chaos theory in microeconomics is ultimately a way of seeing markets not as tidy, predictable machines but as living systems where small actions by individual agents can cascade into large, unexpected outcomes. Microeconomics traditionally focuses on how consumers, firms, and workers make decisions under constraints. It often assumes rational behavior, smooth curves, and stable equilibria. Chaos theory disrupts that picture. It argues that even when individuals follow simple, deterministic rules, their interactions can produce nonlinear, unstable, and highly sensitive dynamics. In other words, micro-level decisions can generate macro-level unpredictability.

The foundation of chaos theory is sensitivity to initial conditions—the idea that tiny differences at the start can lead to dramatically different outcomes later. In microeconomics, this plays out in markets where individual choices interact through feedback loops. A slight change in consumer preference, a small shift in a firm’s pricing strategy, or a minor adjustment in expectations can ripple outward. These ripples can amplify, collide, and transform into large market movements. The classic supply-and-demand diagram suggests smooth adjustments, but real markets often behave more like turbulent ecosystems.

Consider consumer behavior. Traditional microeconomic models assume stable preferences and predictable responses to price changes. Chaos theory suggests something more dynamic. Preferences evolve, are influenced by social networks, and can shift suddenly. A small trend—say, a handful of consumers adopting a new product—can explode into widespread demand if social feedback loops kick in. Conversely, a tiny reputational shock can collapse demand. These nonlinear patterns resemble chaotic systems where outcomes depend heavily on initial conditions and interactions rather than simple price signals.

Firms also operate within chaotic dynamics. A slight change in cost structure, a small innovation, or a minor strategic adjustment can set off competitive cascades. One firm’s price cut may trigger retaliatory cuts, shifting the entire market equilibrium. A small technological improvement can destabilize established industries. Chaos theory helps explain why industries sometimes experience sudden shakeups, why dominant firms can fall quickly, and why competitive landscapes evolve unpredictably. Even when firms behave rationally, their interactions can produce chaotic outcomes.

Market competition itself often resembles a chaotic system. In models where firms repeatedly adjust prices or quantities based on competitors’ actions, the resulting dynamics can oscillate, diverge, or behave unpredictably. Instead of converging to a stable equilibrium, markets may cycle endlessly or shift abruptly. Chaos theory shows that even simple strategic rules—like adjusting output based on last period’s profits—can generate complex patterns. This challenges the assumption that markets naturally gravitate toward stability.

Chaos theory also reshapes how economists think about supply chains. Microeconomics traditionally treats supply chains as linear sequences of production. In reality, they are networks of interdependent agents. A small disruption at one node—a delayed shipment, a minor shortage, a slight increase in demand—can propagate through the network. These ripples can amplify, producing large swings in inventory, pricing, and production. The “bullwhip effect,” where small changes in consumer demand cause large fluctuations upstream, is a classic example of chaotic dynamics in microeconomic systems.

Expectations play a central role in microeconomic chaos. Individuals and firms make decisions based not only on current conditions but on beliefs about the future. These beliefs are influenced by limited information, heuristics, and social cues. A small rumor or a slight shift in sentiment can alter expectations, which then alter behavior. This feedback loop can generate chaotic patterns in markets. For example, a minor concern about future prices can trigger hoarding, which then drives actual price increases. Chaos theory helps explain why expectations-driven markets—like housing, cryptocurrency, or collectibles—often behave unpredictably.

Labor markets also exhibit chaotic dynamics. A small change in hiring practices, a slight shift in worker preferences, or a minor technological adjustment can reshape job flows. Workers respond to wages, working conditions, and expectations, while firms respond to productivity, costs, and competition. These interactions can produce nonlinear outcomes: sudden shortages, rapid wage spikes, or unexpected declines in labor participation. Chaos theory highlights how sensitive labor markets are to small changes and how difficult it is to predict their evolution.

Even bargaining and negotiation reflect chaotic principles. In microeconomic models of bargaining, small differences in information, timing, or expectations can lead to vastly different outcomes. Chaos theory suggests that negotiation dynamics may not converge smoothly but may jump between equilibria depending on subtle shifts in strategy. This helps explain why seemingly minor details—tone, timing, or framing—can dramatically influence economic outcomes in real-world negotiations.

***

***

Chaos theory also intersects with behavioral microeconomics. Human decision-making is nonlinear, emotional, and context-dependent. Small psychological triggers can produce large changes in behavior. When millions of individuals behave this way simultaneously, the aggregate effects can be chaotic. Herd behavior, fads, and sudden shifts in sentiment all reflect nonlinear micro-level dynamics. Chaos theory provides a framework for understanding why markets sometimes behave irrationally and why small nudges can produce large outcomes.

Ultimately, chaos theory in microeconomics is not about rejecting traditional models. It is about enriching them. It acknowledges that individual agents operate within complex networks of interactions, feedback loops, and evolving expectations. It teaches that micro-level decisions can produce macro-level unpredictability and that stability is often an illusion. Chaos theory encourages economists to embrace complexity, recognize the limits of prediction, and design policies and strategies that are robust to uncertainty.

In practice, this perspective fosters humility and creativity. It reminds us that markets are not mechanical systems but dynamic human environments. It encourages economists, policymakers, and businesses to pay attention to small details, subtle signals, and emerging patterns. Chaos theory does not offer simple answers, but it provides a powerful lens for understanding why microeconomic systems behave the way they do—and why small actions can matter enormously.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

MEDICAL EDUCATION: High Tuition Costs

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The cost of medical education in the United States has climbed to a level that forces students, families, and even institutions to confront uncomfortable questions about who can realistically pursue a career in medicine. While the profession carries prestige, purpose, and the promise of financial stability, the path to becoming a physician is increasingly defined by staggering tuition bills, years of lost income, and long‑term debt obligations that shape graduates’ lives for decades. The price tag has grown so large that it is no longer just an economic issue; it is reshaping the demographics, motivations, and mental health of future physicians, and ultimately influencing the healthcare system itself.

Medical school tuition alone often exceeds what many Americans earn in a year. Students routinely face annual costs that can surpass $60,000 to $70,000, and that figure does not include housing, food, transportation, exam fees, or the cost of applying to residency programs. When the full journey is tallied—undergraduate education, medical school, and the years of training that follow—many new physicians emerge with debt loads well above $200,000. Some carry balances closer to $300,000. These numbers are not abstract; they shape every decision a student makes, from where they apply to school to what specialty they choose.

The financial pressure begins even before medical school acceptance. The application process itself is expensive. Prospective students pay for standardized tests, primary applications, secondary applications, and travel for interviews. For many, this phase alone costs several thousand dollars. Students from lower‑income backgrounds often struggle to compete in this early stage, not because of academic ability, but because the financial barrier is already too high. The pipeline narrows before training even begins.

Once enrolled, the intensity of medical education makes it nearly impossible for students to work part‑time to offset costs. The curriculum demands long hours, constant studying, and clinical responsibilities that leave little room for supplemental income. As a result, most students rely heavily on loans. Interest accumulates quickly, and because medical school lasts four years—followed by residency training that can stretch from three to seven years—many graduates watch their balances grow even as they work full‑time caring for patients.

The burden of debt influences career choices in ways that ripple across the healthcare system. Students who might otherwise pursue lower‑paying specialties such as primary care, pediatrics, or psychiatry often feel compelled to choose fields with higher salaries to manage their financial obligations. This dynamic contributes to shortages in essential specialties and exacerbates disparities in access to care. The country needs more primary care physicians, yet the economics of medical education push students away from these roles. In this way, the cost of training does not just affect individuals; it shapes national healthcare outcomes.

The psychological toll is equally significant. Medical school is already known for its demanding workload and high stress levels, but financial anxiety adds another layer of pressure. Students worry about every dollar they borrow, every interest payment, and every future bill. This chronic stress can affect academic performance, personal relationships, and mental health. For some, the weight of debt becomes a defining feature of their medical journey, overshadowing the excitement and purpose that initially drew them to the profession.

The high cost also affects diversity within medicine. Students from wealthy families can navigate the financial landscape more easily, while those from lower‑income backgrounds face barriers that are often insurmountable. This creates a profession that does not fully reflect the population it serves. Diverse physicians bring cultural insight, language skills, and lived experiences that improve patient care. When the cost of education limits who can enter the field, the entire healthcare system loses these valuable perspectives.

***

***

Institutions often justify high tuition by pointing to the expense of running medical programs. Teaching hospitals, laboratories, simulation centers, and faculty salaries require substantial funding. While these costs are real, the escalation of tuition has outpaced inflation and income growth for decades. Students are left wondering whether the financial structure of medical education is sustainable or whether it is drifting toward a crisis that will eventually force reform.

Despite these challenges, many students continue to pursue medicine because they feel called to the work. They want to heal, to serve, and to contribute to society in a meaningful way. But passion alone cannot erase the financial realities. The question is not whether medical education should be rigorous or resource‑intensive—it must be both. The question is whether the current model is fair, accessible, and aligned with the nation’s healthcare needs.

The high cost of medical education is more than a personal burden; it is a systemic issue with far‑reaching consequences. It shapes who becomes a doctor, what specialties they choose, where they practice, and how they experience their training. It influences the availability of care in underserved communities and contributes to workforce shortages in critical fields. Addressing this challenge will require creativity, commitment, and a willingness to rethink long‑standing assumptions about how physicians are trained.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

THEORY: Financial Relativity

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***.

***

Financial Relativity as a Perspective-Based Framework

At its core, financial relativity argues that value, risk, and opportunity are not fixed properties. They change based on the observer’s circumstances. A pension fund with a 40‑year horizon experiences volatility as background noise; a day trader experiences the same volatility as existential threat. A government views inflation as a macroeconomic variable; a household views it as a direct assault on purchasing power. The underlying reality is the same, but the interpretation—and the resulting decisions—are relative.

This relativity of perspective explains why financial debates often feel circular. Two people can look at the same data and reach opposite conclusions because their frames of reference differ. The theory suggests that instead of searching for universal financial truths, we should analyze the observer’s position first. Only then does the behavior of markets make sense.

Time as the Central Variable

In physics, relativity reshapes our understanding of time. In finance, time is the most important dimension. Every financial decision—investing, borrowing, saving, hedging—depends on how much time the observer has and how they perceive it.

  • Short-term observers (traders, speculators, leveraged investors) experience markets as chaotic, fast-moving, and dominated by noise.
  • Long-term observers (retirement savers, endowments, sovereign wealth funds) experience markets as slow-moving systems governed by cycles, mean reversion, and structural trends.

The same asset can be “risky” in one frame and “safe” in another. A volatile stock may be dangerous for a trader but ideal for a long-term investor who sees volatility as the price of future growth. Financial relativity argues that time doesn’t just influence risk—it defines it.

Relativity of Risk and Reward

Traditional finance treats risk as measurable and objective. The theory of financial relativity challenges this by asserting that risk is always relative to goals, constraints, and psychology.

For example:

  • A retiree holding cash sees risk in market downturns.
  • A young investor holding cash sees risk in inflation eroding future wealth.
  • A corporation sees risk in credit spreads and refinancing windows.
  • A policymaker sees risk in systemic instability.

Each observer is correct within their own frame. Financial relativity helps explain why universal risk metrics—like volatility or beta—often fail to capture lived financial experience. They measure movement, not meaning.

***

***

Incentives as Gravitational Forces

In relativity, gravity bends space-time. In finance, incentives bend behavior. They shape how individuals and institutions interpret information, allocate capital, and respond to uncertainty.

  • Analysts paid for short-term performance emphasize quarterly results.
  • CEOs compensated with stock options emphasize share price.
  • Regulators emphasize stability.
  • Venture capitalists emphasize growth.

These incentive structures create “financial gravity wells” that pull decisions in predictable directions. The theory of financial relativity argues that markets cannot be understood without mapping these incentive fields. They distort financial space just as gravity distorts physical space.

Information and the Observer Effect

Financial relativity also incorporates an observer effect: the act of observing or acting on information changes the system itself. Markets react to expectations, forecasts, and sentiment. A rumor can move prices; a central bank statement can reshape global capital flows. Information is not passive—it is an active force.

This explains why markets often behave irrationally or overshoot fundamentals. Observers influence the system, and the system influences observers, creating feedback loops that resemble the curvature of space-time.

Relativity of Value

Value is often treated as intrinsic, but financial relativity argues that value is contextual. It depends on:

  • liquidity needs
  • tax considerations
  • regulatory constraints
  • alternative opportunities
  • personal or institutional priorities

A bond yielding 4% may be unattractive to a hedge fund but essential to an insurance company. A startup may be worthless to a bank but priceless to a venture capitalist. Value is not a universal constant; it is relative to the observer’s world.

Implications for Financial Decision-Making

The theory of financial relativity encourages a shift in thinking:

  1. Understand your frame of reference. Your time horizon, incentives, constraints, and goals define what is risky or valuable.
  2. Recognize that others operate in different frames. Market movements often reflect conflicting perspectives rather than irrationality.
  3. Avoid universal prescriptions. What is “good” or “bad” financially depends on who you are and what you need.
  4. Embrace dynamic interpretation. As your circumstances change, your financial truths should change with them.

Conclusion

The theory of financial relativity is a conceptual framework that treats financial behavior, market dynamics, and economic outcomes as dependent on the observer’s position, incentives, and time horizon—much like Einstein’s relativity treats measurements of space and time as dependent on the observer’s frame of reference. It isn’t a formal academic doctrine, but it’s a powerful way to understand why markets behave differently for different participants, why risk is never absolute, and why financial truths often shift depending on who is looking and when.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

NOBEL PRIZE: Economics

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Robert E. Hall and Michael Woodford win Nobel memorial prize in economics

American economists Robert E. Hall and Michael Woodford won the 2026 Nobel Memorial Prize in Economic Sciences for research that has helped governments and central banks manage economic shocks and stabilise economies during crises.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Columbus Day Stock & Bond Markets

***

***

Monday, October 12th 2026

  • Today is a federal/bank holiday in observance of Columbus Day.
  • U.S. equity, options, and futures markets will be open but it’s a non-settlement day. 
  • All trades placed on Friday, October 9th 2026, will settle on Tuesday, October 13th, 2026.
  • All fixed income and bond markets will be closed.
  • Requests to move money received after the standard cut-off times on Friday, October 9th 2026, will not be processed until Tuesday, October 13th 2026.

Global Markets 

  • All Canadian markets will be closed in observance of Canadian Thanksgiving. Dually listed Canadian stocks will trade in the U.S. markets on Monday, October 12th 2026.

COMMENTS APPRECIATED

EDUCATION: Books

***

CAR LOANS: Interest Deductions 2025-2028

***

***

The Treasury Department and IRS have finalized regulations regarding the deduction of up to $10,000 in personal car loan interest by individuals for tax years 2025 through 2028. This includes regulations on information returns required to be filed by a lender or other person engage in a trade or business who receives $600 or more of qualified interest during the calendar year.

The final regulations adopt the proposed regulations published in January 2026 (NPRM REG-113515-25) with some changes in response to public comments.

COMMENTS APPRECIATED

EDUCATION: Books

***

PARADOX: Financial Health?

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

FINANCIAL HEALTH PARADOX

Classic Definition: Research from Ernst-Young [Nikhil Lele and Yang Shim] uncovered a chasm between how consumer patients think they’re doing financially, and the actual state of their finances. Even more striking, their study suggested that improving consumers’ financial health will become one of the top imperatives in reframing consumer financial services.

Modern Circumstance: For example, the study asked consumers to rate their own financial health, and 83 percent rated themselves “good,” “very good” or “excellent.”  Now, contrast this figure with what is known about their actual situation:

  • 60 percent of Americans say they are financially stressed.
  • 56 percent of Americans have less than $10,000 saved for retirement.
  • 40 million American families have no retirement savings at all.
  • 40 percent of Americans are not prepared to meet a $400 short-term emergency.

Paradox Example: Fortunately, even though the vast majority of consumers rate themselves as financially healthy, the study found that most still want to improve. Importantly for health economists, the attractive 25-34 and 35-49 year-old age groups were most likely to be extremely or very interested in improving their financial and economic health.

Paradox Example: Massively affluent consumer patients are even more interested in improving this paradox than their mass market counterparts.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Nobel Prize in Chemistry

***

***

STOCKHOLM — Scientists Henri B. Kagan and Kenso Soai just won the Nobel Prize in chemistry for untangling mysterious mirror images in molecules, a discovery that has been used to develop countless drugs and transformed modern medicine.

COMMENTS APPRECIATED

EDUCATION: Books

***

ELTON MAYO: Human Relations Management Theory

By Dr. David Edward Marcinko; MBA MEd

By Eugene Schmuckler; PhD MBA MEd CTS

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Human Relations Theory is an important approach to management that emphasizes the role of people, social relationships, communication, and employee satisfaction in an organization. It developed as a reaction to earlier management theories that mainly focused on productivity, efficiency, rules, and financial incentives. One of the most important contributors to this approach was Elton Mayo, an Australian-born psychologist and sociologist who became closely associated with the Human Relations Movement. Mayo argued that workers are not simply economic beings motivated by money; they are also influenced by social relationships, recognition, group belonging, morale, and the attitudes of managers.

Elton Mayo’s ideas became particularly influential through the Hawthorne Studies, conducted at the Western Electric Company’s Hawthorne Works in Chicago during the 1920s and early 1930s. These studies helped draw attention to the importance of informal groups and human factors in the workplace. Human Relations Theory subsequently became an important foundation for modern organizational behavior and management.

Meaning of Human Relations Theory

Human Relations Theory refers to an approach to management that recognizes employees as social and psychological beings. According to this approach, organizational performance depends not only on physical working conditions and financial rewards but also on how employees feel about their work and their relationships with colleagues and supervisors.

Traditional management approaches tended to view employees primarily in terms of productivity and economic rewards. Human Relations Theory introduced a different perspective. It suggested that employees have social needs, such as the need for friendship, recognition, acceptance, respect, and a sense of belonging. When these needs are addressed, employees may develop greater commitment to their work and organization.

The theory therefore emphasizes the importance of communication, leadership, teamwork, employee participation, morale, and informal social groups. Managers are encouraged to understand employees and create working environments in which people feel valued and respected.

Elton Mayo and the Hawthorne Studies

Elton Mayo’s contribution to management is strongly associated with the Hawthorne Studies. The studies were initially designed to examine whether changes in physical working conditions affected worker productivity. Researchers examined factors such as lighting, working hours, rest periods, and other workplace conditions.

An important observation emerged from these experiments: changes in productivity could not always be explained simply by physical conditions. Workers’ attitudes, relationships, group behavior, and the attention they received from researchers appeared to influence their behavior.

Mayo and his colleagues concluded that workers were influenced by social factors within the workplace. Employees formed informal groups, developed their own standards of acceptable behavior, and responded to group expectations. This demonstrated that organizations contain both formal structures, created by management, and informal structures, created naturally through relationships among employees.

The Hawthorne Studies therefore helped shift attention from purely mechanical explanations of productivity toward the social and psychological aspects of work.

Main Principles of Human Relations Theory

One of the central principles of Human Relations Theory is that employees are social beings. People seek interaction with others and want to feel that they belong to a group. A workplace that ignores these needs may experience dissatisfaction and poor cooperation.

Another important principle is the importance of informal groups. Employees naturally form friendships and social groups, and these groups can influence attitudes and productivity. Informal group norms may sometimes be more influential than formal organizational rules.

Employee morale is also important. When workers feel respected, recognized, and valued, they may show greater enthusiasm toward their responsibilities. Managers therefore need to consider employee satisfaction alongside productivity.

The theory also emphasizes communication. Open and effective communication between managers and employees can reduce misunderstandings and improve cooperation. Employees are more likely to feel involved when managers listen to their opinions and explain organizational decisions.

Another principle is participative management. Employees can contribute useful knowledge about their jobs and working conditions. Giving workers opportunities to express their views can strengthen their sense of involvement and responsibility.

Finally, Human Relations Theory stresses the importance of leadership and supervision. Managers are not merely controllers of work; they also influence employee attitudes and relationships. Supportive leadership can encourage cooperation, trust, and commitment.

***

***

Importance of Human Relations Theory

Human Relations Theory made a significant contribution to management because it broadened the understanding of employee motivation. It showed that productivity cannot be understood entirely through wages, physical conditions, or formal rules. Human emotions and social relationships can also affect workplace behavior.

The theory also influenced the development of modern approaches to organizational behavior. Contemporary organizations pay attention to teamwork, employee engagement, organizational culture, leadership, communication, and workplace relationships. These areas reflect many of the concerns first emphasized by the Human Relations Movement.

The theory also changed the role of managers. Instead of seeing management only as the process of planning, organizing, and controlling work, it encouraged managers to develop interpersonal skills. A manager is expected to communicate effectively, understand employees, resolve conflicts, encourage teamwork, and create a positive working environment.

Furthermore, the theory highlighted the importance of informal organization. Every workplace has relationships and social networks that exist alongside its official hierarchy. Understanding these informal relationships can help managers improve cooperation and address workplace problems.

Criticism of Human Relations Theory

Although Human Relations Theory made important contributions, it has also been criticized. One criticism is that it may place too much emphasis on social relationships while giving insufficient attention to economic and structural factors. Employees are influenced by wages, job security, working conditions, career opportunities, and organizational policies as well as social relationships.

Another criticism concerns the interpretation of the Hawthorne Studies. Later scholars questioned some of the conclusions traditionally associated with the experiments and argued that the relationship between attention, workplace conditions, and productivity was more complicated than early accounts suggested.

The theory can also be criticized for assuming that greater employee satisfaction will automatically result in higher productivity. A satisfied employee is not necessarily a highly productive employee. Productivity can depend on technology, skills, resources, organizational structure, incentives, and many other factors.

Despite these limitations, Human Relations Theory remains significant because it introduced a more human-centered perspective into management.

Conclusion

Elton Mayo and the Human Relations Movement played an important role in changing the way organizations understand employees. Through the Hawthorne Studies, Mayo drew attention to the influence of social relationships, informal groups, communication, morale, and leadership on workplace behavior. His work challenged the idea that employees could be understood only through economic incentives and physical working conditions.

Human Relations Theory established that organizations are social systems as well as economic and technical systems. Employees have psychological and social needs, and these needs can influence their attitudes and behavior at work. Although the theory has limitations and some of the conclusions drawn from the Hawthorne Studies have been debated, its influence on management remains considerable. Modern ideas about teamwork, employee participation, communication, leadership, organizational culture, and employee engagement continue to reflect the central insight of the Human Relations approach: effective management requires attention not only to work and productivity but also to the people who perform the work.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Nobel Prize Winners 2026

***

****

The Nobel Prize in Physiology or Medicine 2026 was awarded jointly to Karl Deisseroth, Peter Hegemann and Georg Nagel “for their discoveries concerning light-gated ion channels and optogenetics.”

COMMENTS APPRECIATED

EDUCATION: Books

***

HEALTHCARE: Propensity to Pay

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The propensity to pay in healthcare refers to an individual’s willingness and ability to spend money on healthcare services, medicines, treatments, and other health-related needs. It is an important concept because healthcare decisions are influenced not only by medical needs but also by financial circumstances, personal preferences, perceptions of quality, and expectations about future health. Understanding the propensity to pay can help healthcare providers, policymakers, and organizations better understand how people make decisions about accessing and purchasing healthcare.

One of the main factors influencing a person’s propensity to pay is income. Individuals with higher incomes generally have greater financial flexibility and may be more willing to pay for private consultations, specialist services, advanced treatments, preventive care, or shorter waiting times. In contrast, people with lower incomes may postpone treatment, rely more heavily on publicly funded services, or choose less expensive alternatives. However, income alone does not determine healthcare spending. People may prioritize healthcare differently depending on their circumstances and personal values.

The perceived importance of a healthcare service also affects willingness to pay. When individuals believe that a treatment is essential or could significantly improve their health or quality of life, they may be willing to spend more. For example, someone experiencing severe pain may place a higher financial value on immediate treatment than on other types of expenditure. Similarly, parents may be particularly willing to pay for services that they believe will protect the health of their children. Preventive services, however, can be more difficult to value because their benefits may occur in the future rather than immediately.

Trust and perceived quality are also important. Patients are more likely to pay for healthcare when they believe that a provider is competent, trustworthy, and capable of delivering good outcomes. Reputation, communication, professional qualifications, facilities, and previous experiences can all influence this perception. A patient who has confidence in a particular doctor or hospital may be willing to pay more for its services than for an unfamiliar provider. Conversely, poor experiences or concerns about unnecessary treatment can reduce willingness to pay.

***

***

Insurance and the structure of healthcare financing can substantially change individual behavior. When insurance covers a large proportion of healthcare costs, patients may face relatively small direct payments and therefore be less sensitive to the full price of services. Deductibles, copayments, and other forms of cost sharing can increase price sensitivity. At the same time, high out-of-pocket costs may discourage people from seeking necessary care, particularly when their income is limited. Consequently, the relationship between price and healthcare utilization is more complicated than in many ordinary consumer markets.

Cultural, social, and demographic factors can also influence propensity to pay. Age, education, family responsibilities, health status, and attitudes toward medicine may affect healthcare spending decisions. Some individuals may place considerable emphasis on preventive care and wellness, while others may seek medical attention primarily when symptoms become serious. Social expectations can also influence choices, particularly when healthcare decisions involve family members or dependents.

The propensity to pay is also relevant to healthcare businesses. Providers need to understand what patients value when designing services and pricing strategies. Convenience, accessibility, personalized care, technology, and shorter waiting periods may increase the perceived value of a service. Nevertheless, healthcare organizations must balance financial considerations with ethical responsibilities. Unlike many consumer products, healthcare can involve essential services that people cannot reasonably avoid purchasing.

Overall, propensity to pay in healthcare is shaped by a combination of economic, medical, psychological, and social factors. Income and price are important, but willingness to pay also depends on perceived need, expected benefits, trust, quality, insurance coverage, and individual circumstances. Understanding these factors can help healthcare providers design accessible services and help policymakers consider how financing systems affect access to care. Ultimately, examining propensity to pay provides insight into the complex relationship between healthcare needs, financial resources, and individual decision-making.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Unemployment Rate Ticks Up

***

***

WASHINGTON (AP) — U.S. employers added a disappointing 29,000 jobs and the unemployment rate ticked up last month, the government reported Friday, a month before voters go to the polls in pivotal midterm elections at a time of discontent over the high cost of living and the state of the economy.

Hiring dropped from a revised 133,000 in August, the Labor Department said. The unemployment rate rose to a still-low 4.2% from 4.1% in August.

Economists had expected September payrolls to come in around 90,000!

Labor Department revisions also shaved 60,000 jobs off combined July and August payrolls.

COMMENTS APPRECIATED

EDUCATION: Books

***

GUYTON-KLINGER: Equation

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The Guyton–Klinger equation, more accurately described as the Guyton–Klinger decision rules, is a set of mathematically defined withdrawal‑rate adjustments designed to guide retirees in determining how much they can safely withdraw from an investment portfolio each year. Unlike fixed‑percentage or inflation‑adjusted withdrawal strategies, the Guyton–Klinger framework introduces a dynamic system that responds to market performance. Its purpose is to preserve the longevity of a retirement portfolio while still allowing the retiree to enjoy a stable, predictable income. The “equation” is not a single formula but a set of interlocking rules that operate like a feedback system. These rules—commonly known as the inflation rule, the capital preservation rule, and the prosperity rule—form a mathematical structure that adjusts withdrawals up or down depending on portfolio conditions.

At its core, the Guyton–Klinger system begins with an initial withdrawal rate, often around 4–5 percent of the portfolio’s starting value. This initial rate is then subjected to annual adjustments based on the rules. The inflation rule governs whether the withdrawal amount should be increased to keep pace with rising prices. Unlike a simple inflation‑adjusted strategy, the Guyton–Klinger method restricts inflation adjustments during years when the portfolio has declined. This creates a built‑in stabilizer: the retiree does not automatically increase spending when the portfolio is under stress. Mathematically, this rule can be expressed as a conditional statement: if the portfolio’s real return for the year is negative, the inflation adjustment is skipped. This conditionality is the first component of the broader Guyton–Klinger equation.

The second component, the capital preservation rule, introduces a lower guardrail. It compares the current withdrawal rate—defined as the withdrawal amount divided by the portfolio’s current value—to the initial withdrawal rate. If the current rate rises too far above the initial rate, typically by more than 20 percent, the rule triggers a spending cut. This can be expressed as a ratio: if (current withdrawal ÷ portfolio value) > (initial withdrawal rate × 1.20), then the withdrawal amount is reduced by a fixed percentage, often 10 percent. This is the mathematical heart of the system: a dynamic ratio that signals when the portfolio is at risk of depletion. The rule ensures that withdrawals do not become unsustainably large relative to the shrinking portfolio.

The third component, the prosperity rule, acts as the counterpart to the capital preservation rule. When the portfolio grows significantly, the retiree is allowed to increase withdrawals. The rule is triggered when the current withdrawal rate falls below a lower guardrail—typically 20 percent below the initial rate. In mathematical terms, if (current withdrawal ÷ portfolio value) < (initial withdrawal rate × 0.80), then the withdrawal amount is increased by a fixed percentage, again often 10 percent. This rule allows retirees to enjoy the benefits of strong market performance without jeopardizing long‑term sustainability.

Together, these rules form a dynamic system that resembles a thermostat. When the portfolio overheats—meaning the withdrawal rate becomes too high relative to the portfolio’s value—the system cools spending. When the portfolio is performing well, the system allows spending to warm up. The inflation rule adds a third dimension by moderating spending increases during downturns. The interplay of these rules is what people often refer to as the “Guyton–Klinger equation,” even though it is more accurately a set of conditional equations.

One of the most important features of the Guyton–Klinger framework is that it balances two competing goals: income stability and portfolio longevity. Retirees typically want predictable income, but they also want assurance that their savings will last. Fixed‑percentage withdrawal strategies can cause income to fluctuate dramatically, while fixed‑inflation strategies can cause withdrawals to become unsustainable. The Guyton–Klinger system attempts to strike a middle ground by allowing adjustments only when necessary and by basing those adjustments on mathematically defined thresholds.

Another key aspect is that the system is forward‑looking but rule‑based. It does not attempt to predict market performance. Instead, it reacts to actual portfolio changes. This makes it adaptable across different market environments. During prolonged bull markets, the prosperity rule allows retirees to increase spending without fear of overshooting. During bear markets, the capital preservation and inflation rules work together to slow spending and protect the portfolio.

The Guyton–Klinger equation also implicitly acknowledges behavioral realities. Retirees often struggle with cutting spending, and the system’s guardrails help make those decisions objective rather than emotional. The rules provide a clear rationale for when spending must be reduced, which can make difficult adjustments easier to accept. Similarly, the prosperity rule encourages retirees to enjoy their savings when conditions allow, countering the tendency to underspend out of fear.

In summary, the Guyton–Klinger equation is a structured, mathematically grounded approach to retirement withdrawals that uses conditional rules to adjust spending based on portfolio performance. It replaces rigid withdrawal strategies with a flexible, responsive system that aims to preserve both income stability and long‑term financial security. By defining clear thresholds for when to increase or decrease withdrawals, the framework offers retirees a disciplined yet adaptable method for navigating the uncertainties of retirement finance.

COMMENTS APPRECIATED

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

FINANCE: Propensity to Pay

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

****

***

The propensity to pay is an important concept in finance that describes the likelihood and willingness of an individual, business, or organization to make a financial payment when it becomes due. It is closely related to financial behavior, creditworthiness, liquidity, and the ability to meet financial obligations. Financial institutions, businesses, and investors consider payment behavior when making decisions about lending, credit management, investment, and risk. Understanding the propensity to pay therefore helps financial decision-makers evaluate whether expected payments are likely to be made on time and in full.

In personal finance, propensity to pay can be influenced by income, employment stability, existing debt, spending habits, savings, and financial priorities. An individual with a stable income and manageable debt is generally more capable of meeting regular obligations such as loan installments, credit card balances, rent, and utility bills. However, the ability to pay does not always guarantee the willingness to pay. A person may have sufficient financial resources but choose to delay a payment because of competing priorities or expectations about future income. This distinction between ability and willingness is important when assessing financial risk.

For businesses, propensity to pay is particularly significant in managing accounts receivable and extending credit to customers. Companies frequently allow customers to purchase goods or services before making payment. While this practice can encourage sales and strengthen business relationships, it also creates the possibility of late or unpaid invoices. Businesses therefore evaluate customers’ previous payment records, financial condition, industry circumstances, and credit terms. A strong propensity to pay can support more flexible credit arrangements, whereas uncertainty about payment behavior may lead a company to require deposits, shorter payment periods, or additional security.

Banks and other financial institutions also rely heavily on payment behavior when assessing borrowers. Credit scores, repayment histories, debt-to-income ratios, and other financial information can help lenders estimate the probability that borrowers will meet their obligations. A borrower who has consistently made payments on time may be viewed as presenting less repayment risk than someone with a history of missed or late payments. These assessments influence lending decisions, interest rates, credit limits, and other terms. In this way, propensity to pay is an important component of credit risk management.

Economic conditions can also affect propensity to pay. During periods of economic growth, employment and business revenues may increase, making it easier for borrowers and customers to meet their obligations. During economic downturns, unemployment, declining sales, inflation, and higher interest rates can place pressure on household and business finances. Even financially responsible borrowers may experience difficulties when their income decreases or expenses rise unexpectedly. Consequently, financial institutions must consider broader economic conditions rather than relying solely on an individual’s or company’s past payment behavior.

Technology has made the assessment of payment propensity increasingly sophisticated. Financial institutions and businesses can analyze large amounts of transaction and credit data to identify patterns in payment behavior. Automated systems can monitor missed payments, changes in account activity, and other indicators of financial stress. These tools can improve risk assessment and allow organizations to respond more quickly to potential repayment problems. At the same time, responsible use of financial data is important because inaccurate information or inappropriate assessment methods can unfairly affect access to credit.

Propensity to pay also has implications for financial planning and business strategy. Individuals can improve their payment behavior by maintaining budgets, building emergency savings, reducing unnecessary debt, and organizing payment schedules. Businesses can improve collections by establishing clear credit policies, communicating payment expectations, monitoring outstanding invoices, and maintaining good relationships with customers. These practices can reduce financial uncertainty and improve cash flow.

In conclusion, propensity to pay is a fundamental concept in finance because it helps explain whether financial obligations are likely to be fulfilled. It reflects both the ability and willingness to make payments and is influenced by personal financial circumstances, business conditions, economic developments, and payment history. By understanding these factors, lenders, businesses, and individuals can make more informed financial decisions, manage risk, and maintain healthier financial relationships.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

Hospitals Have a Little-Known Tool To Prevent Medical Debt

Here’s How It Works

By Melanie Evans, Tradeoffs

October 1st, 2026

If you have medical debt, there’s a good chance you owe money to a hospital.

One way patients can avoid medical debt is through hospital financial assistance, also known as charity care. Most of the nation’s hospitals offer free or discounted medical care to patients with very high medical debt or low incomes.

Getting financial assistance, however, can be challenging. Many patients don’t know that hospitals offer financial help, surveys show, and complex application forms leave others stymied.

Hospitals often demand that applicants turn over bank statements, pay stubs, tax returns, divorce filings, or other materials, and submit their applications in person, by mail, or by fax.

“They don’t make it easy,” said Neale Mahoney, a Stanford University economist who studies medical debt.

Such hurdles leave many patients with unpaid bills they should never have had to pay in the first place. In a single year, hospitals and health systems billed patients for at least $2 billion that they likely didn’t owe, one analysis found.

As healthcare costs climb and more people lose their coverage, states and hospitals are testing an emerging approach to fix this problem: automatically screening patients to see if they qualify for assistance and proactively wiping out debt when they do. This is known as “presumptive eligibility.”

Under this approach, patients may have the cost of their care wiped out before they see any bills — but not always. Hospitals differ on when, how, and for whom they use auto-enrollment, potentially impinging on patients’ finances.

Here’s what you need to know about how auto-enrollment works.

What is hospital financial assistance?

In many states, hospitals set their own criteria for whom they provide financial aid. Eligibility is typically based on income for the patient’s entire household. The closer patients are to poverty, the less they have to pay. Patients with middle incomes and insurance are sometimes eligible for discounts, especially if their bills would gobble up a big chunk of what they earn.

At least 11 states require hospitals to wipe out bills for low-income patients, though income cutoffs vary. Georgia, for example, mandates free care for anyone with income slightly above the federal threshold for poverty. In several states — including Oregon, North Carolina, and Maryland — patients can earn double that amount and still get free care.

But in most states, many patients must complete applications to receive assistance.

Several states in recent years have launched investigations and passed legislation designed to make it easier for people to get help. Research into medical debt, however, suggests gaps persist.

***

***

How many hospitals use auto-enrollment?

Nearly all nonprofit hospitals say they screen and automatically reduce bills for certain patients.

Under the Affordable Care Act, nonprofit hospitals must make reasonable efforts to find people who are eligible for help before they take patients to court, sell their debt to collection agencies, or ding their credit over bills. Presumptive eligibility is one way hospitals can comply with the regulation, which took effect in 2016.

In the first year under the new rules, about 70% of tax-exempt hospitals nationwide said they screened patients and proactively reduced bills, according to an analysis of federal data for Tradeoffs by the independent research institute RTI International. As of 2022, that figure was nearly 90%.

The federal law doesn’t apply to for-profit and public hospitals, which don’t have to report the actions they take before going after patients for unpaid bills.

In six states, policymakers require hospitals to use presumptive eligibility and skip applications for certain patients. Those states are California, Delaware, Illinois, Maryland, North Carolina, and Oregon.

Who is eligible to be automatically enrolled in financial assistance?

In most states, hospitals decide which patients can skip the application.

Common groups automatically screened include people who are homeless, deceased, or already enrolled in state or federal programs to help low-income households with housing, food, or prescriptions. Other hospitals have more unique criteria, like Christus Health, which will write off bills for anyone in a religious order who took a vow of poverty.

Eligibility criteria are often buried in official policies and hard to find or decipher. Some hospitals share little to no public information about whom they will proactively screen. Thirteen hospitals owned by Ascension, one of the nation’s largest Catholic health systems, state only that they may screen patients “with a sufficient unpaid balance.”

Across the half-dozen states with presumptive eligibility mandates, eligibility rules vary. Maryland, for example, requires hospitals to proactively wipe out bills only for patients who already get government help for food or utilities but are ineligible for Medicaid. In Illinois, lawmakers created less-stringent requirements for rural hospitals compared with urban facilities.

In Oregon, starting in 2024, hospitals had to screen anyone who owed more than $500 and every patient on Medicaid or who is uninsured. In 2025, roughly 80% of Oregon patients who got financial help with bills never filled out an application, based on data shared publicly by the first 26 hospitals to do so. The state’s legislature this year raised the screening threshold to include patients who owe at least $1,500 for a single visit.

***

***

Without an application, how do hospitals figure out who gets help?

Hospitals have several ways to find patients eligible for financial assistance.

Typically, hospitals turn to public records, any information patients have previously volunteered, or tools from consumer credit companies to estimate whether patients qualify to have bills reduced.

For example, if a hospital sees that a patient lives in a high-poverty ZIP code or has no address listed, that could be enough to deem them eligible. Many pay companies to run employment and credit checks on patients to determine whether they qualify for free care.

Hospitals may also consider how likely patients are to pay bills, regardless of how much they earn. This is called “propensity to pay.” California and Oregon prohibit its use, concerned that hospitals may try to collect more often from people who dutifully pay their bills even though their incomes qualify them for financial assistance.

When do hospitals screen patients for financial aid?

It depends.

Illinois, North Carolina, and Oregon require hospitals to screen certain patients before they send any bills. California hospitals will have to do the same starting in 2027.

Some hospitals voluntarily screen patients before sending bills; others try to collect money from patients first. As long as they screen patients before suing them for very overdue bills, hospitals can stay within the letter of the federal law that pushed many of them to embrace presumptive eligibility.

For example, the policy of Christus Health is to screen patients only “after all other eligibility and payment sources have been exhausted.”

Anna Stelter, vice president of policy for the Texas Hospital Association, said hospitals want to investigate other options for payment — like Medicaid or county safety net programs — before they give out financial assistance.

“We do want to make sure that whoever is financially responsible for that care is identified and pays,” Stelter said. “Charity care is the relief of last resort.”

Hospitals’ publicly posted policies may also be fuzzy about when they will screen for patients likely eligible for help. For example, Cook Children’s Health Care System in Fort Worth, Texas, says its goal is to determine a patient’s eligibility “as soon as sufficient information is available.”

Who pays the bills when patients get free care?

In one sense, we all do. Taxpayers cover some or all of the cost of financial assistance, though the amount varies by hospital.

About half the nation’s hospitals are nonprofit and legally get a pass on paying most taxes. KFF estimates that nonprofit hospitals pocketed $24 billion in 2020 that they would otherwise have paid as income, sales, or property taxes.

Government-owned and for-profit hospitals have their own sets of tax benefits to help offset costs for low-income patients. Government hospitals often get additional taxpayer support, and for-profit hospitals generally receive smaller government subsidies, like additional payments for caring for high numbers of uninsured and Medicaid patients.

Whether taxpayer dollars fully cover hospitals’ costs for financial assistance depends on the amount of government support they receive — information often not publicly available. It also hinges on how many patients need help, how many meet hospitals’ criteria for assistance, and how many get through an application. Research shows hospitals spend widely different amounts on financial assistance, from less than 1% of yearly expenses to more than 7%.

Philanthropy and hospitals’ income cover costs not absorbed by tax dollars.

This article is part of “Hidden Help,” an investigative series from Tradeoffs and KFF Health News about how hospitals can protect their patients from the life-altering harms of medical debt.

Melanie Evans is a reporter for Tradeoffs, a nonprofit newsroom reporting on healthcare’s toughest choices. Sign up for the weekly newsletter to get the latest stories every Thursday morning.

Tradeoffs’ reporting for this series was supported, in part, by the California Health Care Foundation, the National Institute for Health Care Management Foundation, and the Solutions Journalism Network.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

From Artificial Intelligence to Super Intelligence

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Artificial intelligence (AI) has developed from a largely theoretical idea into a technology that is increasingly part of everyday life. AI systems can now understand language, recognize images, generate content, assist with scientific research, and perform complex tasks. As these systems become more capable, researchers and society are beginning to consider a possible future transition from artificial intelligence to artificial superintelligence. This development could transform human civilization, creating extraordinary opportunities while also raising serious questions about safety, control, and responsibility.

Artificial intelligence refers to computer systems designed to perform tasks that normally require human intelligence. These tasks include learning from information, solving problems, understanding language, recognizing patterns, and making decisions. Modern AI can already perform some tasks at a level comparable to or beyond humans. However, most existing AI systems remain specialized or limited in important ways. They depend on human-designed objectives, training data, computing resources, and environments in which they operate.

The concept of artificial general intelligence (AGI) describes a potential future system with broad intellectual abilities. Rather than being designed for one particular task, an AGI would theoretically be able to learn and perform a wide range of intellectual activities. It could potentially transfer knowledge between different subjects, adapt to unfamiliar problems, and improve its abilities through experience. Whether and when AGI will be achieved remains uncertain, and there is no universally accepted definition or test for it.

Artificial superintelligence represents a further hypothetical stage. It generally refers to an AI system whose intellectual capabilities substantially exceed those of humans across most or all areas of cognitive activity. Such a system could potentially conduct scientific research, develop technologies, analyze enormous amounts of information, and solve problems far more rapidly than individual humans or existing institutions. If achieved, superintelligence could accelerate progress in areas such as medicine, energy, transportation, education, and scientific discovery.

At the same time, the development of increasingly powerful AI could create significant challenges. One concern is the problem of ensuring that highly capable systems reliably pursue goals that are consistent with human intentions and values. A system that is extremely capable but misunderstands its objectives could produce harmful consequences even without intending to cause harm. Other concerns include cybersecurity, economic disruption, concentration of technological power, privacy, misinformation, and the possibility that advanced AI could be used irresponsibly by individuals or organizations.

The transition from AI to superintelligence should therefore not be viewed simply as a race to create increasingly powerful machines. It also involves developing methods for testing, monitoring, controlling, and governing advanced systems. Researchers are exploring areas such as AI alignment, interpretability, robustness, evaluation, and safety. Governments, businesses, researchers, and the public may all have roles in determining how increasingly powerful AI technologies are developed and used.

Ultimately, the path from artificial intelligence to superintelligence is uncertain. Some experts believe highly advanced systems could emerge relatively soon, while others believe major technical challenges remain. Regardless of the timeline, the possibility deserves careful consideration. AI has the potential to expand human capabilities enormously, but realizing its benefits will require thoughtful development and responsible decision-making. The central challenge is not simply creating machines that become more intelligent, but ensuring that increasing technological power contributes to human well-being and remains subject to appropriate human oversight.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe!

SEND IN YOUR TOPIC IDEAS, TODAY

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

She Left After Waiting Hours in the Emergency Room

The ER Billed Her Anyway

By Michelle Andrews

September 29th, 2026

A woman sits at a table for a portrait, holding a copy of her medical bill.
After hospital staffers checked her vital signs, Autumn Daniels spent four hours in the waiting room before her sister took her to another hospital. She still got a bill from the ER for $410. (Taylor Glascock for KFF Health News)

Autumn Daniels is no stranger to migraine headaches, which have troubled her since childhood.

The migraine tormenting the 32-year-old in April was even worse than usual. After a week of piercing head pain, she went to an urgent care center near her home in Champaign, Illinois, and received an injection of Toradol, a non-steroidal anti-inflammatory drug that usually helps with her symptoms. The doctor at the clinic told her that if the pain didn’t improve, she should go to an emergency room the next day.

It didn’t improve. So the next morning, Daniels’ sister took her to a nearby ER, at Carle Foundation Hospital in Urbana. She said the ER didn’t seem very busy when she registered at the front desk and was taken briefly to an exam room, where a staffer checked her vital signs and asked whether she had migraines frequently. Then they told her to sit in the waiting room until she was called.

She and her sister waited. And waited. By then, Daniels said, she was vomiting every 10 minutes, a not-uncommon occurrence during one of her serious migraine attacks.

After four hours, with no indication that Daniels would be seen anytime soon, her sister took her to another hospital. There, after a wait of about an hour and a half, Daniels was seen and received treatment, including more Toradol and anti-nausea medication.

Having left Carle without getting treatment, Daniels didn’t expect to be charged.

Then the bill came.

The Medical Service

Daniels said a staffer checked her pulse, temperature, and blood pressure when she arrived at Carle. She said she received no other services, nor was she seen by a doctor.

At one point while they sat in the waiting room, Daniels said, her sister asked for an ice pack for her head, but the staff wouldn’t provide one.

“ER triage is driven by risk of death or serious harm, not by level of suffering,” said Jennifer Robblee, a neurologist at the Barrow Neurological Institute in Phoenix and a board member at the Association of Migraine Disorders. “Migraine patients without red flags are unlikely to be prioritized, as they are not at immediate risk of dying.”

The Bill

$410 for an “Emergency Room Level 1” visit. Daniels said she requested an itemized bill showing how the hospital arrived at that figure but never received one.

This is not the first time that a patient has complained to KFF Health News’ “Bill of the Month” about receiving a bill after leaving a Carle Health emergency room without being treated. In 2023, Maggi Wettstein took her toddler to a different Carle Health hospital and was billed $445 for a nasal swab test for covid and influenza. They, too, left before getting treatment.

The Billing Problem: What Counts as Care?

Though Daniels left the emergency room after a four-hour wait without being treated, the hospital billed her anyway. Her health plan, provided through her job as a state employee, paid for her treatment at the second hospital but denied the Carle claim, leaving her on the hook for the charges.

“Under the terms of her health plan, claims associated with a patient leaving the facility against medical advice are not eligible for coverage,” Leslie Porras, a spokesperson for HealthLink, which administers Daniels’ plan, said in a statement.

When Daniels asked about her bill, a Carle representative responded in an email that said: “Effective March 1, 2026, Emergency Department visits may result in charges even if you are not seen directly by a provider. When you arrive at the Emergency Department, your visit begins as soon as care is initiated.”

The email said “care” could mean registration and nursing assessment, in addition to diagnostic testing and treatment. It said that even if patients leave without being seen by a provider, they may still be charged, because the hospital is using resources to maintain its staff, space, and equipment.

Carle Health declined to discuss Daniels’ bill or her care with KFF Health News, even though Daniels signed a privacy waiver that authorized it to do so.

Autumn Daniels stands in front of a window with a variety of plants on shelves.
Daniels was not expecting to be charged after leaving an emergency room without receiving treatment. But a health system representative later told her an ER visit begins “as soon as care is initiated,” which could mean when the patient registers at the front desk and is assessed for triage purposes. (Taylor Glascock for KFF Health News)

In a statement, Carle Health spokesperson Brittany Simon said, “Our Emergency Department has consistent billing practices for triage care,” referring to the process through which patients are evaluated to ensure the most critical cases are treated first.

“Carle Health takes patient concerns seriously and supports transparency in our billing processes,” she said.

Typically, an ER bill would include separate dollar amounts for physician charges and hospital charges, said Amber Padron, assistant director of case management at the Patient Advocate Foundation, a nonprofit that assists patients with chronic or life-threatening conditions.

Daniels’ bill listed a single charge, for $410. Under the description, it said “Emergency Room Level 1” and included the current procedural terminology code “99281.” CPT codes are used to bill for evaluation and management, or E/M, services provided by a medical professional. Level 1 is the lowest level of emergency care.

But there’s a catch: According to the American Medical Association’s CPT guide, “Triage alone is not an E/M service; therefore, it cannot be reported with an E/M code.”

It gets murkier. According to Robert Mills, a spokesperson for the AMA, the physician charge for an emergency visit under that CPT code would generally be significantly less than $410.

“It is likely the hospital consolidated the provider-billed charge with a facility fee,” Mills said, referring to a fee that hospitals tack onto bills to cover their overhead costs, such as utilities.

Amid the billing uncertainty, Daniels is clear about one thing: The decision to charge ER patients who leave without getting treatment is recent.

In 2025, she went to the same emergency room with gastrointestinal problems. After waiting for several hours, she went elsewhere for care. She said that before leaving, her mother, who accompanied her that day, confirmed with the front desk that Daniels wouldn’t be charged if they left then. And she wasn’t.

“So when I went in for this visit in April, I had no idea I was going to be charged, because it was a very similar set of circumstances,” Daniels said.

The health system didn’t respond to a question about why it changed its policy.

The Resolution

Carle didn’t budge. According to the health system’s email to Daniels, “the charges have been determined to be accurate and fully supported by the medical record documentation.”

Daniels said she paid $25 of the $410 bill and has applied for financial assistance.

Meanwhile, according to HealthLink’s statement to KFF Health News, Daniels can contest her health plan’s denial: “Ms. Daniels has the right to appeal the decision through the established appeals process.”

She’s considering it, but she remains outraged about what happened.

“How is it ethical or even legal for a hospital to essentially bill for occupying a waiting room?” she asked.

Daniels sits at a table with her arms folded on the table.
Daniels is considering contesting her health plan’s denial of coverage for the ER bill: “How is it ethical or even legal for a hospital to essentially bill for occupying a waiting room?” (Taylor Glascock for KFF Health News)

The Takeaway

Don’t assume you won’t be billed if you leave a hospital before receiving medical care. You can check with the front desk about the facility’s policy, as well as ask your insurer whether it provides coverage for such bills.

If the hospital billing department isn’t giving you information about what services you’re being billed for, request your medical records, said Padron, of the Patient Advocate Foundation.

Furthermore, when your health plan processes a claim, you should receive an explanation of benefits informing you of that and explaining what you may owe. Keep an eye on your mail and your insurance portal.

When a claim is denied, filing an appeal with your health plan is always a smart idea, Padron said.

“It’s always going to be a no if you don’t appeal,” she said.

Bill of the Month is a crowdsourced investigation by KFF Health News and The Washington Post’s Well+Being that dissects and explains medical bills. Since 2018, this series has helped many patients and readers get their medical bills reduced, and it has been cited in statehouses, at the U.S. Capitol, and at the White House. Do you have a confusing or outrageous medical bill you want to share? Tell us about it!

KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.

This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***