
How the Medical Executive-Post Survived to our 8th Anniversary?

Join Our Mailing List

And … Why the American Medical News was Shuttered after 50 Years!

[Some Musing on our Eighth Anniversary]

Ann Miller RN MHA

[Executive-Director]

Happy BirthdayAccording to well known healthcare industry journalist Kevin B. O’Reilly, a dramatic drop in medical-publishing revenues caused the recent closure of the American Medical News, effective with a final edition of the newspaper published just last month.

Published for more than five decades, AMNews was hit hard by industrywide trends. The newspaper’s revenue fell by two-thirds during the last decade, as reported by Thomas J. Easley, senior vice-president and publisher of periodic publications for the American Medical Association [AMA].

Unsustainable financial losses forced the move despite the newspaper’s editorial quality, the AMA’s senior management reportedly said. But, the Association’s other news operations will be enhanced.

###

amn

###

What the Death of American Medical News Says About the Future of American Medicine

###

How we survive!

We’ve been online for eight years now. We have a skeleton staff, a scalable business model, an almost free distribution model, no print analog, and a tiny electronic advertising revenue stream.

Oh, let’s not forget some brilliant essayists, contrarian contributors, insightful commentators and controversial opinions that are often the elephant in the virtual room. 

Our gratitude to you all is without limits.

So, how else do we do it?

Interestingly – Our print books are good, better and best sellers. We’ve been releasing one major, semi-peer reviewed text each year …. and sales are brisk. And, we are now negotiating to begin our next and ninth volume for 2014-15. We maintain our own copy-rights, perform in-house editing, seek out the best contributing authors, and reduce the cost of numerous channels of distribution. How do we do it, year after year? In a word, professional crowdsourcing.

Our consulting business is increasingly robust, too. Cudos to healthcare reform, managed care, and the PP-ACA!

And … another thing

I ask again. How do we do it? How do we stay in business?

Here are some more ways to help-us, do just that:

  1. Subscribe to the ME-P site
  2. Tell a friend or colleague about us
  3. Visit our Blogroll list
  4. Use our classified ads or advertise with us
  5. Purchase a printed handbook, dictionary, software product or textbook
  6. Use our career and educational resources
  7. “Ask a Consultant” for free advice
  8. Request a strategic competitive consultation
  9. Hire us for a medical practice valuation or revenue enhancement review
  10. Request a medical business planning RFP
  11. Purchase a practice management checklist
  12. Seek out our financial planning advice
  13. Ask for second opinion; hire our thought-leaders
  14. Request a healthcare econometrics review
  15. Seek out our practice management or business advice
  16. Become a Certified Medical Planner™ www.CertifiedMedicalPlanner.org
  17. Request a speaker for a pharmaceutical seminar or health convention
  18. Attend a seminar, sponsor or take a learning-teaching cruise with us
  19. Donate to us …  and repeat
  20. Buy a link … and repeat again
  21. Send a thank you note to our Publisher-in-Chief and Managing Editor
  22. Visit us often to review, read, rant and rave.

Bottom Line Eight Years Out

The ME-P is an austere … Labor of Love.

Please support us: Support the “Medical Executive-Post”

Printable Donation Form: Printable Donation Form

Electronic Donations: www.e-junkie.com/ecom/gb.php?c=cart&i=641232&cl=109140&ejc=2

Multi-Year Pledge Form: Multi-Year Pledge

###

QuestionEverythingWallpaper

###

Assessment

So, does the demise of the American Medical News really say anything at all about the ME-P; in addition to the future of domestic medicine? How do we avoid the same fate? Please tell us. Question Everything … Trust No One … Paddle your Own Canoe … Keep the Faith!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Did the AMNews forget the aphorism; No margin – No Mission?

Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
BLOG: www.MedicalExecutivePost.com

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Product Details

Some US Federal Budget Proposals

Join Our Mailing List

Government Shutdown Hoopla for Retirees, Inheritors and Savers

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPLost in the hoopla over the government shutdown, defunding Obamacare, and raising the debt ceiling are some proposals contained in President Obama’s budget that will have a significant impact on retirees, inheritors, and savers.

Most of the President’s proposals are aimed at enforcing higher taxes on savers who maximize their retirement plans. This is a way to raise revenue for government entitlement programs, like subsidies for health insurance, Medicare, and Social Security.

Retirement and Retirees

Back from last year is his proposal to cap contributions to IRA’s and 401(k)’s when the balance reaches a level determined by a set formula which is tied to interest rates. The proposal sets the cap at $3.4 million initially. As interest rates rise, the cap will lower. When a saver’s IRA balance hits the cap, he or she will not be allowed to make further contributions to any retirement plan.

This will mostly affect savers who terminate employment and roll large accumulations from profit-sharing plans and lump-sum distributions from defined benefit plans into their IRA’s. It will shut down their ability to save into the future.

Taxes and Inheritors

The President has yet another plan to end tax-deductible contributions for upper income earners. Only 28% of a contribution would be deductible for any taxpayer whose bracket exceeds 28%. For a taxpayer in the highest bracket, this means a tax increase of about 50%.

Another of the President’s proposals would end the ability of anyone other than a spouse to inherit a tax-deferred IRA. Under the proposal, all non-spouses inheriting an IRA would have five years to terminate the IRA and pay income taxes on the distributions. This proposal really impacts Roth IRA conversions, as most parents convert traditional IRA’s to Roths with the intention of leaving their children a non-taxable sum of money that can continue to grow tax free during their lifetime. If the President’s proposal passes, many older savers will discover that the intentions behind their Roth conversions have been nullified.

Forced Savings and Savers

While President Obama wants to cap what successful savers can stash away in retirement plans, he also wants to force employees to save for retirement. Employers will be required to open IRA’s for every employee and to fund the plan at a minimum of 3% of the employee’s pay, unless the employee specifically opts out. The employee can contribute more than 3%, up to the $5,000 cap for those under 50 and $6,000 for those over 50.

Of course, savvy savers and ME-P readers know most of us need to be saving 20% to 50% of our salaries, depending on our ages, so saving just 3% of pay won’t amount to much in the way of retirement income.

Good News

On the positive side, the President wants to end required minimum distributions on IRA balances under $75,000. This will reduce some paperwork for savers with smaller IRA’s who are not making withdrawals.

Typically, most retirees with small IRA’s are those with less savings anyway, who need to take withdrawals from their IRA’s to make ends meet. So it’s doubtful this rule change will have much impact.

Finally, the President proposes letting inherited non-spousal IRA’s enjoy the same benefit of a 60-day rollover window on any distribution, similar to what they can do with a non-inherited IRA. This will simply eliminate a lot of confusion, as most people don’t understand the 60-day rollover provision does not include inherited IRA’s.

Shutdown[US Federal Government Shut-Down]

Assessment

Of course, whether any or all of these proposals make it into law is anyone’s guess. Anyone whose retirement and estate planning includes saving in IRA’s will want to keep an eye on these provisions as the budget moves through Congress.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
PODIATRISTS: www.PodiatryPrep.com
BLOG: www.MedicalExecutivePost.com

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

On Setting Your Household Budget [ugh!]

 Join Our Mailing List 

Trim Daily Expenditures or Don’t Sweat the Small Stuff?

By Lon Jefferies MBA CFP® http://www.NewWorthAdvice.com

Lon JefferiesHow often do you see articles containing money saving tips? Make dinner at home more often and eat out less, rent movies rather than going out, bring lunch to work rather than visit a restaurant, take advantage of coupons, and brew your coffee rather than driving-through Starbucks.

Do Advice Tips Work?

Are these tips worthwhile? If we spare the $8 expense of a lunch five days per week, 50 weeks per year, we could save $2,000 – nothing to scoff at!

However, what’s the cost of these savings? Eating at our desk everyday removes our ability to get outside and away from our work for that important hour, and prevents us from spending time, talking to, and laughing with friends. Is there a better way?

The DOL Report

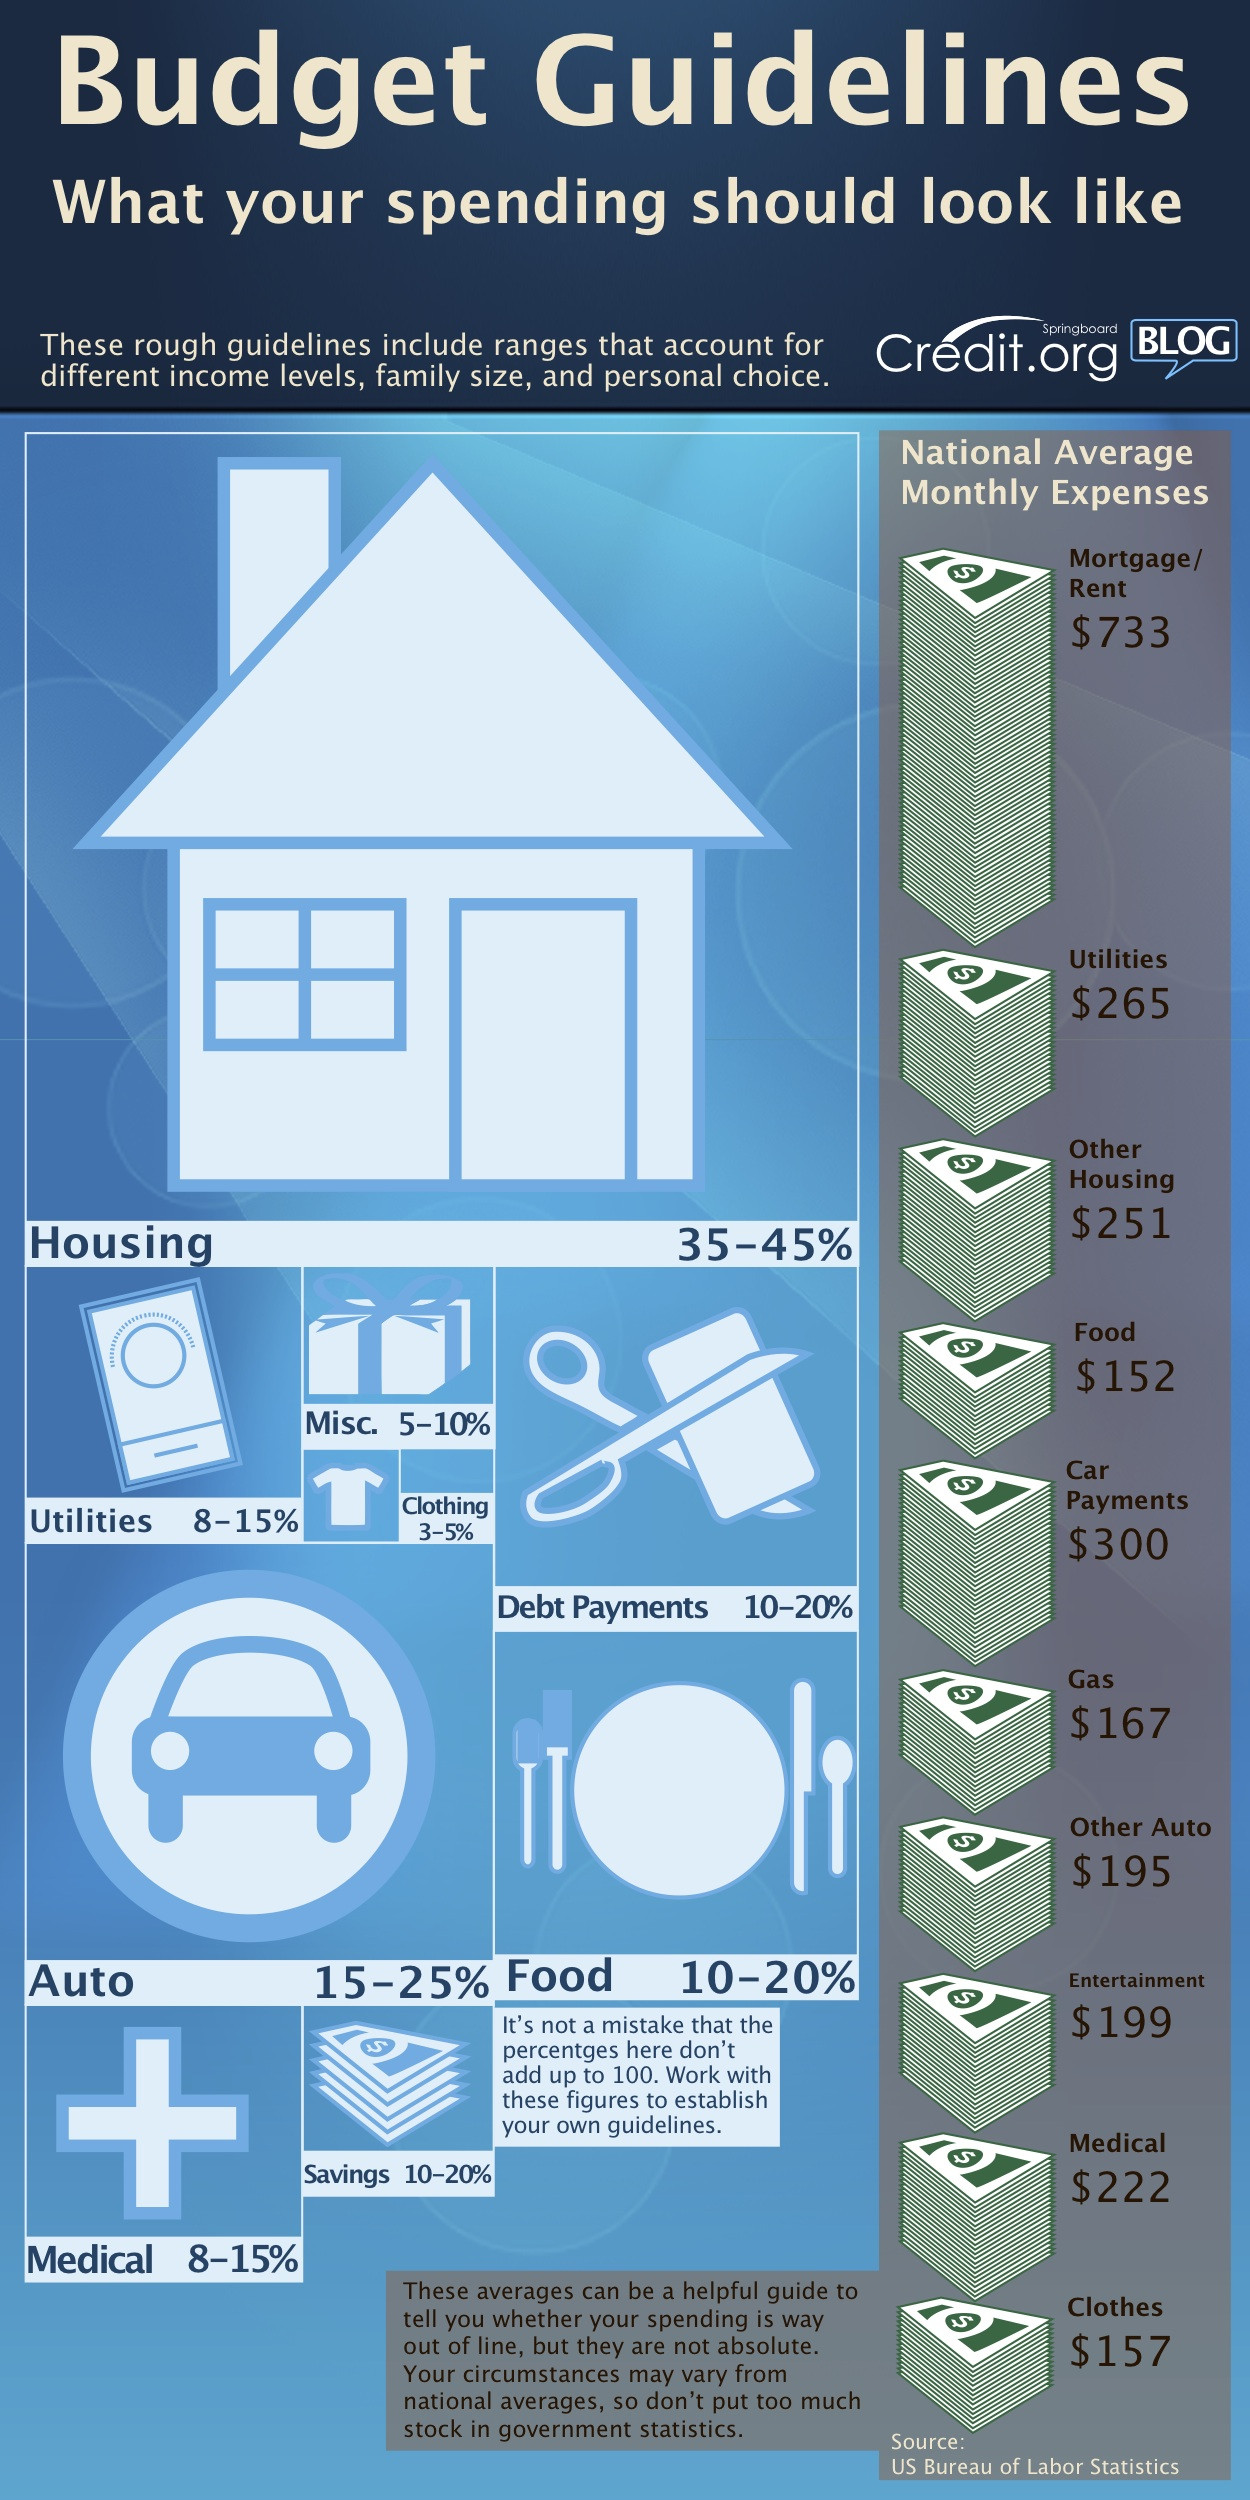
According to a new study released by the Department of Labor, the average U.S household earns $65,132 per year before taxes, and spends an average of $50,631 on annual expenditures (excluding taxes and savings). Of that spending, $20,093, or 39.7%, goes towards housing expenses.

Additionally, $11,211, another 22.1%, goes towards transportation and automobiles. Combined, those elements make up 61.8% of the average household’s spending!

By comparison, only $10,835, or 21.4%, of our spending goes toward food, apparel and services, and entertainment combined. If we are going to explore ways to reduce spending, shouldn’t we start with the elements that are costing us the most?

Example:

For instance, most financial professionals say only 28% of our gross income should be committed to housing costs. Of the average $65,132 gross income, 28% would mean reducing our housing spending from $20,093 to $18,236, saving us $1,857 per year.

Assuming a 250-day work year, this savings could allow us to spend nearly $7.50 per day on lunch, enjoying our friends, and taking a break from the office.

More dramatically, reducing our mortgage payment by $500 per month, saving us $6,000 per year, pays for a whole lot of dinner and movie date nights.

Similarly, assume we spend $4 per day enjoying our morning coffee at Starbucks with friends five times a week, for 50 weeks a year. Annually this would cost us $1,000. Now suppose we purchase a nice used automobile for $15,000 rather than a new car for $25,000. This saves us $10,000 or 10 years worth of coffee breaks with friends (plus interest!).

Prioritize

Of course, everyone has different priorities. I suggest spending your money on what you are passionate about. For the occasional car fanatic, perhaps spending more on a car that makes you happy each day is preferable to other spending options.

Likewise, if homes happen to be your hot spot, heavy spending in this area makes sense.

Different Doctors?

However, I’d suggest that for most people, the experience of constantly eating with friends or spending a night out with your spouse is more likely to bring happiness than the possession of an expensive home or car. After all, would you rather eat out with friends or clip coupons alone in a large kitchen?

But, are doctors any different?

Budgets

Assessment

Consequently, reducing large expenses like a home mortgage or car loan may be the most effective way to stay within your budget and maintain your level of happiness – especially for docs!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

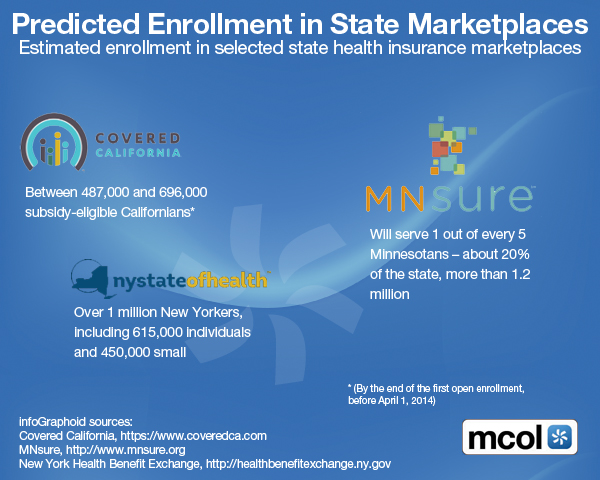
Marketplace HIE Enrollment Update

Join Our Mailing List

In Selected States

[By www.MCOL.com]

###

enrollment

###

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

How affordable is the new health care law – Really?

Join Our Mailing List 

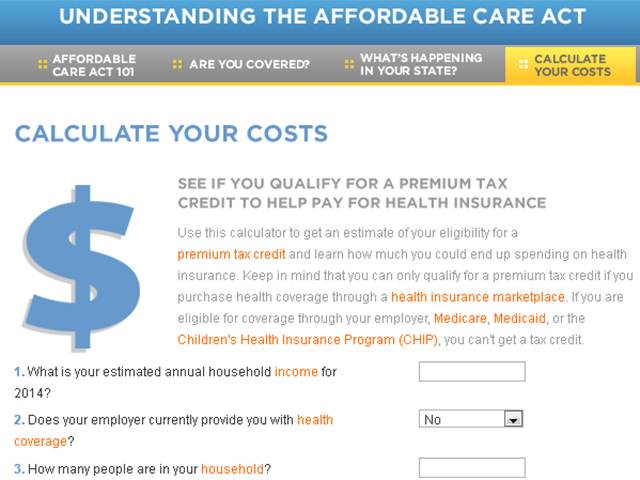
Calculate your costs

[By Staff Reporters]

The Affordable Care Act is going to change health care for tens of millions of Americans.

But, what about the cost?

LET’S BEGIN

ACA

###

NOW CALCULATE

Whether you’re an individual who has health insurance or needs it, or a small business owner, you need to know how health care reform affects you.

What’s it going to cost? What’s happening in your state?

### 8C9220491-tdy-130929-aca-calculator-4x3-606p_blocks_desktop_large

### 

Link: http://www.nbcnews.com/health/how-affordable-new-health-care-law-really-calculate-your-cost-8C11296290

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Understanding Basics of the Health Insurance Exchanges [HIEs]

Join Our Mailing List 

The Four Basic Categories of the PP-ACA

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPThe opening date was yesterday, October 1, 2013. And today, the competition is lined-up and ready to go after bronze, silver, gold, and even platinum.

These competitors aren’t athletes, but insurance providers. The field they are entering is the new health insurance exchanges [HIEs] as mandated by Obamacare [ACA].

The New Year

Beginning January 1st 2014, nearly everyone in the US will need to have health insurance or pay a tax penalty. Those not insured through their employers can apply for coverage through these health insurance exchanges, also called “marketplaces.” Enrollment began October 1st, 2013 for coverage starting in January, 2014.

These exchanges are intended to make it easier to find insurance providers and compare their coverage and costs. Each state’s exchange website will list all the policies available in that state, with prices and policy provisions.

So far, over half of the states (including my State of South Dakota) have opted to use exchanges managed by the federal government instead of setting up their own.

The Four Basic [Colors] Categories

Bronze, silver, gold, and platinum describe the four basic categories of policies that will be available through the exchanges at different costs. Here is a very brief summary of each category.

Bronze

The least expensive option is a bronze plan, which might be the best choice for younger people with lower incomes and good health. The plan will pay 60% of health care costs and the insured will be responsible for 40%.

Silver

The second level, silver, will pay 70% of health care costs.

Gold and Platinum

Gold covers 80%, and a platinum plan covers 90%. Obviously, the categories with higher benefits also will have higher premiums.

The Essential Benefits

All these plans are required to cover “essential health benefits.” These include preventive and wellness care like cancer screening, chronic disease management, pediatric care, many prescription drugs, injury rehabilitation, mental health and addiction treatment, maternity and newborn care, hospitalization, and emergency services.

Companies are not allowed to deny coverage or charge more for those with pre-existing conditions. There are no lifetime benefit limits.

The Carrot and Stick Approach

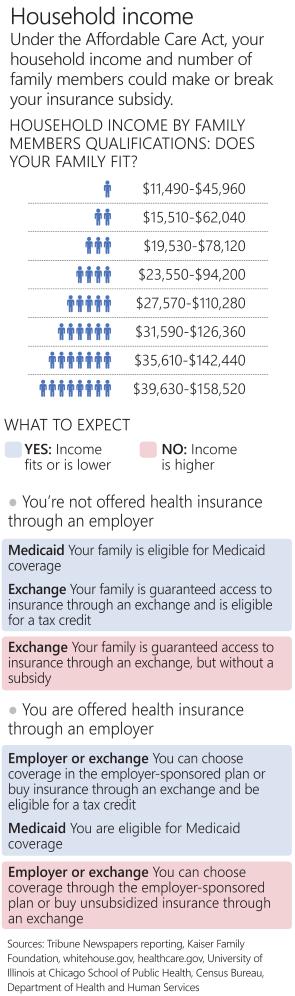
The requirement to have health insurance coverage, the “stick” of Obamacare, is accompanied by a “carrot” in the form of federal subsidies to help pay insurance premiums. It’s estimated that two-thirds of Americans will be eligible for subsidies, which will be figured on a sliding scale. The upper limit for qualifying is four times the federal poverty level, which amounts to about $88,000 a year for a family of four.

Other Outlines

This ME-P summary is just the barest outline of the health care changes coming our way. To find out more, it’s a good idea to spend some time online, especially at two sites that offer a lot of helpful information.

  1. The First site is the federal government website at www.HealthCare.gov. It provides links to the state exchanges, plus detailed information that for the most part is explained in straightforward, plain English.
  2. The Second site is the Henry J. Kaiser Family Foundation at kff.org. An especially useful tool available here (http://kff.org/interactive/subsidy-calculator/) is a calculator to determine the federal subsidy that applies at your family’s income level.

Obamacare 2014

The elements of Obamacare that take effect in 2014 represent a huge shift in the way we cover health care costs. I strongly recommend that you start now to figure out what this will mean for you and your family.

###

Obama Care

###

Don’t wait until December and end up making hasty decisions in a last-minute rush. The more informed you are; the better insurance choices you can make.

Assessment

The changeover to the new insurance environment is likely to be chaotic and confusing. Navigating it will take some energy, commitment, and stamina. When all the scrambling is over, we can only hope the ultimate winners will be the American people.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Affordable Care Act HIEs at Launch

Join Our Mailing List

Some Important Launching Information for Doctors and Business Owners

By Bobby Whirley CPA

[Whirley & Associates LLC – Alpharetta, GA]

Dear ME-P Readers,

The ACA (Affordable Care Act) requires employers to provide their workers with a notice about the state health insurance exchanges.

Today October 1st is the deadline for providing these notices.

These exchanges will sell insurance to individuals who don’t get coverage through their employers. The exchanges are also available to medical practices and small businesses, which may or may not currently offer heath care coverage.

The Fines?

Some doctors or business owners are concerned about paying a fine of up to $100 per day under the general non-compliance penalty provisions.

The recent notice of the Affordable Health Care Act states that there will be no penalty.  Please refer to http://www.dol.gov/ebsa/faqs/faq-noticeofcoverageoptions.html

If your medical practice, clinic or company is covered by the Fair Labor Standards Act (you have one or more employees, sales of over $500,000, and deal in interstate commerce), you must provide a written notice to your employees about the Health Insurance Marketplace by Oct 1, 2013.

Model Notices

The U.S. Department of Labor has two model notices to help employers comply. There is one model for employers who do not offer a health plan and another model for employers who offer a health plan or some or all employees.

More:

The model notices are also available in Spanish and MS Word format at http://www.dol.gov/ebsa/healthreform/

###

Health-Information-Exchange

###

Assessment

Employers may use one of these models, as applicable, or a modified version. More compliance assistance information is available in a Technical Release issued by the US Department of Labor.

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
BLOG: www.MedicalExecutivePost.com

Product DetailsProduct Details

Product Details

5 Car Interior Upgrades that Will Make Your Drive More Enjoyable

Join Our Mailing List 

I Love Used [Previously Owned] Cars –– But!

Dr. Marcinko

By Dr. David Edward Marcinko MBA CMP™

By Nalley Lexus Roswell

As a doctor and financial advisor, I love a good used car.

Why? Let some else take the monetary depreciation hit. A vehicle about 2-4 years old, depending on make or model, is usually about right.

Take my own favorite auto, for example. It is a Jaguar 2000 XJ-V8-L, and she is a classic beauty. My daughter even named her Ele; short for Elegant. And, I show her off every chance I get.

But, did I pay $90,000 for her as a new vehicle? No Way!

Ageism

Allow me to say it again.  I love a good used car. But unfortunately, cars like people, get old over time.

So, if your car is starting to look and feel a bit tired and you don’t have the cash, or are too smart to go for a new one, you can consider investing in some car interior upgrades. An interior upgrade doesn’t need to cost a fortune, and you might be surprised at what a difference it can make. And it is a nice treat for your car as Fall approaches.

My Jaguar's engine after a steam

My Five Tips

Here are 5 car interior upgrades we at are confident will help make your ride more enjoyable without breaking the bank.

1. New seat covers

Car seats quickly get worn and tired, fabric can get ripped or stained, and leather or PVC can age and crack, making the seats rather less comfortable. New seat covers could make a big difference. There are a huge variety of different covers on the market with styles to suit all budgets and tastes. If you want to spend a bit more, consider having some or all of the seats completely re-upholstered. You’ll soon be enjoying a much more comfortable drive.

2. Driver’s seat upgrades

If the driver’s seat really isn’t comfortable any more, then a more viable option might be to upgrade the whole seat. A sports seat will provide a more comfortable, responsive driving position, offering much more support to different parts of your body.

3. Upgraded audio system

Music can make even the longest car journeys more bearable, so why not consider investing in an upgraded audio system? Talk to your local dealer, or neighborhood kid, about getting a price on a new system and having it fitted. You may be quite limited by the dimensions of the cavity on your dashboard, so make sure you measure accurately and opt for a device that you can secure when the car is not in use to minimize the risk of theft.

4. Air purifier

Although you may use your air conditioner, the air in the cabin of your car can still get stale. Unless you open your car windows all the time, the chances are that you are continually breathing dead air. An air purifier can be bought cheaply, and in most cases, installs easily into the cigarette lighter socket.

5. Car mounts

Car mounts are an increasingly popular way for drivers and their passengers to make better use of their gadgets on the move. A dashboard car mount can help you store and use your iPhone or iPod Touch on the go. A mount on your sun visor can be used to keep your sunglasses safe and secure. You can even get a mount, which attaches to the back of the driver or front passenger seat and then folds down into a table for the rear passenger to use for a laptop.

###

Jaguar Touring sedan XJ-V8-LWB

###

Jaguar front seat

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

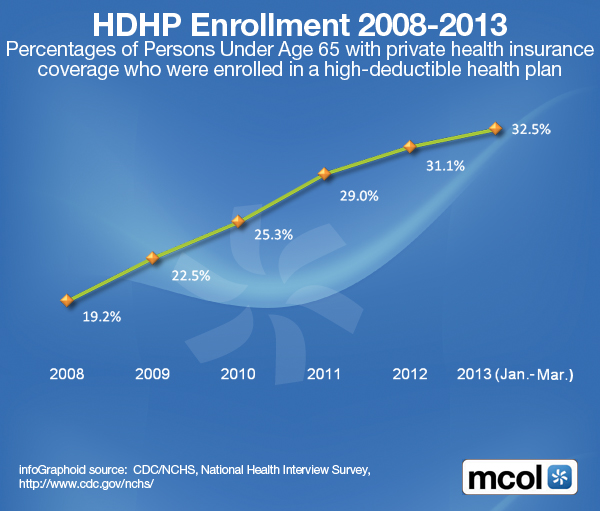
HDHP Enrollment Stats for 2008-2013

Join Our Mailing List

Enrollment Stats for those Under Age 65

By www.MCOL.com

### HDHCP

###

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Some Modern Issues Impacting Hospital Revenue Cycles

Join Our Mailing List

By Carol S. Miller RN CPM MHA

By Dr. David Edward Marcinko MBA CMP™

Carol S. Miller “Collectively the healthcare industry spends over $350 Billion to submit and process claims while still working with cumbersome workflows, inefficient processes, and a changing landscape marked by increasing out-of-pocket cost for patients as well as increasing operating costs.”

The Norm Continues Downhill

For many years hospitals and healthcare organizations have struggled to maintain and improve their operating margins.  They continue to face a widening gap between their operating costs and the revenues required to cover not only current costs, but also to finance strategic growth initiatives and investments.

Faced with increased operational costs and associated declines in rates of reimbursement, many healthcare hospital executives and leaders are concerned that they will not achieve margin targets.  To stabilize the internal financial issue, some hospital have focused on lowering expenses in order to save costs – an area they control and an area that will show an immediate impact; however, that is not the best solution.

Beware Cost Reductions

Hospital executives are concerned with the effect that these reductions may have on patient quality and service.  Finding ways to maximize workflow to lower operating costs is vital.  Every dollar not collected negatively impacts short- and long term capital projects, lowers patient satisfaction scores and possibly affects quality of patient care.

Status Today

Hospitals, healthcare organizations and all medical providers are under great pressure to collect revenue in order to remain solvent. And so, here are some of the issues impacting the modern hospital revenue cycle as Obama-Care, or the PP-ACA of 2010, is launched next month?

Issues Impacting the Revenue Cycle

Several of the major leading issues facing the revenue cycle are:

  • Impact of Consumer-driven Health – This process has emerged as a new approach to the traditional managed care system, shifting payment flows and introducing new “non-traditional” parties into the claims processing workflow.  As market adoption enters the mainstream, consumer-driven health stands to alter the healthcare landscape more dramatically than anything we have seen since the advent of managed care.  This process places more financial responsibility on the consumer to encourage value-drive healthcare spending decisions.
  • Competing high-priority projects –Hospitals are feeling pressured to maximize collections primarily because they know changes are coming down the pike due to healthcare reform and they know they will need to juggle these major initiatives along with the day-to-day revenue cycle operations.
  • Lack of skilled resources in several areas – Hospital have struggled to find the right personnel with sufficient knowledge of project management, clinical documentation improvement, coding and other revenue cycle functions, resulting in inefficient operations.
  • Narrowing margins – Declines in reimbursement are forcing hospitals to look at their organization to determine if they can increase efficiencies and automate to save money.  Hospitals are faced with the potential of increased cost to upgrade and adapt clinical software while not meeting budget projections.  There are a number of factors contributing to the financial pressure including inefficient administrative processes such as redundant data collection, manual processes, and repetitive rework of claims submissions.  Also included are organizations using outdated processes and legacy technologies.
  • Significant market changes – Regardless of what happens with the Patient Protection and Affordable Care Act, hospitals will have to deal with fluctuating amounts of insured and uninsured patients and variable payments.
  • Limited access to capital – With the trend towards more complex and expensive systems, industry may not have the internal resources and funding to build and manage these systems that keep pace with the trends.
  • Need to optimize revenue – There are five core areas hospitals have to examine carefully and they are:
    • ICD-10 – This is an entirely new coding and health information technology issue but is also a revenue issues
    • System integration – Hospitals need to look at integrating software and hardware systems that can combine patient account billing, collections and electronic health records.
    • Clinical documentation – Meaningful use will require detailed documentation in order for payment to be made and this is another revenue issue.
    • Billing and claims management – Reducing denials and reject claims, training staff, improving point-of-service collections and decreasing delays in patient billing can improve the revenue cycle productivity,
    • Contract analysis – Hospitals need to focus more on negotiating rates with insurers in order to increase revenue.

Hospital

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details

Product DetailsProduct Details

***

Do creepy anti-Obamacare ads defile an icon?

Join Our Mailing List

Is Uncle Sam Under Attack?

via: The Joker

Featuring a bizarre Uncle Sam figure, these commercials are coming under fire from liberals as debasing a national figurehead.

###

creepy-uncle-sam

[CLICK HERE FOR VIDEO]

http://www.youtube.com/watch?v=R7cRsfW0Jv8

More:

Creepy ads target Obamacare

Assessment

What do you think?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

On the Notice of Privacy Practices

Join Our Mailing List 

Encryption and HHS are Taking Hits

[By D. Kellus Pruitt DDS]

1-darrellpruittIt is bad politics for the President’s Department of Health and Human Services to get caught deceiving voters.

Word gets around much faster than it did before transparency sucked the power from the entrenched.

The NoPP

You know those Notice of Privacy Practices (NoPP) forms we are asked to sign in doctors’ offices? Since it makes no difference to anyone whether patients sign them or not, why needlessly waste everyone’s time? The NoPP is not an agreement, and just because virtually everyone is tricked into signing it, does not mean anyone reads it. HIPAA has become a source of danger to patients, with no redeeming value.

HHS Estimates 

According to the US Department of Health and Human Services own recent estimate:

“… many centuries of time—nearly 35 centuries, in fact, or just short of 30.7 million hours—will be devoted each year by healthcare providers and patients for the dissemination to patients and their acknowledgement of HIPAA notices of privacy practices [NoPP] for protected healthcare information, HHS estimates. Even at just 3 minutes apiece, with 613 million of these routine privacy notices to be delivered, signed and stored, the time adds up…”

-Joseph Conn

… “HHS estimates 32.8 million hours of interaction required to comply with privacy, security rules” …

-ModernHealtcare.com [September 5, 2013]

http://www.modernhealthcare.com/article/20130904/BLOG/309049995?AllowView=VW8xUmo5Q21TcWJOb1gzb0tNN3RLZ0h0MWg5SVgra3NZRzROR3l0WWRMWGJYZjBGRWxyd01qUzMyWmVpNTNnWUpiV2s=&utm_source=link-20130904-BLOG-309049995&utm_medium=email&utm_campaign=hits

Censorship Concerns? 

I tried to bring attention to this absurdity over a year ago – back when HHS was still keeping unfavorable news about EHRs hidden from voters using censorship:

… “Put another way, the ONLY reason for a doctor to ask patients if they feel like signing the NoPP is to protect already busy doctors from a HIPAA fine. How is that not senseless, yet admittedly humorous bureaucratic waste?” …

On July 3, 2012, my opinion of the waste that HHS recently confirmed was censored by an HHS employee from the taxpayer-supported Linkedin site, Health IT and Electronic Health Records. If that is not against federal law, it damn sure should be.

http://www.linkedin.com/groups/IT-in-Healthcare-Why-Building-3993178.S.216432610?qid=bafac2e5-fb9c-4a39-8348-5a3074abff67&trk=groups_items_see_more-0-b-ttl

Among the items that HHS requires providers include in Notices of Privacy Practice is a one-sentence statement addressing data breaches:

…“We will let you know promptly if a breach occurs that may have compromised the privacy or security of your information [unless it is encrypted]”…

http://www.hhs.gov/ocr/privacy/hipaa/npp_booklet_hc_provider.pdf

Now that it is widely known that encryption is no longer acceptably secure, protection from accountability is encryption vendors’ only remaining selling point. HIPAA stipulates that if breached patient information is encrypted according to standards set forth by the National Institute of Standards and Technology (NIST), doctors are freed from the tremendous cost of notifying (former) patients – even though patients’ privacy and security have been nevertheless compromised.

For example, two weeks ago, the NIST abandoned the very encryption standards that HIPAA demands. Oops! (See: “Government Standards Agency ‘Strongly’ Suggests Dropping its Own Encryption Standard,” by Jeff Larson and Justin Elliott, ProPublica, September 13, 2013).

http://www.propublica.org/article/standards-agency-strongly-suggests-dropping-its-own-encryption-standard

###

eMR Privacy

###

NSA Secrets 

US spy agency NSA’s secret success at decrypting previously impenetrable codes – which was revealed by former NSA contractor Edward Snowden – proves that today’s best encryption is tomorrow’s crossword puzzle. What’s more, once an individual’s medical identity is lost in the cloud, it can never be reeled back in.

And, when DNA records are included, a breach today could put the welfare of generations of Americans at risk.

A Gut-Check 

The ultimate gut-check: If your encrypted identity were fumbled, wouldn’t you want to be notified? Of course you would.

Assessment 

In my opinion, the HIPAA Rule should be immediately amended to demand notification of all individuals involved in all data breaches unless they allow opt out. Who knows? Some might prefer not to be bothered.

What is your opinion; doctor, patient and/or consultant?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

How Many Die From Medical Mistakes in U.S. Hospitals?

Join Our Mailing List 

Patient SafetyExploring Quality of Care in the US

By Marshall Allen
ProPublica, Sep 19th, 2013, 10:03 am

AMIn 2010, the Office of Inspector General for Health and Human Services said that bad hospital care contributed to the deaths of 180,000 patients in Medicare alone in a given year.

Now comes a study in the current issue [1] of the Journal of Patient Safety that says the numbers may be much higher — between 210,000 and 440,000 patients [2] each year who go to the hospital for care suffer some type of preventable harm that contributes to their death, the study says.

That would make medical errors the third-leading cause of death in America [3], behind heart disease, which is the first, and cancer, which is second.

New Estimates

The new estimates were developed by John T. James, a toxicologist at NASA [4]’s space center in Houston who runs an advocacy organization called Patient Safety America [5]. James has also written a book [6] about the death of his 19-year-old son after what James maintains was negligent hospital care.

Asked about the higher estimates, a spokesman for the American Hospital Association said the group has more confidence in the IOM’s estimate of 98,000 deaths. ProPublica asked three prominent patient safety researchers to review James’ study, however, and all said his methods and findings were credible.

What’s the right number? Nobody knows for sure. There’s never been an actual count of how many patients experience preventable harm. So we’re left with approximations, which are imperfect in part because of inaccuracies in medical records and the reluctance of some providers to report mistakes.

Patient safety experts say measuring the problem is nonetheless important because estimates bring awareness and research dollars to a major public health problem that persists despite decades of improvement efforts.

“We need to get a sense of the magnitude of this,” James said in an interview.

James based his estimates on the findings of four recent studies that identified preventable harm suffered by patients – known as “adverse events” in the medical vernacular – using use a screening method called the Global Trigger Tool [7], which guides reviewers through medical records, searching for signs of infection, injury or error. Medical records flagged during the initial screening are reviewed by a doctor, who determines the extent of the harm.

Four Studies

In the four studies, which examined records of more than 4,200 patients hospitalized between 2002 and 2008, researchers found serious adverse events in as many as 21 percent of cases reviewed and rates of lethal adverse events as high as 1.4 percent of cases.

By combining the findings and extrapolating across 34 million hospitalizations in 2007, James concluded that preventable errors contribute to the deaths of 210,000 [2] hospital patients annually.

That is the baseline. The actual number more than doubles, James reasoned, because the trigger tool doesn’t catch errors in which treatment should have been provided but wasn’t, because it’s known that medical records are missing some evidence of harm, and because diagnostic errors aren’t captured.

An estimate of 440,000 deaths from care in hospitals “is roughly one-sixth of all deaths that occur in the United States each year,” James wrote in his study. He also cited other research that’s shown hospital reporting systems and peer-review capture only a fraction of patient harm or negligent care.

“Perhaps it is time for a national patient bill of rights for hospitalized patients,” James wrote. “All evidence points to the need for much more patient involvement in identifying harmful events and participating in rigorous follow-up investigations to identify root causes.”

###

Ankle-Leg Trauma

###

The Patient Safety Gurus

Dr. Lucian Leape, a Harvard pediatrician who is referred to the “father of patient safety,” [8] was on the committee that wrote the “To Err Is Human” report. He told ProPublica that he has confidence in the four studies and the estimate by James.

Members of the Institute of Medicine committee knew at the time that their estimate of medical errors was low, he said. “It was based on a rather crude method compared to what we do now,” Leape said. Plus, medicine has become much more complex in recent decades, which leads to more mistakes, he said.

Dr. David Classen, one of the leading developers [9]of the Global Trigger Tool, said the James study is a sound use of the tool and a “great contribution.” He said it’s important to update the numbers from the “To Err Is Human” report because in addition to the obvious suffering, preventable harm leads to enormous financial costs.

Dr. Marty Makary, a surgeon at The Johns Hopkins Hospital whose book “Unaccountable” calls for greater transparency in health care, said the James estimate shows that eliminating medical errors must become a national priority. He said it’s also important to increase the awareness of the potential of unintended consequences when doctors perform procedure and tests. The risk of harm needs to be factored into conversations with patients, he said.

Leape, Classen and Makary all said it’s time to stop citing the 98,000 number.

IOM’s Death Estimate

Still, hospital association spokesman Akin Demehin said the group is sticking with the Institute of Medicine’s estimate. Demehin said the IOM figure is based on a larger sampling of medical charts and that there’s no consensus the Global Trigger Tool can be used to make a nationwide estimate. He said the tool is better suited for use in individual hospitals.

The AHA is not attempting to come up with its own estimate, Demehin said.

Assessment

Dr. David Mayer, the vice president of quality and safety at Maryland-based MedStar Health [10], said people can make arguments about how many patient deaths are hastened by poor hospital care, but that’s not really the point. All the estimates, even on the low end, expose a crisis, he said.

“Way too many people are being harmed by unintentional medical error,” Mayer said, “and it needs to be corrected.”

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com

FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

It’s Here: Financial Management Strategies for Hospitals and Healthcare Organizations

Join Our Mailing List

Finally … Our Newest ME-P Textbook Release

By Ann Miller RN MHA

[Executive-Director]

In this book, a world-class editorial advisory board and an independent team of contributors draw on their experience in operations, leadership, and Lean managerial decision making to share helpful insights on the valuation of hospitals in today’s changing reimbursement and regulatory environments.

Using language that is easy to understand, Financial Management Strategies for Hospitals and Healthcare Organizations [Tools, Techniques, Checklists and Case Studies]  integrates prose, managerial applications, and regulatory policies with real-world case studies, models, checklists, reports, charts, tables, and diagrams. It has a natural flow, starting with costs and revenues, progressing to clinic and technology, and finishing with institutional and professional benchmarking. The book is organized into three sections:

  1. Costs and Revenues: Fundamental Principles
  2. Clinic and Technology: Contemporary Issues
  3. Institutional and Professional Benchmarking: Advanced Applications

The text uses healthcare financial management case studies to illustrate Lean management and operation strategies that are essential for healthcare facility administrators, comptrollers, physician-executives, and consulting business advisors. Discussing the advancement of financial management and health economic principles in healthcare, the book includes coverage of the financial features of electronic medical records, financial and clinical features of hospital information systems, entity cost reduction models, the financial future of mental health programs, and hospital revenue enhancements.

CASE MODEL: Managerial Costs

###

book

Description

Table of Contents

Editor Bio(s)

Reviews

Foreword.Baum

Foreword.Nash

###

The Companion Text

Product Details

BOOK FOREWORD / TESTIMONIAL

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

And, send us a book review; the good, bad and ugly!

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Product Details  Product Details

Some Prudent Thoughts on Hospital Stewardship

Join Our Mailing List 

And … Capital Formation

By Calvin Weise MBA CPA CMA

By Dr. David Edward Marcinko MBA CMP™

Some of the most important strategic decisions hospital executives make are related to capital expenditures. Almost every hospital has capital investment opportunities that are far in excess of their capital capacity. Capital investments are bets on the future. How these capital bets are placed has long-lasting implications. It is of utmost importance that hospitals bet right.

Hospitals as Businesses

Hospitals are capital intensive businesses. Hospital buildings are unique structures that require large amounts of capital to construct and maintain. Inside these buildings are pieces of expensive equipment that have fairly short lives. Technological innovations continually drive demand for new and more expensive equipment and facilities. The ability to continually generate capital is the lifeblood of hospitals.

But – Profits Needed

In order to compete and succeed, it’s imperative for hospitals to continually invest in large amounts of capital equipment and expensive facilities.

Capital investment is fueled by profit. In order to continually make the necessary capital investments, hospitals must be profitable. Hospitals unable to generate sufficient profit will fail to make important capital investments, weakening their ability to compete and survive.

Hospital managers bear important responsibility in choosing which capital investments to make. There are always more capital opportunities than capital capacity. In many cases, capital opportunities not taken by hospitals create openings for others with capital capacity to fill the vacuum. By not taking such opportunities, hospitals are weakened, and their operating risk increases.

Stewardship

Stewardship is a term that aptly describes the responsibility borne by hospital managers in making capital investments. The New Testament parable of the talents describes this kind of stewardship. In this story, a merchant entrusted three managers with money to invest. One manager was given five units, another two, and a third one. At the end of the investment period, the two managers given five units and two units reported a 100% return. The manager given one unit reported zero return — he was fired and his unit was given to the first manager.

CXOs are Stewards

This is stewardship — and hospital managers are stewards of their organizations’ assets. Too often, not-for-profit hospital managers hold an erroneous view of the returns expected of them. Like the third manager in the parable, they think zero return on equity is acceptable. They understand capital investment funded by debt needs to cover the interest on the debt, but they view capital investments funded by equity as having no cost associated with the equity.

From an accounting perspective, they are right. From a stewardship perspective they are dead wrong — just like the third manager in the parable.

###

Hospital

####

Here’s Why

As stewards, they are responsible for managing the entrusted assets. They can either put these assets at risk themselves, or they can put those assets in the market and let other managers put them at risk. If they choose to put them at risk themselves, then they have the mandate of creating as much value from putting them at risk as they would realize if they put them in the market for other managers to put at risk.

CXOs have the duty to realize returns that are equivalent to the returns they could realize in the market; otherwise, they should just put them in the market. They can either invest in hospital assets or work the assets themselves, or they can invest in financial market assets so others can work the assets. When they choose to invest in hospital assets, the required return is not zero. That’s the return they get fired for. The required return is equivalent to market returns.

Assessment

Thus, when evaluating performance of hospital management teams, the minimum acceptable performance level is return on equity that is equivalent to the return that could be realized by investing the hospital assets in the market. And when evaluating a capital investment opportunity, it is important to apply a capital charge equivalent to the hospital’s weighted cost of capital — a measure that imputes an appropriate cost to the equity portion of the capital along with the stated interest rate for the debt portion of the capital structure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

More ME-P Industry Leading “WORKING WHITE-PAPERS”

Join Our Mailing List

OUR INDUSTRY “WORKING WHITE-PAPER” KNOWLEDGE SERIES … for only $99 each!

By Ann Miller RN MHA

[ME-P Executive Director]

At the ME-P working white-paper and iMBA Knowledge Center, we bring to life health administration best practices for BDs, RIAs, consulting firms, private equity and mutual fund companies, institutional wealth managers, physician-executives, administratrors, CXOs, hospitals and clinics, and large financial planning and business management firms.

Books

Certified Medical Planner

###

Therefore, as part of the combined ME-P and iMBA Research Library®, we highly recommend these Working White-Papers [WW-Ps] on various business management principles of the healthcare industry.

Topics: https://medicalexecutivepost.com/wp-content/uploads/2009/02/imba-inc-firm-services.pdf

Sample: http://certifiedmedicalplannerdotorg1.files.wordpress.com/2012/03/summary-white-paper-topics2.pdf

Checklists: https://medicalexecutivepost.com/office-checklists-on-cd-rom/

PayPal: Only $99 each.

ORDER HERE: MarcinkoAdvisors@msn.com

More Info

https://medicalexecutivepost.com/white-papers/

Business%20Optimization

On Our Financial Comfort Zones

Join Our Mailing List 

Exploring the Range

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPTry to imagine the enormous range of possible financial conditions in which human beings can live. At the lowest end is bare subsistence—the minimum food and shelter possible to sustain life. At the highest end is unlimited wealth—multi-billionaires with more than they, their children, and their grandchildren could possibly spend.

Think: Abraham Maslow’s hierarchy of needs.

The Rest of Us

Most of us, including doctors of course, live in relatively narrow bands somewhere in between these extremes. In Wired for Wealth, we describe these bands as “financial comfort zones.”  People who share a financial comfort zone tend to have similar incomes, lifestyles, spending and savings habits, and beliefs about money.

For those growing up in wealthy families, “normal” may include private schools, international travel, live-in household help, and expectations of an Ivy-League education followed by a lucrative career.

Those growing up in families with limited incomes will inhabit a much lower financial comfort zone. Their “normal” might include shopping at thrift stores, squeaking by from month to month, and having little or no expectation of higher education.

In both cases, the expectations people grow up with tend to keep them in their financial comfort zones. These zones are artificial financial boundaries that we impose on ourselves, and they are not necessarily defined by what we can or cannot afford. Yet we become uncomfortable if we move too far outside them.

Expanding the Zone

Certainly, people can and do expand their financial comfort zones. Children who grow up in low-income families, for example, may be able to get an education and go on to careers that bring them financial success far beyond that of their parents.

The real problems arise when circumstances unexpectedly push people out of their financial comfort zones.

Out of the Zone

I once had a client couple inherit several million dollars. They had no idea Mom had that much money. All at once, they had the means to move into a much higher financial comfort zone. Yet their reaction was depression. They came into my office asking, “What is wrong with us?” We spent some time exploring their money beliefs and discovered their number-one money script was “Money we didn’t earn isn’t worth having.” Moving slowly out of their financial comfort zone thru their-own efforts would have been fine. Being shoved out of it by an unearned inheritance was a challenge.

It’s no wonder that many people, coming into unexpected wealth, unconsciously feel a need to get rid of it. It’s one way to get back into the familiar zone where they know how things work, they are comfortable, and they belong.

Solo Doc

The Higher Zone

The same thing can happen to those in higher financial comfort zones. Suppose a high-earning medical or professional couple, who are accustomed to an affluent lifestyle, lose nearly half their net worth in an economic downturn. Then; one of them is laid off. They aren’t going to starve. In fact, they could scale back their spending a great deal and still live perfectly comfortably.

Yet this may not seem like an option to them. Changing their financial circumstances would move them out of the place they belong. It’s possible they may go into debt or spend down the assets they do have left, jeopardizing their financial future, in order to maintain a lifestyle that keeps them in their financial comfort zone.

Assessment

Ironically, this couple would have a better chance of returning to their financial comfort zone if they were willing to live below it until their financial circumstances improved. Choosing to live at the low end of your financial comfort zone so you can invest for the future is one of the most important ways to build long-term financial independence and lasting financial comfort.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product DetailsProduct Details

Upcoming Webinars and Health Administration Essays around the Net

Join Our Mailing List

By Staff Reporters

Some Topics of Interest for ME-P Readers

###

US capitol

###

Assessment

Enjoy these informative private sector and government publications.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

On Hospital Re-Admissions

Join Our Mailing List

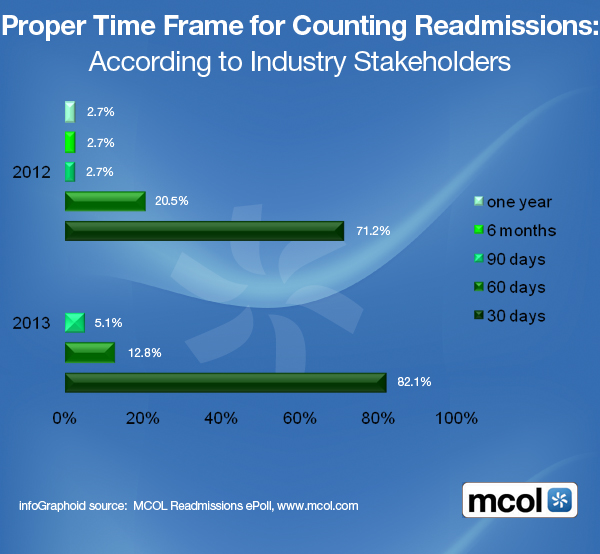
Counting Re-Admissions using an Infographic

By www.MCOL.com

###

ImageProxy

###

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

On Target Date Retirement Funds for Physicians

Join Our Mailing List 

What You Haven’t Considered

By Lon Jefferies MBA CFP® http://www.NewWorthAdvice.com

Lon JefferiesAn increasing number of physician investors are utilizing target-date funds in their investment accounts and employer retirement plans.

In theory, an individual should select a target-date fund that matches their estimated year of retirement, such as the Vanguard Target Retirement 2015, or Fidelity Freedom 2020 fund. The philosophy of these funds is that as one ages, the proportion of stocks in their portfolio should decline, while their exposure to less volatile fixed-income positions increases.

My Concerns

While I agree with the concept that investors should continually make their portfolios less aggressive as they age, there are two concerns I have about utilizing these funds.

First and most obviously, an appropriate asset allocation for an individual physician investor as they enter retirement is dependent on their risk tolerance and is best not left to generalizations. At retirement, an aggressive doctor may be comfortable holding a portfolio that is 70 percent stocks while a more conservative investor may not be able to tolerate the volatility that accompanies a portfolio that has any more than 40 percent exposure to equities.

Of course, assuming these two investors retired around the same time, a target-date fund would place both in a one-size-fits-all asset mix.

Next, and perhaps less obvious but equally important is the fact that an asset allocation is better designed around when the investor will need the money as opposed to when they will retire.

Case Examples:

Consider two hospital employees who are retiring in 2015, and consequently, are invested in the Fidelity Freedom 2015 target-date fund (which is quite conservative – only 45 percent stocks and a 55 percent mix of bonds and cash). One of these employees will be taking an early retirement at age 59 and won’t be allowed to draw a Social Security benefit for at least three years.

As a result, this individual will need to draw a large amount of funds from his retirement account in order to pay for the first several years of retirement. The worst thing that could happen to a retiree is to endure a market crash shortly after leaving the workforce and suffers an excessive loss right as the funds are needed.

In such a case, the physician investor wouldn’t have time to wait for the market to recover and would be forced to sell at a loss. If money will need to be withdrawn sooner rather than later, sound financial planning says it should be invested in a conservative portfolio that is likely to limit loss, potentially similar to the 45 percent stock and 55 percent bond mix that the Fidelity Freedom 2015 fund provides.

###

Financial

###

Another Case Example:

Now consider that the second hospital employee invested in the Fidelity Freedom 2015 fund is age 67, will immediately be receiving a full Social Security benefit when he retires, and has a healthy pension from his employer. With two significant sources of income immediately upon leaving the workforce, this employee may not need to withdraw meaningful assets from his investment portfolio during the early years of his retirement.

Now, with a longer investment time frame before funds will be withdrawn, a more assertive portfolio is likely appropriate for this investor as he can afford to endure a full market cycle of pullbacks and advances while attempting to achieve superior gains.

Assessment

Hopefully this example illustrates the importance of considering other potential income sources and the timing of your expenses during retirement rather than simply treating target-date funds as your entire asset base. While the theory of target-date funds is sound, other factors should be considered before utilizing them as a significant portion of your investment nest egg.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Financial Freedom through Commercial Real Estate Education and Investing

Join Our Mailing List

A Viable Alternate Investment Class for Physicians?

By Dennis Bethel MD  www.nesteggrx.com

dennis-bethelI’ve worked as an Emergency Medicine Physician for over a decade now.

Most of that time, I’ve also been investing in real estate.

Real estate has been good to me and I’ve been asked to share my story with this ME-P

RESIDENTIAL REAL ESTATE

Not long after graduating from residency in 2002, I began investing in real estate.  I watched my father-in-law make some money in residential real estate (1 – 4 units), read some books, and jumped in feet first.  I purchased and rented out single family homes, a triplex, and multiple four-plexes (quads).  What I didn’t realize at the time was that I made two critical errors.

My First Mistake

The first mistake was that I purchased residential real estate when I should have gone bigger and purchased commercial multifamily.  I had limited resources and I thought bigger properties were out of my reach.  At that time, I had not heard of fractional investing.

My Second Mistake

The second error, that is inherent to residential real estate, is that I became a landlord.  At times I managed properties and at other times I employed a property manager and limited myself to managing the manager.  Regardless, I was putting in a significant amount of time at my unintended second career as a landlord without the desired compensation.

Not Scaleable

Since there are no economies of scale with residential real estate the cash flow is small and unpredictable.  I was on the long, hard path to financial freedom.  The rents from my properties would someday replace my income as a physician, however, that wasn’t going to happen until I paid off the mortgages completely.  Until then it was going to be too inconsistent and I would have to ride several market cycles including the very painful down-turns.

THE MOVE TO COMMERCIAL REAL ESTATE

Unfortunately, chronic understaffing in the ER coupled with increased regulation and the rigors of shift-work had begun to catch up to me.  I was beginning to feel the effects of burnout.  I began to question whether I could make it 30 years.  I began to see earned-income as a trap in which you trade your valuable time for heavily-taxed income.

Then some devastating news, my wife tested positive for the BRCA (breast cancer) gene mutation.  That was a game changer.  I could no longer rest on my laurels, slowly burning out waiting for a comfortable retirement.  The future was uncertain, and I needed to ensure our wealth.  Come what may, I was determined that she would get the best health care money could buy.

I knew real estate was an incredible wealth building investment vehicle and my path to financial freedom.  In fact, 90% of the Forbes 400 (wealthiest people in the US) either made or retain their wealth in real estate.  While I was doing far better than my colleagues who invested in the stock market, I knew that I could do better.

My New Mission

I made it my mission to become an expert in real estate.  I read even more books as well as attended numerous conferences and seminars.  I invested heavily in my education, took advanced real estate investing classes, retained mentors, and developed networks.  I also grew my experience, buying and selling more properties.

I learned that although real estate won’t make you rich overnight, it needn’t take 30 years either.  I needed to transition out of residential real estate and go bigger into commercial multifamily.  I ultimately landed on multifamily, because shelter is a basic need.  People will give up their luxuries long before they give up the roof over their head.  The difference is that I now look for properties that are between 80 – 250 units.  These types of properties afford the investor true economies of scale that provide for predictable multisource income.  I invest in these properties fractionally, pooling my money with other like-minded investors.

MULTISOURCE INCOME

Real estate is the only investment I know of in which the investor makes his or her money in four different ways.

  • Cash Flow (monthly, quarterly, or yearly distributions of net profits)
  • Appreciation (increasing value of the property as net operating income increases)
  • Tax Benefits (can result in little to no taxes on income and gains)
  • Principal Pay Down (Increased equity as the loan gets paid down by the residents)

Multisource income is an incredible benefit of multifamily commercial real estate investing.  In fact, in all of my commercial properties, I have been able to obtain double-digit returns year after year.  Making money and compounding those gains is what investing is all about.

###

real estate

###

SAFETY PROFILE

While all investments have risk, the safety profile of multifamily commercial real estate is impressive.  Let’s compare it to business.  We’ve all heard that 9 out of every 10 businesses fail.  These failures are not just limited to small business.  Every year, many big businesses fail as well.  Names like Circuit City, Hostess, Borders, and Mervyns just to name a few.  Many other, well known, national brands teeter on the brink of insolvency.

In contrast, the commercial multifamily properties I invest in meet current Fannie Mae underwriting standards.  Nationally these properties have a paltry 1% – 2% foreclosure rate.  That rate is even lower in the best markets.  In the hands of a quality syndicator, in thriving markets, utilizing proven property management these properties are FAR safer than stocks for capital preservation, equity growth, and current income.

Additional safety measures include the use of non-recourse lending, the ability to insure against loss, and the use of sole purpose entity structures to eliminate any liability risk.

The “Conversation”

Switching from residential real estate to commercial has enabled me to provide for my family and has allowed me to work only part-time in the emergency department.  A few years ago, I walked into the physician lounge and overheard a conversation between two colleagues.  Both around 20 years my senior, were lamenting their inability to retire.  They had each invested heavily in the stock market without any diversification into real estate.  They bemoaned the fact that they had each worked 25 – 30 years in medicine and were nowhere close to retirement.  They wondered how I could afford to work so many fewer shifts than them with two young boys to raise.

An Eye-Opener

This interaction was eye-opening.  I was grateful for the decisions I had made but saddened by the fate of my 60 year old colleagues.  I’ve watched far too many of them push back retirement as the stock market and economic cycles ruined their plans.

Assessment

I knew I could help.  I have recently started an educational website intended to demystify the subject of real estate investing.  My mission is to help physicians and other health care workers find financial freedom through real estate investing and education.

We also provide quality real estate investments for busy professionals looking to diversify a portion of their portfolio out of the stock market and into commercial multifamily real estate without having to become a landlord.  We do this by helping like-minded professionals pool their resources together to buy quality multimillion dollar assets as fractional investors.

I invite you to visit my website at www.nesteggrx.com and explore the content to learn more about real estate and see if it might be right for you.

NOTE: This ME-P is NOT a personal or professional endorsement.

More:

Physician’s Acquiring Real-Estate

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Did the NSA End Obamacare?

Join Our Mailing List

Did ambitious NSA officials unintentionally end Obamacare years ago?

[By D. Kellus Pruitt DDS]

1-darrellpruittIf loss of trust in encryption ends Obamacare, can whistleblower Edward Snowden be blamed for that as well? Yep.

What’s even more ominous, the former National Security Agency contractor’s news that encrypted medical records are no longer secure reached Alaska on a weekend.

“Risky electronic health records: Alaska should make information exchange system safer – Imagine: The National Security Agency slips into your doctor’s office and peeks at your medical records,”

by Alaska ACLU executive director Joshua Decker was posted hours ago on Newsminer.com, out of Fairbanks.

http://www.newsminer.com/opinion/community_perspectives/risky-electronic-health-records-alaska-should-make-information-exchange-system/article_a9947eb0-1863-11e3-8153-001a4bcf6878.html

Decker questions the security of the state’s Health Information Exchange (HIE), and offers common sense but costly steps which arguably lessen the danger of privacy breaches – including giving patients the choice of “opting-in” to permit their encrypted, but increasingly vulnerable identities to be shared online via Obamacare’s exchanges.

My POV 

In my opinion, if informed Americans are given the choice of volunteering to risk identity theft, HIEs won’t be around a year from now, and neither will Obamacare. If informed Americans are not given a choice, the costs are even greater. Americans deserve honesty.

National Obamacare Hangs in the Balance

In a related, slow-burning game-changer, Obamacare hangs in the balance, not just for Alaska, but for the nation.

It was September 5th when the Guardian Weekly posted: “Revealed: how US and UK spy agencies defeat internet privacy and security,” written by James Ball, Julian Borger and Glenn Greenwald, and based on top secret NSA information Snowden stole.

http://www.theguardian.com/world/2013/sep/05/nsa-gchq-encryption-codes-security

Snowden told the Guardian that years ago, the NSA joined with the UK’s spy agency GCHQ (Government Communications Headquarters) to successfully make encryption obsolete – including for medical records.

Naturally, if properly informed Americans fear that secrets they tell their doctors might be breached, incorrect EHRs become less than worthless. They become dangerous.

More on Health Information Exchanges

What’s more, even before the added expense of waiting for Americans to opt-in to the exchanges – instead of discouraging them from opting-out – the very funding for the increasingly-battered Obamacare is based on a rumor of savings.

Starting years ago, health IT lobbyists, including former Speaker of the House Newt Gingrich, told lawmakers to expect annual savings of $77 billion and 100,000 lives – quoting the results of a once popular, EHR-friendly 2005 RAND study which was funded by General Electric and Cerner Corporation.

Obamacare

As you can see, while we were not paying attention, we were had!

The RAND Study

Predictably, both GE and Cerner profited immensely from the development and sales of EHR systems before the RAND study was widely discredited months ago – even by RAND.

According to a NY Times article from January, “Cerner’s revenue has nearly tripled since the report was released, to a projected $3 billion in 2013, from $1 billion in 2005.”

(See: “In Second Look, Few Savings From Digital Health Records by Reed Abelson and Julie Creswell, January 10, 2013).

http://www.nytimes.com/2013/01/11/business/electronic-records-systems-have-not-reduced-health-costs-report-says.html?_r=0

Assessment

Last weekend’s bad news for Obamacare is still under the radar, but I predict within days it will become apparent that the mounting obstacle between President Obama and healthcare reform will be in regaining trust his administration squandered while helping GE and Cerner profits at the expense of soon-to-be pissed off American patients.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Is a Stock Market Correction Imminent?

Join Our Mailing List

Destined for a significant pullback; or not!

By Lon Jefferies MBA CFP® http://www.NewWorthAdvice.com

Lon JefferiesThe market has allowed itself a well-deserved “cool down” period during the month of August. The S&P 500 was down 3.13% while the Dow Jones Industrial Average was down 4.45% for the month.

After Running of the Bulls

After the roaring bull market we’ve enjoyed since April 2009, it is natural for investors to question whether this is a turning point and the market is destined for a significant pullback.

Currently, it is valuable to remind ourselves that even through the woes of August, the S&P 500 is only down 4.5% from its recent all-time high.

Wall Street Writes

Additionally, it is useful to define some terms, as Josh Brown, one of my favorite Wall Street writers, recently did:

Percentage    Drop: Defined    As: Feels    Like:
less than   5% Pause “whatever”
5% to 10% Dip Refreshing
10%+ Correction Nerve-wracking
20%+ Bear Market Panic
50%+ Crash Can’t Get   Out of Bed

The Market Pause

You may have heard the word correction in the financial media lately. With a market pause still under 5%, it’s probably a bit early to start talking about a correction. Still, let’s assume we are headed for an actual correction, or a loss of 10% to 20%.

Expectations

What should we expect? Here are some interesting numbers that Mr. Brown accumulated:

  • Since the end of World War II (1945), there have been 27 corrections of 10% or more. Only 12 of these corrections evolved into bear markets (a loss of 20%+). The average decline during these 27 episodes has been 13.3% and they’ve taken an average of 71 trading days to play out.
  • On average, the market has endured a correction every 20 months. Of course, the corrections aren’t evenly spaced out — 25% of the corrections occurred during the 1970′s, and another 20% occurred during the secular bear market of 2000-2010. However, from 1982 through 2000, there was just four corrections of 10% or more. This is relevant as it illustrates that bull markets can run for a long time without a lot of drama.
  • Since the stock market’s bottom in March of 2009, there have been two corrections. In the spring of 2010 the S&P 500 lost 16% over 69 trading days. In the summer of 2011, the S&P 500 dropped a hair over 20% before snapping back. Technically, this qualified as a bear market, which would mean the current rally is only two years old as opposed to almost five years old if dated from March of 2009.
  • The market pulled back 9.9% during 60 days in the summer of 2012. While not quite a correction, this dip set up one of the greatest rallies of all time.
  • There have been 58 bull market rallies (defined as market advances of 20% or more) in the post-war period, and they have run for an average of 221 trading days and resulted in an average gain of 32%. Comparatively, when measured by both length and magnitude, the current bull market is overdue for a correction and has been for awhile.

###

Stock_Market

###

Financial Action Plan

So what should you do assuming we are heading for a correction?

First, it is critical to remind yourself that if you are following sound financial planning principals, you already have an investment portfolio that matches your risk tolerance and investment time horizon.

Remember that just because the market loses 10% doesn’t mean your portfolio will lose 10%. In fact, if you scaled back the assertiveness of your portfolio as you transitioned into retirement and your portfolio is only 60% stocks, your portfolio would likely only be down approximately 6%.

Second, in the instance of an investor with a portfolio that is 60% equities, recall that you selected such a portfolio because you deemed a 6% loss to be acceptable. In fact, if due diligence was completed when you selected an asset allocation, you were aware that the largest loss a 60% stock, 40% bond portfolio suffered during the last 44 years was -19.35% (2008).

Additionally, you were aware that such a loss could (and likely would) happen again and you determined that was acceptable.

Grinding Teeth

Thus, for medical professionals and other investors who have done their planning, the best thing to do in the event of a market correction is grit your teeth and do very little!

For those doctors who haven’t planned in advance, now would be an ideal time to do your homework and create a portfolio that matches your situation and behavior patterns.

Assessment

Once you’ve done your planning, all you need to do is remember what Josh Brown calls the ABCs of investing: Always Be Cool.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

September is National Preparedness Month

Join Our Mailing List

Fore-Warned is Fore-Armed

[By Staff Reporters]

September is National Preparedness Month — a time for all individuals and communities to better prepare for an emergency.

To get started, visit: www.ready.gov

###

Banner_NPM2013_square_250x250 (2)

###

Assessment

To learn how you can promote emergency preparedness in your community and access tools that will help, check out the 2013 Toolkit!

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:


Product DetailsProduct Details

Got Cash Money in the Bank?

Join Our Mailing List

Is it Really a Long-Term Investment?

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPGot money in the bank? Of course, that’s a good thing.

But, more than a fourth of Americans think the best long-term investment strategy is money in the bank. However, that may be a bad thing!

So, what about medical professionals; and what is a doctor to do?

The Bankrate Survey

Here is the rather discouraging result of a July survey by Bankrate. One of its questions was, “For money you wouldn’t need for more than 10 years, which one of the following do you think would be the best way to invest the money?”

Cash was the top choice at 26%, followed by real estate at 23%. Sixteen percent of the respondents chose precious metals such as gold. Only 14% would put their long-term investment into the stock market, and just 8% thought bonds were the best choice.

Head-on-Desk Syndrome

Doh! That thumping sound you hear is me banging my head on my desk.

I assume those who opted for cash did so because keeping money in the bank seemed to be the safest choice. For long-term investing, however, that safety is an illusion. The best and safest place to put your nest egg for the future is not in the bank, but in a well-diversified portfolio with a variety of asset classes.

Here’s why:

Savings accounts and CDs are safe places to store relatively small amounts of cash that you expect to need within the next few months or years. The funds are protected by insurance. You know exactly where your money is, and you can get your hands on it anytime you want.

Short Term Stability

This short-term safety does not make the bank a good place for money you will need for retirement or other needs ten years or so into the future. It may seem like safe investing because the amount in your account never goes down. You’re always earning interest. Yet, over time, that interest isn’t enough to keep pace with inflation. The purchasing power of your money decreases, which means you’re actually losing money. It just doesn’t feel like a loss because you don’t see the loss in value.

Stock Markets Fluctuate

In contrast, the stock market fluctuates. The media reports constantly that “the DOW is up” or “NASDAQ is down,” as if those day-to-day numbers matter. This fosters a perception that investing in the stock market is risky. Combine that with the scarcity of education about finances and economics, and it’s no wonder that so many people are afraid of the stock market and view investing almost as a form of gambling.

Wise long-term investing in the stock market is anything but gambling. Instead of trying to buy and sell a few stocks as their prices go up and down, wise investors neutralize the impact of market fluctuations by owning a vast assortment of assets.

A Dual Strategy

This is accomplished with a two-part strategy.

1. The first is to invest in mutual funds rather than individual stocks. With just one mutual fund that invests in an index of stocks, you might own thousands of different companies. Your hard-earned fortune isn’t dependent on the fortunes of just a few companies.

2. The second component is asset class diversification. An asset class is a type of investment, such as U. S. and International stocks, U. S. and International bonds, real estate investment trusts, commodities, market neutral funds, Treasury Inflation-Protected Securities, and junk bonds. Ideally, a diversified portfolio should include nine or more asset classes.

###

MD Retirement planning

###

Assessment

By holding small amounts of a great many different companies and asset classes, you spread your risk so broadly that the inevitable fluctuations are small ripples rather than steep gains or losses. As some types of investments decline in value, other types will be gaining value. Over the long term, the entire portfolio grows.

And, in the long term and for most medical professionals, investing this way is usually safer than money in the bank.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
PODIATRISTS: www.PodiatryPrep.com
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Informatics at the Intersection of Healthcare IT

An Informative Inforgraphic

Join Our Mailing List
Did you know that 50,000 HIT professionals will be needed in the next 7 years?
###
Well, that’s according to the University of Illinois at Chicago’s Online Health Informatics Program, which published an infographic asserting that the industry needs new ways to provide improved care, sans errors. And, healthcare informatics is where that potential resides.
###
But, what do healthcare informaticists actually do? What are the sub-disciplines of the practice? And, how do they enhance medical care delivery? … Scroll down to find out.

###

it

###

Related Resources

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

The Percentage of Covered Employees by Type of Health Plan

Join Our Mailing List

From 1988 to 2000

###

Health Plans

###

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

How Medical and Financial Professionals can Teach their Children Fiscal Discipline

Join Our Mailing List

Exercising Pediatric Fiscal Discipline

By Andrew D. Schwartz CPA

Andrew SchwartzI’m a CPA and my wife is a CFP (Certified Financial Planner). Many ME-P readers are the same; or are doctors or nurses; or MBAs, PhD, CFAs; or other learned professionals, etc.

Even so, I think together we’ve done a lousy job teaching our two kids – Jonathan (age 15) and Lizzie (age 14) – much about personal finances. We have also done little to help them learn anything about exercising fiscal discipline.

Over the years, we’ve toyed with monthly allowances and paying our kids for doing their household chores. The problem is that we have never been consistent with doling out the promised $20 per month or with enforcing the rules they need to follow to even be eligible to receive their allowance.

Our Allowance System

So my family’s allowance system has evolved to something like this:

Child: “Dad and/or Mom, I’m getting together with friends. Can I have some money?”

Parent: “Sure thing, Jonathan and/or Lizzie. Will $20 be sufficient?”

Well, as my kids continue to grow up, we have reached the point where this conversation happens pretty regularly. Our kids have no incentive not to ask us for money, since we have a track record of giving them money whenever they ask. And they also don’t have an incentive to try to earn any money on their own, since we have gladly been supporting 100% of their spending.

Change is Coming

That’s all about to change. Financial responsibility for the Schwartz Clan, here we come. As a parent of a teenager, you might be asking, “How will you pull this off Andrew?”

For Christmas/Chanukah last winter, we gave each child a Pass Card issued by American Express.  These cards are only available to kids 13 or older.

Enter AMEX

According to American Express, “Pass is a prepaid reloadable Card parents give to teens. It’s safer than cash, and unlike a debit or credit card, teens can only spend what’s preloaded on the Card.” For my two kids, we loaded each card with $100, and then will reload the card on the tenth of each month with their $25 allowance.

Pass cardholders can spend money on the prepaid card pretty much anywhere that takes credit cards. And while parents do have the right to deny their kids access to cash from ATMs, we decided to set up the cards to allow ATM withdrawals. We can change this setting at any time, however. The first ATM transaction each month is free for each kid, and then there is a charge of $2 per withdrawal.

The Thought Process

In theory, when either kid spends all the money on the card, they are out of money until they next receive the $25 on the tenth of the month. Here is where my wife and I will need to exercise some parental discipline and not just dole out more spending money.

Instead, we need to try to use this opportunity to remind Jonathan or Lizzie that if they want to spend more than $25 per month, they can always babysit, shovel snow or rake leaves for our neighbors, work at my office during tax season, or try to find another job that hires 14 and 15 year-old kids to earn extra money.

Referral

Other Advantages

For parents, the Pass Card has a nifty web interface that allows parents the opportunity to view balance and purchase history online at any time, transfer additional funds into the card, or tweak the amount or frequency of the automatic reloads. Teens will also be able to logon to the Pass website under a separate login to monitor balances and activity.

According to the site, the Pass Card also provides your child some additional benefits similar to the benefits that come with the AMEX card, including:

  • Purchase Protection if an item purchased with the Pass Card breaks within 90 days
  • Roadside Assistance if your child’s car won’t start
  • Global Assist Services to provide your child with emergency services while traveling

Assessment

I hope the Pass Card works out well for my family and helps my wife and I teach my kids a little about personal finances and fiscal discipline.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Afghanistan and Iraq’s Healthcare Costs

Join Our Mailing List

An Informative Infographic

###

war

###

Assessment

Over the next 40 years, Afghanistan and Iraq veterans will need an estimated $750 billion in healthcare, a challenge for the VA to innovate, especially when treating soldiers who grew up with the Internet.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

R.I.P. Muriel “Mickie” Siebert

Join Our Mailing List

On Muriel Siebert

“Mickie” Siebert, founder of the brokerage firm that bears her name, Muriel Siebert & Co. Inc., bought a seat on the New York Stock Exchange in 1967.

She was one of the pioneers in the discount brokerage field, as she transformed Muriel Siebert & Company (now a subsidiary of Siebert Financial) into a discount brokerage in 1975, on the first day that Big Board members were allowed to negotiate commissions; the so-called “May Day” decision.

BORN: Sept. 12, 1932, in Cleveland.

DIED: Aug. 24, 2013, in New York.

EDUCATION: Attended Western Reserve University (now Case Western Reserve University) 1949-1952.

FAMILY: Never married and did not have any children.

Link: http://news.msn.com/obits/muriel-siebert-first-woman-member-of-the-nyse-dies?ocid=ansnews11

##

NYSE

###

Assessment

She was the first woman to become a member of the New York Stock Exchange [NYSE].

Visit: www.SiebertNet.com

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

On Aging and Getting Better with Age

Join Our Mailing List

Consumer Reports on Health

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFP

How old is “old?” I don’t know exactly, but after my recent birthday I can say that it’s much older than 58. My 12-year-old son told me, “Dad, I’ve always thought of people who are over 60 as being really old. I don’t think of you as really old, so guess I will need to redefine what is old.”

Old Enough?

Still, I am old enough to know from personal experience that the body begins to slow down and fall apart as we age. I also know from working with clients that aging can be expensive. One of the biggest threats to a retirement nest egg, besides the possibility of outliving it, is the high cost of medical care for increasing health needs.

All this leaves me wondering if there is anything good about getting older.

Consumer Reports on Health

Well, yes, there is. A recent article in Consumer Reports on Health found there are some things that actually get better with age:

1. You get wiser.

This one seems intuitively obvious to me, but as I once heard a researcher say, “If you can’t measure something, it doesn’t exist.” Research conducted by the Universities of Texas and Michigan found that significantly more older people ranked in the top 20% in wisdom performance and the group with an average age of 65 consistently outperformed younger participants. Maybe there’s some truth to the joke about parents seeming to get smarter as their kids get older.

2. You have fewer difficult emotions.

A Gallup survey found that people in their 70’s and 80’s reported less stress, worry, and anger than younger respondents. I found it curious that stress peaks at age 25 and steadily declines, dropping rapidly from age 60 to 73. I guess that leaves me something to look forward to in a couple of years.

3. You become happier.

This was a surprise, especially given my projection that increasing aches and pains probably increase unhappiness. Again, the devil is in the definition of “happiness”. I suggest that we often equate happiness with well-being, which can be broken into three segments: physical, emotional, and financial. Stanford University found that aging is actually associated with increased emotional well-being. The article didn’t mention physical and financial well-being. Based on my experience, I expect that physical well-being decreases with age and financial well-being is dependent upon a complex host of variables.

4. Your marriage gets better.

The Journal of Social and Personal Relationships found that older couples experience greater satisfaction and positive experiences with each other. The report also says happily married older people have better health, quality of life, and relationships with their children and friends. I think that is another one of those intuitively obvious facts that researchers still feel they must validate.

5. Your relationships get deeper and richer.

While younger people have more friends, the quality of older people’s relationships becomes richer. A study done by Case Western Reserve University found that volunteering was the most consistent predictor of cognitive well-being in people over age 72.

Assessment

Even with all these positives, old age isn’t exactly something to look forward to. Yet it doesn’t mean our golden years will necessarily be overridden with tarnish and rust. Living a healthy lifestyle and planning financially for retirement can certainly help make aging more comfortable. And clearly, aging is better than the alternative of not being around to grow old; especially when we factor in one last advantage of aging.

I haven’t yet experienced this personally, but I hear plenty about it from clients and friends. According to these sources, the best thing about aging is grandchildren.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product DetailsProduct Details

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

IRS Offers New Simplified Home-Office Deduction

Join Our Mailing List

Effective January 1, 2013

By Andrew D. Schwartz CPA

Andrew SchwartzThe IRS has introduced a simplified option for many home-based businesses and some home-based workers to use to figure their deductions for the business use of their home, effective January 1, 2013.

The new optional deduction, capped at $1,500 per year based on $5 a square foot for up to 300 square feet, will reduce the paperwork and recordkeeping burden on small businesses by an estimated 1.6 million hours annually.

An Easy Path

The new option provides eligible taxpayers an easier path to claiming the home office deduction. Currently, they are generally required to fill out a 43-line Form 8829, often with complex calculations of allocated expenses, depreciation and carryovers of unused deductions. Taxpayers claiming the optional deduction will complete a significantly simplified form.

No Allocation

Though homeowners using the new option cannot depreciate the portion of their home used in a trade or business, they can claim allowable mortgage interest, real estate taxes and casualty losses on the home as itemized deductions on Schedule A of their tax return.  These deductions need not be allocated between personal and business use, as is required under the regular method.

Business expenses unrelated to the home, such as advertising, supplies and wages paid to employees are still fully deductible.

Restrictions

Current restrictions on the home office deduction, such as the requirement that a home office must be used regularly and exclusively for business and the limit tied to the income derived from the particular business, still apply under the new option.

Drs. Home

Assessment

The new simplified option is available starting with the 2013 return which most taxpayers file early in 2014.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product DetailsProduct Details

Ground Breaking Book Explains Why Accountable Care Organizations May Be the Answer the Health Care Industry Has Been Seeking!

Join Our Mailing List

Book Reviews, with Testimonial, by ME-P Founding Publisher Dr. David Edward Marcinko MBA CMP®

PRESS RELEASE!

August 23, 2013CRC Press / Productivity Press is pleased to announce the publication of  Accountable Care Organizations: Value Metrics and Capital Formation authored by nationally recognized healthcare expert, Robert James Cimasi. This dynamic book explores the historical background and evolution of the highly anticipated ACO model which is rapidly expanding since its adoption as part of the Affordable Care Act, commonly referred to as Obama Care. The book describes the basis for the development of value metrics and capital formation analyses that are foundational to assessing capacity for change in healthcare organizations considering the development of an ACO, as well as, the current efficacy of the model.

Book Reviews

“Bob Cimasi has done it again. As a thought leader in contemporary healthcare matters, his new book, Accountable Care Organizations: Value Metrics and Capital Formation, establishes and explains, in plain terms, the operational and financial DNA and genomic construct and understanding for any organization considering the development and operations of an ACO…a must read and resource for any healthcare industry executive.”

-Roger W. Logan, MS, CPA/ABV, ASA, Senior Vice President of Phoenix Children’s Hospital

“Accountable Care Organizations is the first comprehensive text on capital formation and value metrics for this new healthcare business model… I can think of no one more qualified to write it than Bob Cimasi at Health Capital Consultants … it is destined to become a classic work … read, review, refer, and profit by this valuable resource.”

-Dr. David Edward Marcinko MBA CMP® of the Institute of Medical Business Advisors, Inc Atlanta, GA

“As both a healthcare management educator and as a consultant who has worked on health and professional services transactional advisory work for many years, I applaud the ambitious undertaking of Bob Cimasi’s latest book, Accountable Care Organizations: Value Metrics and Capital Formation. Cimasi’s description of the complex history and evolution of the US health system provides a useful framework for students and professionals who may lack a detailed background in the field. This should help them better understand both how we have arrived at the ACO approach, and how it might work. This addressing capital and valuation information is also uncommon in the literature on ACOs. It should provide a valuable contribution to the field, especially given that a some surveys of healthcare leaders have pointed to access to capital and to a lesser but still important degree, agreement on valuation, as concerns as they consider acquisitions, mergers, and other affiliations towards forming/joining ACOs or similar organizations to help deal with the changing reimbursement and competitive environment.”

-R. Brooke Hollis, MBA/HHSA, Executive Director, Sloan Program in Health Administration, Cornell University and Managing Member, Hollis Associates Acquisition Advisors, LLC

The book examines the Four Pillars of Value in the Healthcare Industry: regulatory, reimbursement, competition and technology in addressing the value metrics of ACOs, including requirements for capital formation, financial feasibility, and economic returns. It focuses the discussion of non-monetary value on a review of aspects of population health within the context of such objectives as improved quality outcomes and access to care. It also examines the positive externalities of the ACO model, including results for third parties outside the basic construct of the ACO contracts shared savings payments. The potential role and opportunities for consultants in assisting their provider clients in the consideration, development, implementation, and operation of an ACO are also discussed.

###

Accountable Care Organizations

###

About the Author:

Robert James Cimasi, MHA, ASA, FRICS, MCBA, AVA, CM&AA, CMP® is CEO of Health Capital Consultants (HCC), a nationally recognized healthcare financial and economic consulting firm headquartered in St. Louis, Missouri, since 1993. Cimasi has more than 30 years of experience in serving clients in over 45 states, with a professional focus on the financial and economic aspects of healthcare service sector entities including feasibility analysis and forecasting; valuation consulting and capital formation services; healthcare industry transactions including joint ventures, mergers, acquisitions, and divestitures; certificate-of-need and other regulatory and policy planning consulting; and, litigation support and expert testimony.

Mr. Cimasi has served for many years as faculty in both an academic and professional basis for continuing education courses, and he has provided testimony before federal and state legislative committees and has served as an expert witness in numerous court cases. He is a nationally known speaker on healthcare industry topics, the author of several books, including A Guide to Consulting Services for Emerging Healthcare Organizations (John Wiley & Sons, 1999), The U.S. Healthcare Certificate of Need Sourcebook (Beard Books, 2005), The Adviser’s Guide to Healthcare (AICPA, 2010), and Healthcare Valuation: The Financial Appraisal of Enterprises, Assets, and Services (John Wiley & Sons, 2013), as well as numerous chapters, published articles, research papers and case studies, and is often quoted by healthcare industry press.


UPDATE:
Top Five Videos Trending in The Last Month On HealthShareTV
  1. Accountable Care Directory 2014
  2. Achieving Quality in Accountable Care Organizations
  3. High-Performing Care Coordination in a Patient/Family-Centered Medical Home
  4. ‘Aetna’s Medicare Advantage Collaborative Initiatives’
  5. Aligning High Performance in Medication Safety to Improve Patient Outcomes and Reduce Readmissions

Source: HealthShareTV

###

Product DetailsProduct Details
 

How a Doctor’s Job Seach May Lower Taxes

Join Our Mailing List 

Same line-of-work Tax Tips

By Andrew D. Schwartz CPA

Andrew SchwartzSummer is often a time when doctors and other people make major life decisions. Common events include buying a home, getting married or changing jobs; especially for hospitalist physicians.

If you’re looking for a new job in your same line of work, you may be able to claim a tax deduction for some of your job hunting expenses.

The Tax Tips

Here are seven things the IRS wants you to know about deducting these costs:

1. Your expenses must be for a job search in your current occupation. You may not deduct expenses related to a search for a job in a new occupation. If your employer or another party reimburses you for an expense, you may not deduct it.

2. You can deduct employment and job placement agency fees you pay while looking for a job.

3. You can deduct the cost of preparing and mailing copies of your résumé to prospective employers.

4. If you travel to look for a new job, you may be able to deduct your travel expenses. However, you can only deduct them if the trip is primarily to look for a new job.

5. You can’t deduct job search expenses if there was a substantial break between the end of your last job and the time you began looking for a new one.

6. You can’t deduct job search expenses if you’re looking for a job for the first time.

7. You usually will claim job search expenses as a miscellaneous itemized deduction. You can deduct only the amount of your total miscellaneous deductions that exceed two percent of your adjusted gross income.

###

jobs

###

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product DetailsProduct Details

Passive Investing with a “Steroid Twist”

Join Our Mailing List 

A Core and Satellite Philosophy

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFP“Keep your hands away from your investments and back away from the market reports.”

That pretty much sums up passive investing, the approach I have practiced for years. I’ve preached it for years, too, and did so in a recent column. The wisest way to build wealth is by investing in a variety of asset classes, setting target allocations in each asset class, and then taking your hands off except to periodically rebalance to the original target allocations.

For most of us, including doctors, the best way to invest in an asset class is to give our funds to a mutual fund manager who will purchase the appropriate investments. Mutual fund managers have a choice of actively or passively managing the money you give them to invest.

Passivity 

Passive managers try to match market indexes, which are groups of companies representing a cross-section of a certain type of investment. The most popular index in the world is probably the S&P 500 index, which consists of the largest 500 companies in the United States. Another popular index is the Dow Jones Industrial Index which is made up of 30 companies. When we consider the US has almost 10,000 companies, we can quickly see that many indexes represent just a segment of the entire market.

Research indicates it is very hard to beat an index, especially with stocks, bonds, real estate investment trusts, and commodities. I prefer to keep about 80% of my investment portfolio in a broad variety of passively managed investments in these asset classes.

Timing or Strategy?

Where do I put the other 20%? In mutual funds with active managers who try to earn returns similar to stocks and bonds and that are not correlated to either.

This may seem to make me a hypocrite. I’ve been saying for years not to be a market timer, and now here I am suggesting you do just the opposite with a portion of your portfolio. Not hypocrisy at all. What I’ve preached for many years is that neither you nor I have any business timing investments. That doesn’t mean no one should ever do it.

So, is it timing or strategy?

Core and Satellite Philosophy

It can be wise to put a small portion [satellite] of our portfolios [core] into various investment strategies with active managers. The key is to find managers who have a disciplined approach that eliminates emotion and who have long-term track records of success. These strategies include managers who attempt to time markets by shorting stocks they think will decline in value and buying stocks they think will rise.

It also includes one investment strategy, managed futures, that I call “timing on steroids.”

###

Bull markets

###

Rationale

My reason for including some actively managed funds is to have part of my investment portfolio that is not correlated to stocks. I want these investments to have a positive return over a long period, but also to move in opposition to other major asset classes, especially stocks. So when stocks are up, I am not fazed if my managed futures are down. And, when stocks are down, I am thankful when my managed futures are up. If both asset classes earn 6 to 9% over a long period of time, I’m happy.

So, call it … passive investing with a steroid twist.

Assessment

So I stand by my commitment to passive investing. It’s based on research suggesting that timing the markets is a loser’s game.

Yet part of passive investing is having a fully diversified portfolio. This includes having a small portion—20% or less—in mutual funds with disciplined, successful active managers. My job is to research and find those managers. Then it’s okay to let them time their hearts out. I just make sure I don’t try to time the timers.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

***

  Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

On Mentally Ill Inmates

Join Our Mailing List
###
By Christie Thompson
[This story was co-produced with WNYC]

In New York, inmates diagnosed with “serious” disorders have been protected from solitary confinement. But, since that policy began, the number of inmates diagnosed with such disorders has dropped.

###

Hospital

###

Link: New York Promised Help for Mentally Ill Inmates – But Still Sticks Many in Solitary

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Commercial Health Plans’ Medical Loss Ratio [2nd Quarter 2013]

Join Our Mailing List

By http://www.MCOL.com

The 85% Rule

###

ImageProxy

###

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors


Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

The Danger of Used Health Information Technology

Join Our Mailing List

Remember to destroy that hard drive!

By D. Kellus Pruitt DDS

1-darrellpruittNEWS FLASH!

Affinity Health Plan to Pay $1.2 Million+ for HIPAA Violations -The HHS Office for Civil Rights on August 14 sent the industry a message on the importance of erasing protected health information on hardware being sold, recycled or returned,” by Joseph Goedert, HealthDataManagement.

http://www.healthdatamanagement.com/news/breach-notification-hipaa-privacy-security-affinity-46483-1.html

Talk about bad luck

A photocopier once leased by Affinity Health was purchased by CBS Evening News – which discovered that the copier’s hard drive contains 344,579 individuals’ unencrypted Protected Health Information.

The Response

In response to the federal investigation triggered by the CBS discovery, the Office of Civil Rights announced: “OCR’s investigation indicated that Affinity impermissibly disclosed the protected health information of these affected individuals when it returned multiple photocopiers to leasing agents without erasing the data contained on the copier hard drives.

Moreover ….

In addition, the investigation revealed that Affinity failed to incorporate the electronic protected information stored on photocopier hard drives in its analysis of risks and vulnerabilities as required by the Security Rule, and failed to implement policies and procedures when returning the photocopiers to its leasing agents.”

Assessment

Before disposing of used technology, remember to destroy the hard drive.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

On Overspending and Overeating?

Join Our Mailing List 

Is there a Causal Relationship?

Rick Kahler CFPBy Rick Kahler CFP® http://www.KahlerFinancial.com

Over the years, I’ve noticed a commonality among people with money problems. Many of them are also overweight. Is there a relationship between overspending and overeating?

Behavioral science

Until now, I couldn’t be sure my experience was anything more than circumstantial. But I recently read about a 2009 study done by Dr. Eva Munster at the University of Mainz in Germany. It found that people who were in deep consumer debt were 2.5 times more likely to be overweight than those who were debt free. This confirms what I’ve observed over the past 15 years.

It isn’t possible to pinpoint one simple reason for this link. Among the causes I’ve seen suggested are overeating because of the stress of being in debt, difficulty buying healthful food with limited income, or an inability to delay gratification in both spending and eating.

Based on my work with people in financial trouble, however, I suspect a deeper root cause. Just as chronic money problems aren’t about the money, chronic weight problems probably aren’t about the food.

Evidence?

For supporting evidence, I went to an expert: my daughter. London recently took a graduate level course in previewing medicine. I asked her what the medical link between overspending and overeating might be. She explained that sugar is addictive and lights up the same part of the brain that narcotics do. It produces a euphoric response within the brain that calls for more of the substance when the euphoria subsides.

She wondered whether people addicted to sugar might overspend on junk food to feed their addiction. They might also spend money they really don’t have on diets, fitness centers, and the higher medical costs associated with being overweight.

I pointed out that I spend a lot on healthy food that costs more than junk food. I also spend money on a fitness center and medical costs to pay for the damage I do to my body compulsively working out. “Well, I guess my argument doesn’t hold much weight,” she quipped.

She pondered for a moment. “Oh, I think I got it. I’ll bet for some people spending money lights up the same part of the brain as sugar and narcotics?”

###

Obesity in the USA

###

Bingo!

That is why the key to changing any addictive behavior—eating, drinking, using drugs, or overspending—is not simply about eliminating the substance or the activity. Something else just pops up to take its place. That’s why many people who successfully stop drinking gain weight or get into serious money problems. The brain just substitutes one dopamine producer for another.

The ultimate answer is a sort of “rewiring” of the brain to create new neuropathways that do not require the harmful substance or activity to produce the same euphoric event. The latest research on the brain tells us this rewiring is completely doable.

I’ve seen that permanently changing the most entrenched damaging money behaviors takes more than knowledge about money or budgeting. Experts on obesity tell us the solution to permanently losing weight rarely lies with learning more about nutrition or finding the right diet. Making deep life changes such as these requires looking into the past. This recovery process takes time, effort, and money. It’s a path that many people are just not willing to follow.

Assessment

But there may be some good news. If the underlying causes for overeating and overspending are the same, then doing the work to recover from one is likely to help someone recover from the other, as well. It’s a sort of “two for the price of one” sale. In terms of long-term financial, physical, and emotional well-being, it seems like a bargain.

More: Are Doctors Spenders or Savers?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

How to Reach Your Career Goals Faster

Join Our Mailing List

A Three Step Program

By Marie Abrahms

We all have the ability to reach our career goals in everyday life.

For many people, this involves obtaining a big paycheck. While for others like FAs and allied healthcare professionals, doing what you love is important. Regardless, most of us might like a little extra aid in order to progress down our career paths.

So, if you wish to reach your goals, below are three things that that can be done in order to augment your career path.

1. Further Your Education

In order to look more inviting to prospective employers you should do things to improve your CV. One strategy is simply by continuing college. An MBA, by way of example, can make it likelier that you’ll be able to uncover a higher paying job.

Moreover, this is easier if you have use of a http://www.amerasiaconsulting.com MBA admissions consultant that will steer you from the right direction and still provide the guidance you need.

2. Promote Your Self on Networking Sites

If you wish to advance inside your career, you must create as many opportunities as you can. There are many work-at-home opportunities available online, in case you are prepared to spend some more time developing them. You’ll find popular networking sites such as LinkedIn and CareerBuilder to promote your resume.

Although they offer no guarantees, they certainly improve your chances.

##

Amerasia-3-1

##

3. Study the Success of Others

When you have chosen the career path you want to capture, you could take advice from others who have already managed to rise in their particular field. You’ll find books, classes and even mentoring programs where you stand to study the secrets of the pros.

###

Amerasia-3-2

###

Assessment

Should you be prepared to take a positive step towards reaching your work goals, visit http://www.amerasiaconsulting.com where you will discover the assistance you’ll need to achieve the MBA degree that may help you meet your employment objectives.

Good luck!

###

Professional Wake Up Call

ADVERTISEMENT

A Survey on Applications in Mobile Healthcare

Join Our Mailing List
University of Delaware Research

By Thomas Martin
Doctoral Candidate
School of Public Policy and Administration
University of Delaware
412 992 1285
trm@udel.edu

Dear Dr. Marcinko,

The University of Delaware is conducting a study to assess provider attitudes towards applications “Apps” in healthcare settings. Mobile devices hold great promise for reshaping the “time and place” where an individual receives care.

Key Topics

The research tool evaluates a number of key topics emerging in the healthcare space:

  • Opinions on the integration of apps into the Meaningful Use program
  • Characteristics important to users when downloading an app
  • Assessing desirable pricing structures

I’d like to invite you and the ME=P readers to provide us with feedback on how you leverage Apps in the healthcare setting. The research instrument should take no more than 10 minutes to complete and all responses will remain confidential. The results may be published in a scholarly journal or industry research publication.

ME-P Respondents Should Be:

• U.S. Providers, Physicians, or Nurses
• IT Staff involved in Health IT and mobile decisions

smart phone mobile ME-P

Assessment

If you have any questions, please do not hesitate to contact (PI) at trm@Udel.edu, tmartin@himss.org or follow this link to the Survey:

Take the Survey

Or copy and paste the URL below into your internet browser:
https://delaware.qualtrics.com/WRQualtricsSurveyEngine/?Q_SS=6GwUOhdbw9Z193f_1Te8TH0W0ZEYMGF&_=1

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.
Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko
Practice Management: http://www.springerpub.com/product/9780826105752
Physician Financial Planning: http://www.jbpub.com/catalog/0763745790
Medical Risk Management: http://www.jbpub.com/catalog/9780763733421
Hospitals: http://www.crcpress.com/product/isbn/9781439879900
Physician Advisors: http://www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Is Passive Investing Right for You?

Join Our Mailing List

On the “Buy low and Sell high” Strategy 

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFP“Buy low and sell high.” That was my simple approach when I was a smart young investment advisor. I poured over a company’s balance sheet, earnings statements, and forecasted returns. Then I bought those companies that were bargains and waited for my gains to roll in. More times than not, they did—eventually.

The problem came with the “not” and “eventually.” A majority of my picks did go up in value, but the minority that were “nots” still lost enough to have a negative impact on my bottom line. Even more frustrating, some of my “nots” turned into gains “eventually” after I sold them.

My investment returns were similar to findings from Dalbar, Inc., a financial services research firm. Dalbar’s studies have shown that average active investors barely beat inflation over the long term. They significantly underperform investors who put their money in an index fund of stocks and leave it alone.

So much for my early investment brilliance! Over the past 40 years, I’ve learned that with every passing year I know less than I thought I did the year before. I’ve proven to myself I have no idea where any market is going tomorrow, next month, next year, or in the next 10 years.

This awareness has led me to become increasingly passive in my investments. In passive investing, rather than trying to time the buying and selling of winners and losers, you instead buy a representative sample of the entire market. This is possible in any market: bonds, stocks, real estate investment trusts, or commodities. You simply buy mutual funds and exchange-traded funds (ETF’s) called index funds.

Benefits

The two biggest benefits of passive investing are cost and diversification.

Costs

Index funds have incredibly low costs, with annual fees as low as 0.1%. Contrast that with the average equity fund that costs 1.5%, fifteen times more. According to research, 97% of active mutual fund managers don’t beat the index over 20 years. Even the 3% who do must beat the index by more than the 1.5% fee they charge, in order for their investors to come out ahead.

Diversification

The smaller number of stocks owned – the more my fortunes are tied to those few companies. It’s the old adage, “don’t put all your eggs in one basket.” By owning index funds, I own hundreds or thousands of securities. While I will never hit a home run, I also will never strike out. My returns will be “average.” Investing may be one of the few professions where being average puts you in the 97th percentile of all investment managers.

The NaySayers

Not all of my peers agree with this philosophy. Many very smart investment advisors jumped off the passive investing bandwagon after 2008 and returned to tactical asset allocation, which is another name for timing the markets.

###

cropped-the-medical-executive-post3.jpg

###

Harold’ Strategy

A noted investment advisor, Harold Evensky MBA CFP® of Evensky & Katz, addressed this issue at a conference last year. After the 2008 crisis, his firm hired researchers to evaluate whether they could find any tactical strategies that would have avoided the crisis. They found some that, in hindsight, would have worked. Yet he didn’t feel those strategies could be comfortably applied looking forward. Instead, the firm decided to add a 20% allocation to non-correlated alternative investments, something I’ve done since the late 90’s. In other words, they increased their clients’ diversification.

Assessment

The bottom line is that passive investing actually gives you more control. It allows you to focus on reducing costs and taxes, the aspects of investing you can control. It frees you from trying to beat the market and worrying over what you can’t control.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

On Medicare Part D Savings?

Join Our Mailing List

An infographic

By www.MCOL.com

###

MC-D

###

More

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

About the ICD-10 Hub

Join Our Mailing List
Free Transition Information and News

[By Staff Reporters]

ICD-10 Hub is a leading source of information about ICD-10 news and events.

Sponsored by the AAPC and Navicure, this website is dedicated to being an essential resource to help practices and HIT vendors understand how this transition will impact the entire industry and how every organization can properly prepare.

loop11

Assessment

So, give em’ a click, and tell us what you think?

http://icd10hub.com/

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.
Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:
Health Dictionary Series: http://www.springerpub.com/Search/marcinko
Practice Management: http://www.springerpub.com/product/9780826105752
Physician Financial Planning: http://www.jbpub.com/catalog/0763745790
Medical Risk Management: http://www.jbpub.com/catalog/9780763733421
Hospitals: http://www.crcpress.com/product/isbn/9781439879900
Physician Advisors: http://www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Doctors as Private Financiers?

Join Our Mailing List

Doctors Acting as Lenders, White-Knights and Venture Capitalists

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFP

Every now and then I get a call from a doctor client wanting my opinion about starting a business with a friend, investing money in a business owned by a family member, or co-signing a loan to help a family member buy a business. Being in business with family is something I know a little bit about, having been in partnership with my father and brother for 40 years. Going into business with family members or close friends can carry a high degree of risk, both financially and emotionally.

In part this is because it is uncomfortable or difficult to ask the necessary dollars-and-cents questions. We don’t want to seem uncaring, unsupportive, or untrusting. We are concerned about damaging the relationship. Yet the relationship is far more likely to suffer if we don’t ask those questions and the venture fails.

My Rules

The following are some things to consider before you invest or go into business with someone close to you:

1. Don’t even consider putting money into a business without seeing a detailed business plan. Ask the same questions about risks, costs, and potential profits that you would ask if this person were not a family member.

2. Insist that the person at least talk to other possible investors who aren’t emotionally involved. This will give both of you some feedback from neutral third parties about the validity of the opportunity. A banker or a potential investor who isn’t a family member will ask questions you may not even think of asking.

3. Do your own research and seek out some independent advice. A financial advisor or someone with a lot of business experience can be a valuable source of questions, information, and alternatives.

4. Ask yourself whether you want to be involved in this business. Does it support your own goals? Do you know anything about this field or have any interest in it? Sometimes people invest on behalf of family members because they feel they “should.” Yet, had those same proposals come from acquaintances or business colleagues, they would almost certainly have said no without a second thought.

5. Try to think of other ways you might be supportive without putting money into the venture. Maybe you can think of lower-risk alternatives or other possible sources of funding. Remember, too, that if your wish is to support and encourage family members, helping them jump into an unacceptably risky investment isn’t exactly doing them any favors.

6. Pay close attention to any difficult feeling you are experiencing when considering investing in this enterprise. Explore any feelings like fear, anxiety, or sadness to determine if there is further wisdom to be gleaned. Perhaps you may be unconsciously ignoring some crucial warning signs.

7. Communicate clearly. Emphasize from the beginning that protecting the relationship is your most important consideration. If you decide not to get involved, be direct about it. Saying no right away is more respectful than is stringing the person along because you don’t want to hurt someone’s feelings. Yes, choosing not to invest in a family member’s project may cause some tension in the relationship. That’s minor compared to the damage the relationship could incur if you invest and the business fails.

###

Achievement

Assessment

Sometimes, the best way for a successful doctor to support a family member’s financial well-being is to turn down an investment request. If outside parties are not willing to commit funds to a project, maybe there’s a message there that both of you need to hear. If you wouldn’t make an investment on its own merits, you almost certainly shouldn’t make it just because it involves a friend or family member.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Will Healthcare Reform Impact a Spine Surgeon’s Retirement Plan?

Certified Medical Planner

Q&A With Dr. Brian Knabe of Savant Capital Management

Brian J. Knabe MDBy Ann Miller RN MHA

Brian Knabe MD CFP® CMP® is a former medical physician turned financial advisor at Savant Capital Management, a fee-only wealth management firm.

Here, he discusses the smartest moves for spine surgeons at various stages in their careers to ensure an enjoyable retirement.

###

retirement

LINK: Will Healthcare Reform Impact a Spine Surgeon’s Retirement Plan? Q&A With Dr. Brian Knabe of Savant Capital Management

More

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Product DetailsProduct Details

A New Physician Compensation Report

Join Our Mailing List
A Physician Compensation Infographic and Review

Doctors saw a small salary increases in 2012 but they were smaller than those in 2011, according to a physician compensation survey released this week by global consulting firm, the Hay Group.

For example, in 2011, physician salaries increased by 2.7 percent but 2012 saw they increased only by 2.5 percent.

####
Pay
More

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Medical Director Needed for NovaSys Health

Join Our Mailing List

Physician Career Opportunity

By Paul Esselman

[Executive Vice President, and Managing Principal]

Cejka Executive Search

Dear Dr. Marcinko,

Centene Corporation is seeking a Medical Director for NovaSys Health, a full-service managed care company and health plan administrator based in Little Rock. This newly created position will be responsible for assisting in the development of a medical management infrastructure for the health plan as NovaSys expands their member base through the participation in the Arkansas Healthcare Exchange.

A Fortune 500 company, Centene is a national leader in low-cost solutions for high quality healthcare services for uninsured and underinsured patients. Centene’s subsidiary health plans bring better health outcomes to their 1.5 million members. Centene’s core philosophy is that quality healthcare is best delivered locally. This local approach enables them to provide accessible, high quality and culturally sensitive healthcare services to their members in their own communities.

The Medical Director will perform utilization review, quality assurance and medical review of services; oversee the activities of physician advisors; assist in provider network development and expansion; and participate in strategic program developments for improving quality of care while lowering costs. The Medical Director will also work closely with the Plan President and Vice President, Medical Management (RN) in establishing and carrying out the strategic vision of the organization working closely with external constituents as appropriate.

Successful candidates will be physician leaders with knowledge of quality improvement practices and familiarity with medical information systems, medical claims payment processing and coding. Knowledge of managed care, Medicaid and case management programs are preferred. Board certification in a recognized medical specialty, preferably in internal medicine, family practice, pediatrics or emergency medicine, and an active medical license are required.

###

inheritance

Assessment

Qualified candidates should submit their resumes for consideration to me:

Thank you. 

Paul Esselman Executive Vice President, Managing Principal Cejka Executive Search 4 CityPlace Dr., Ste. 300 St. Louis, MO 63141 314.236.4588 Office pesselman@cejkasearch.com http://www.cejkaexecutivesearch.com

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details