
Education versus Retirement

Join Our Mailing List

Not An “all-OR-nothing” Proposition

Rick Kahler CFPBy Rick Kahler MS CFP® http://www.KahlerFinancial.com

I recently had the opportunity to share an evening out with some friends, new parents with six-month-old twins.

The conversation centered on birthing, breastfeeding, and burping!

Thinking Education

One topic we didn’t discuss was baccalaureate degrees. Most people might think it’s premature to consider college education while your kids aren’t even crawling.

Actually, that’s the perfect time to think about it, especially if you intend to fund all or a significant part of your children’s education. Don’t wait till kids are 17, 14, or even 11 to settle on a philosophy of “who pays what” toward their education. If you do, you risk becoming a financial burden to your children in retirement.

Most parents perceive paying their children’s college expenses as a loving act. They believe it will help give their children a good start on a career and chance to get ahead. The facts suggest it actually may accomplish just the opposite. The reason? Most American parents who fund their children’s college education underfund their own retirement.

Parents who fail to fully fund their own retirement may dearly cost their children later. Such parents often rely on their children to take care of them in their final years. Research indicates that looking after parents in their old age comes at a great financial price.

The Research

According to Alan Blaustein, the founder of CarePlanners, elderly parents who underfunded their retirement cost their children an average of 18 hours a week, $30,000 a year in hard costs, and a total of $300,000 in forfeited wages and benefits. Most studies put the total cost from $250,000 to $750,000, depending on the length of time the parents needed care.

Considering that the tuition at many four-year colleges averages around $100,000, most children would be much further ahead to pay for their own education while parents fully funded their own retirement.

Not only does paying for kids’ college education potentially hurt them financially, it also can hurt them academically. I reported last year on research  that found children whose parents pay the tab for college have lower GPA’s than those who earn scholarships, borrow, or work their way through college.
humpty-dumpty

[Retirement-OR- Educational Funding?]

The Psychology

Clearly, the logical and loving approach for parents is to focus on retirement first, even if that means letting children pay for their own education. Yet the average American parent recoils from the thought, finding it unloving, selfish, or irresponsible even in the face of clear evidence that the opposite is true.

Such “illogical” emotional responses to factual data actually make perfect sense. The Nobel Prize-winning psychologist, Daniel Kahneman, discovered that we make 90% of all financial decisions emotionally, not logically. Moreover, the more complex the financial decision, the higher the probability is that we rely on our emotions to make it. Sadly, evolution wired our brains to make poor financial decisions.

So, Start Early

Do yourself and your children a favor and assess your ability to save for retirement when your children are very young. Fully fund your retirement first with maximum contributions to 401(k) plans or IRAs. If there is anything left over, start 529 college savings plans when kids are babies. This will allow the tax-free earnings to grow and multiply by the time they set off to college.

Assessment

Remember, too, that college funding isn’t an “all or nothing” proposition. Many parents choose to pay some college expenses and help the kids find ways to fund the rest through scholarships, jobs, and loans.

More:

Conclusion

In any case, early planning is the key to supporting both your kids’ futures and your retirement. Making logical college funding decisions, rather than emotional ones, creates a win/win for everyone.

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Fiduciary Financial Advisor versus Non-Fiduciary FAs

Join Our Mailing List 

Understanding the Difference

Dr. DEMBy Dr. David Edward Marcinko MBA CMP™

GOAL: To understand the difference between fiduciaries and non-fiduciaries, examine the SEC conduct rules.

Stock-Brokers (non-fiduciaries) are subject to FINRA Conduct Rule 2310(a) which reads:

In recommending to a customer the purchase, sale or exchange of any security, a member shall have reasonable grounds for believing that the recommendation is suitable for such customer upon the basis of the facts, if any, disclosed by such customer as to his security holdings and as to his financial situation and needs.

A fiduciary follows a higher standard of conduct: 

A fiduciary duty is an obligation to act in the best interest of another party. A fiduciary obligation exists whenever the relationship with the client involves a special trust, confidence and reliance on the fiduciary to exercise his discretion or expertise in acting for a client. A person acting in a fiduciary capacity is held to a high standard of honesty and full disclosure in regard to the client and must not obtain a personal benefit at the expense of the client.

Five primary responsibilities as a fiduciary to clients are:

  • To always put clients’ interest first
  • To act with utmost good faith
  • To provide full and fair disclosure of all material facts
  • Not to mislead clients, and
  • To expose all conflicts of interest and all compensation to clients.

More:

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Common Daily Clinician Health Technologies

Join Our Mailing List

Most Commonly Provided to Support Daily Activities

www.MCOL.com

Health Technology

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

American’s Personal Experience with the PP-ACA

Join Our Mailing List

The Law of the Land

By www.MCOL.com

ACA

More:

Assessment

So, tell us your personal experi9ence with the ACA

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

On Recent Stock Market Losses

Join Our Mailing List 

Should Physician Investors Be Concerned?

Lon JefferiesBy Lon Jefferies MBA CFP®

Many doctors and some investors viewed the end of January and early February as a pretty scary time. Over a period of just 12 trading days (1/15-2/3), the S&P 500 lost -5.76%. This spurred conversations online and in the media about the end of a long bull market run and even the possibility of a bubble. However, since the end of that tough stretch, the market has responded strongly and is again reaching new all time highs.

What’s Up!

So what happened during that short time span to cause such a response? Was it a concern about the health of emerging markets that caused such a scare, or perhaps the threat of rising interest rates? Did the uncertainty of having a new Fed chairman cause a pullback in the market, or maybe the concern of a terrorist attack in Sochi during the Olympics? These are all clearly issues that obtained a good amount of short-term attention, but I’d contend that none of them were the root cause of the market decline.

Historical Review

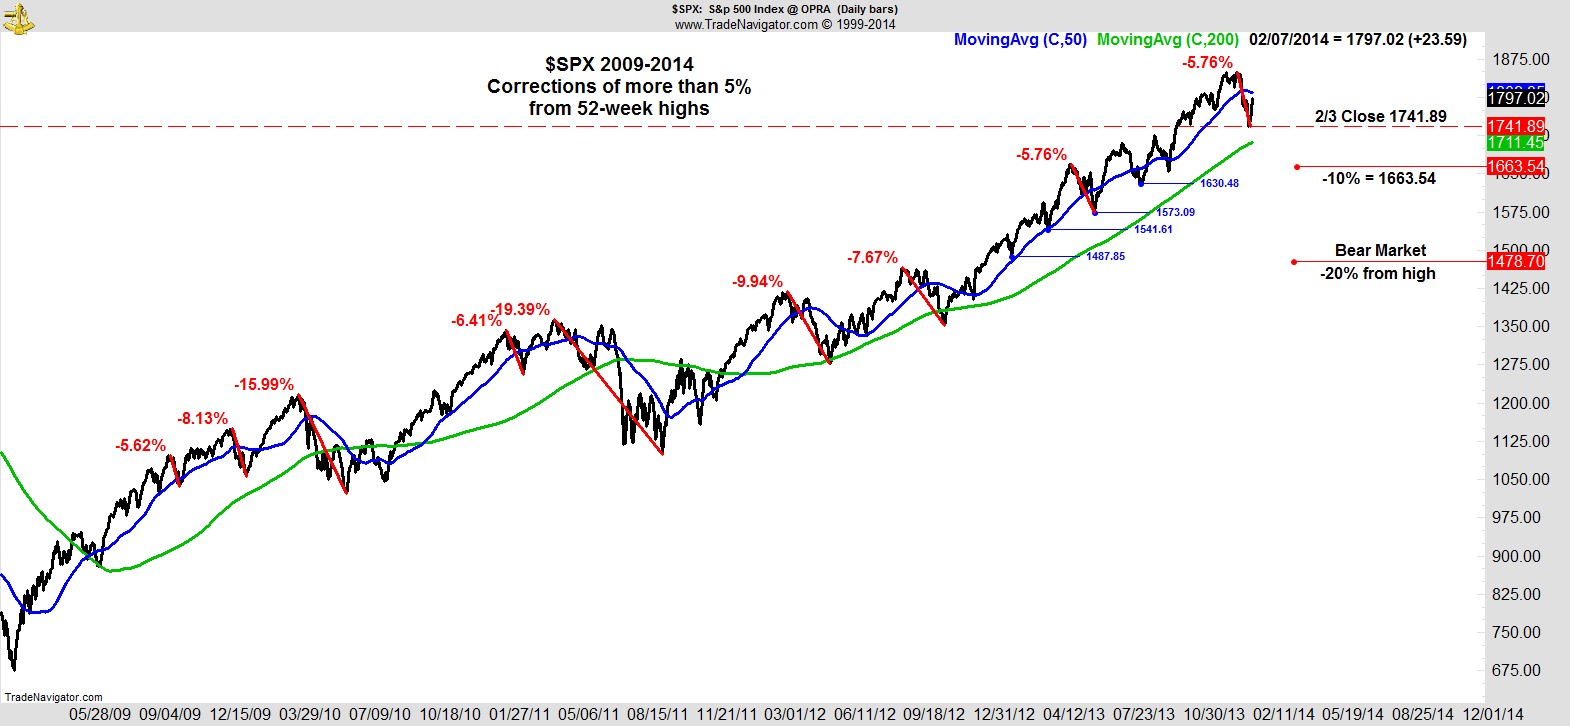
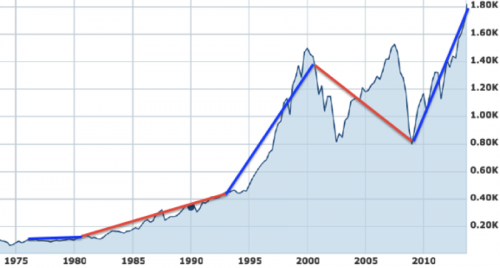
History illustrates time and again that market volatility leads to memory problems for many investors.  Check out this chart itemizing all market corrections of 5% or more since the bull market began.

****

original_19861592

****

As you can see, although the S&P 500 index has increased in value from 676.53 on March 9, 2009 to 1,819.75 on February 11, 2014, the S&P 500 has endured nine pullbacks of over 5% during that time frame.

As illustrated by the lengths of the red lines associated with each correction, many of these market declines happened over a similarly short time span.

Consequently, despite the S&P increasing in value by 169% over the last five years, the market has experienced a decline of at least 5% every six and a half months on average.

In fact, nearly a third of the months since the bull market began have seen the market decline, and by an average of 3% per month.  Considering this information, late January and early February wasn’t particularly unusual.

Periodic Pull-Backs

These periodic market pullbacks aren’t specific to the recent strong run. Historically, we typically see three stock market dips of 5% or more every year and one correction of more than 10% every 20 months. Yet, for some reason, the same conversations and concerns are repeated during every market correction. Investors wonder if this is the beginning of an extended market decline or even a crash?

People consider selling their assets and taking their money out of the market. It is so easy to forget that we have seen similar circumstances in the past and that very rarely has anyone benefitted from selling.

Refer back to the chart itemizing all market corrections over the last five years. There wasn’t a single market decline that didn’t recoup all value in a short period of time. Even the 20% decline that occurred in 2011 only took nine months to go from peak to trough to new all time high.

Assessment

As a result, I’d suggest that the January decline in the markets is not only nothing to be concerned about, but it is expected and healthy. In fact, if you have done your homework as an investor and have a well diversified portfolio with a stocks/bonds ratio that matches your risk tolerance, you’ll be hard-pressed to find a market movement that justifies dramatic action.

Of course, there will always be market corrections (even the occasional crash), but as long as your portfolio is built to accurately match your investment time horizon, market values are likely to recover before the pullback is catastrophic to your retirement goals. Next time the market experiences a short-term correction, remember it isn’t anything we haven’t seen before.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

On “Ethical Wills”

Join Our Mailing List

AKA Heritage or Legacy Wills [An Ash Wednesday Tribute]

By Dr. David Edward Marcinko MBA CMP™

www.CertifiedMedicalPlanner.org

Dr. DEM

An ethical will is a document designed to pass ethical values from one generation to the next.

It was first postulated in 1998 by Barry K. Baines MD in his Ethical Will Resource Kit.

He then founded the www.EthicalWill.com website, now known as www.CelebrationsofLife.net His hospice care experience provided the impetus for developing resources to help people write and preserve their legacy of values at any stage of life [personal communication].

By 2005, Andrew Weil MD promoted ethic wills as a “‘gift of spiritual health”’ to leave family members. The goal is to link a person to both their family and cultural history, clarify ethical and spiritual values, and communicate a legacy to future generations.

Today, ethical wills are written by both men and women of every age, ethnicity, faith tradition, economic circumstance, and educational level. For FAs, an ethical will can open the door to start a bigger conversation about estate planning. Susan Turnbull, a principal with Personal Legacy Advisors in New Hampshire is author of The Wealth of Your Life: A Step By Step Guide for Creating Your Ethical Will, a document that some financial advisors offer their clients as a template for creating them.

###

ethical-exercises

###

Assessment

In recent years, the practice has been increasingly used by the general lay public and medical professionals. In fact, the American Bar Association [ABA] described it as an aid to estate planning in health care and hospice and as a spiritual healing tool.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

The Baby-Boomer Retirement Crisis

Join Our Mailing List 

Panic or Warning?

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFP“The world braces for retirement crisis.”

This headline caught my attention because of its tone of near-panic. It implied that the pending retirement crisis was like a hurricane or other natural disaster, striking with little warning and beyond our control. Not so. Financial columnists like me have warned for the past two decades that Baby Boomers are woefully unprepared for retirement.

The AP Piece

The article itself, an AP piece published at the end of 2013, was actually quite a good summary of the problems looming as Boomers retire worldwide. It quotes a survey done by the Center for Strategic and International Studies as concluding, “Most countries are not ready to meet what is sure to be one of the defining challenges of the 21st century.”

Governmental Outsourcing 

Instead of limiting their lifestyles and saving for retirement like their parents did, Boomers around the world outsourced their retirement to government. Not only did the Boomers not save, they fostered an entire culture of spending more money than they’ve earned; a trend evident not only in their personal finances, but also in all levels of government.

The Blame Game

The financial press often blames the Great Recession of 2008 for the coming retirement crisis. Few reporters ever suggest that the personal and public overindulgences of the Boomers in the decade prior to 2008 were largely the cause of the crash. Neither the Boomers nor most of their governments have the cash to support them in retirement. Retirees need a nest egg of 25 times their desired annual income.  Most Boomers don’t have more than three or four times that income saved in retirement plans.

The Poll

According to a 2010 Gallup poll, Americans are concerned about the Social Security system but unwilling to make sacrifices in order to fix it. A majority of respondents favored raising taxes on high earners and limiting benefits to the wealthy. Otherwise, they didn’t want to limit benefits, raise retirement ages, or increase taxes for all workers. Given a choice between raising taxes OR reducing benefits, however, more respondents (49% to 40%) would opt for higher taxes.

The Dilemma

The problem with this is two-fold.

First, in many developed countries facing this problem, including the US, tax rates already exceed 50% on upper income earners, leaving little room for extra revenues.

Secondly, the AP articles notes that birth rates in most developed countries are declining “just as the bulge of people born in developed countries after World War II retires.” This means the younger taxpayers just will not be able to foot the bill.

The Solution

One possible solution has three components:

1. Lower taxes to spur economic activity, thus creating more jobs and ultimately increasing revenues to government.

2. Increase the Social Security retirement age. When Social Security was created, average Americans lived only a few years beyond age 65. Now we live into our 80’s. Increasing the retirement age to 75 or 80 would be keeping with the original intent of the program.

3. Create incentives for young Americans to save. Australia is already doing this. Allow taxpayers to save up to $75,000 a year, tax-free, and allow distributions to be tax-free.

For now, if you are a physician, medical professional or lay Boomer who has woefully underfunded your retirement plan, putting more money away now won’t make much difference unless you can save 30% to 50% of your income. Declining birth rates, however, mean fewer available skilled workers, so many Boomers will be able to work longer.

Assessment

The best retirement plan, then, might be to invest in improving your workplace skills, shedding weight, starting an exercise program, and eating healthier. The biggest assets Boomers may have for retirement are the skills and health to stay in the workforce.

But, what about doctors and other medical professionals?

MD Boomers

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Our ME-P Recommended Books Review

Join Our Mailing List

Purchase today and Profit in 2014

By Ann Miller RN MHA

[Executive-Director]

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Product Details

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to write a book review or check out our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

###

On Malicious Healthcare Cyber Traffic

Join Our Mailing List

According to Sector

By www.MCOL.com

Cyber Traffic

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details

How to Stop Winter Road Salt Vehicle Damage

Join Our Mailing List 

Act quickly to prevent rust and undercarriage damage

[By Dr. David Edward Marcinko MBA and Nalley Lexus, Roswell GA]

DEM blue tieEach year, physicians and all drivers face the same challenge in the aftermath of wintry weather: potential rusting and other vehicle damage due to the buildup of road salt, ice, and grime. And, this winter was particularly severe; even here in Georgia.

Salt Rage

Road salt serves an important function by actively melting snow and ice that may have formed on the surface of the highway in addition to preventing snow and ice from settling in the first place, improving traction for road users and helping to keep the traffic flowing more safely. The main disadvantage of road salt is that, if left unchecked, it can potentially cause damage to your car.

When road salt builds up on your vehicle, don’t wait to get your vehicle thoroughly cleaned as soon as possible, or use a professional cleaning and detailing service.

Prevention is key to avoid long-term damage

Many experts recommend applying a coat of protective wax, followed by a coat of wax sealant, before road salt buildup, since it is far more difficult to prevent damage to the car after the fact. These products help protect the paintwork from the corrosive effects of road salt.

But it’s not just the paintwork that requires protection. Your brake and fuel lines are very susceptible to damage from corrosion. Therefore, road salt cannot only have damaging aesthetic implications—it can have a significant impact on your vehicle’s safety as well.

Get salty deposits removed quickly

When you have been driving on salted roads, it is important to remove salt deposits as soon as possible. A simple car wash may not always be the most effective option. With professional detailing services though, you can count on getting a thorough cleaning which will help protect your vehicle against possible damage. Additional services like steam cleaning and undercarriage cleaning offer even more peace of mind.

Professional detailing services may be more affordable than you think, especially when you consider the long-term damage that can result if road salt is left unchecked. After the cleaning, we recommend getting your vehicle re-waxed and sealed to protect your vehicle against any future wintry conditions during the season.

###

Jag

###

Jag interior

###

JaguarBoot

###

Assessment

Take a look at my 2000 Jaguar XJ-V8-L touring sedan above; pristine!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Product Details

The “Die-Brokers”

Join Our Mailing List

Results of an HBSC Survey

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFP

In recent ME-P columns I reported on a survey done by the financial services company HBSC that found only 59% of US parents intend to leave their children an inheritance, the lowest of the 15 nations in the survey. The fact the US is last came as no surprise to me. What did surprise me was that 59% seemed high.

My Average Clients

My average client is someone who has saved over one million dollars. I am guessing that less than 2% of them have any intention or goal of constraining their current lifestyle in order to maximize their kids’ inheritance. Consuming their last penny of savings about the time they take that last breath is their spending plan of choice. There is even a name for these folks: “Die Brokers.”

If they did a good job of planning for retirement, however, most Die Brokers will leave something behind. Almost all of these I work with intend to divide what remains equally among their children. The point is that leaving an inheritance just isn’t a priority or a goal that constrains their current spending. As a side note, I rarely see any intention to leave any significant portion of their estate to charity.

The Survey

Why did the survey find such a high number of parents who intend on leaving their kids an inheritance, as compared to my observations that almost none intend to? My experience is that most people have a money script of, “Good parents should leave something to their children.” It is similar to another money script of, “Good parents should pay for their children’s college education.” These are seen as things “good” parents do. My hunch is that when most respondents answered the survey question, they let their money script do the talking, rather than their true intention.

The Explanation

Still, this does not explain why US parents intend to leave their children less than parents in any other country. One reason could be that more parents in other countries have money scripts that it’s necessary to leave their kids an inheritance.

One of the most common themes among my affluent clients is a desire to see their children “make it on their own.” Over 90 percent of these clients are first-generation wealth builders, meaning they didn’t inherit their money but accumulated it from saving, investing, or building a business. They value hard work and frugality and feel leaving a large inheritance to a child is more hurtful than helpful.

First Generation Millionaires

Many of these first-generation millionaires also feel accumulating wealth in the US is very attainable with hard work, discipline, and frugality. This is not the case worldwide. In many countries, it doesn’t matter how hard you work or how frugal you are, confiscatory taxes and oppressive regulations insure that those people not fortunate enough to be born into money will never have a chance to become affluent. The only way to have a comfortable net worth in many countries is to either inherit it or work for the government.

Sadly, the US is closer to adopting a model that makes accumulating wealth increasingly difficult. I can’t name a politician currently campaigning who advocates lowering income taxes on wealth builders. Yet I can name scores who are running on increasing taxes on “the rich.”

staitns572x0

Assessment

Affluent parents in the US may soon begin to feel that, without an inheritance, their children may never have the means to get ahead. If more US parents begin believing this, we will probably see increasing numbers intending to leave money to their kids. The money script of “Good parents should leave something to their children” might become the truth.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Determining Intrinsic Stock Value Using the Dividend Discount Model

Join Our Mailing List

What it is – How it works?

By Dr. David Edward Marcinko MBA CMP™

http://www.CertifiedMedicalPlanner.org

DEMM high-def White

The Dividend Discount Model (DDM) is one of the most widely used valuation methods for estimating a stock’s intrinsic value.  A stock can be thought of as the right to receive future dividends. A stock’s intrinsic value is defined as the present value of its dividends under the DDM.

In its simplest form (i.e., zero-growth), the DDM determines a stock’s value by dividing the stock’s dividend by the investor’s required rate of return.  The investor’s required rate of return should reflect current interest rates plus the risk associated with investing in the stock.

Rate of Return

The rate of return determined under the CAP-M [Capital Asset Pricing Model] is frequently used in the DDM.

For example, assuming that ABC Corporation pays a $2.00 dividend per share and that an investor requires a 10 percent return for holding ABC stock, the stock’s intrinsic value is $20 ($2/0.10).

Shortcomings

Shortcomings of the zero growth DDM include the following:

  • The model assumes that the stock’s dividends will remain constant over time.
  • The model assumes that dividends are the only source of return available to stock investors, ignoring the effect of reinvested earnings.
  • The model can only be used to value stocks that pay dividends.
  • The model assumes that the company and the dividends last forever.

Despite its shortcomings, the DDM highlights the point that the stock market is discounting mechanism and that financial investments should be assessed in light of the future cash flows that they are expected to provide investors.

A Variation

One variation on the DDM that may be appealing to healthcare professionals involves determining the present value of a stock’s earnings rather than simply its dividends.

Theoretically, owning a stock entitles investors to a claim on the earnings that are left after accounting for the company’s costs (including interest costs).  A model accounting for a stock’s earnings rather than just dividends may help account for the capital appreciation element of owning stocks because a corporation can either invest its earnings back into the company to pursue growth opportunities or distribute the earnings to shareholders in the form of dividends.

Stock_Market

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Healthcare Business Trends of Greatest Impact for 2014

Join Our Mailing List

According to Healthcare Professionals

By www.MCOL.com

ImageProxy

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Do Doctors RV?

Join Our Mailing List

On Recreation Vehicles?

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFP“See new places!”

In my experience, the number-one activity most people look forward to when they retire from earning an income is travel. Seeing and experiencing the world has never been easier. True, air travel is rarely easy or pleasurable, and it can be expensive. Yet, with a little planning and work, travel can fit easily into many retirees’ budgets.

Affordable

The most affordable option is becoming a part-time or full-time RVer. While to me driving around the country in a motorhome or hauling a camper sounds like a lot of work, it’s very pleasurable for a lot of folks. There are no security lines, tour schedules to keep, or nights spent stranded in airports. You may not go fast, but you get to go where you want, when you want.

Options

RVing doesn’t mean you need to buy a motorhome as long or as pricy as a semi-trailer truck. It can be as simple as pulling a small camper/trailer or a fifth wheel. While you will need a heavier gas-guzzling vehicle than a Toyota Avalon to pull your rig, the costs can be significantly lower than staying in motels. This is the case even when you consider costs like auto insurance, depreciation, tires, maintenance, and camping fees. You can even minimize the camping fees as long as you’re okay with a view of the local Walmart’s parking lot.

A Lifestyle?

Judging from retirees I know, RVing can become a lifestyle very quickly. RVers develop networks and associations with other RVers to share experiences, costs, and information. Some of my clients enjoy the lifestyle so much they have actually sold their homes, preferring the RV as their primary residence.

This is when RVing can take financial efficiency to new levels. By not owning a home, you can take the money previously tied up in a personal asset and make it produce income.

Example:

Let’s illustrate with some numbers. It isn’t uncommon for couples in the Black Hills who are in their 50’s or 60’s to own a paid-for home worth $250,000. That amount, invested in passively-managed mutual funds diversified in five or more asset classes, reasonably produced an annualized return of 6% over the past 10, 20,or even 30 years. If you leave half this return to help keep up with inflation and withdraw the other half, you’ll have  about $625 a month in new income.

The good news is you don’t need a lot of money to retire to an RV lifestyle. The extra $625 a month from selling a home, combined with Social Security and a modest IRA, can go a long way. I know several RVers who do nicely on such income.

Economic Organization

Here’s how it might work for a typical couple. A total amount saved to IRA’s of $450,000, plus the proceeds from selling their home for $250,000, would produce income of $21,000 a year. Adding this to their combined Social Security income of around $30,000 a year would give them $51,000. That’s more than enough to enjoy modest but comfortable RV living.

An added benefit for residents of a state like South Dakota, which has no income tax but relatively high property tax, is a lower tax bill.

Road to Retirement

Assessment

Just one word of caution. Before you sell your house, make sure full-time RVing is right for you. Take a trial period of at least a year, renting out your home while you travel. Then, once you decide the roving lifestyle is what you want, you can cut your ties to terra firma and set out to enjoy the freedom of the open road.

Conclusion

So, do doctors and other medical professionals, RV? Really?

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Mastering the Business of Healthcare

Ohio University Master of Health Administration Online

Join Our Mailing List

By Frankie Rendón

Ohio University online MHA

MBH

Link: Ohio University Master of Health Administration Online

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Are Eye Exams Diagnostic?

Join Our Mailing List

We Champion the Visually-Impaired

By www.MCOL.com

eye

Assessment

You bet they are!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Join the 4th Global m-Health App Developer Economics Study

Join Our Mailing List

Invitation to Participate

By Flavio Zoppini

Dear Dr. Marcinko,

I am contacting you to ask the ME-P to become a partner for the 4th Global M-Health App Developer Economics.

The 4th Global MHealth App Developer Economics is conducted in partnership with Global Health Alliance and established global mHealth players and healthcare publishers like Happtique, HIMSS, WIP and Pharmaphorum.

Our partners will help us to make this project the largest mHealth app development study globally.  The target audience for the study is mHealth app developers and publishers as well as decision makers in the healthcare industry and institutions that oversees mHealth activities.

Results will be presented on the mHealth Summit in Berlin May 2014.

Partner benefits:

  • Our partners will get first hand insights from the study results.
  • Brand will be part of the largest study about mHealth apps.
  • Raise awareness for publications and blogs among a large target group.

We invite you to become a partner as well and help us to:

  • Invite survey participants. The study will be largely based on the results of a global online survey which has been launched last week.

Here is a link to the survey. Take the survey

Write about the results of the study once it is finished.

Here are some topics the study is covering:

  • Impact on healthcare: e.g. how will mHealth apps help to reduce healthcare costs?
  • Market potential: e.g. what are the mHealth app categories that offer the biggest market potential in the next five years?
  • Business models: e.g. what impact do sensors and wearable devices (e.g. glucometers and glasses) have on mHealth apps?
  • Trends: e.g. what will be the main distribution channels for mHealth apps in five years?
  • The market’s current status: e.g. what are the main reasons for publishing mHealth apps?
  • Innovation: e.g. how do APIs change the way mHealth apps deliver their services?

SONY DSC

Assessment

We would like you to join the team of partners for this project.  I look forward to your ME-P reader feedback.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Do Medical Practices Really Like EHRs?

Join Our Mailing List

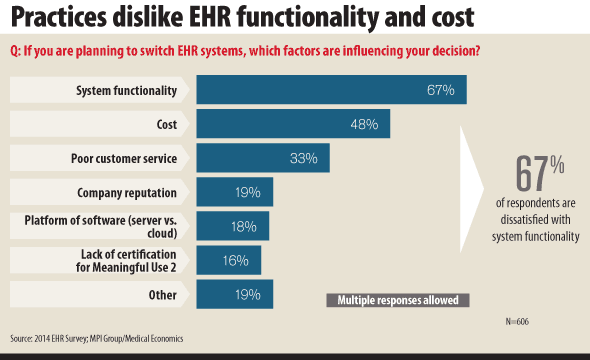
Do practices like functionality and cost?

By www.MCOL.com

EHR

More:

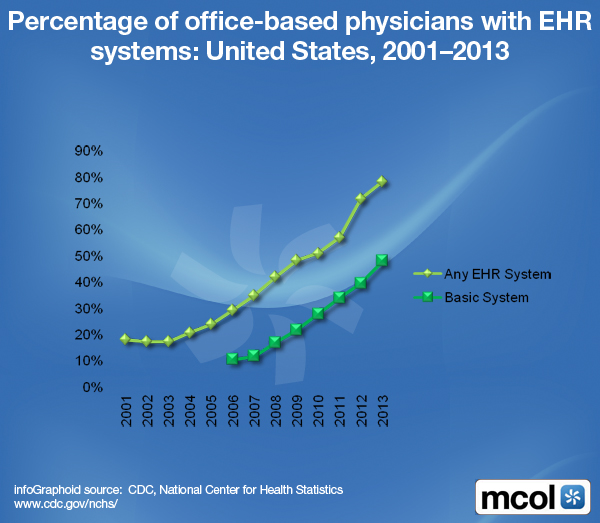
  1. The Percentage of Office-Based Doctors with EHRs
  2. Do Nurses like EHRs?
  3. EHRs – Still Not Ready For Prime Time
  4. The “Price” of eHRs

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Are Dentists Satisfied with their EDRs?

Join Our Mailing List

Major Discontent With EHR Adoption

[By D. Kellus Pruitt DDS]

1-darrellpruittUnlike physicians, dentists never complain. That means they are probably 100% satisfied with their electronic dental records.

What do you think, Doc?

MarketWatch 

Recently, the Wall Street Journal’s MarketWatch posted a press release titled, “Physicians Cite Major Discontent With Adoption And Use of Electronic Health Record Systems, Despite Government’s $27 Billion Incentive Program”

http://www.marketwatch.com/story/physicians-cite-major-discontent-with-adoption-and-use-of-electronic-health-record-systems-despite-governments-27-billion-incentive-program-2014-02-07

“CLEVELAND, Feb. 7, 2014 /PRNewswire/ — The $27 billion government experiment to incentivize physicians to convert to electronic health records (EHRs) has not been worth it, according to nearly 70% of physicians surveyed.

Medical Economics 

***

In fact, a national [Medical Economics] survey of nearly 1,000 physicians, set for release on February 10, 2014, shows widespread dissatisfaction related to the functionality and cost of these patient record systems. About 45% of physicians believe patient care is actually worse as a result of adopting EHR technology, two-thirds would not purchase their current EHR system again, and 43% of physicians say these systems have resulted in significant financial losses.

In addition, the current state of technology has not improved the coordination of care with hospitals, physicians say.”

***

It is probably better for HHS that very few dentists were able to participate in the ARRA stimulus giveaway. Otherwise, tax-paying citizens might have learned about the wastefulness of Meaningful Use requirements for dentists – which nobody has the guts to reveal. That pretty much rules out brilliant Meaningful Use ideas.

Those who might patriotically defend the benefits of the tasks would do so, if they were idiots.

So how do dentists feel about their electronic dental records? It’s hard to tell. Over 96% of them are HIPAA-covered entities, making them vulnerable to audits, which can be “random” now. As one can imagine, very few dentists openly discuss EDRs. Do you think the silence is more likely to improve or harm patient care?

doc

Even though thousands of physicians have participated in dozens of national surveys like Medical Economics’ over the last few years, as far as I know, not one survey of dentists’ opinions has ever been published. Perhaps someone can prove me wrong. I doubt it.

The Survey

The results from the Medical Economics survey include:

  • 67% say that system functionality influences their decisions to purchase or switch systems.
  • 48% say that cost is influencing their decisions to purchase or switch systems.
  • Nearly half of physicians say that implementation of EHR systems has made the quality of patient care worse.
  • 69% of respondents say that coordination of care with hospitals has not improved.
  • 45% say they have spent more than $100,000 on an EHR
  • 77% of the largest practices (more than 10 physicians) spent more than $200,000 on an EHR.
  • 38% doubt their systems will still be viable in 5 years.

Assessment

Not long ago, Wisconsin became the first state to outlaw paper dental records, which are both cheaper and safer than digital.

So, is it still too soon for dentists and patients demand more transparency in dentistry? When costs and danger are hidden in dental care, it is always the last in line who suffer the most – clueless, trusting dental patients.

Am I right, Doc?

More:

  1. Sales of Dental Equipment and eDRs Down
  2. Military Electronic Dental Records [eDRs]
  3. Dr. Pruitt Invites Dr. Cohen to Discuss eDRs
  4. Cyber Insurance for Dentists

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Who Gets Government Aid thru the HIEs?

Join Our Mailing List

The Premium Assistance Tax Credit

By Lon Jefferies MBA CFP®

Lon JeffriesThe Premium Assistance Tax Credit (PATC) is designed to help “lower” income individuals and families pay for health insurance plans purchased through the new health care exchange program.

However, more people may qualify for government assistance when purchasing health care through the exchange than may realize.

Terms and Definitions

The program defines “lower” income as households that earn less than 400% of the Federal Poverty Level (FPL), which is based on the number of individuals in the home. In 2013, the FPL for a single individual was $11,490.

Similarly, the FPL for a household of two people was $15,510 and the FPL for a home of four individuals was $23,550. Consequently, at least some premium assistance credit is available for individuals earning less than $45,960, couples earning less than $62,040, and a household of four earning less than $94,200. (Click here for more information on the Federal Poverty Level for households of various size.)

It’s important to note that for the purposes of the assistance program, income is defined as modified adjusted gross income. This means that a taxpayer’s adjusted gross income will include all Social Security benefits received (whether it was taxable or not), and all bond interest (tax-exempt or not). This factor will reduce a person’s eligibility for aid if he begins receiving Social Security before age 65 (at which point he qualifies for Medicare and can no longer participate in the health care exchange).

A Reverse Calculation

The amount of aid the government will provide is essentially calculated in reverse – the maximum amount that an individual or family can owe is calculated, and the government will pay the remaining premium. This table shows the Premium Assistance Tax Credit thresholds based on income relative to the Federal Poverty Level:

###

Income Relative To FPL: Premiums Limited To:
Up to 133% of FPL 2% of household income
133% to 150% of FPL 3% to 4% of income
150% to 200% of FPL 4% to 6.3% of income
200% to 250% of FPL 6.3% to 8.05% of income
250% to 300% of FPL 8.05% to 9.5% of income
300% to 400% of FPL 9.5% of income

###

Example:

For example, assume John is a single 62-year-old living in Utah and making $30,000 per year. (Again, remember that when calculating the PATC, it really doesn’t matter whether John’s $30,000 of income is from employment, a Social Security benefit, or a combination of the two.) John’s income is 261% of the FPL amount for singles [($30,000/$11,490) * 100], so this puts his threshold between 8.05% and 9.5% of his income. His exact threshold is 11/50ths of the way between 250% and 300% of the FPL, so his maximum premium is 11/50th of the way between 8.05% and 9.5%, which means his maximum premium is 8.37% of his $30,000 income, or $2,511 per year ($210 per month). This is the most John will need to pay for an adequate health insurance plan.

telehealth

What is Adequate Health Insurance?

What is deemed an adequate health insurance plan? The next relevant figure in the calculation involves determining the cost of the second least expensive Silver plan in the state. This can be determined by obtaining a quote at www.healthcare.gov. Assuming John lives in Salt Lake County, the second least expensive Silver plan available to him cost $5,100 per year ($425 per month). Whether or not John decides to purchase this exact policy, the $5,100 annual cost of the plan is significant.

Since the second least expensive Silver plan available to John cost $5,100, but the most John will be required to pay is $2,511 per year (8.37% of his income), the PATC program will cover the cost difference of $2,589. This amount will be the tax credit available to John for purchasing any health insurance policy through the exchange.

However, this does not mean that John is required to actually purchase and utilize the second least expensive Silver plan available to him. If John is so inclined, he can purchase a less expensive policy and he will still receive the $2,589 tax credit determined to be available to him.

Nevertheless, since the policy is less expensive, John would need to cover less of the cost of the inferior policy out of his own pocket. Similarly, John could also purchase a more expensive policy, but his tax credit would still be $2,589 and he would need to cover the additional cost of the superior policy with his own money.

Assessment

People are still familiarizing themselves with the options available within the health care exchange. Many will be surprised by their eligibility for assistance, and the amount of government aid available. Determining whether you qualify for a Premium Assistance Tax Credit will help you evaluate the attractiveness of the program.

More: Understanding Basics of the Health Insurance Exchanges [HIEs]

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Percentage of Families with Medical Care Financial Burdens

Join Our Mailing List

The CDC Definition

By www.MCOL.com

CDC

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details


Enrollment, Coverage and the PP-ACA

Join Our Mailing List
For Medicaid

By www.MCOL.com

ImageProxy

Assessment

1. Aetna CEO: Only 11% Of ObamaCare Signups Have Been Uninsured 
2. The Individual Mandate for Health Insurance in the U.S.
3. Survey of Americans’ Preparations for Health Care in Retirement
4. Medi-Cal at a Crossroads: What Enrollees Say About the Program 
5. The Affordable Care Act: The Exchanges Go Live

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

How Have Bonds Responded to Higher Interest Rates?

Join Our Mailing List 

A Survey of Economists

By Lon Jefferies MBA CFP™

Lon JeffriesRecently, I pondered the possibility of interest rates rising and the impact it might have on bonds. The article was motivated by a Wall Street Journal survey of 50 top economists who forecasted the yield on the 10-year Treasury bond to rise to 3.47% by the end of 2014.

As you may know, the investment return of existing bonds tends to move inversely to interest rates. Consequently, there has been significant concern that bond values are due for a considerable drop, and investors have constantly questioned whether they should reduce their exposure to fixed-income investments.

The Forecast Results

So how has the economists’ forecast panned out through January? The 10-year Treasury bond began the year at 3.03%, but ended January at 2.65% — a significant decline.

As a result, bonds have generally increased in value. For instance, the iShares Investment Grade Corporate Bond ETF (LQD) is up 1.88% since the New Year, while the iShares Barclays 7-10 Year Treasury Bond (IEF) is up 3.06%. Even the SPDR Barclays International Treasury Bond ETF (BWX) is up .45% in 2014.

Why?

What has caused this unexpected result?

First, the historical inaccuracy of interest rate forecasts is well documented. A study by the University of North Carolina found economists predict future rates far less accurately than a random coin flip would fare as a predictor. Rising interest rates have been a general expectation since shortly after the market crash of 2008. Remember all the people who refinanced their homes away from an adjustable-rate mortgage to a fixed mortgage from 2010-2011 out of fear of rising rates? That rate hike still hasn’t come.

But, more important than the unpredictable nature of interest rates is the way bond performance has historically been related to the stock market’s performance.

In difficult market environments, the investment returns of stocks and bonds tend to have an inverse relationship. In fact, the S&P 500 (a broad measure of the U.S. stock market) has decreased in value during a calendar year five times since 1990 (1990, 2000, 2001, 2002, 2008). In all five instances, the value of U.S. Government Bonds (as measured by the Barclays Long-Term Government Bond Index) has increased (6.29%, 20.28%, 4.34%, 16.99%, and 22.69%, respectively).

RISK

Performance of Equities

How have risky stocks performed in 2014? The S&P 500 is down -3.46%, the Dow Jones Developed Market ex-U.S. market index (a measure of international stock performance) is down -3.64%, and the iShares MSCI Emerging Markets Index is down -8.63%.

It appears investors have fled stocks in a declining market and sought solace in the fixed income benefit that bonds provide, in-step with historic behavioral norms. Of course, higher demand for bonds means higher values. This last month has been a nice reminder of the stability bonds can add to a portfolio in a time of declining stock prices.

Assessment

While it is reasonable to expect interest rates to rise by some measure over the long-term, it would clearly be a mistake to dramatically shift your asset allocation away from bonds if they were determined to be a part of an investment portfolio that matches your risk tolerance.

January 2014 illustrated that bonds tend to increase in value and add benefit to a portfolio during market pullbacks, regardless of what interest rates are doing. In fact, bonds’ historical inverse relationship with stocks may be a larger determinate of performance than interest rate expectations.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Before You Jump to a Full-Fledged EMR Check Out Other Options [Part 2]

Join Our Mailing List

HIT: PART TWO

By Shahid Shah MS

Shahid N. ShahWowsa!

What a year [2013] in the HIT business?

Because of all the talk about EMRs and medical records software you’ll have many reasons to start immediately looking for an EMR vendor.

Try to resist that urge and look at broader non-EMR solutions that can help remove some of the non-clinical burdens from your staff in 2014:

  • Fax Server – a fax server allows you to centrally manage all incoming and outgoing faxes. Since most medical practices live on fax, this is one of the fastest investments you can recoup.
  • Shared drives – start using shared drives either using your existing software or you can purchase inexpensive “network disks” for a few hundred dollars to share business forms, online directories, reports, scanned charts, and many other files.
  • Online backups and Internet PACS storage – there are online tools like JungleDisk.com that allow you to store gigabytes of encrypted data into the Internet “cloud” for just a few dollars a month.
  • E-mail (beware of HIPAA, though) – internal office messaging and email is a great place to start. If you haven’t started your office automation journey here you should. If you’re going to use it for patient communications you’ll need to make sure you have patient approvals and appropriate encryption. If you’re on Gmail today and you want to have customers immediately be able to communicate with you on Gmail, that’s generally HIPAA compliant because communications between two Gmail accounts stays within the Google data center and is not sent unencrypted over the Internet.
  • E-Prescribing – e-prescribing is a great place to start your automation journey because it’s a fast way to realize how much slower the digital process is in capturing clinical data. If e-prescribing alone makes you slower in your job, EMRs will likely affect you even more. If you’re productive with e-prescribing then EMRs in general will make you more productive too.
  • Office Online and Google Apps (scheduling, document sharing) – Google and Microsoft® have some very nice online tools for managing contacts (your patients are contacts), scheduling (appointments), dirt simple document management, and getting everyone in the office “on the same page”. Before you jump into full-fledged EMRs see if these basic free tools can do the job for you.
  • Modular clinical groupware – this is a new category of software that allows you to collaborate with colleagues on your most time-consuming or most-needy patients and leave the remainder of them as-is. By automating what’s taking the most of your time you don’t worry about the majority of patients who aren’t.
  • Patient registry and CCR bulletin boards – if you’re just looking for basic patient population management and not detailed office automation then patient registries and CCR databases are a great start. These don’t help with workflow but they do manage patient summaries.
  • Document imaging – scanning and storing your paper documents is something that affects everyone; all scanners come with some basic imaging software that you can use for free. Once you’re good at scanning and paper digitization you can move to “medical grade” document managements that can improve productivity even more.
  • Clinical content repository (CMS) – open source systems like DrupalModules.com and Joomla.org do a great job of content management and they can be adapted to do clinical content management.
  • Electronic lab reporting – if labs are taking up most of your time, you can automate that pretty easily with web-based lab reporting systems.
  • Electronic transcription – if clinical note taking is taking most of your time, you can automate that by using electronic transcribing.
  • Speech recognition – another “point solution” to helping with capturing clinical notes; you can get a system up and running for under $250.
  • Instant Messaging (IM) – IM gives you the ability to connect directly with multiple rooms within your office using free software; if you want, you can also connect with patients and other physicians during work hours.

working with computer

Assessment

Can you think of any others?

Part One: Before you Jump to a Full-Fledged EMR Check out Other Options [Part 1]

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Can Physician-Patient Intimacy be Electronic?

Join Our Mailing List 

More on Emerging Information and Communication Technologies

[By Jennifer Tomasik MS, © iMBA Inc., All rights reserved. USA]

Jennifer TomasikToday’s electronic and social media make possible a certain kind of healthcare intimacy.

ICTs—information and communication technologies—enable 24/7 monitoring of basic information such as blood pressure, glucose levels, pulse, and respiration.

ICTs

In one study, an ICT not only made it easier for patients to stay in touch with their doctors, the outcomes were also significantly better. Today, Hippocrates is no longer trailing patients around the house to keep track of their snacks and moods.

But, Hippocrates has gone digital in the form of a wearable device that records subtle changes in biological markers and communicates them instantaneously to a health provider

Taking a Pause

While this is obviously a great advance, we suggest you pause for a moment before plugging in. Why? ICTs and social media tools can make a difference to one of the most important dimensions—physiological outcomes. But you can have the latest interactive technology at your disposal and still fail to be connected.

Example:

A story that a friend told us shows how. One morning, her elderly father was touching up the paint on his sailboat. Nearby, another boat-owner, who happened to be an emergency medical technician, noticed her father was struggling to breathe and that his lips had turned purple. A trip to the local community hospital led to a barrage of high-tech tests and procedures, a diagnosis of emphysema, later complications with cerebral hematomas, and hospitalizations and re-hospitalizations that brought him into contact with a neurologist, a neurosurgeon, a cardiologist, and a pulmonologist. Throughout her father’s medical ordeal, the team of specialists stayed in touch with each other and the primary care physician via various electronic media.

But, one person remained out of the loop—her father. One day, six months into the experience, the primary care physician phoned our friend’s mother to check on his patient. Her father recalls thinking, “Why was he calling her?” The physician was communicating, but he was emotionally disconnected.

eMRs and MU

The Moral

The moral of the story: communication needs to be patient-centered in both electronic and psychological terms. That means understanding how someone likes to communicate and making sure the medium fits the message. Electronic media are just part of the equation. The other is the doctor-patient relationship. Once a relationship is established, it may be fine to use e-mail to send information about dosage.

But, delivering a new diagnosis may require the extra effort of scheduling a phone call or a face-to-face visit.

Assessment

Today, since you have so many Health 2.0 choices, it takes some effort to select the right way to communicate in a particular situation.

ABOUT THE AUTHOR

Jennifer Tomasik is a Principal at CFAR, a boutique management consulting firm specializing in strategy, change and collaboration. Jennifer has worked in the health care sector for nearly 20 years, with expertise in strategic planning, large-scale organizational and cultural change, public health, and clinical quality measurement. She leads CFAR’s Health Care practice. Jennifer has a Master’s in Health Policy and Management from the Harvard School of Public Health. Her clients include some of the most prestigious hospitals, health systems and academic medical centers in the country.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

Product DetailsProduct Details

On Parents’ Inheritance Excuses

Join Our Mailing List 

An Estate Planning Follow-Up Discussion

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPPreviously on this ME-P, we explored three fears that stop adult children from talking with parents about their estate plans, even though such conversations could greatly benefit both generations.

These are: “It’s none of my business,” “I don’t want them to think I am greedy,” and, “It will ruin our relationship.”

Parents Fear, Too!

Children aren’t alone in their fear of approaching this topic. Most parents are just as reluctant—and for the same basic reasons. In my experience, parents’ biggest reasons for not talking with kids about legacy intentions are: “It’s none of their business,” “If I share financial information, they will take advantage of me,” and “Talking about money will hurt our relationship.”

Let’s look at each of these:

“It’s none of their business.” This is certainly true, unless you’ve made it their business. If you name a child as an executor of a will, a successor trustee of a trust, or an agent in a Durable Power of Attorney, you have made it that child’s business to know your business.

Shared Decision Making  

To throw a child into suddenly having to make financial decisions in your best interest without knowing what they must manage, where assets are held, and what your wishes are is unfair to both you and your child. Any time you put someone in a position of authority in any of your estate documents, it’s essential to carefully go through the document with them and to disclose details of the assets they will make decisions on. Start with showing them your financial statements, the contact information of your trusted advisors, and a listing of where you hold all your accounts.

If you feel you can’t trust a child with such information today, then why do you feel you can trust them as your agent or executor tomorrow? If you don’t trust a child, you’re better off to name a bank trust office or trust company to these positions.

Bank

“If I share financial information, they will take advantage of me.” This fear may be justified if your child has a history of taking advantage of you. If not, they probably aren’t going to start now. Preparing a child for an inheritance is not only prudent, it’s also a loving act of kindness you can give your child.

Sudden Money

I have worked with several families where children had no idea of their parents’ net worth. In every case, it was much higher than the kids ever imagined. Suddenly, they learned they were about to inherit hundreds of thousands or millions of dollars in various investments they knew nothing about. I witnessed these heirs try to cope with a plethora of emotions and money scripts, in addition to needing to learn the mechanics of managing a portfolio of investments. Without proper preparation, it’s not uncommon for what parents intended as a loving gift of wealth to turn into a destructive force of misery.

“Talking about money will hurt our relationship.” Parents are just as terrified to have money conversations with their kids as kids are afraid to talk with them. And no wonder—it’s parents who teach kids the no-talk rule in the first place.

Parental Wisdom

As parents, you can exercise the wisdom of age and begin the family money conversations. It may be helpful to have the first meeting with your financial planner or estate attorney, or engage the help of a financial therapist. You might be amazed to find that talking with your kids about money in a straightforward and healthy way can actually help your relationships.

Assessment

Do your kids a favor and break the no-talk rule. It’s a gift to both generations.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

How “Leaner” Hospitals Can Be Profitable in 2014

    Our Newest Textbooks with Checklists

Buy from Amazon

Learn How to Profit and Thrive in the PP-ACA Era

BOOK FOREWORD / TESTIMONIAL

###

Financial Management Strategies for Hospitals and Healthcare Organizations: Tools, Techniques, Checklists and Case Studies

###

Before you Jump to a Full-Fledged EMR Check out Other Options [Part 1]

Join Our Mailing List

HIT: PART ONE … OF TWO PARTS

By Shahid Shah MS

Shahid N. Shah MSWowsa!

What a year [2013] in the HIT business?

Because of all the talk about EMRs and medical records software you’ll have many reasons to start immediately looking for an EMR vendor.

Try to resist that urge and look at broader non-EMR solutions that can help remove some of the non-clinical burdens from your staff in 2014:

  • Using Microsoft Office Outlook® or an online calendaring system like Google to maintain patient schedules. While most vendors of clinical scheduling will tell you that medical scheduling is too complex to be handled by non-medical scheduling systems, most small and medium sized physician practices can easily get by with free or very inexpensive and non-specialized scheduling tools. By using general-purpose scheduling tools you will find that you can use less expensive consultants or IT help to manage your patient scheduling technology needs.
  • Using off-the-shelf address book software such as those built into Microsoft Office®, the Windows® and Macintosh® operating systems, or online tools such as Google apps you can maintain complete patient and contact registries for managing your patient lists. While a patient registry may not give you all of the features and functions you need immediately they can grow to a system that will meet your needs over time.
  • Using physician practice management systems you can remove much of the financial bookkeeping and insurance record-keeping burdens from your staff. Unlike calendaring or address book functionality which can be adapted from non-medical systems, insurance claims and related bookkeeping is an area where you should choose specific software based on how your practice earns its revenue. For example if a majority of your claims are Medicare related, then you should choose software that is specifically geared towards government claims management. If however your revenue comes less from insurance and more from traditional cash or related means you can easily use small business accounting software like Quicken® or Microsoft accounting.
  • Using computer telephony technology you can integrate automatic call in and call out the services that can be tied to your phone system so that you can track phone calls or send out call reminders.
  • Using integrated medical devices that can capture, collect, and transmit physiological patient data you can reduce paper capture of vital signs and other clinical data so that your staff are freed to do other work.
  • Using e-mail, instant messaging, social networking, and other online advanced tools you can reduce the number of phone calls that your practice receives and needs to return and yet continue to improve the patient physician communication process. One of the most time-consuming parts of any office is the back-and-forth phone calls so any reduction in phone calls will yield significant productivity increases.

eHRs

Assessment

Can you think of any other work-arounds?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Why Modern Physician-Hospital Relations are more Important than Ever?

Join Our Mailing List 

It’s all About Collaboration

[By Jennifer Tomasik MS]

Jennifer TomasikToday’s constantly changing medical environment demands so much more of hospitals and physicians alike. Connections with one another become all-important as partners build practices, work with office staff to streamline services, collaborate with specialists to provide advanced care, use technology to enhance processes and communication, and align with hospitals to tap into sophisticated treatment and diagnostic resources. So much more can be accomplished and offered, and the complexities of business and professional life simplified, when relationships are cultivated, maintained and appreciated.

Example:

Perhaps a certain medical practice has a better way of organizing around the patient or a more effective way to recruit and retain a new physician, both of which are centered on developing strong relationships?

There may be opportunities to build healthier relationships with hospital leadership by seeking out occasions to provide meaningful and constructive feedback and input. The bottom line is that collaboration, whether it’s within the practice, across referral partnerships or with a hospital or other provider, is a key to making the relationship more successful for all involved.

Six Steps to Building Strong Relationships

Building a strong physician-to-physician or physician-to-hospital relationship is no different than building a relationship with your bank, your lawyer, your accountant or other non-healthcare service provider. You want each of them to make your life easier, solve your problems, return your calls and value both your business and you as a customer.

And, you treat each other with mutual respect, trust and even admiration.

The Six Steps

These six steps can go a long way toward building and sustaining strong relationships.

  1. Do your homework. Research the opportunities and learn from what others have done before you get started. Educate yourself about what has worked well and compare that situation to your own.
  2. Establish goals. Look at your consistent challenges, business issues, practice patterns and results and prioritize how those determine your goals. Use this as benchmarking data to help identify future needs and goals.
  3. Build a list of potential relationships. Create a profile of the ideal partner for a relationship. Then develop a list of potential partners who have as many of those characteristics as possible.
  4. Create a framework for competition. Consider what you offer to potential partners and how you can leverage that to your advantage in evaluating future relationships. Because some potential partners may eventually become your fiercest competitors, be cautious with the types of information and data you share.
  5. Select the relationship. Whether the relationship is with a fellow physician, a support staff person or a hospital system, use an interview process to determine the right match.
  6. Start off on the right foot. Conduct a kick-off meeting to start the relationship with open communication and clear expectations. Establish an atmosphere of collaboration and mutual respect. Allow other team members to get to know the newest addition while he or she is given time to get to know the practice and its processes and procedures. Ask for feedback early on in the relationship to avoid culture clashes or misunderstandings.  Don’t allow electronic communication or online social networking to replace personal, face-to-face communication.

Hospital with paper MRs

More:

ABOUT THE AUTHOR

Jennifer Tomasik is a Principal at CFAR, a boutique management consulting firm specializing in strategy, change and collaboration. Jennifer has worked in the health care sector for nearly 20 years, with expertise in strategic planning, large-scale organizational and cultural change, public health, and clinical quality measurement. She leads CFAR’s Health Care practice. Jennifer has a Master’s in Health Policy and Management from the Harvard School of Public Health. Her clients include some of the most prestigious hospitals, health systems and academic medical centers in the country.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

The Percentage of Office-Based Doctors with EHRs

Join Our Mailing List

US 2001-2013

By www.MCOL.com

EHR

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Understanding Economics of the Medical Practice Profit Motive

  Join Our Mailing List 

Wither the Patient-Assembly Line Product Mentality

By Dr. David Edward Marcinko MBA CMP™

[Editor-in-Chief]

Dr. MarcinkoA cost-volume-profit relationship exists in any healthcare entity and emphasizes the point that the goal of an efficient emerging healthcare organization (EHO) should be profit optimization, rather than revenue or volume maximization.

The profit of any healthcare facility is what’s left after all financial outflows are removed from all financial inflows. This optimization is reached at the point where patient volume, fee per patient, and costs per patient produce highest profit, not the highest revenue.

This is the point of maximum efficiency and is where you want to be. It can be described in the equation below.

The Profit Equation

Medical profit traditionally can be defined by the equation:

Profit = (Price x Volume) – Costs

or P = (P x V) – C

whereas:

Revenue = Price x Volume

or R = PV

Making more Money

To make more money and increase profits, the [physician-executive] doctor must increase price (if possible), increase volume (if possible), or decrease costs (if possible); and ideally the doctor should perform all three maneuvers simultaneously.

Assumptions

If we assume that only costs are under the doctor’s control (a not altogether valid strategy), any strategic financial planning process that ignores them will not be beneficial.

A more efficient doctor addresses cost and volume together; but at some point, more volume does not equal more profit. This point is known as the average cost per patient and should be determined and known for each doctor, service segment, clinic, or hospital.

If visually graphed, the curve would be “U” shaped with both arms extending upward and the hump pointed downward at its most efficient point on the long-range average cost (LRAC) curve.

This tangent is the point of maximum efficiency and this is where the healthcare entity should be, as seen diagrammatically below.

Figs 1 and 2

Working harder by taking on more patients, performing additional procedures, or working additional hours in this scenario will not get the clinic, hospital, or medical practice ahead, only further behind and less economically efficient.

Thus, the main goal for all EHOs is profit improvement, not just revenue improvement …. DO-H!

Doctor-Business

The Cost Volume Relationship

Once the fixed and variable costs of a medical practice or hospital clinic are known, the effects of changes in volume on its cost structure can easily be determined.

This is known as the cost-volume relationship, as seen diagrammatically below.

Figs 1 and 2

Cost-Volume-Profit Analysis

Once a basic understanding of medical cost behavior has been achieved, the techniques of cost-volume-profit analysis (CVPA) can be used to further refine the managerial cost and profit aspects of the office business unit. They can also help illustrate the important differences between the traditional office net income statement and the more contemporary contribution margin income statement.

***

***

Assessment

CVPA is thus concerned with the relationship among prices of medical services, unit volume, per unit variable costs, total fixed costs, and the mix of services provided.

MORE: Negotiating CVPA

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
PODIATRISTS: www.PodiatryPrep.com
BLOG: www.MedicalExecutivePost.com

Children and Inheritances

Join Our Mailing List

The Last Money Taboo?

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPTalking about money is taboo in the US. If you don’t believe me, next time you’re at a social gathering ask everyone these two questions:

1. “What was your taxable income last year?”

2. “What is your net worth?”

Well, it’s not a recommended way to make new friends.

The Money Taboo

The taboo on money conversations can cause real difficulties when it extends to families. My experience as a financial planner suggests most families in the US have a “no-talk” rule around money. While a lot of family members know each other’s earnings, fewer know family members’ net worth. Even fewer have asked about their parents’ estate planning.

Many don’t intend to ever ask.  A blogger who calls himself the Financial Samurai wrote: “I never want to have the inheritance talk with my parents unless they initiate the conversation.”

Based on the responses to his article, he isn’t the only person holding this opinion. Most children recoil at even the thought of asking their parents about the particulars of their estate plans.

None of My Business

In my experience, the most common reasons for not talking to parents about their inheritance plans are these:  “It’s none of my business,” “I don’t want them to think I am greedy,” and, “It will ruin our relationship.”

Why Not Ask?

Let’s look at each of these reasons:

1. “It’s none of my business.” It’s true that parents have no obligation to disclose their finances and estate plan to their children. Yet it could quickly become your business if you are named as an executor in their wills, a successor trustee in a trust, or an agent in their powers of attorney. Asking whether you are designated as any of these roles is totally reasonable. If you are, then knowing the particulars of their estate plan and finances would be helpful for you to know. It is such a reasonable request that, if your parents are not willing to discuss the details, you may be best served asking them to name someone else.

2. “I don’t want them to think I am greedy.” If you’ve had your hand out to your parents most of your life, asking them how much you’re going to get when they kick off may not evoke a loving response. However; if you have never asked your parents for money – or – if you have asked for money and have paid them back; then you probably don’t have much to worry about! If you approach the topic from the standpoint of wanting to be fully prepared to carry out any duties bestowed upon you, I seriously doubt your parents will suddenly think you’ve morphed into a greedy, money-sucking leach.

3. “It will ruin our relationship.” One of the strongest money scripts around talking about money is that doing so will permanently harm a relationship. The Financial Samurai wrote, “I hate thinking about money and family because so often money tears relationships apart.” While money issues can certainly tear apart a relationship, so can abusing alcohol, sex, drugs, work, power, and a host of other things.

Mature Woman

Assessment

What I’ve seen is that keeping secrets about money is more harmful to relationships than talking about money. When the no-talk rule is in effect, family members make up their own stories about what is real. Those stories are rarely true, and the assumptions around them can cause misunderstanding and mistrust.

Being the first to break a family’s “no money talk” rule isn’t easy. Yet having the courage to start money conversations can be a service to the whole family. In my experience, it ultimately leads to better estate plans, more trust, and stronger relationships.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

On the Growing Population [Mental] Health Cohorts

Join Our Mailing List

[By Carol Miller RN MBA]

Carol S. MillerIncreased and Diversified Patient Populations

It is well know that patient populations at community mental health centers are on the rise and this rise is associated with different groups or classifications of individuals. Some centers may or may not have experienced increases in these specific classifications previously; however, they are increasing in many centers today and will continue in the future.

For example:

Older Adults

There is an unprecedented number of older adults who are experiencing substance abuse issues, depression, anxiety, or dementia-related behavioral and psychiatric symptoms along with a multitude of medical issues as well as complicated medication regimens that frequent these centers across the United States. The current clinic healthcare workforce is not prepared to address this influx of patients and their associated special needs at these centers.

Youngsters

Another category, children and teenagers, is also on the rise. This can be attributed to more schools referring students, more families seeking care for their children, more emphasis being placed upon mental health treatments and medications, or a combination of things.

Minorities

Minorities, such as Hispanics, Latinos, African American, and others are somewhat reluctant to seek behavioral health treatment because of the associated cultural stigma surrounding mental health. However, when these same individuals have a combined physical and mental healthcare related need, they are seeking care at community centers.

PTSD

Finally, others seeking care have had terrorism scares, are Veterans with Post Traumatic Stress Disorder (PTSD) and other affiliated behavioral symptoms, or have been afflicted with a long term mental or emotional issue from the impact of natural disasters that caused a lost loved one, home, pet, or job.

Brain view

Assessment

Many of these individuals not only have mental health issues but also have one or many medical health issues creating a complex case.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

Medical Provider Readiness for ICD-10?

Join Our Mailing List

And, for Health Plans, too!

By www.MCOL.com

ImageProxy

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Are Employees Opting Out of 401(k) or 403(b) Plans?

Join Our Mailing List 

New Retirement Thoughts for all Employees

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPHow hard is it to do things we know are good for us – like exercising more – or saving for retirement?

New Year’s Resolutions

This time of year, with broken New Year’s resolutions piling up like snow-banks, it’s clear that the answer is “very hard.” Most of us have good intentions, but we aren’t so good at taking consistent action to turn those intentions into reality.

Retirement Pans

One of the areas where many people don’t do what’s best for them-selves is participating in company retirement plans. If your employer offers a 401(k) or 403(b) plan, it’s ridiculous not to participate in it. For one thing, it’s an easy way to put money away for retirement before you see it—and before you pay taxes on it. Even better, the employer’s matching contributions give an extra boost to your savings that’s almost like found money.

Yet studies have shown that only 67% of eligible employees participate in these plans if they have to choose to sign up. When employees are automatically enrolled in the plans, and have to actively choose to opt out; however, the level of participation increases to 77%.

For this reason, the US government in recent years is encouraging large employers to offer automatic-enrollment retirement plans.

US News Report

Yet a recent article in US News points out a downside to this well-intentioned attempt to save procrastinating non-savers from themselves. Plans with automatic enrollment may have higher participation, but that doesn’t necessarily mean greater benefits for employees.

Why no Better?

When more employees participate in a 401(k) plan, the employer has higher costs in the form of increased matching contributions.

A study last fall by the Center for Retirement Research at Boston College found that companies with automatic enrollment tend to compensate for those higher costs with smaller matches. The average amount—3.2%, compared with 3.5% for plans that don’t have automatic enrollment—may seem insignificant. Yet over time it can make a big difference in the amount of money an employee has available at retirement.

Default Rates

More importantly, the study also found that the default contribution rate (the amount invested out of each paycheck) in some automatic-enrollment plans resulted in employees saving less than had they chosen that amount themselves. The default contribution rates are likely to be less than the rate required to receive the employer’s maximum matching contribution. The default investment options also tend to have underperforming investment choices compared to those chosen independently by participants.

Report Synopsis

One rather obvious conclusion of the study is that automatic enrollment means more retirement savings for employees who otherwise would not have signed up for a 401(k). At the same time, because of the lower employer matches, employees who would have chosen to sign up anyway are likely to end up with less retirement savings than they would have in a non-automatic plan.

MD Retirement planning

Questions

Does this mean automatic-enrollment 401(k) plans are not a good option for retirement saving? Not at all! If you passively participate in an automatic plan and leave your contributions at the default contribution rates and investment choices, you’ll still be better off than if you don’t participate at all.

Research

Yet the research suggests that settling for the employer defaults, a one-size-fits-most option, is probably not your best choice. You can choose instead to educate yourself about the investment choices in a plan, contribute the maximum amount you can, and take full advantage of the employer match. The more you learn about the available options, the better choices you’ll be able to make.

Assessment

Ultimately, no employer or plan manager will ever care more about your investments than you do. The most successful retirement savers are still those who take responsibility for their own future.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Three New Medical Management and Retirement Planning Videos

Join Our Mailing List

Watch These Channel Presentations

By Andrew Schwartz CPA

www.schwartzaccountants.com

Andrew SchwartzRetirement Plan Basics for Practice Owners

Wondering which type of retirement plan makes the most sense for your practice? Here, you’ll also learn why it makes sense to set up and begin to max out your retirement plan savings as soon as possible.

Million Dollar Metrics for General Dentists

General dentists can learn which metrics to generate to gauge how their practice is doing, and compare those metrics with other practices, including a sample of practices that routinely collect one million dollars or more each year.

SIBS: Implementing a Simple Incentive Bonus System

Learn to increase revenues and profits at your practice by implementing a Simple Incentive Bonus System [SIBS]. We’ve seen a lot of clients implement a SIBS and experience immediate results within their practices.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

National Health Expenditure Growth

Join Our Mailing List

A Report from the Office of the Actuary

Source: Centers for Medicare & Medicaid Services

According to the Centers for Medicare & Medicaid Services (CMS) Office of the Actuary, overall national health expenditures grew at an annual rate of 3.7 percent in 2012, marking the fourth consecutive year of low growth. Health spending as a share of gross domestic product fell slightly from 17.3 percent in 2011 to 17.2 percent in 2012.

Private Insurance

Private health insurance spending growth remained low. Private health insurance spending continued to grow at a low rate, increasing 3.2 percent in 2012 compared to 3.4 percent growth in 2011. Medicare spending growth continued to be low. Despite a large uptick in Medicare enrollment, Medicare spending growth slowed slightly in 2012, increasing by 4.8 percent compared to 5.0 percent growth in 2011.

The Totals for MC/MD

Total Medicare spending per enrollee grew by only 0.7 percent in 2012. Medicaid spending continued to grow at a historically low rate. Total Medicaid spending grew 3.3 percent in 2012. While an increase over 2011, this increase still represents historically low overall growth rates tied to improved economic conditions, as well as efforts by states to control costs.

Rx Drugs

Prescription drug spending growth was low. Retail prescription drug spending slowed in 2012, growing only 0.4 percent as the result of numerous drugs losing their patent protection, leading to increased sales of lower-cost generics. Nursing home spending growth slowed.

Pharma

Assessment

Spending for freestanding nursing care facilities and continuing care retirement communities increased by only 1.6 percent in 2012, down from 4.3 percent growth in 2011, due to a one-time Medicare rate adjustment for skilled nursing facilities.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Reviewing National Health Expenditures

Join Our Mailing List

Average Annual Percent Change from the Previous Year

By www.MCOL.com

ImageProxy

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

3 Steps to Take Before Buying Healthcare E-Signature Solutions

Join Our Mailing List

More on Paperless Healthcare Records

[By Patrick McTosh]

The movement towards paperless healthcare is growing. Every year, more and more health professionals are beginning to implement EMRs and EHRs as a way to turn their file cabinets into data on a hard drive. While EHRs help the problems of storing paper, they do not create documents that can be legally, securely and efficiently shared with third parties and patients during day to day activities.

These issues can be addressed by implementing an electronic signature solution. These types of solutions allow professions to create documents for physician orders, prescriptions, patient admissions, consent forms and other important medical documents in a timely and relatively paper free manner.

Verify EHR or EMR Integration

It’s important to ensure that whatever electronic signature software is compatible with your current EHR and EMR software. While most e-signature solution providers claim they have specialized services for healthcare organization, it’s best to confirm with a phone call or email that they have experience integrating their services with the EMR that is currently in use.

Verify Local Legislation & Signature Guidelines

Hospital accreditors have already recognized e-signatures as equivalent to paper signatures. However, it’s always important to verify federal and state regulations regarding e-prescriptions and electronic signatures.

For example, the latest DEA regulations on electronic prescriptions require digital signatures to have at least a biometric authentication. In addition, some states have not adopted the Uniform Electronic Transactions Act and therefore have difference laws pertaining to the legality of e-signatures.

Most e-signature providers specializing in healthcare tend to be on top of these things because better legal compliance is one of the benefits of e-signatures as a whole, but it’s always better do double check.

eHRs

Ensure It’s Human Error Proof

Many e-signature solutions attempt to reduce the risk of human error due to lost, damage or incorrectly completed forms which can cause significant delays. As most e-signature software will actually guide the signer through the complete process ensuring that the document meets necessary requirements before sealing the document with a tamper-evident digital seal.

Assessment

However, not all providers have such precautions against human errors, but it is definitely a must in the healthcare industry.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

On Inheritances by Country

Join Our Mailing List 

Spending an Inheritance

By Rick Kahler CFP® www.KahlerFinancial.comRick Kahler CFP

Stroll through a retirement camping resort or pass an RV on the highway, and you might see this bumper sticker:

“We’re spending our children’s inheritance”

No Joke

Apparently, this isn’t a joke. A December 13, 2013, article in CNN Money reported on a recent survey by the British-based international financial services company HSBC which asked more than 16,000 people in 15 countries about their estate plans. The US ranks last in the percentage of retired parents (56%) that intend to leave money to their kids. This is significantly below the 15-country average of 69% and far below the leading percentage of 86% in India.

US Rank

The US also ranks sixth in the amount of money ($177,000) that parents expect to pass on. This is behind Australia ($501,000), Singapore ($371,000), the UK ($234,185), France ($233,699), and Taiwan ($191,039).

No doubt there are many reasons for the country-by-country differences in what parents expect to leave their children. These may include differences in cultures, beliefs about family responsibilities, and attitudes toward charitable giving.

Contributing Factors

Other contributing factors, however, are differences in countries’ economic strength and tax laws. In a December 13 interview with The Australian, Graham Heunis, the head of retail banking and wealth management for HSBC Australia, credited some of the large inheritances there to the country’s unbroken 22 recent years of economic prosperity. Australian household wealth grew 7.6 per cent a year over the past decade, making it one of the richest nations per capita in the world.

Heunis also said, “In markets like the UK and US, inheritance and estate tax may cost heirs upwards of 40 per cent of an inheritance. With no inheritance tax in Australia, it’s no surprise the value and proportion of inheritance among Australian retirees is exponentially higher than the rest of the world.”

A Good Thing

It’s refreshing to see that accumulating and keeping wealth is still looked upon as a good thing in some countries. I doubt it’s a coincidence that most of those countries have strong economies, similar to what the US enjoyed in the past.

According to the 2013 Index of Economic Freedom, Singapore and Australia, the top two countries for inheritances, are two of the only three countries considered to have “free economies.” (The third is Hong Kong, where the average amount parents expect to pass on to kids is $145,943.) The US, considered the third top “free economy” in 2000, now sits at tenth as a “mostly free economy.”

Survey

This survey is not good news for baby boomers hoping to retire on inheritances from their parents. According to CNN Money, “About two-thirds of U.S. respondents said the inheritances they receive will at least partly fund their retirement, and 10% said they will rely on their inheritance completely to retire.”

If two-thirds of middle-aged Americans expect substantial inheritances, but only about half of elderly retired parents expect to leave inheritances, somebody is going to be disappointed.

Still, for those, like the majority of baby boomers, who are unprepared for retirement, every little bit helps. While an inheritance of $177,000 won’t put anyone on Easy Street in retirement, it could pay off a home mortgage or, if invested wisely, generate a monthly income of $450 for life.

inheritance

Another Problem

One last problem for potential heirs, of course, is that just because parents expect to leave an inheritance doesn’t mean they will be able to do so. Medical expenses or other unanticipated costs might well eat up parents’ resources during their lifetimes.

Assessment

Ultimately, relying on an inheritance for your retirement is never a wise move. It’s far wiser to use your own resources, start retirement planning early, and build your own financial security.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Learn the “Right” Investing Lessons from 2013

Join Our Mailing List 

Understanding the Recency Effect

Lon JeffriesBy Lon Jefferies MBA CFP® www.NetWorthAdvice.com

The year 2013 was viewed as a very positive one by most investors; especially physician-investors.

The S&P 500 index (measuring large cap U.S. stocks) was up 32.39% for the year.

However, the reality is most other asset categories didn’t come close to keeping up with the pace set by U.S. equities.

For instance:

  • Foreign Stocks (IEFA): 22.46%
  • Emerging Markets (IEMG): -2.77%
  • Real Estate (IYR): 1.16%
  • US Government Bonds (IEF): -6.09%
  • US TIPS (TIP): -8.49%
  • Corporate Bonds (LQD): -2.00%
  • International Bonds (IGOV): -1.37%
  • Emerging Market Bonds (LEMB): -6.73%
  • Commodities (DJP): -11.12%
  • Gold (GLD): -28.33%

In Hindsight

In retrospect, the way to maximize your gain last year would have been to hold a completely undiversified portfolio consisting of nothing but U.S. stocks. The danger going forward is to learn the wrong lesson from 2013. Investors always have the temptation to fall prey to the Recency Effect, continuing and exaggerating the behaviors that worked in the recent past believing the environment we’ve just been through will be permanent.

The Long-Term Benefits of Diversification

Many will abandon their investment strategy because it didn’t give them the absolute best result last year, failing to recognize the long-term benefit of diversification. I’d argue that a better perspective is to remind yourself that the definition of diversification is that you always dislike a portion of your portfolio.

Always Laggards

Even in the most widely prosperous market environment, a truly diversified portfolio will have an element or two that lags the market. In fact, if at any time a portion of your portfolio isn’t generating negative returns, you should be concerned about a lack of diversification in your investment strategy.

Allocate Assets Now

Now is an ideal time to review your asset allocation and remind yourself why we diversify. Modifying your allocation with a focus on what happened in 2013 would be similar to guessing a coin flip will land on tails because it did on the previous flip.

Stock Market

Assessment

The correct lesson to take from 2013 is that over time, a well-diversified portfolio is capable of producing sufficient returns to help you reach your investment goals while minimizing risk.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

The 2000 Jaguar Touring Sedan [One of the finest luxury cars ever built – yesterday]

Join Our Mailing List 

About the JAGUAR XJ-V8-L [circa 2000]

By Dr. David Ewdard Marcinko MBA CMP™

Dr. David E. Marcinko MBAProof is in the long haul, of course [more than a decade for me], but it appears as if Jaguar finally threw off the curse of unreliability. Credit typically goes to many sources, but leading the pack has to be Jaguar’s prior owner, Ford, which has brought its mighty engineering and quality suppliers into the Jaguar picture. Tata Motors, today.

Based on my experience, the XJ8L represents the highest point in Jaguar’s history. Many think it’s one of the finest luxury sedans ever built. The Vanden Plas, named for a famous British maker of custom automobile bodies, is the most luxurious XJ8L, swathed in chrome, walnut and lambs wool.

As the XJ8 designation suggests, this is a V8-powered Jag. The V12 and inline 6-cylinder engines were discontinued with the 1999 models. The 4.0-liter V8 called a sweetheart was refined in 2000 to reduce emissions. Performance was not affected.

Jaguar’s XJ8 was available in four versions in 2000: Originally priced at $55,780 XJ8, the $60,830 long wheelbase XJ8L, the even more luxurious $64,880 Vanden Plas and the $69,030 supercharged and fully loaded XJR. Those prices compared favorably to those of the $66,970 BMW 740iL and the $74,495 Mercedes-Benz S420; back in the day.

2

Walkaround

Regardless of trim line, Jaguar’s XJ is a beautiful car. It is stately without being stuffy, and the soft lines are uniquely Jaguar. The 2000 XJ8 continued the design theme set in 1986; Jaguar tried horizontal, contemporary-looking headlights in the 1980s, but they were so universally assailed that the company came back with round lights and they are critical to the overall look.

The Vanden Plas shares the longer wheelbase with the XJ8L, which is 117.9 inches. The standard XJ8 and the XJR ride on a 113-in. wheelbase. Visually, that wheelbase extension is reflected in the length of the rear windows.

The powertrain, suspension and electrical system were new to the sedan. Tata now owns Jaguar and has brought financial support and technology to the company, which greatly benefited the XJ8. Electrical systems, electronics and other traditional Jaguar problem areas have been eliminated since Ford got involved.

The 4.0-liter V8 has double overhead-cams and four valves per cylinder. It produces 290 horsepower at 6100 rpm and 290 pound-feet of torque at 4250 rpm.

That impressive power is delivered to the rear wheels through a five-speed automatic transmission. This electronically controlled automatic adapts to varying driving conditions; it senses whether the driver is cruising along the highway, hot-footing down a back road or climbing a long grade and it varies shift points accordingly for optimum power and efficiency.

The transmission also had a self-regulating adaptive capability; it compensates automatically for the effects of aging by adjusting shift quality based on any slippage it detects. Sport and standard modes can be selected by the driver: The standard PRNDL pattern can be used, or shifts can be made manually by moving the stick to the left.

Automatic Stability Control comes standard on all Jaguars. ASC operates at all speeds, using engine intervention to reduce wheel spin on slippery roads. If a rear wheel starts to spin, the anti-lock brake (ABS) controller signals a computer, which controls the spinning by reducing throttle, retarding ignition timing or cutting fuel to the cylinders. This feature has been a bit problematic for me; and others.

An optional traction control system includes all ASC functions plus brake intervention. This system comes as part of the All-Weather package, which also includes heated front and rear seats. Both types of traction control can be switched off.

The front suspension is fully independent with unequal-length upper and lower wishbones, coil springs, shocks and an anti-roll bar. Double wishbones are also used at the rear with the drive shafts acting as upper links.

They are arranged for anti-lift under braking and anti-squat under acceleration. Variable-ratio rack-and-pinion power steering is speed-sensitive.

1

Interior

Jaguar’s uniqueness is especially evident inside my vehicle. Getting in is like sliding into an English gentleman’s club, with yards of supple leather, luxurious deep-pile carpeting, and polished wood on the doors, instrument panel and steering wheel. The instruments are simple and understated in keeping with the elegant mood.

Memory functions automatically adjust the driver’s seat, steering wheel and outside mirror. The driver’s seat moves back when Park is engaged for easy exit. It moves back to the last position it was set when the ignition is turned on. A [fragile] cup-holder pops out from the console, but any drinks in it tend to get in the way of shifting.

Thanks to the long wheelbase of the Vanden Plas, or L model, the rear compartment is huge and legroom is expansive. The bench seat has two depressed seating areas, but a third person would be comfortable in the middle. Airplane-like tray tables fold down from the front seatbacks. A small pod with two rocker switches on the left side of the passenger seat allows rear-seat passengers to move the seat fore and aft and adjust the angle of the seat back. Headroom is just as generous as legroom.

4

Driving Impression

The unique looks of the XJ8 and L are complemented by a driving experience all its own. Mercedes and BMW share a ride that is more on the firm side and generally feel tight and buttoned up. Lexus and Infiniti offer a softer ride and a more relaxed atmosphere. The XJ8L is wonderfully comfortable with an elegant feel.

Acceleration performance is startling with instant throttle response. On dry pavement, the Jag will light the rear tires up if the traction control is turned off. In a handful of seconds it’s hurtling past the speed limit. Jaguar says the XJ8 can accelerate from 0 to 60 mph in 6.9 seconds, an impressive feat given its size and weight at 290-horse-power. (The 370-horsepower XJR can do it in a mere 5.4 seconds.)

Shifting is silky smooth, even at full throttle. You can almost feel the transmission signaling the engine to reduce power slightly because a shift is coming. It’s an almost imperceptible pause as the shift is made.

I had some fun with the manual shifting mode, but it seemed superfluous with a transmission that does such a great job on its own. The manual operation is electronically controlled to prevent downshifting at an inappropriate speed. The gear can be selected, but the shift won’t be made until speed has dropped sufficiently.

Differences between Normal and Sport suspension modes are perceptible on rough surfaces and in hard cornering. The Sport setting lets a little more road roughness come through the steering, but gives the car a slightly flatter stance in cornering.

Driving on narrow roads, I discovered that the fenders loom large from the driver’s seat. The left front fender obscures the center line and the right front fender masks the verge to give the driver a feeling the car is taking up all the lane and more. But it isn’t; and we never posed a threat to mail boxes or other vehicles.

The steering lets the driver feel connected to the road, providing a strong sense of control. The wheels do not straighten by themselves after a tight maneuver; they must be brought back in line by turning the steering wheel, just like a race car.

Quiet is an expected part of the luxury quotient, but we didn’t expect this much quiet. It is so quiet inside it’s almost eerie. No wind noise, no road noise, no harmonics from various systems. You can hear the transmission as it reaches a shift point, and there is a sound you realize must be the engine, but it is more like an electric motor humming than a V8 combusting.

Visibility is good in all directions; but I find the headrests make it a bit cumbersome. The C-pillars are quite thin, so rear visibility is above average for cars this size.

Overall, my 2000 XJ-8L provides a very pleasurable driving experience.

3

Assessment

This is certainly one of the finest cars built – yesterday. Ford’s involvement has undoubtedly had a lot to do with that achievement. The old quality bugaboo seems to be just a memory.

BMW and Mercedes and the rest really can’t be compared with the XJ8, other than in price, because the Jaguar offers something altogether different. In price, however, the XJ8 or L was very competitive. For luxury with a difference, drive a Jaguar XJ8 or L series.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Product Details

The Impact of Rising Interest Rates on Bonds

Join Our Mailing List

On Interest and Exchange Rates

Lon JeffriesBy Lon Jefferies MBA CFP® www.NetWorthAdvice.com

An interest rate hike has been widely anticipated for some time. According to an October survey of 50 top economists conducted by the Wall Street Journal, the yield on the 10-year Treasury was forecasted to rise nearly one percentage point to 3.47% by the end of 2014.

What impact would such a rise have on your investment or retirement portfolio?

The Impact

Christopher Philips, a senior analyst in Vanguard’s Investment Strategy Group, points out the historical inaccuracy of such forecasts.

For instance, a similar survey conducted in 2010 had economists predicting a 4.24% 10-year Treasury yield by the end of the year, an increase from 3.61% at the time of the forecast. In actuality, rates declines to 3.30% at year-end. The inaccuracy of these forecasts is well documented.

In fact, as Allen Roth mentioned in the December issue of Financial Planning Magazine, a 2005 study by the University of North Carolina titled “Professional Forecasts of Interest Rates and Exchange Rates” found economists predict future rates far less accurately than a random coin flip would fare as a predictor.

Clearly, we can’t be confident what interest rates will do in 2014, but what if economists are finally correct and rates rise? How damaging would an interest rate increase be for bonds? If interest rates rise one percentage point next year, the intermediate aggregate bond index is expected to lose -2.8% — far from catastrophic. Of course, such potential risk is notably minimal when compared to the downside of owning stocks (remember the -36.93% loss endured by the S&P 500 in 2008?).

Historical Performance

It is also interesting to study how bonds have historically performed in periods of rising interest rates. Craig Israelsen, a BYU professor, recently documented how bonds performed during the two most recent periods of rate increases. Israelsen points out that although the federal discount rate rose from 5.46% to 13.42% from 1977 through 1981, the intermediate government/credit index had a 5.63% annualized return during that period. The next period of rising interest rates was from 2002 through 2006, when the federal discount rate had a fivefold increase: from 1.17% to 5.96%. During this period, the intermediate government/credit index obtained a 4.53% annual return. Clearly, even in an environment of rising interest rates, bond performance was surprisingly strong.

##

Muni Bond Underwriters

###

Most importantly, investors should never forget the value bonds add to a portfolio as a diversifier to stocks. Frequently, the performance of stocks and bonds are inversely related.

For instance, when the stock market suffered during the tech bubble crash of 2000-2002, the Barclays Long-Term Government Bond Index rose 20.28%, 4.34%, and 16.99% in those years, respectively.

Current Indices

More recently, when the S&P 500 lost -36.93% in 2008, the Long-Term Government Bond Index rose 22.69% during the year. This diversification benefit may prove useful when stocks ultimately cool off from the extended hot streak they have experienced since 2009.

In 2013, the Aggregate Bond Index decreased in value by -1.98%. Given the occasional negative correlation in performance between stocks and bonds, is it really surprising that bonds didn’t produce a positive return given the incredible year stocks had (S&P 500 up over 32%)? Additionally, held within a diversified portfolio, isn’t the -1.98% return produced by bonds during the recent equity surge a small price to pay for the additional security they are likely to provide when markets reverse?

Assessment

It doesn’t seem prudent to avoid bonds entirely during periods of expected interest rate increases.

  1. First, forecasts of rising rates are far from certain.
  2. Second, even if interest rates rise bonds are still likely to be far less risky than stocks.
  3. Third, rising interest rates don’t necessarily mean declining bond values are a certainty – in fact, bonds performed quite well during the past two periods of rate increases.
  4. Finally, bonds are a vitally important part of a diversified portfolio, and owning uncorrelated and negatively correlated assets will be critical when equities ultimately lose their momentum.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

The Associated Press “American Dream”?

Join Our Mailing List 

On Changing Definitions

By Rick Kahler CFP® http://www.KahlerFinancial.com

Rick Kahler CFPThe surest road to financial success and independence is a long one. That path includes working hard at a career you enjoy, living on less than you earn, taking educated and appropriate risks, and building wealth gradually through diversified investing.

The American Dream

I know many people who have followed this route successfully. Their achievement—what has long been described as the American Dream—should be something to be proud of.

The Associated Press

Apparently, in today’s world, that isn’t the case. At least not according to an Associated Press news article published in the Rapid City Journal on December 9, 2013. The headline was straightforward enough: “Rising riches: 1 in 5 in US reaches affluence.” The article stated that 20% of Americans will have household incomes of $250,000 or more at some point in their lives. This includes those with high incomes for only one year or a few years. During those periods of affluence, they are in the top 2% of earners.

AP Inaccuracies and Assumptions

Beyond that, the piece was filled with inaccuracies and assumptions.

First, its writers confused “affluence” and “wealth.” Someone with a high income in a given year is affluent. Anyone with a basic grasp of finance, however, understands that wealth is associated with net worth. When only 2% of Americans have a net worth of $1 million or more, 20% can’t be accurately described as wealthy.

A One Time Affluent Deal

Some high earners are two-income couples, or professionals like physicians, at the peak of their careers. For others, affluence is a one-time deal.

Consider this example: A couple in their 50’s have always earned around $40,000 a year (adjusted for inflation). The husband inherits a $250,000 IRA from his parents. The couple decides to distribute the money in the IRA, pay the income taxes, and use the balance to pay off their mortgage. For that one year only, their income exceeds $250,000. That certainly isn’t enough to earn the label of “new rich.”

The article notes these “new rich” tend to be “much more fiscally conservative” than other Americans and “less likely to support public programs, such as food stamps or early public education to help the disadvantaged.” This makes anyone who ever receives over $250,000 in any one year look like Ebenezer Scrooge before his transformation. but it is true.

Windfalls

Ask anyone, no matter how liberal, who received a windfall in 2013 and watched 25% to 50% of it disappear to federal and state income taxes, whether they are happy about this income redistribution.

The AP also notes the number of people reporting income of over $250,000 doubled since 1979, leaving the impression that the rich are getting richer while the poor are getting poorer. While this is technically correct, the figures are meaningless because they are not adjusted for inflation.

cropped-header.jpg

Accenture’s Institute for High Performance and Research

The article also cites Paul F. Nunes of Accenture’s Institute for High Performance and Research, in support of its contention that those who are newly or temporarily affluent aren’t spending enough. Their “capacity to spend more will be important to a U.S. economic recovery.” Instead, they “spend just 60 percent of their before-tax income, often setting the rest aside for retirement or investing.”

Taking Care of Business

In other words, these successful Americans are doing exactly what the American Dream says they should do. They are taking care of themselves and planning for the future by working to build their short-term affluence into lasting wealth and financial independence.

Assessment

For this, they should be applauded. It would be more helpful to our country, economically and socially, to see them as role models rather than part of the problem. Instead of trying to bring successful people down, we would achieve more by using their example to lift others up.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

ACOs and Marketplace Competition

Join Our Mailing List

An Estimation of Material Impact

By www.MCOL.com

ACOs

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

On Items NOT Purchased in the Sale of a Medical Practice

Join Our Mailing List

Excluded – Not Included – Items

By Dr. Charles F. Fenton III JD

fentonMuch is written about the sale of a medical practice: price, taxes, terms, loans, negotiations and FMV etc; especially on this ME-P by Editor Dr. Dave Marcinko and his team. Excellent thoughts, all! But, little is written about items not purchased.

So, here is a different perspective.

Excluded Items

Items not purchased or “excluded items” often list the personal items of the parties – or of the employees of the parties. Such items would often include:

  1. All cash on hand or on deposit;
  2. All accounts receivable generated prior to the closing date;
  3. All prepaid expenses, utility deposits, tax rebates, insurance claims, credits due from suppliers and other allowances after Closing Date;
  4. The personal effects, including but not limited to; photographs, diplomas, uniforms, books, mementos, memorabilia, personally owned art objects and any other personal property owned by them;
  5. Life insurance, disability insurance, and disability buy-out insurance on seller;
  6. Motor vehicles used in connection with the practice;
  7. Any and all tangible and intangible assets used in conjunction with another practice of seller; and
  8. All other assets owned by seller other than those specifically described as items purchased.

ME-P medical malpractice education

Assessment

The exact items transferred will often depend upon the prior negotiations of the parties.

For example, the parties may have agreed that the accounts receivable will be transferred with the practice. In such an instance, the accounts receivable will be listed as an item to be purchased.

MORE:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

Are FAs a Wise Investment?

Join Our Mailing List 

Ask-the-Advisor

Dear Dr. David Edward Marcinko,

Dr. MarcinkoAre financial advisors a wise investment? Mine charges me 1% each year for all my assets under their management. Is it worth it?

—Allen

It is hard to know for sure. But the fact that many financial advisers have different hidden fees suggests to me that they themselves don’t think that people would pay if they charged for their services in a clear and upfront way.

Re-Frame

To help you think about this question in your own life, let’s contrast two cases: In case one, you are charged 1% of your assets under management, and this amount is taken directly from your brokerage account once a month. In case two, you pay the same overall amount, but you send a monthly check to your financial adviser.

Consider

The second case more directly and clearly depicts the cost of your financial adviser, providing a better frame for your question. So, put yourself in the mindset of the second case, and ask yourself if you would pay directly for these services.

I think the best answer, according to colleague and economist Dan Ariely PhD, can be expressed in this manner.

If the answer is yes, keep your financial adviser; if the answer is no, you have your first action plan for the New Year.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

My Experience with ObamaCare

Join Our Mailing List 

Not a Unique Story – to Date

Rick Kahler CFPBy Rick Kahler CFP® http://www.KahlerFinancial.com

Like millions of Americans, I jumped on Healthcare.gov on October 1 to view the long-anticipated plans on the insurance exchanges mandated by the Affordable Healthcare Act, known as Obamacare. I needed a new healthcare plan and purposely held off buying one in September to compare the coverage and prices of an Exchange plan.

My disappointment paralleled that of thousands of other Americans wanting to do the same. After six tries that day, I gave up. I tried the site multiple times for each of the next six days. No luck.

The Short Form

Finally, on the seventh day, the site actually let me start an application. I chose to go with the “short” form since I was certain I would not qualify for a subsidy.

The short form application took 30 minutes to fill out. There were very few questions about health, just whether anyone in the household smoked. A number of questions had me wondering if I was applying for a passport. These included my Social Security number, race, citizenship, relationships to everyone in the family, and whether I was ever incarcerated.

When I reached the end of the form, I hit “submit,” anticipating that plan options and costs would appear. Instead, I was sent back to the starting page of the form. After 60 minutes of trying to get out of this endless loop, I gave up.

Three More Weeks of Trying

For the next three weeks, I went to the site at least once a day. I was never able to get past the endless loop to view plans or prices. I took a two-week break.

On November 14, I tried again. Success! Well, sort of. No endless loop. Instead, the site said it lost my original application and I needed to complete a new one. After another 60 minutes filling out the application, I ended up stuck in a loop again, unable to view plans or prices, much less choose one.

Giving Up

Frustrated, I decided to give it a rest until the site re-launched on December 1. I figured I would still have plenty of time to meet the December 15 deadline for enrollment.

On December 1, I eagerly popped onto the site. Not only was the site not functional, it had lost my application for the third time.

I gave up.

Enter the Insurance Broker

I phoned my insurance broker. She was able to give me all the information I had tried to get out of healthcare.gov for the past 60 days. She also said my insurance company was canceling my current plan. Obamacare deemed the coverage substandard because it did not cover pregnancy, mental health costs, and pediatric dental and vision costs. Although I don’t want or need any of that coverage, Obamacare gives me no choice.

Prices

My old policy cost $1,192 a month. The new one costs $1,506, which includes $59 a month in mandated surcharges on non-exchange policies to help fund Obamacare. My maximum family out-of-pocket expenses must also increase $208 a month. The total potential increase is a staggering $524 a month.

###

Obama Care

###

A Skeptic

As someone who listened with great skepticism as politician after politician promised that Obamacare would lower health care costs, lower our deficit, and guarantee we could keep any existing plan, I feel sadly vindicated. In March 2010, when Congress passed Obamacare, I paid $660 a month for health care that had better coverage than I have now. For that same coverage today, my premium would be $2,450 a month.

Assessment

Unfortunately, my story is not unique. It is ubiquitous to the average American who has health insurance. Our elected officials and government agencies failed us miserably. So far, there appears to be no relief in sight.

More

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Product Details

On Bull Markets under Democrats

Join Our Mailing List

A Political Discourse by Kevin Outterson

[By Staff Reporters]

The Dow hit an inflation adjusted record high this week (WSJ). Here is the (unadjusted) S&P since 1975 with Republican administrations in red and Democrats in blue.

chart

Before you jump to partisan conclusions, last month, Tyler Cowan reviewed the Blinder and Watson paper on why Democrats preside over superior economic performance (their conclusion: mostly good luck).

Source: Bull markets under Democrats

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

The Business of Christmas 2013

X-Mass Illustrated

Join Our Mailing List 

XMass

With Christmas today, we thought it would be fun to post an infographic on the business of Christmas.

From the explosive growth of online shopping to the top selling Christmas gifts of different decades, we’ve got it covered.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details