
Don’t Tread on Me – Obama

Join Our Mailing List

Bite Me – CMS

[By D. Kellus Pruitt; DDS]pruitt

Shy but proud Texas Dental Association leaders still direct employees to encourage members to volunteer for permanent, mandated National Provider Identifier numbers. Why? “Just ‘cause.”

As part of an agreement the TDA made with the state to help politicians out of a lawsuit they brought upon themselves for not providing adequate dental care for the poor in the state, TDA leaders followed someone’s bad advice to encourage Texas dentists to accept CHIP (Medicaid) – which requires dentists to have arbitrary 10 digit NPI numbers to participate.

Don’t get me wrong. I have the highest respect for dentists who treat the poor for pay that doesn’t even cover overhead. That is compassion to a fault – even before CMS investigators arrive with subpoenas based on vague, nuisance complaints from disappointed patients, disgruntled employees and hungry competitors. Getting even with rich, greedy, or otherwise mouthy dentists has never been easier because I’ve heard that CMS intends to investigate all complaints.

Yes, low pay is only part of the nasty package that TDA officials are officially discouraged from discussing with membership – even as they beg for us to sign up for CHIP and “do our part to return our debt to society by helping those who cannot care for themselves.” So who would dare question the reason for the faux sentiment expressed by a long string of TDA Presidents? That would be me.

There are simply so many other charitable ways of publicly and privately returning help to the community that don’t add to the risk of donating one’s skill. Even if one does not help local free clinics, how hard can it be to quietly give away care, Doc, in these hard times? It’s just between you and God anyway, isn’t it? One simply enters N/C in the fee column. Confidentially I sometimes get hugs that so far can be neither controlled nor taxed.

It appears to me that CMS is arguably more influential with TDA leaders than common TDA members like me. If I am correct, this means that dentistry is at risk of being overrun by authoritarian bureaucrats hired by ambitious politicians who often promise more than they can deliver before ducking accountability for earthly bad decisions. The business model even reminds me of the TDA’s.

So now that the TDA played its hand with regard to its fondness for BCBSTX and the NPI number, what does it mean for Texas dentists if Obama’s imminent “Public Plan Option” turns into “Medicaid for All” – as some naively hope and others justifiably fear? This week, the AMA gave its support to the Public Option. Will the ADA be next? 

Dentistry unhurried is value-added service. One cannot get rich at it, but it’s an honorable living.

Regardless of whether you approve of my tactless vitriol or not, I have to say that when it comes down to feeding my family, even this special bastard could be silenced if there is no longer a market on the east side of Fort Worth for dentistry unhurried. Especially if it meant a monthly visit by CMS inspectors like Dr. Annie Bukacek is going through right now. Like me, she also gives her patients the time they deserve. But unlike me, she doesn’t have time to pick fights with shy bullies who hide behind employees.

I’ll get to the physician’s story in a moment. But first, just how important are secrets to the leaders of the nation’s preeminent non-profit dental organization? It’s important enough that many in the ADA House of Delegates want the power to mete out punishment to fellow officers who cannot keep their mouths shut. Some of those we elected even want to make the sanctions retroactive to deal with colleagues who have already broken the traditional unwritten good ol’ boy code of stoic conduct. At the same time, the TDA is begging dentists in the state to run for ADA office – starting on the local level. Why do you think dentists in Texas don’t want to get involved? Nobody accepts delivery from the cluetrain in Austin. It probably stops there at least a couple of times each week day.

I copied below three of the ADA Delegates’ referred resolutions from Judy Jakush’s November 2 ADANews article, “Delegates vote on Association business matters,”

http://www.ada.org/prof/resources/pubs/adanews/adanewsarticle.asp?articleid=3821

1] Res. 70 states that if any member of the ADA, including delegation member, council, committee or task force member, or Board of Trustees member has been acknowledged as breaking the attorney-client privilege or executive session, that member is, at a minimum, barred from ever again participating in an attorney-client or executive session within the ADA. This shall include such acts which have been acknowledged as occurring prior to the enactment of this resolution.

2] Res. 67 would specify that candidates for elective or appointive officers may not have had any sanctions bestowed upon them by the Association. Also referred was Res. 67RC, which would direct that anyone found by the Committee on Credentials, Rules and Order to have violated his or her duties to the Association would be disqualified from holding elective or appointive office.

3] Res. 68 was referred to the Council on Ethics, Bylaws and Judicial Affairs for report to the 2010 House with recommendations for Bylaws changes. The proposal calls for CEBJA to review the Bylaws and craft language that would define the mechanism for sanctions up to and including removal from office of a delegation member or Board of Trustee member if there is found to be cause for removal as shall be defined. That cause, at a minimum, should include those causes as delineated currently for council members. Res. 68 also calls for a method for fair and impartial hearings to be recommended and the establishment of an authorized House committee that can be held on an ad interim basis between annual sessions of the House of Delegates with authority to determine and impose any such sanctions deemed appropriate. 

Remember, the ADA is a non-profit, professional organization whose only purpose for existence is to serve dental patients through dentist members who support it with dues. When one reads these and other resolutions in Jakush’s article, it looks like ADA President Dr. Ron Tankersley is running the Pentagon. We’re only dentists for crying out loud!

Dr. Annie Bukacek’s 6-month battle with CMS

This morning I read what has turned out to be a popular article titled “Investigators descend on doctor,” written by Candace Chase, writing for the Daily Inter Lake which serves northwest Montana.

http://www.dailyinterlake.com/news/local_montana/article_d8cde54e-cc2d-11de-9ddd-001cc4c03286.html

“Dr. Annie Bukacek of Hosanna Health Care in Kalispell was surprised when a 30- to 40-foot-long command-post vehicle pulled up unannounced last week, along with a posse of state and federal health-care fraud investigators.”

“Bukacek points out that anyone – a disgruntled ex-employee or patient or someone who doesn’t like a physician’s looks or politics – could trigger an investigation and cost a physician as well as the government thousands of dollars.” 

I wonder what would happen if a dentist openly taunts CMS leaders? As I previously mentioned, it is Dr. Bukacek who claims, “They said they have to followup every allegation made.” 

When all American dentists are required to volunteer for NPI numbers and can no longer be legally paid in cash at the time of service, we’ll all be hung by an ADA-approved mistake of historic proportions. I suggest that ADA members take time right now to jot down names so that when judgment day inevitably arrives, one will be prepared to hold accountable the ADA employees who recommended the numbers. After reading how ADA leaders are hunkering down, it looks like going through employees will probably be the only way to touch the bosses they bravely try to shield.

Oh yeah. I posted the 5th of almost 30 comments that so far follow Candace Chase’s provocative article:

“Dr. Annie Bukacek’s experience is why as a US citizen in the land of the free, I simply refuse to do business with the US government. Bite me, CMS. Did you hear me? I said bite me!”

Assessment

It’s not likely that I’ll regret those words because I am powerless to stop myself from typing them anyway.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

When to Change Portfolio Managers

Some Considerations for Medical Professionalsfp-book

By Clifton N. McIntire, Jr.; CIMA, CFP®

By Lisa Ellen McIntire; CIMA, CFP®

Sometimes even the best made physician financial plans just don’t work out. And, despite extensive time and energy spent on due diligence before hiring an investment or portfolio manager, it becomes evident that you must change managers.

Some Thoughts for Doctors

Here are a few thoughts when considering a portfolio manager change:

  • You should have initially hired the manager with a long-term relationship in mind. Realizing that styles go in and out of favor, we were not simply buying last quarter’s best numbers; in 2009.
  • Market statistics often mask “real” performance of money managers, both good and bad. The S&P 500’s 2007 performance can be attributed to a few very large companies.
  • Generally, a full market cycle would be required to assess money manager performance. Having said that, what could happen that would warrant changing managers? Here is a brief list:
  1. Style Drift: You have a growth manager and when growth stocks turn down, you begin to see the purchase of “value” stocks.
  2. Not Sticking to Previously Established Disciplines: If the process is to sell if the price declines 20 percent down from the original buy range and now they are holding because, “This time, it is different.”
  3. Personnel Changes: New analysts are hired with a different philosophy. Recent transactions seem 180 degrees off course.
  4. Principals Leave: Like professional sports figures, good money managers are in demand and sometimes change firms. The replacement may be a 29-year-old MBA with little experience.
  5. The Firm is Sold: This may be good new if it broadens ownership and helps retain good people.  Look for long-term incentive driven “staying” bonus plans.
  6. Loss of Major Accounts: Reduced revenues may force cut backs in personnel and services. Attention may shift from portfolio management to marketing.

Assessment

Finally, sometimes it is just not working. Misjudgments in asset allocation and poor stock selection over a reasonable period of time can be reason enough to change managers.

Join Our Mailing List

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

More Health 2.0 Technologies

Become Privy to Some New Product Launchs

By Staff Reporters

Visit the virtual Health 2.0 Conference Exhibit Hall of piooner blogger Matthew Holt www.Health2con.com,  or click-on each individual product launch where you’ll see the introduction of  brand new technologies from the following vendors:

Disclaimer

The ME-P has no relationship with these products or vendors.

Join Our Mailing List

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. If you’ve ever used, seen or tried these products or services, do tell us what you think!

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Remembering the IOM Medical Quality Report

Join Our Mailing List

Despite the IOM Warning, Medical Errors May Have Killed 1 Million Plus In Past Decade

[By Fard Johnmar: First posted May 20, 2009]

IOM Report

Much like remembering the fallen Berlin Wall, it is fitting during this time of political healthcare reform debate, to again consider the IOM report – now more than a decade old.

In a scathing report, Consumers Union estimates that more than 1 million people have died over the last decade due to preventable medical harm.  The newly released report, “To Err is Human — To Delay is Deadly,” suggests that since the Institute of Medicine’s influential 1999 report on medical errors, “98,000 people die each year needlessly because of preventable medical harm, including healthcare-acquired infections. Ten years after To Err is Human, we have no national entity comprehensively tracking patient safety events or progress.”

While some hospitals have made great strides in the effort to reduce medical errors and the U.S. government has taken steps to limit reimbursement for preventable medical events, the nation still has a long way to go.  Consumers Union is recommending that we develop a national system for tracking medical errors.  The organization suggests that concerns about malpractice lawsuits due to reports of medical harm may be overstated.

Assessment

To learn more about the Consumer Union report, please click here.

Channel Surfing

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you . You can unsubscribe at any time. Security is assured.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:


About Carena In-Home Medical Care

In-Home Medical Care Services for the Modern Era

By Dr. David Edward Marcinko; MBA, CMP™

[Publisher-in-Chief]Dr. David E. Marcinko MBA

We have written about the high cost, questionable quality and scheduling burden of emergency room visits on the Medical Executive-Post before. And, for some non-emergency or after-hours needs, the ER may possibly be one of the worst places to deliver medical care.   

Enter Carena, Inc

Seattle-based Carena Inc. was founded in 2000 on the principle that expanding access to medical care improves outcomes and reduces costs. By providing around-the-clock medical care and education at a patient-identified time of need, Carena patients, clients and health plans are reported to experience lower costs while patients receive the right care – at the right time [www.CarenaMD.com].

A New [Old] Business Model

Carena is not an emergency room, not an urgent care center and not someplace patients go. This medical group delivers 24/7 house-calls both to render care and provide education for urgent medical needs.

House calls last as long as needed—often an hour—to make sure patients have the care and education needed to take control of their health.

The Carena model also offers medical care at the workplace enabling corporate clients to offer on-site care without the cost and space requirements of a typical employer-sponsored health clinic.

Home Visits in the Modern Era

Carena medical group physicians treat a wide range of urgent concerns. They carry an updated version of the traditional “doctor bag” filled with state-of-the art and portable instruments. For example, physicians have the equipment to suture minor cuts, deliver nebulizer treatments for asthma, or obtain lab samples. They run in-home rapid diagnostic tests for influenza, strep throat, and other medical issues. If X-rays or tests are needed, physicians coordinate scheduling and share results with patient PCPs. Electronic medical records are used throughout.

Always Open 24/7

Carena is always open. No waiting in the ER while doctors treat true emergencies. No wondering if other waiting patients are contagious.  

Reduced Financial Shock.

Carena house calls are reported to costs about 30-35 percent less than a typical emergency room visit of about $1,500.

Another New Term

With apologies to my esteemed colleague Robert M. Wachter MD, the hospitalist guru at UCFS, Carena doctors are often called “housepitlists.”  

Assessment

Carena is a medical company that provides a new model of health care delivery for innovative, self-insured companies. Internist Frances Gough MD is the Vice President of Product Development at Carena, Ted Conklin MD is the founder and Ralph C. Derrickson is President and CEO. Corporate clients for both Carena business models are Costco and the Microsoft Corporation of Redmond, WA.

Disclaimer

I own shares of MSFT common stock and am a professional member of MS-HUG.

Join Our Mailing List

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Spotlight on the “Health Tech Today” Video Launch

Video Clip from Microsoft

By Staff ReportersConnected Doctor Health 2.0

Health Tech Today is a new monthly, on-line video series at the intersection of health and information technology.  The show premiers November 10th 2009, but you can view a video trailer of their first show on the link below, right now

HealthBog

HealthBlog includes thoughts, comments, news, and reflections about healthcare IT from Microsoft’s worldwide health senior director Bill Crounse MD, on how information technology can improve healthcare delivery and services around the world.

Link: http://blogs.msdn.com/healthblog/default.aspx

Assessment

Please help them spread the word. Blog about it. Tweet your friends. Post information about Health Tech Today on Facebook.  Health IT has a new voice. We think you’ll like what you see.

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. So, give em’ a click and tell us what you think! Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Our Newest ME-P Milestone

Growing and Thriving – Thanks to You!

By Ann Miller; RN, MHA

[Executive Director]Congratulations

This month we passed the 145,000 reader mark. As you know, the ME-P was launched in 2007 and initially reached about a thousand Internet pioneers. It has grown exponentially, from our initial list-serve, to more than one hundred thousand readers and subscribers today.

A Thriving Community

The ME-P is now a thriving online and onground community that connects physicians with financial advisors and management consultants.

Our goal in the modern Health 2.0 era is to: “bridge the gap between medical mission and profit margin.”

Since inception, we have become one of the most popular and influential electronic networks in the healthcare administration, economics and financial planning space. 

Assessment

ME-P would like to thank all of our devoted readers, zealot subscribers, authors and participants as well as our advertisers for making this publication possible:

Channel Surfing

Join Our Mailing List

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. 

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Get our Widget: Get this widget!

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

A New Remote Patient Monitoring Device

Join Our Mailing List

The Next Step in RPM Solutions  

[By Staff Reporters]Tele Doctor

Long-term medical conditions create many challenges—for patients who have them, as well as for their attending physicians. This gadget reports to address those challenges

What it Is

The Intel® Health Guide is a comprehensive, next-generation remote patient monitoring (RPM) solution that combines an in-home patient device [the Intel Health Guide PHS6000] with the Intel® Health Care Management Suite; an online interface that allows clinicians to monitor patients and remotely manage care.

Reported Benefits

The benefits of the Intel Health Guide include patients who feel empowered to take a more active and positive role in their own care. For doctors, it enables more informed and personalized care—which may lead to better patient satisfaction. And it helps healthcare organizations to face the challenges of chronic care, increase efficiency, and achieve organizational objectives.

Assessment

In short, Intel® technology hopes to fulfill the promise of RPM, where interactive, data-rich telehealth helps to create timely, personalized and cost-effective care.

Disclaimer

The Intel® Health Guide requires an internet connection to enable communications with the patient’s care team and back-end data hosting. The Intel Health Guide is intended for use by patients under the guidance of a healthcare professional and is not intended for emergency medical communications or real-time patient monitoring.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

  Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

***

Update on HIPAA Administrative Simplification

New Enforcement Rules

Federal Register: October 30, 2009 [Volume 74, Number 209]

Rules and Regulations – Page 56123-56131

From the Federal Register Online via GPO Access [wais.access.gpo.gov]

DOCID: fr30oc09-12typewriter

DEPARTMENT OF HEALTH AND HUMAN SERVICES

Office of the Secretary

45 CFR Part-160 [RIN 0991-AB55]

HIPAA Administrative Simplification: Enforcement

AGENCY: Office of the Secretary, HHS.

ACTION: Interim final rule; request for comments

SUMMARY:

The Secretary of the Department of Health and Human Services (HHS) adopts this interim final rule to conform the enforcement regulations promulgated under the Health Insurance Portability and

Accountability Act of 1996 (HIPAA) to the effective statutory revisions made pursuant to the Health Information Technology for Economic and Clinical Health Act (the HITECH Act), which was enacted as part of the American Recovery and Reinvestment Act of 2009 (ARRA).

More specifically, this interim final rule amends HIPAA’s enforcement regulations, as they relate to the imposition of civil money penalties, to incorporate the HITECH Act’s categories of violations, tiered ranges of civil money penalty amounts, and revised limitations on the Secretary’s authority to impose civil money penalties for established violations of HIPAA’s Administrative Simplification rules (HIPAA rules). This interim final rule does not make amendments with respect to those enforcement provisions of the HITECH Act that are not yet effective under the applicable statutory provisions. Such amendments will be subject to forthcoming rulemaking(s).

Assessment

Join Our Mailing List

Link: http://edocket.access.gpo.gov/2009/E9-26203.htm

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct Details

RFID versus WiFi Hospital Inventory Tracking Systems

Understanding Competing Wireless Technologies

By Davd Piasecki, with

Hope Hetico; RN, MHA

www.HealthcareFinancials.comHOFMS

The two wireless technologies currently competing to provide hospitals with better systems for managing equipment inventories are (WiFi) and active RFID.

Wireless-Fidelity [WiFi]

WiFi is the name of the popular wireless networking technology that uses radio waves to provide wireless high-speed Internet connections. The WiFi Alliance is the non-profit organization that owns WiFi (registered trademark) and the term specifically defines WiFi as any “wireless local area network products that are based on the Institute of Electrical and Electronics Engineers’s 802.11 standards.”  Yet, less than 5 percent of North American healthcare facilities are equipped with these real-time locating systems, so the market is currently up for grabs.

WiFi Pros

The advantage of WiFi-based real time locating systems (RTLSs) is that most hospitals already have WiFi networks in place, and many medical devices are equipped with WiFi functionality. Moreover, WiFi vendors such as Aeroscout, Ekahau, and PanGo market their products based on a standards-based non-proprietary functionality. The downside of WiFi systems is that hospitals will need to install additional access points to bring the needed functionality to existing networks.

RFID Pros

On the other hand, RFID vendors such as RF Code and Radianse point to the wide application of RFID for asset tracking, and to the technology’s longevity in the industry. Still, RFID tags remain suspect because their ability to efficiently track DME may not be private or secure. Increasingly, WiFi seems more ubiquitous than RFID.

Finally, of the three WiFi major vendors, only Ekahau makes a point of stressing that its inventory system is based only on WiFi and not RFID, so the issue isn’t clear cut.  Perhaps it will take both technologies to deploy RTLSs for hospitals.

General Recommendations

As a general recommendation, RFID is not yet practical for most small to mid-sized healthcare entities or medical clinics looking to automate their inventory-related transactions (though it does work for other applications such as with returnable containers and asset tracking).

RFID Hype

Despite the hype over RFID, bar codes are not becoming obsolete and are still very effective at quickly and accurately identifying products, locations, and documents. Unless there exists an application where bar codes simply don’t work, or where RFID offers a significant advantage over bar codes, use bar codes. Even if an application that cries out for RFID exists, hospital material management administrators may want to consider waiting (if possible) as the cost of the technology comes down.

Both RFID and WFI Needed

According to Robert M. Wachter MD, Professor and Chief of the Division of Hospital Medicine and Associate Chairman of Department of Medicine, and Lynne and Marc Benioff Endowed Chair in Hospital Medicine, University of California at San Francisco, and Chief of the Medical Service at UCSF Medical Center [personal communication], both should be used.

Ultimately, of course, we do need both bar coding and RFIDs, and we need rigorous studies looking at what works and what doesn’t. But, you have to start somewhere. Even though the evidence continues to trail, based on what I know today, if I was a hospital ready to get into the IT game, I’d go with bar coding first. 

Assessment

Join Our Mailing List

In the next few years, standards will be finalized, hardware prices will drop, software will become more readily available, and, more importantly, the bugs will be worked out of all these systems.   

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

How to Search the ME-P?

Efficient Information Seeking

By Ann Miller; RN, MHA

[Executive Director]ME-P Consulting

A simple query that demands a cogent answer!

First Explore our Archives

Let’s say that you’ve reached the ME-P archives. Use this feature to explore articles on a monthly basis; since inception in 2007. To surf through the current month, click the first entry on the list and start reading. If you want something specific, try searching by channel topic category.

Then Try Topical Channel Categories

Through the channel category menu you can explore posts on a topical basis; there are more than 50 of them. And if you’re looking for something really specific, try using the search button on the top-right of the home page.

Assessment

Join Our Mailing List

To encourage ME-P users to participate in the ongoing community discussion, we’ve left commenting enabled, so feel free to speak your mind and leave all the comments you like! We are lightly moderated however, to prevent that annoying spam.  

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

ADA Opens a Facebook

Join Our Mailing List

Perhaps too Early?

[By Darrell K. Pruitt; DDS]pruitt

Something strange has happened to www.DentalBlogs.com I think they have partially shut down their Facebook account. They no longer feature original articles such as those by Dr. Rhonda Savage and Ms. Linda Miles, and in the last couple of weeks, they eliminated their collection of photos. Now the site only features ads and press releases. Does anyone else wonder what happened? Sure you do! This is exciting.

Perhaps Re-Tooling 

Unless they are just re-tooling this weekend, I suspect that since their previous format was biased heavily in favor of advertising dollars in a tough economy, their funding simply dried up. Like so many other advertising-related careers, the dinosaur found it couldn’t compete in a 2.0 market.  Nevertheless, today I did learn something important from the DentalBlogs Wall: The ADA has opened a Facebook account.

http://www.facebook.com/home.php#/pages/American-Dental-Association/32252997166?ref=mf

Such transparency is inspirational

When I announced this news on Twitter a few hours ago (“Proots”), neither the ADA nor the TDA had yet told membership. Yea, I scooped them on their in-house news. It happens all the time.  Naturally, I became a fan of the ADA Facebook. When I joined, there were already 1205 fans, even though the site is yet operational. I found that intriguing because it usually takes a long time for most FBs to attain 1200 fans – especially when all one can gather is the mission statement of the ADA’s newest Internet site.

My View 

Here’s what I see: About the time DentalBlogs laid off employees from their fully active Facebook, the ADA opened theirs (Gasp)! The ADA was well known to DentalBlogs because the ADA once advertised with them regularly. That is where I found an article about the ADA-approved CareCredit/GE that ended up causing problems for some people and entertainment for others. Let’s face it, friends. I just know that I’m not the only dentist in the nation with at least two burning questions. I bet at least 4 others are wondering who were the first seven fans to sign up for the ADA Facebook and Has Kim Volk, CEO of DDPA signed up yet?

Because the number of fans is rapidly piling up, such information from a few weeks (?) ago could soon be just too difficult to uncover from the fans list on the ADA site. It took a long time for me to scroll down through 1200 names – looking for those I recognize (Gasp)!

Scrolling Quickly, but Carelessly

I could have easily missed several easily recognizable names in contemporary dentistry, but as far as I can tell, not only was Delta Dental Plans Association CEO Kim E. Volk’s name not present in the list of 1200 fans, but there were very few names I recognized … and I’m sorry if I insulted anyone. I also did not see “Ron Tankersley” and other ADA officials’ names on the fans list. Didn’t the ADA try partial transparency like this once before? I may be wrong, but I think I played a role in shutting it down a few years ago with my persistent and still unanswered questions about the NPI number.

More Semi-Reliable Information

Here’s another bolus of semi-reliable information: I also quickly scrolled through DentalBlog’s list of 400 fans and did not notice an unusual amount of matches with the ADA Facebook fans list.

Those who dare to do so, might just ask, “So if the ADA fans didn’t come from dentalblogs, where did they come from?” I think one possibility is that the ADA effort has been in Beta and limited to a select group of people up until now. Doesn’t it seem strange that nobody is able to post anything? Did someone open the doors a few hours early? So who were the first 7 fans? No, you don’t have to scroll down to find out for yourself. I’ll tell you.

Who is John Hergert?

The first person to become a fan of the ADA Facebook account is named John Hergert from Chicago, Illinois.

2nd – Laurie Rich

3rd – Amy Lund

4th – Kelsey Majors

5th – Jessica Stevens

6th – Samantha Campbell

7th – Lina Kulkormi

I don’t recognize any of the seven, and I have not searched anyone’s name other than John Hergert’s – the first person to become a fan of the ADA Facebook. I found someone named John Hergert in Chicago, Illinois who is Associate Vice President at Lipman Hearne Inc. – an advertising agency.

http://www.spoke.com/info/p6JVgPy/JohnHERGERT.

Here is the bio of the person I only suspect is the first to become a fan of the ADA Facebook.

John Hergert’s Biography

John Hergert Associate Vice President John Hergert has a keen understanding of what it takes to capture and hold the attention of marketing audiences via innovative marketing techniques. Formerly Associate Director of Marketing Communications at DePaul University in Chicago, John works with both traditional and interactive media to design and implement marketing strategies that build a client’s image, increase support, and grow enrollment or attendance. John’s experience includes developing ROI-based marketing strategies for a variety of nonprofit and for-profit clients. Prior to DePaul, John was an account executive overseeing marketing and advertising strategy, web development, direct mail, print production, and promotional development for clients including Disney, Marconi, Owens Corning, and Reynolds. John began his marketing career while at the University of Wisconsin, where he was hired by a Los Angeles firm to implement cutting-edge marketing programs for Saturn and Trek Bicycle Corporation. John received his B.A. in Journalism from the University of Wisconsin and his Master of Science in Information Systems from DePaul University.”

Assessment 

What do you want to bet that the ADA Facebook is Mr. Hergert’s baby?

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Dictionary of Health Insurance and Managed Care


Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

Grading the Public Options That Already Exist

Understanding Existing Healthcare Plans

By Sabrina Shankman, www.ProPublica.org

October 28, 2009 12:27 pm EDT

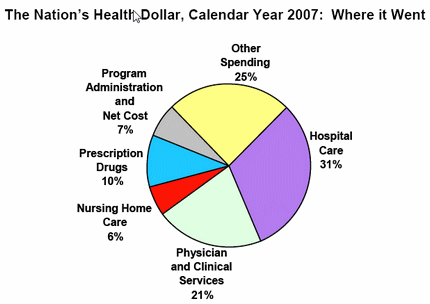
2007 Healthcare Costs

What might a public health option look like in practice? One way to find out is to look at what’s already out there.

Link: http://www.propublica.org/ion/health-care-reform/item/grading-the-public-options-that-already-exist-1028

Assessment

Join Our Mailing List

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Doctors versus Retail Bankers

Understanding Modern Reality

By Dr. David Edward Marcinko; MBA, CMP™

[Publisher-in-Chief]Dr. David E. Marcinko MBA

Doctors often carry notoriously heavy debt loads. Beyond the costs of a medical education are substantial costs for equipping, launching and staffing a practice. Technology changes fast these days and capital is required frequently. And, the era of eMRs, ARRA, HI-TECH and Obama-Care is upon us!

“I‘m a Banker – I’m Here to Help”

Unfortunately, retail bankers are now very conservative by nature; and the liquidity squeeze and financial meltdown of 2008-2009 makes credit even more difficult to obtain. It may be increasingly difficult to borrow money, especially since modern bankers know that a medical degree is no longer the guarantee of a steady and high income that it once was in the past. As more than one banker has often opined to me,

“We don’t usually loan money to doctors who really need it.”

Nevertheless, the more business a physician does with a bank, the better the terms that can be obtained; even thought hey may also not have a clue about what the practitioner can do to better compete in the managed care arena.

Why Big-Banks Hate Customers

http://articles.moneycentral.msn.com/Investing/JubaksJournal/why-big-banks-hate-banking.aspx

Local Community

Some bankers do have a good concept of local community politics however, for those not familiar with a practice venue. They frequently can provide references to more focused advisors, and bankers generally do not charge a fee for their advice. But, banks selling products are doing so according to their governing regulations as “prudent experts” under ERISA, and are not necessarily held to a fiduciary standard in any broader sense.

Join Our Mailing List

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Events Planner: November 2009

ADVERTISEMENT

Events-Planner: NOVEMBER 2009

Staff WritersME-P Events Planner

“Keeping track of important health economics and financial industry meetings, conferences and summits”

Welcome to this issue of the Medical Executive-Post and our Events-Planner. It contains the latest information on conferences, news, and relevant resources in healthcare finance, economics, research and development, business management, pharmaceutical pricing, and physician/entity reimbursement!  Watch for a new Events-Planner each month.

First, a little about us! The Medical Executive-Post is still a relative newcomer. But today, we have almost 25,000 visitors and readers each month from all over the country, in addition to our growing subscriber base. We have been a successful collaborative effort, thanks to your contributions.  As a result, we are adding new resources daily.  And, we hope the website continues to provide the best place to go for journals, books, conferences, educational resources, tools, and other things you need to establish the value your healthcare consulting and financial advisory intervention. And so, enjoy the Medical Executive-Post and our monthly Events-Planner with our compliments. 

A Look Ahead this Month

November 1: Print Edition Healthcare Journalism: If you would like to “step-up-your-game” and be considered as a peer-reviewed contributor to the third print edition of: The Business of Medical Practice [Health 2.0 Profit Maximizing Techniques for Savvy Doctors]; contact Ann at: MarcinkoAdvisors@msn.com. There are several chapter topics still available. Now, the important dates:

Nov 1-4: ASPPA Conference, National Harbor, Maryland.

Nov-5-6: Investment Decisions and Behavioral Finance, CFA Institute, Cambridge, MA.

Nov 16-17: Financial Behavior in Retirement, Source Media, Philadelphia, PA.

Nov 18: FINRA Small Firm Conference, San Francisco, CA

Please send in your meetings and dates for listing in the next issue of our ME-P Events-Planner.

MarcinkoAdvisors@msn.com

Join Our Mailing List

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest E-Ps delivered to your email box each morning? Just subscribe using the link below. It’s free. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Slide Show on the Social Life of Health Information

A Graphical Presentation

By Susannah Fox [Pew Institute]

First reported here:

Link: http://www.slideshare.net/PewInternet/trends-the-social-life-of-health-information-10262009

Channel SurfingIntegration

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. 

Please take a minute to visit.

And, to prevent that annoying spam, we ask that you join our mailing list and register. 

Join Our Mailing List

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Return on Investment Calculations for [Concierge] Medical Practice Marketing Initiatives

Calculating Tangible ROI for Intangible Activities

By DeeVee Devarakonda; MBA [Former CMO of Quaero, Inc]

By Dr. David Edward Marcinko; MBA [Publisher-in-Chief]Doctor with Advisor

Gone are the days when money was freely spent on medical practice marketing activities such as the yellow pages, radio or TV advertisements. And, today’s internet based business climate is especially harsh for ethereal programs that can not present a clear Return on Investment [ROI] for their existence. Concierge and cash-based medical practice marketing is especially vulnerable in this climate unless supported with a sound ROI argument.

The Challenge

A very basic challenge all medical practices is not only pooling the resources but also allocating them wisely. ROI arguments help practices make those choices. Typically marketing budget and outlay decisions focus on operating expenses like public relations, podcasts, webcasts and internet advertising. However, marketing can also involve capital investment decisions. To be successful, medical practitioners should learn to speak the language of business and build ROI analysis to support such initiatives.

How do you calculate the ROI for internet marketing initiatives?

Here are some basic steps to help you build the ROI scenario for your marketing initiatives:

  1. Detail the marketing costs:
  2. Estimate the revenue impacts:
  • Hardware – computers, servers, accessories
  • Software  – database, campaign management software
  • Implementation costs of hardware and/or software
  • Internal resource costs associated with the deployment of the capital improvement
  • Upfront investments in call centers, staff, equipment and so on.
  • Increase in patient response rates
  • Increase in patient conversion and practice acceptance rates
  • Increase cross-sell product and services ratios
  • Decreased account patient attrition rates
  • Increase in practice CM fees
  • Increase in average spend per patient/account
  • Increase in average number of patient transactions.

Practices can use past experiences to guesstimate the revenue impact; others like-minded colleagues.

Net Present Value

Once you calculate the revenue and cost impacts, you need to calculate the Net Present Value (NPV) of your marketing initiative. For a marketing project, if the NPV is greater than zero that means your project will make money; if it is less than zero – it will not (and you typically need a compelling business reason to implement a marketing project with an NPV less than zero).

NPV calculations include:

1) Investment – money you expend for the initiative at the beginning

2) Revenues – that accrue as a result of the initiative over a period – can be one time or a recurring revenue

3) Costs – that accrue as a result of the initiative over a period – can be one time or a recurring item

4) Discount rate – your accountant can give this rate.

5) Time Period – define the time period for which you would like to compute the NPV.

6) NPV is the cumulative differential between the revenue and cost stream discounted at the discounted rate minus the investment.

NPV=SUM ((Rt-Ct) / (1+r)t) – I

t=1

Given:

where t represents time, n  represents the number of time periods, R is revenue impacts, C is cost impacts, r is the discount rate and I is the Investment.

An NPV >0 means the project will pay for itself, <0 means the project does not pay for itself and an NPV of zero will give you a break even.

Assessment

Remember NPV is simply a guideline to help quantify the marketing results to make informed investment decisions. Note: NPV calculations that include assumptions also allow room for error. Spreadsheets help calculate the NPV for any initiative. Simple software can also help develop “what-if” scenarios with various values for NPV components and marketing options. The model can be used for non-marketing, or any initiative, as well.

Conclusion

Join Our Mailing List

And so, your thoughts and comments on this Medical Executive-Post are appreciated. How do you determine ROI for any medical practice initiative? Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
BLOG: www.MedicalExecutivePost.com


Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

Invite Dr. Marcinko

***

Take the Electronic Medical Records Survey

Discerning the Effects of ARRA and HI-TECH on eMR Adoption

By Ann Miller; RN, MHA

[Executive Director]Medical Chart

Hi Dr. Marcinko and ME-P Readers

I hope you and all readers are doing well.

As you know, this Friday marks the close of the first reporting period for Recovery Act funds. Any grants or loans awarded between February 17th (the signing of the bill) and September 30th 2009 will be reported in the survey.

Electronic Medical Records

I am eager to see the results because I want to know what effect the economic Stimulus Bill has had on eMR adoption rates. Are more doctors buying eMRs as a result of incentives? Or, has the bill simply reinvigorated research?

Take the Survey

I’m hosting a survey about this on our blog and I would love for you to participate. To be involved, just answer the question I’ve posted at:

http://www.softwareadvice.com/articles/medical/obamas-emr-stimulus-of-2009-creating-buyers-or-tire-kickers-1102709/

Assessment

I would also really appreciate your help in getting the word out about this survey. Would you mind posting a link back to the survey from your blog?

Thanks in advance for your participation!

Houston Neal
www.softwareadvice.com

Office: (512) 364-0117
Email: houston@softwareadvice.com

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details

Criticizing Electronic Medical Records?

By Brent A. Metfessel; MD, MS

By Staff Writers

www.HealthcareFinancials.comHOFMS

Despite ARRA and the HITECH initiatives, eMRs are not without drawbacks. And, with apologies to USCTO Aneesh Chopra, we list the following.   

List of Drawbacks

The following are some of the more notable negatives:

  • Operator dependenceThe term “garbage in, garbage out” applies to eMRs as well. The computer only works as well as the data it receives. If one is resistant to computing and works begrudgingly, is not well-trained, or is rushed for time, the potential exists for significantly incomplete or error-prone documentation.
  • Variable flexibility for unique needs — When one sees a single hospital, one sees just that — a single hospital, with unique needs unlike any other facility. A “one size fits all” approach misses the target. Even within a hospital, needs may change rapidly over time given the continued onslaught of external initiatives and measurement demands. Systems vary in flexibility and the ease with which they can customize options. More flexible systems exist but cost much more.
  • Data entry errors — Although data items normally only have to be entered once, data entry errors may still occur and be propagated throughout the system. Most notably, patient data can more easily be entered into the wrong chart when there is an error in chart selection. In general, simple double-checking and “sanity checks” in the system usually catch these errors, but if the error goes through the system the impact can be significant.
  • Lack of system integration — Interconnectivity of systems becomes more important with eMRs than with any other system. Personnel use the data in many different areas. If there are isolated departmental systems without connectivity, redundant data entry occur leading to confusion in the different departments. Appropriate and intelligent clinical decision support systems can make the job of the physician easier through education, real-time feedback, and through the presentation of choices that allow for clinical judgment.
  • Costs of implementation — Intelligently applied eMR implementations may also be cost saving; long term. For example, one large east coast hospital found that eMRs saved $9,000 to $19,000 annually per physician FTE. This savings was achieved through a decrease in costs for record retrieval, transcription, non-formulary drug ordering, and improvements in billing accuracy. And, in radiology, storage of digital pictures and the use of a picture archival and communication system significantly [PACS] decreased the turnaround time for radiology image interpretation — from 72 hours to only 1 hour. However, there is significant front-loading of costs prior to achieving such costs savings. 

Link: WSJ_Letter_3M_Company_2009-10-16

Assessment

At the American Health Information Management Association [AHIMA] October 2006 conference,  panelists suggested that developing, purchasing, and implementing an EMR would cost over $32,000 per physician, with an outlay of $1,200 per physician per month for maintenance.  This is larger in economic scope, today. Also, there exists no national standard that would require compatibility between the numerous competing eMR vendor systems that may need to communicate with each other, which can escalate costs and frustration in systems that attempt to integrate the features of multiple vendors.

Some recent HIT fiascos:

 Link: http://psnet.ahrq.gov/resource.aspx?resourceID=3090

 Link: http://psnet.ahrq.gov/resource.aspx?resourceID=1905

 Link: http://psnet.ahrq.gov/resource.aspx?resourceID=5286

 Link: http://psnet.ahrq.gov/resource.aspx?resourceID=3891

 http://sanfrancisco.bizjournals.com/sanfrancisco/stories/2009/10/12/newscolumn3.html#

Conclusion

Join Our Mailing List

And so, your thoughts and comments on this Medical Executive-Post are appreciated. What about CCHIT? Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Championing Electronic Medical Records?

By Brent A. Metfessel; MD, MS

By Staff Writers

www.HealthcareFinancials.comHOFMS

eMRs involve accessibility at the bedside either through bedside terminals, portable workstations, laptops, wireless tablets, and hand-held computers and personal digital assistants (PDAs), (e.g., 3ComtmPalm Pilot®). The inputs can either be uploaded into the main computer system after rounds or transmitted immediately to the system in the case of wireless technology. Bedside technology obviates the need to re-enter data from notes after rounds are complete. This improves recall and avoids redundancy in the work process, saving time that can instead be devoted to patient care. 

Usual eMR Features

Common features of an eMR include the following:

  • history and physical exam documentation, progress notes, and patient demographics;
  • medication and medication allergy information;
  • CPOEs and laboratory results;
  • graphical displays of medical imaging studies including X-rays, CT, and MRI;
  • ordering of drugs, diagnostic tests, and treatments, including decision support and drug interaction alerts;
  • clinical practice guidelines (evidence-based) to aid diagnostic and treatment decisions;
  • alerts that can be sent to patients reminding them of appointments and necessary preventive care;
  • scheduling of appointments;
  • processing of claims for payment; and
  • a GUI, which may include secure Web-based and wireless technologies that allows providers or other authorized healthcare personnel access to health information from remote sites, including outside offices and home.

Assessment

There are also other benefits, as well. For example, instead of calculating fluid balance off-line, the computer can perform calculations immediately, once again saving time and ensuring accurate values. Medication orders can also be entered in real-time, giving the provider the option to react to alerts at the bedside rather than waiting to load the orders into the system in “batch” mode.

Conclusion

Join Our Mailing List

And so, your thoughts and comments on this Medical Executive-Post are appreciated. What about “meaningful use”? Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

About Archimedes.com

A Mathematic Model of Human Disease?

By Staff Reporters

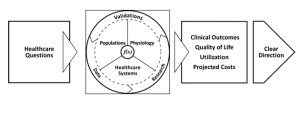
No, we don’t mean the classical scientist of antiquity.  Rather, Archimedes is an independent healthcare modeling organization located in San Francisco. Their core technology – the Archimedes Model – is a mathematical model of human physiology, diseases, interventions and healthcare systems. The Model is reportedly detailed, rigorously validated and made available for use by health plans, pharmaceutical companies, researchers, and other organizations to help understand and resolve vital clinical and administrative healthcare questions.

The ModelArchimedes-Model


Founders

Archimedes was founded by industry veterans David Eddy MD PhD, and Len Schlessinger PhD. 

Disease Entities

Currently the Model includes: 

  • Diabetes and complications
  • Coronary artery disease
  • Hypertension
  • Congestive heart failure
  • Stroke
  • Dyslipidemia
  • Obesity
  • Metabolic syndrome
  • Asthma
  • Colon cancer
  • Breast cancer
  • Lung cancer

Other conditions are continuously being added.

Assessment

By using advanced methods of mathematics, computing, and data systems, the Model strives to enable managers, administrators, and policymakers to be better informed and to make smarter decisions than has previously been possible. So, give em’ a click and tell us what you think?

Link: http://archimedesmodel.com/index.html

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

New-Wave ME-P Sponsorship Opportunities

Invest in the ME-P

By Ann Miller; RN, MHA

[Executive Director]Doctor-Business

Next year’s budgets are being planned now. Will your company receive a portion of your clients’ budget? Do you have the market presence to attract new clients? Or, to have your electronic message seen by the busy decision makers you want to influence? 

If so, our ME-P suite of solutions may right for you. 


Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise 

Advocacy

Reach out and impress more than 100,000 physician and nurse-executives, financial advisors, CEOs and medical management consultants in the Health 2.0 space. Our premium institutional e-journal: www.HealthcareFinancials.com and complimentary companion newsletter blog: www.HealthcareFinancials.wordpress.com has limited sponsorship and advertising opportunities available; So; be sure to act now! We advocate for your cause.

Advertise with us! Reserve your space today.HOFMS

For more information please contact:

Edward: MarcinkoAdvisors@msn.com

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements.

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Why America Spends More on Healthcare

A McKinsey Global Institute Review

By Nancy Chockley; PhD
President & CEO
NIHCM FoundationRed Cross

Path breaking work by the McKinsey Global Institute (MGI) shows that, relative to other peer countries from the Organization for Economic Cooperation and Development, the U.S. spends nearly $650 billion more on health care than would be expected after adjusting for cross-country differences in wealth.  Fully two-thirds of this added spending occurs in the outpatient sector. 

Out-Patient Services

The highly profitable nature of many outpatient services coupled with the incentives of a fee-for-service payment system are contributing to greater intensity of outpatient care and helping to fuel this spending.  In this essay, “Why America Spends More on Health Care,” Eric Jensen and Lenny Mendonca describe MGI’s work to examine all sectors of the American health care system and identify factors responsible for the higher-than-expected spending.  

More Examples

Other recent Expert Voices essays on health reform include:

Channel Surfing

Join Our Mailing List

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. 

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Current Milestones in Retirement Planning For Physicians

What if You Are Behind Your Target Goals?

By: Alexander M. Kimura; MBA, CFP®

By: Robert J. Greenberg; CFP®

By: Richard P. Moran; CFP®fp-book

The stock market has been in a terrible place for your money and retirement planning, since October 2007. Perhaps even the last decade or so for some physicians. But, if none of your assumptions have changed and you feel that you can make up the difference in the next year, you probably can use the same retirement cash flow plan. As a rule of thumb, if you’re less than 10 percent off of your goal, you may not need to do anything. This is rare in the investing climate today!

So, if you have fallen so far behind that each year’s target seems unachievable, you will probably need to make some changes. However, before you change your planning and investing, you need to see why you’re behind.

Examine Expenses

If you haven’t saved as much as you expected, take a look at your expenses [personal and office] and see where you can cut down. Remember, you need to pay yourself first before you spend on luxuries. Contribute as much as possible to your qualified retirement plan at work, too.

Examine Returns

Next, you need to look at your investment returns. Since the stock market has been in one of its inevitable “corrections” for several years, this can significantly impact your balances. Remember, your return assumptions are based on averages that should include the bad and good years. If you’re close to retirement and have a large shortfall, then you may need to increase the risk in your investment portfolio in order to meet your goals. If the market falls more, or stays down for some time, increasing risk by buying more stocks forces you to “buy low” which should pay off over time.

Assessment

Join Our Mailing List

As a doctor, you can always delay retirement and work a few more years. Fortunately, medicine is one profession where experience earns an economic premium.

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. How will you make up any retirement shortfall? Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

About the HelloHealth.com Primary Care Business Platform

Connecting Doctors and Patients

By Staff Reportersbody

Hello Health is a platform for improving the way primary care practices do business. The platform includes a significant level of support such as online access to the Hello Health practitioner community, offline and online training and continuing education.

What it is – How it works

With Hello Health, doctors can set up their own Hello Health “storefront,” and use their online web-based platform to see local patients in the office and online, communicate, document, and receive payments from them [www.HelloHealth.com].

According to its’ website, Hello Health helps primary care doctors to:

  • Sell professional services. Simply apply for a practice.
  • Be Web-Based and Mobile. Like the rest of the world— anytime, anywhere.
  • Keep track of a medical practice. Manage visits and appointments.
  • Communicate in the 21st Century. Email, IM, and video chat with patients.
  • Document quickly and easily. Record in-person and online interactions.
  • Connect with medical colleagues. Communicate, share wisdom, and collaborate.
  • Get paid hassle-free. Patients pay doctors with their credit card on file.

Founder by noted physician blogger Jay Parkinson MD, MPH, the Hello Health platform was built from the ground up to help doctors do what they do best— form relationships and practice real medicine [http://blog.jayparkinsonmd.com]. Jay says,

“It’s practicing medicine using today’s technology and today’s communication – and getting paid for communicating with your patients whether it’s in your office or using email, IM, or video chats within hellohealth.com.”

A companion educational service is run by L. Gordon Moore, MD of Hello Health University.

Join Our Mailing List

Here is a slideshow from the Feast Conference and EfficientMD.com

http://efficientmd.blogspot.com/2009/10/dr-jay-parkinsons-slides-from-feast.html

Assessment

There is also a platform for patients to help them connect with Hello Health physicians online or on-ground.

Conclusion

And so, thoughts and comments from Hello Health doctors and patients are appreciated. Give em’ a click and tell us what you think [www.HelloHealth.com]?

Channel Surfing

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. 

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

When Investing or Stock Trading Is No Longer Fun

Understanding Obsessive-Compulsive Behavior

By: Dr. David Edward Marcinko; FACFAS, MBA, CMP™

By: Dr. Eugene Schmuckler; MBA, CTS

By: Dr. Kenneth H. Shubin-Stein, CFA

By: Richard B. Wagner; JD, CFP®fp-book1

An obsession is a persistent, recurring preoccupation with an idea or thought. A compulsion is an impulse that is experienced as irresistible. Obsessive-compulsive individuals feel compelled to think thoughts that they say they do not want to think or to carry out actions that they say are against their will. These individuals usually realize that their behavior is irrational, but it is beyond their control. In general, these individuals are preoccupied with orderliness, perfectionism, and mental and interpersonal control, at the expense of flexibility, openness, and efficiency.

Specifically, behaviors such as the following may be seen:

  • Preoccupation with details.
  • Perfectionism that interferes with task completion.
  • Excessive devotion to work and office productivity.
  • Scrupulous and inflexible about morality (not accounted for by cultural or religious identification).
  • Inability to discard worn-out or worthless objects without sentimental value.
  • Reluctance to delegate tasks or to work with others.
  • Adopts a miserly spending style toward both self and others.
  • Demonstrates a rigid, inflexible and stubborn nature.

Most people resort to some minor obsessive-compulsive patterns under severe pressure or when trying to achieve goals that they consider critically important. In fact, many individuals refer to this as superstitious behavior. The study habits required for medical students entail a good deal of compulsive behavior.

Related Addictions

As the above examples suggest, there are a variety of addictions possible. Recent news accounts have pointed out that even high-level governmental officials can experience sex addiction. The advent of the Internet has led to what is referred to as Internet addiction where an individual is transfixed to the computer working for hours on end without a specific project in mind. The simple act of “surfing” offers the person afflicted with the addiction some degree of satisfaction.

The Gambler

Still another form of addictive behavior is that of the compulsive gambler. This is the behavior of an individual who is unable to resist the impulse to gamble. Many reasons have been posited for this type of behavior including the death instinct; a need to lose; a wish to repeat a big win; identification with adults the “gambler” knew as an adolescent; and a desire for action and excitement. There are other explanations offered for this form of compulsive behavior. The act of betting allows the individual to express an immature bravery, courage, manliness, and persistence against unfavorable odds. By actually using money and challenging reality, he puts himself into “action” and intense emotion. By means of gambling, the addicted individual is able to pretend that he is favored by “lady luck,” specially chosen, successful, able to beat the system and escape from feelings of discontent.

Just Plain Greed

Greed is another reason. In fact, a 1987 poll conducted by the Chicago Tribune revealed that people who earned less than $30,000 a year, said that $50,000 would fulfill their dreams, whereas those with yearly incomes of over $100,000 said they would need $250,000 to be satisfied. More recent studies confirm that goals keep getting pushed upward as soon as a lower level is reached. Now, consider Bernie Madoff, and the recent sub-prime mortgage debt fiasco in this light?

Compulsive Doctors

Edward Looney, executive director of the Trenton, New Jersey based Council on Compulsive Gambling (CCG) reports that the number of individuals calling with trading-associated problems is doubling annually. In the mid 1980s, when the council was formed, the number of people calling the council’s hotline (1 – 800 Gambler) with stock-market gambling problems was approximately 1.5 percent of all calls received. In 1998 that number grew to 3 percent and it is projected to rise to 7-8 percent by 2005. Dr. Robert Custer, an expert on compulsive gambling reported, that stock market gamblers represent over 20 percent of the gamblers that he has diagnosed. It is evident that on-line trading presents a tremendous risk to the speculator. The CCG describes some of the consequences:

  • Dr. Fred B. is a 43-year-old Caucasian male physician with a salary above $100,000 and in debt for more than $100,000. He is married with two children. He was a day trader.
  • Michael Q. is a 28-year-old Caucasian male registered nurse. He is married and the father of one (7 month old) child. He earns $65,000 and lost $40,000 savings in day trading and is in debt for $25,000. He has suicidal ideation.

Assessment

Join Our Mailing List

Question: So how much money is enough?

Answer: Just a little bit more.

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Physician Advisors: www.CertifiedMedicalPlanner.org

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details  Product Details

Understanding Behavioral Finance and Economics

Historical Review

By: Dr. David Edward Marcinko; MBA, MEd, CMP™

By: Eugene Schmuckler; PhD, MBA, CTS

By: Dr. Kenneth H. Shubin-Stein, CFA

By: Richard B. Wagner; JD, CFP®

***

Validating the emerging alliance between psychology (human behavior) and finance (economics) is the fact that two Americans won the Royal Swedish Academy of Science’s, 2002 Nobel Memorial Prize in Economic Science. Their research was nothing short of an explanation for the idiosyncrasies incumbent in human financial decision-making outcomes.

The Pioneers

Daniel Kahneman, PhD, professor of psychology at Princeton University, and Vernon L. Smith, PhD, professor of economics at George Mason University in Fairfax, Va., shared the prize for work that provided insight on everything from stock market bubbles, to regulating utilities, and countless other economic activities. In several cases, the winners tried to explain apparent financial paradoxes.

The Experiments

For example, Professor Kahneman made the economically puzzling discovery that most of his subjects would make a 20-minute trip to buy a calculator for $10 instead of $15, but would not make the same trip to buy a jacket for $120 instead of $125, saving the same $5.

Initially, in the 1960’s, Smith set out to demonstrate how economic theory worked in the laboratory (in vitro), while Kahneman was more interested in the ways economic theory mis-predicted people in real-life (in-vivo). He tested the limits of standard economic choice theory in predicting the actions of real people, and his work formalized laboratory techniques for studying economic decision making, with a focus on trading and bargaining.

Academe’

Later, Smith and Kahneman together were among the first economists to make experimental data a cornerstone of academic output. Their studies included people playing games of cooperation and trust, and simulating different types of markets in a laboratory setting. Their theories assumed that individuals make decisions systematically, based on preferences and available information, in a way that changes little over time, or in different contexts. By the late 1970’s, Richard H. Thaler, PhD, an economist at the University of Chicago also began to perform behavioral experiments further suggesting irrational wrinkles in standard financial theory and behavior, enhancing the still embryonic but increasingly popular theories of Kahneman and Smith.

Other Pioneers

Other economists’ laboratory experiments used ideas about competitive interactions pioneered by game theorists like John Forbes Nash Jr., PhD, who shared the Nobel in 1994, as points of reference. But, Kahneman and Smith often concentrated on cases where people’s actions depart from the systematic, rational strategies that Nash envisioned. Psychologically, this was all a precursor to the informal concept of life planning.

Enter the Financial Planners

Of course, comprehensive financial planners have always consulted with their clients regarding their goals and objectives, hopes and dreams, but typically from the point of view of money goals, rather than life ideals or business goals. The absence, or presence of biological and/or psychological reasons for them was never conceived, nor discussed. But, quantifying future subjective and objective goals, and doing a technical analysis of factors such as risk tolerance, age, insurance, tax, investing, retirement and estate planning needs, has certainly been the norm, especially for Certified Medical Planners (CMP).

Assessmentcmp-logo

Life planning and behavioral finance then, as proposed for physicians and integrated by the Institute of Medical Business Advisors (iMBA) is somewhat similar. Its uniqueness emanates from a holistic union of personal financial planning and medical practice management, solely for the healthcare space.  Unlike pure life planning, pure financial planning, or pure management theory, it is both a quantitative and qualitative “hard and soft” science. It has an ambitious economic, psychological and managerial niche value proposition never before proposed and codified, while still representing an evolving philosophy. Its’ zealous practitioners are called Certified Medical Planners (CMPs).

www.CertifiedMedicalPlanner.org

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

  ***

***

Stock Broker Report Card Survey

Join Our Mailing List

Doctor – Does your Broker Make the Grade?

[By Staff Reporters]Medical staff

Dear Colleagues,

Does your stock-broker or brokerage firm make the grade?

Be sure to participate in the annual broker report cards survey. And, if you work for Merrill Lynch, UBS, Morgan Stanley Smith Barney, Wells Fargo Advisors or Edward Jones, this trade magazine [Registered Rep] survey is for you.

Assessment

Click here to participate!

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

On Physician Bonuses

Money and Incentive Pools 

By Brent A. Metfessel; MD, MSbiz-book

Some Managed Care Organizations [MCOs] use medical provider profiles to allocate funds to the top-performing physicians. The MCO may give additional bonuses or preferential allocation of incentive pool funds to providers that perform well on particular cost-effectiveness and quality indices. 

Incentive Pools

Incentive pools are often built based on a certain percentage or “withhold” of dollars that are taken from the providers’ usual reimbursement and placed in a pool.  Top performers would be allocated the greatest percentage.

Example:

One mid-sized health plan in the Southeast paid a 20% bonus to providers with a case-mix adjusted performance ratio (actual/expected cost) of less than 1.3. Although such allocation schemes might incent providers to practice efficiently and with high quality, the MCO should attempt provider education as to the most appropriate practice patterns for the first one to two years after new profiles are introduced. This education should occur prior to introducing monetary incentives, since otherwise the relationship between providers and MCOs may ultimately become strained. 

Assessment

Join Our Mailing List

Unfortunately, money can become a major point of contention between providers and between providers and the health plan.

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. How do your bonus pools work; or should work? Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Congressional Budget Office Healthcare Reports of Interest

Ten [10] Aggregated CBO Reports

By Staff ReportersIntegration

Courtesy of Healthcare Town Hall:


Assessment

 Join Our Mailing List

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Goals of Medical Performance Improvement

Understanding Best Clinical Practices

By Brent A. Metfessel; MD, MSbiz-book

The major goals of medical performance improvement are twofold: First, for a particular practice pattern measure, the desire is to narrow the practice variation around the present health care mean. For instance, the spread of the distribution of a cost variance measure should decrease with process improvement.  Second, clinical guideline-based “best practices” can be utilized to move the entire provider population mean toward better cost-efficiency and quality.

Best-Practices

Although best-practices may be guideline-based, they should be adapted to local considerations and evaluated periodically through actual outcomes analysis. Such outcomes measures may include:

  • Cost-efficiency improvement, showing a decrease in resource utilization.
  • An increase in the performance of preventive measures, such as childhood immunizations and various screening tests such as breast and cervical cancer screening.  This may increase costs initially but will more than pay for itself through a decreased illness burden and cost in the future.
  • A decrease in episode length, usually implying a quicker resolution of symptoms.
  • A decrease in emergency room visits and unplanned hospital admissions.
  • A decrease in the rate of “sentinel events” such as status asthmaticus, hemorrhage during pregnancy, diabetic ketoacidosis, and ruptured appendix.

Many of these measures can be obtained using commonly available claims and administrative databases, although supplementation with clinical and functional status data will only increase the reliability and scope of outcomes analysis.

Assessment

Join Our Mailing List

In order to see significant performance improvement in response to quality improvement initiatives, one must be patient.  Two to three years may be needed to see this improvement.  Trending of measures helps analysts to determine whether such improvement is occurring.  Trending of data, however, can be quite resource-intensive since there must be an adequate data set – usually requiring storage of data for several years of experience. 

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

The Medical “Do Not Use” Acronym List

Joint Commission Abbreviations Not Used

By Staff ReportersHDS

In May 2005, The Joint Commission first affirmed its “do not use” list of abbreviations. The list was originally created in 2004 by The Joint Commission as part of the requirements for meeting National Patient Safety Goal Requirement 2B [Standardize a list of abbreviations, acronyms and symbols that are not to be used throughout the organization].

Link: http://www.jointcommission.org/PatientSafety/DoNotUseList/

Official List [Updated 3/5/09] 

Link: http://www.jointcommission.org/NR/rdonlyres/2329F8F5-6EC5-4E21-B932-54B2B7D53F00/0/dnu_list.pdf

Assessment

In the era of twitter and other text messaging abbreviations, the list is similar to “never-events” and related conditions frequently discussed on this ME-P.

More info:  https://healthcarefinancials.wordpress.com/2008/01/16/never-event-payment-trend-continues/

Conclusion

Join Our Mailing List

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

OSHA Medical Record Keeping Standards

On the Recording – Reporting of Occupational Injuries and Illness [29 CFR 1904]

By Pati Trites; MPA, CHBC and CPC

tritesIn this era of eHRs, and eMRs, it is vital to understand how OSHAs Recording and Reporting of Occupational Injuries and Illnesses Standard [29 C.F.R. 1904 – also known as the Recordkeeping Standard] requires employers to record & report work-related fatalities, injuries and illnesses www.HealthcareFinancials.com

Exemptions

For example, in January 2001, OSHA provided for a partial exemption from this Standard for many industries including: Offices & Clinics of Medical Doctors, Offices and Clinics of Dentists, Offices of Osteopathic, Offices of Other Health Practitioners, Medical and Dental Laboratories, and Health and Allied Services, Not Elsewhere Classified [1].

The exemption applies as long as the above-stated employers do not have at least one of the following events occur:

  • any workplace incident that results in a fatality; or
  • the hospitalization of three or more employees (example: a malfunctioning heat exchanger on a furnace causes carbon monoxide poisoning to the employees. If three or more must be hospitalized, then the exemption is lost for the calendar year).

If either of these two events occurs then the practice must comply with the reporting requirements of this Standard. Again, each employer who is physically located in one of the 26 states that has its own OSHA must follow state requirements if they are stricter.

Fatality or Hospitalization

In the event of a workplace fatality or an incident that causes the hospitalization of three or more employees, the employer must notify OSHA’s Area Office nearest to the site of the incident either in person or by phone. Notification can also be made by calling the OSHA toll-free central telephone number, 1-800-321-OSHA (1-800-321-6742). This notification must be accomplished within eight hours of the occurrence [2].

OSHA Form 330

Although the likelihood of either of these occurrences taking place is slight, it may be prudent to maintain records that comply with the OSHA Recordkeeping Standard in the event the practice’s partial exemption is lost during a calendar year. Keeping adequate records includes maintaining an OSHA Form 300, which is a log of the following events: days away from work, restricted work or transfer to another job, medical treatment beyond first aid, loss of consciousness, and a significant injury or illness diagnosed by a physician or other licensed healthcare professional.

OSHA Form 330-A

If the practice maintains its partial exemption throughout the calendar year, nothing further needs to be done. But if the practice loses its partial exemption this form must be used to complete a second OSHA form, Form 300A, the annual summary. The employer must post a copy of Form 300A in each practice location (if there are multiple locations) in a conspicuous place or places where notices to employees are customarily posted. The employer must also ensure that the posted annual summary is not altered, defaced, or covered by other material. The Form 300A remains posted from February 1 through April 30 of the calendar year following the year of data collection [3]. In other words, for all records kept in 2005, Form 300A would be posted from February 1, 2006, through April 30, 2006, and so on.

AssessmentMedical Chart

An additional recordkeeping requirement for healthcare entities is established in the Bloodborne Pathogen Standard, wherein the Sharps Injury Log must be maintained by any employer who must comply with the Recordkeeping Standard. If the employer loses his or her partial exemption during the year, then there is an obligation to complete and maintain the Sharps Injury Log. Again, this is a form that probably should be maintained by all healthcare organizations just in case the partial exemption is lost in any particular year.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

1.  29 C.F.R. 1904 Subpart B Appendix A.

2.  29 C.F.R. 1904.39.

3.  29 C.F.R. 1904.32.

Product DetailsProduct Details

Product Details

First Annual iMBA, Inc Educational Cruise

Meet, Greet, Lunch and Learn from the Experts

By Ann Miller; RN, MHA

[Executive-Director]

CruiseSome time ago, a CPA, CFP® and fellow Certified Medical Planner™ suggested that we hold annual meetings, or education seminars, for all our colleagues. As a nascent organization at the time, this was considered a “pipe dream.” But, it may now become a reality depending on your response. All interested stakeholders are invited. 


The Cruise

Currently, we are soliciting interest in a – Princess – Caribbean cruise [Southern] for 2010. This would afford us the opportunity to meet  you on both a formal or informal basis. Educational and other activities would then be scheduled,  as-needed or requested. Departure from Ft. Lauderdale, Florida. All info subject to change without notice, at this time.

www.CertifiedMedicalPlanner.comcmp-logo

For example, activities could be arranged for CMP™ program credits in health economics and medical management; or simply on an ad-hoc [audit] informational basis. We will also attempt to individualize and accommodate personal situations and professional needs. 

Seeking Interest and Input

And so, your thoughts, ideas and comments on this Medical Executive-Post cruise idea and opportunity are appreciated. Please email me your ideas; or contact us for more information with details. Serious inquiries only:

MarcinkoAdvisors@msn.com

And, feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Seeking Sponsors

Ship Solstice

We are also seeking sponsors for this cruise, and other iMBA corporate engagements.

https://healthcarefinancials.wordpress.com/2007/12/11/support-the-executive-post

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com  or Bio: www.stpub.com/pubs/authors/MARCINKO.htm

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Participating versus Non-Participating Doctors

Understanding Medicare Medical Payment Schemes

By Staff Reporters

www.HealthcareFinancials.comHOFMS

As of 1992, Medicare invoices are paid per resource-based relative value unit (RBRVU), and according to the lesser of the actual billed charges or the fee schedule amount. But, there are two types of medical providers: 1. Doctors who accept Medicare assignment only bill the patient for the co-payment, which is usually 20%.  2. Doctors who do not accept Medicare assignment are offered a lower fee schedule of 95% of the approved schedule, which is a 115% maximum fee limit of the approved schedule.

Example:

A participating physician’s approved fee schedule charge of $100 would yield $80 from Medicare and $20 from the patient. A non-participating (Non-Par) doctor with charges of $200, and with an approved fee schedule of $100, would yield: $109.25 = (.95 X $100) X 1.15 entirely from the patient.

If the Non-Par doctor selects payment type on a case-by-case basis, Medicare will pay its portion of the bill directly to the physician, but the doctor must accept the Non-Par fee schedule.

Assessment

Continuing our example yields: (.8 X $95) plus the patient’s co-payment of (.2 X $95), OR $76 plus $19 = $95.00.  

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

New ME-P Features in Review

Quick Links to Innovation and Integration

By Ann Miller; RN, MHA

[Executive Director]

IntegrationRecently we have added several new features to the Medical Executive-Post. And so, below is an aggregated and integrated list, with hot links, for your easy access and review.

We trust you will use, and enjoy them, frequently.


ME-P Features:

1. Our photo sharing feature called ME-Pr:

Link: https://healthcarefinancials.wordpress.com/2009/10/01/me-pr-photo-sharing-examples-2009/

2. ME-P widget for blogs, wikis and websites.

Link: https://healthcarefinancials.wordpress.com/2009/10/10/get-the-new-me-p-widget/

3. Media advisory service for the ME-P.

Link: https://healthcarefinancials.wordpress.com/2009/10/11/me-p-media-advisory-services/

4. Consultations and referal service.

Link: https://healthcarefinancials.wordpress.com/schedule-a-consultation/

5. Speaker’s bureau.

Link: https://healthcarefinancials.wordpress.com/dr-david-marcinko%e2%80%99s-bookings/

6. Annual doctor’s survey.

Link: https://healthcarefinancials.wordpress.com/media-kit/participate-in-annual-survey/

7. Textbooks, dictionaries and printed handbooks.

Link: https://healthcarefinancials.wordpress.com/2009/10/02/imba-inc-books-texts-and-dictionaries/

8. ME-P blog rating and ranking system.

Link: https://healthcarefinancials.wordpress.com/2009/10/06/our-new-me-p-rating-system/

9. Editorial complaints and publishing corrections.

Link: https://healthcarefinancials.wordpress.com/2009/10/07/me-p-complaints-corrections/

10. Videos and graphic slideshows.

Link: https://healthcarefinancials.wordpress.com/category/videos/

Assessment

Give em’ a click, and tell us what you think?

Join Our Mailing List

Channel Surfing: Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register.  

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Our Recent Experience with CFP® Mark Utility

Join Our Mailing List

Certification Falling from Grace – Deserved or Not?

By Dr. David Edward Marcinko; MBA, CMP™

[Publisher-in-Chief] dem21 

The Premise

In the summer [2008], we sent a random email blast to the first 200 Certified Financial Planners® on our list-serve. These were folks who had previously contacted us, and/or purchased our textbooks, handbooks, tools and/or dictionaries that assist accountants, financial advisors, attorneys, medical management consultants and all those working to assist physicians and medical professionals on business and economics matters.

The “Straw-Poll” Query

Our email blast asked the simple question:

“Did you ever voluntarily resign your license to use the CFP® mark?”

First Round Results

We received four positive responses [2%]. We then followed up to learn that 2 of the 4 were CPAs, one was a CFA and another was an MBA. Now, what do these results signify – probably nothing – or maybe an emerging trend?

Repeat

So, last summer [2009], after the continuing Wall Street collapse, and the Somnath Basu PhD article on “CFP Trust” in Financial Advisor magazine and this blog, we sent out a follow-up email to the exact same 200 Certified Financial Planners® as before; but carved-out and replaced the 4 CFPs who had resigned the mark, with 4 others.

Link: I Jealously “Shake my Fist” at Somnath Basu PhD

This time we asked the question:

“Have you recently considered allowing your CFP mark to lapse; or resigning it?”

Second Round Results

This time we received exactly eight positive replies [4%] or double the number from the first round. One CFP® said:

“I am rethinking my entire business and marketing philosophy. This includes separation from any taint left over from recent industry scandals – and yes – even including my CFP® mark”

 CMP logo

http://www.CertifiedMedicalPlanner.org

Assessment

This little experiment was not statistically significant by any means. And, again it probably is indicative of nothing. Yet, these types of questions must be boldly asked today; even if they were not even timidly asked yesterday.

Nevertheless, cited plausible reasons for the increased negative CFP® mark response may be:


  • CFP BoS lacks modernity and membership alliance. 
  • SEC mismanagement.
  • NASD/FINRA impotence.
  • Wall Street greed.
  • Lack of true fiduciary accountability.
  • Client anger and public distrust.
  • Advisor frustration at lost income.
  • College for Financial Planning and American College credibility.  
  • ME-P operations in the medical niche advisory space.
  • CFP® mark and related industry certification taint.
  • Alternative degrees and available designations.
  • Rise of RIAs and the fiduciary CMPmark for healthcare specificity.
  • Resigning [doing] and considering [thinking] are not equivalent;
  • etc, etc. 

It is interesting to note that no CFP® resigned their mark who did not hold either another graduate degree [MBA, MSFS, MA, MS, PhD], or more rigorous industry [CFA and CPA] certification.

Assessment 

So, is CFP mark allegiance just a union-like mentality of “united we stand – divided we fall”, by those with little to no gravitation pull of their own – or something else; ie., industry group think? You decide; and do tell us what you think.

Note: I am the founder of the CMP online education and certification program for financial advisors and consultants interested in the health economics, finance and medical practice management space, and a former [resigned] certified financial planner www.CertifiedMedicalPlanner.org 

Update 2013:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product DetailsProduct Details

Become a Published Print Author with Us

Join Our Mailing List

The Business of Medical Practice [3rd Edition]

By Hope Rachel Hetico RN, MHA, CMP™

[Managing Editor]biz-book5

Dear Colleagues and ME-P Champions

As you may know, we are commencing work on the third edition of our best selling book: The Business of Medical Practice

TOC 1st: http://www.amazon.com/Business-Medical-Practice-Maximizing-Doctors/dp/0826113117/ref=sr_1_8?ie=UTF8&s=books&qid=1231111232&sr=1-8

TOC 2nd: http://www.springerpub.com/prod.aspx?prod_id=23759

Invitation to Contribute

Accordingly, we would be honored for you to consider contributing a new or revised chapter, in your area of expertise, for a low-effort but high-yield contribution. Our goal is to help physician colleagues and management executives benefit from nationally known experts, as an essential platform for their success in the healthcare industry. Many topics are still available: [health accounting; law, policy and administration; Medicare fraud and abuse; cloud computing; and finance and economics, etc].

Support Always Available

Editorial support is available, and you would enjoy increasing subject-matter notoriety, exposure and public relations in an erudite and credible fashion. As a reader, or preferably a subscriber to the ME-P, your synergy in this space may be ideal. Time line for submission of a 5,000-7,500 word chapter is ample, and in a prose writing style that is “wide, not deep.” 

A Health 2.0 Initiative

And, be sure to address health 2.0 modernity. Update chapters from the second edition are also available. 

Definition: https://healthcarefinancials.wordpress.com/2008/09/12/emerging-healthcare-20-initiatives

Assessment

Please contact me for more details [MarcinkoAdvisors@msn.com], if interested [770.448.0769]. A best selling-book is rare; while a third-edition volume even more so. Join us in this project. Regardless, we trust you will remain apostles of our core ME-P vision, “uniting medical mission and financial profit margin”, and promoting it whenever possible.

Front Matter Link: frontmatter1advancedbusinessmedicine

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details

Health Insurance Prospective Payment System [HIPPS] Grouper Software and Documentation Codes

Enter the CMPs

Understanding Home Health Prospective Payment System (HH PPS) Case-Mix Refinement Changes

[By Staff Reporters]

AdvocacyA few operational changes were made to the V-Code Table in the updated version of the ICD-9-CM Official Guidelines for Coding and Reporting, including:

  • HH PPS grouper software and documentation (effective October 1, 2006): Contains Version 1.06 of the home health PPS case mix grouper software codes, which accommodates changes in OASIS reporting requirements effective 10/1/2006.  Also includes the grouper coding logic (pseudo-code), test records, and demonstration programs.
  • HH Consolidated Billing Master Code List: An Excel workbook file containing complete lists of all codes ever subject to consolidated billing provision of HH PPS.  A master list worksheet shows the dates each code included and excluded from consolidated billing editing on claims, with associated CMS transmittal references.  The master list also associates each code with any related predecessor and successor codes.  Supplemental worksheets show the list of included codes for each CMS transmittal to date.

Example:

The national unadjusted (wage index) per-visit rate payments paid per code were: [a] home health aide $44.37; [b] medical social service $153.55; [c] occupational therapy $105.44; [d] skilled nursing care $95.79 and [e] speech pathology $113.81.

Assessment

Join Our Mailing List

Link: http://www.cms.hhs.gov/homehealthpps/downloads/transitionepisodesqa.pdf

Link: http://www.cms.hhs.gov/HomeHealthPPS/downloads/GuidanceforHHAs_Posting_12-18-2007.pdf

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
BLOG: www.MedicalExecutivePost.com

Product DetailsProduct DetailsProduct Details

Launching the ME-P Tutoring Service

Seeking Academic Assistance in Health Economics, Finance and Administration

By Ann Miller; RN, MHA

[Executive-Director]ME-P Consulting

Enhanced knowledge and a better understanding of medical economics – healthcare finance and medical management – is at present central to more effective policy – making for better health services. We can provide a basic understanding of the key issues in health economics. You can either go online for tutoring or get your homework augmented/reviewed/completed through our assignment help service.

Email Based Homework or Employment Assignment Help in Health Economics

We may be the best resource to get answers to all your doubts regarding health economics, approaches to healthcare finance, medical practice management and other healthcare policy and administration specializations. You can submit your work, homework or assignments to us and we will make sure that you get the answers you need which are timely and also cost effective. Our tutors are available round the clock to help you out in any way with health economics and related topics. 

Live Online Tutor Help for Health Economics

We have a vast panel of experienced economics tutors who specialize in health economics and can explain the different theories to you effectively. You can also interact directly with our tutors for a one-to-one session and get answers to all your problems in other specializations in healthcare finance and medical management. Our tutors will make sure that you achieve the highest grades for your economics assignments. 

Assessment

Ideal for undergraduate and graduate students, practice managers, healthcare administrators, nurses, physician executives and employed laymen. Please contact us for competitive rates and premium prices for this personalize educational service: MarcinkoAdvisors@msn.com

Link: https://healthcarefinancials.wordpress.com/schedule-a-consultation/

Join Our Mailing List

Channel Surfing

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. 

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Overview of Hospital System IT Architectures

Understanding a Variety of Configurations

By Brent Metfessel; MD, MIS

www.HealthcareFinancials.comHOFMS

Hospitals can use a variety of configurations for HIS implementation depending on business needs and budgetary constraints. Staffing needed for these systems can range from a few full-time equivalents (FTEs) per 100 beds for very basic off-site processing systems to 15 or more FTEs per 100 beds for sophisticated systems that attempt to combine several architectures into one system (e.g., combination of client-server systems with mainframe processing). Resource use and customizability tend to vary in tandem; the greater the flexibility of the system to meet unique user needs, the greater the cost outlay for capital and/or additional FTEs.

Basic Systems

The basic system architecture possibilities are as follows:

  • Off-site (remote) processing: In this case the hospital contracts with a vendor external to the hospital. The hospital sends data over to the vendor site where the actual processing takes place. When processing is complete, the vendor sends the data back to the hospital, usually in electronic form.
  • Turnkey systems: A vendor provides the hospital with systems that are “pre-packaged” so that hospital-based system development is minimal. Limited customization of the system is possible using systems analysts or programmers.
  • Mainframe systems: Most applicable to large hospitals, this configuration is highly centralized. A large and powerful computer performs basically all the information processing for the institution and connects to multiple terminals that communicate with the mainframe to display the information at the user sites. Hospital IT departments usually use in-house programmers to modify the core operating systems or applications programs such as billing and scheduling programs.
  • Client-server systems: In this configuration one or more “repository” computers exist, known as “servers,” that store large amounts of data and perform limited processing. Communicating with the server(s) are client workstations that perform much of the data processing and often have graphical user interfaces (GUIs) for ease of use. Both customizability and resource use is high, depending on the desired sophistication. Many clinical information systems that process data directly related to patient care use this configuration.

For instance, the Veterans Health Administration, which has implemented what is likely the largest integrated healthcare information system in the United States, uses client-server architecture.  Known as the Veterans Health Information Systems and Technology Architecture (VistA), this system provides technology infrastructure to about 1,300 care facilities, including hospitals and medical centers, outpatient facilities, and long-term care centers. VistA utilizes a client-server architecture that links together workstations and personal computers using software that is accessed via a graphical user interface.

Overall, for hospitals that have the financial and manpower resources for a significant investment in IT, client-server architectures are the fastest-growing and typically the most preferred of the system architectures, due in large part to their local adaptability and flexibility to meet changing hospital and medical center needs.

Assessment

Join Our Mailing List

The above architectures are broad categories. Modifications and combinations of the above also exist, such as the use of client-server technology with mainframe systems and the addition of wireless technology and personal digital assistants (PDAs) to supplement the core computing functionality.

In considering the optimal architecture for a hospital, management needs to take into account factors such as size of the institution, desired sophistication of the application, IT budget, and anticipated level of user community involvement.

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

ME-P Media Advisory Services

Assisting our Media Colleagues and Target Professional Markets

By Ann Miller; RN, MHA

[Executive Director]Doctor's Bag

Welcome to the Medical Executive-Post. Below is a list of the services we provide to the media: 

1. Certified Medical Planners™ available for interviews or online program matriculation information and consideration www.CertifiedMedicalPlanner.com. Our CMPs™ may be available for interviews or short comments on medical management issues or health economic trends. We do our best to arrange for quick interviews to accommodate your deadlines. Current program matriculants may also available in some cases.

2. Reseach and Trends on Medical Economics and Modern Practice Management Issues: www.MedicalBusinessAdvisors.com.  We conduct ongoing research studies on healthcare financial issues, and also publish regular medical management research reports. Some research reports are available free of charge upon request; others for a modest surcharge. 

3. Pre-packaged information and content, visit: www.HealthcareFinancials.com.

4. Seminars and Speaking Engagements: www.HealthDictionarySeries.com.

5. Free ME-P blog widget: https://healthcarefinancials.wordpress.com/2009/10/10/get-the-new-me-p-widget/

Assessment

Join Our Mailing List

Dr. David Edward Marcinko, our Publisher-in-Chief, is also usually available to the traditional, electronic or new-wave media, as needed. We have a library of over 5,000 premium content pieces that you can integrate into your stories in sidebars, charts, graphs or pieces that can be published as standalone articles within your publication. To contact us about using any of the above services, please e-mail us at: MarcinkoAdvisors@msn.com

Channel Surfing

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. 

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Healthcare Reform Articles from Kevin Pho MD

Aggregating Content – Disseminating Knowledge

By Ann Miller; RN, MHA

[Executive Director] Books

Here are five interesting new articles on the healthcare reform debates from colleauge Kevin Pho, MD. 

Kevin practices at the Nashua Medical Group near the Massachusetts border. He is board certified in internal medicine and provides both comprehensive adult and primary care services.

Related posts:

Give them a click, read em’ and comment now.

Assessment

Join Our Mailing List 

Remember, how we put things together – sets us apart!

Channel Surfing

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register.  

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Get the New ME-P Widget

Spreading ME-P Content and Informaton with our Gift to You

By Ann Miller; RN, MHA

[Executive Director]Our Gift

As someone who reads far too many medical, healthcare finance, political and health economics blogs on a daily basis, I decided to compile our ME-P blog RSS feeds into a nice, clean widget which you can quickly cut and paste into your own blog, wike or website.

Why Would you Want this Widget?

  • Easily keep up with latest ME-P posts and comments on more than 50 topical channels.
  • Spread goodwill throughout the blogo-sphere when you send visitors to other blogs.

Assessment

If you’re not tech savvy, we’ve done the hard work – just cut and paste and you’re done. Please e-mail me if you have any questions.

Get our Widget: Get this widget!

Channel Surfing

Get more from www.BlogSurfer.US  Be sure to visit our other topic channels too! Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. 

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Why Most Financial Advisors Won’t be Fiduciaries

Industry Groups Differ On Fiduciary Standard

By Staff ReportersBenjamin Bills

The House Financial Services Committee recently heard two takes on the fiduciary standard – investment advisors who want it applied to broker dealers – and broker-dealers who want to apply a universal standard of care to all advisors, including investment advisors.

Assessment

And so, we encourage all ME-P subscribers to read industry trade magazines [aka ”trade rags”] to learn how some financial advisors fleece physicians and other investors by not being fiduciaries; with sincere apologies to all honest and hard working fiduciary advisors.Become a CMP IOW: Follow the money.

Link: http://www.financialadvisormagazine.com/fa-news/4532-industry-groups-differ-on-fiduciary-standard-.html

www.CertifiedMedicalPlanner.com

Channel Surfing

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. 

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details  Product Details


A Personal Health Records [PHRs] Video

Where We’ve Been … Where We’re Going!

By John Moore

Channel Surfing

Join Our Mailing List

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register.  

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Take the Hospital Endowment Fund Management Challenge!

Calling all Financial Advisors – Are You CMP™ Worthy?

By Staff ReportersBecome a CMP

After conducting a comprehensive fundraising program, the Hoowa Medical Center received initial gifts of $50 million to establish an endowment. Its status as the community’s only trauma center and neonatal intensive care unit causes it to provide substantial amounts of unreimbursed care every year. This phenomenon, together with the declining reimbursements and an estimated 6% increase in operating costs, leaves the Center with a budgeted cash shortfall of $4 million next fiscal year. Although the new endowment’s funds are available to cover such operating shortfalls, the donors also expect their gifts to provide perpetual support for a leading-edge medical institution.

The Treasurer

Bill, the Center’s treasurer, has been appointed to supervise the day-to-day operations of the endowment. One of his initial successes was convincing his investment committee to retain a consultant who specializes in managing endowment investments. The consultant has recommended a portfolio that is expected to generate long-term investment returns of approximately 10%. The allocation reflects the consultant’s belief that endowments should generally have long-term investment horizons. This belief results in an allocation that has a significant equity bias. Achieving the anticipated long-term rate of returns would allow the endowment to transfer sufficient funds to the operating accounts to cover the next year’s anticipated deficit. However, this portfolio allocation carries risk of principal loss as well as risk that the returns will be positive but somewhat less than anticipated. In fact, Bill’s analysis suggests that the allocation could easily generate a return ranging from a 5% loss to a 25% gain over the following year.

The Committee

Although the committee authorized Bill to hire the consultant, he knows that he will have some difficulty selling the allocation recommendation to his committee members. In particular, he has two polarizing committee members around whom other committee members tend to organize into factions. John, a wealthy benefactor whose substantial inheritances allow him to support pet causes such as the Center, believes that a more conservative allocation that allows the endowment to preserve principal is the wisest course. Although such a portfolio would likely generate a lower long-term return, John believes that this approach more closely represents the donors’ goal that the endowment provide a reliable and lasting source of support to the Center. For this committee faction, Bill hopes to use MVO to illustrate the ability of diversification to minimize overall portfolio risk while simultaneously increasing returns. He also plans to share the results of the MCS stress testing he performed suggesting that the alternative allocation desired by these “conservative” members of his committee would likely cause the endowment to run out of money within 20 to 25 years.

The Polarizer

Another polarizing figure on Bill’s committee is Marcie, an entrepreneur who took enormous risks but succeeded in taking her software company public in a transaction that netted her millions. She and other like-minded committee members enthusiastically subscribe to the “long-term” mantra and believe that the endowment can afford the 8% payout ratio necessary to fund next year’s projected deficit. Marcie believes that the excess of the anticipated long-term rate of return over the next year’s operating deficit still provides some cushion against temporary market declines. Bill is certain that Marcie will focus on the upside performance potential. Marcie will also argue that, in any event, additional alternative investments could be used as necessary to increase the portfolio’s long-term rate of return. Bill has prepared a comparative analysis of payout policies illustrating the potential impact of portfolio fluctuations on the sustainability of future payout levels. Bill is also concerned that Marcie and her supporters may not fully understand some of the trade-offs inherent in certain of the alternative investment vehicles to which they desire to increase the allocated funds.

Key Issues:

1. Given the factors described in the case study (anticipated long-term investment return, anticipated inflation rate, and operating deficit) how should Bill recommend compromise with respect to maximum sustainable payout rates?

2. How should Bill incorporate the following items into his risk management strategy?

a. educating the committee regarding types of risk affecting individual investments, classes, and the entire portfolio;

b. measuring risk and volatility;

c. provisions for periodic portfolio rebalancing;

d. using tactical asset allocation; and,

e. developing and implementing a contingency plan.

3) What additional steps should Bill take to form a group consensus regarding the appropriate level of endowment investment risk?

4) What additional elements should Bill add to his presentation to target the concerns of the “conservative” and “aggressive” committee members, respectively?

Assessment

And so, financial advisors, planners and wealth managers; are you up to answering this challenge? We dare you to respond! Visit: www.CertifiedMedicalPlanner.com

Conclusion

And so, your thoughts and comments on this Medical Executive-Post are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, be sure to subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com 

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Popular Healthcare Reform Articles

Aggregating Content – Disseminating Knowledge

By Ann Miller; RN, MHA

[Executive Director]Text Books 

Here are three interesting and related articles from The Incidental Economist:


Give them a click, read em’ and comment now.

Channel Surfing

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register.  

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Get our Widget: Get this widget!

Our Other Print Books and Related Information Sources:

Practice Management: http://www.springerpub.com/prod.aspx?prod_id=23759

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Health Administration Terms: www.HealthDictionarySeries.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed

And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise