Guide to Biostatistics

Clinical Tools

Join Our Mailing List

Here is a white paper of important epidemiological concepts and common bio-statistical terms to help doctors and related professionals translate medical research into everyday practice.

Link: http://www.medpagetoday.com/Medpage-Guide-to-Biostatistics.pdf

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Our Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Introducing Carol S. Miller BSN MBA

Our Newest Thought-Leader

By Ann Miller RN MHA

[Executive-Director]

Carol S. Miller BSN, MBA, PMP has an extensive healthcare background in operations, business development and capture in both the public and private sector. Over the last 10 years she has provided management support to projects in the Department of Health and Human Services, Veterans Affairs, and Department of Defense medical programs.

Resume

In most recent years, Carol has served as Vice President and Senior Account Executive for NCI Information Systems, Inc., Assistant Vice President at SAIC, and Program Manager at MITRE. She has led the successful capture of large IDIQ/GWAC programs, managed the operations of multiple government contracts, interacted with many government key executives, and increased the new account portfolios for each firm she supported. She is a HIMSS Fellow, Past President and current Board member and an ACT/IAC Fellow.

Education

Carol earned her MBA from Marymount University; BS in Business from Saint Joseph’s College, and BS in Nursing from the University of Pittsburgh. She is a Certified PMI Project Management Professional (PMP) (PMI PMP) and a Certified HIPAA Professional (CHP), with Top Secret Security clearance issued by the DoD in 2006.

Assessment

Carol can be reached at 703.407.4704 or carol.miller@macksonconsulting.com

Our Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Are Doctors Throwing in the Towel?

Doctors versus Insurers

By Staff Reporters

Despite the success of entrepreneurial doctors – the number of doctors who enter private practice are in decline.

The Survey

For example, according to a survey by the “Physicians Foundation”, 89% of respondents believe the traditional model of independent private practice “is a dinosaur soon to go extinct.”

Survey: http://www.physiciansfoundations.org/uploadedFiles/Health%20Reform%20and%20the%20Decline%20of%20Physician%20Private%20Practice.pdf

Pod Cast: http://healthystate.org/archives/5764

Assessment

So we ask; what do you think?

Are physicians “throwing in the towel” and leaving private medical practice?  

Conclusion

Your thoughts and comments on this ME-P are appreciated. Our goal is to prevent same. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details

Update On Medical Smartphone Apps

Offering a Window Of Opportunity For M-Health Service Providers

By Markus Pohl

Join Our Mailing List

The potential revenue that could be made in the mobile healthcare app market is just a fraction of the total integrated healthcare market. Service providers within the healthcare market have a window of opportunity with the possibilities that the mobile apps market offers right now.

The benefits of integrated electronic and mobile healthcare solutions are evident. At the moment there is a lot of potential for companies to scale up their services and learn how to adapt to the changing market. But they have to act quickly to seize the moment. In the last few years those solutions either remained as isolated pilots or struggled with all kinds of barriers from healthcare stakeholders, with only a few exceptions.

Integrated Solutions 

As it is not clear when integrated solutions will become widely accepted around the globe, more and more e-health and m-health service provides are rethinking their strategy. They are turning away from complex and integrated solutions that need acceptance of all national healthcare stakeholders to more simple patient centric services.

m-Health Services Rising

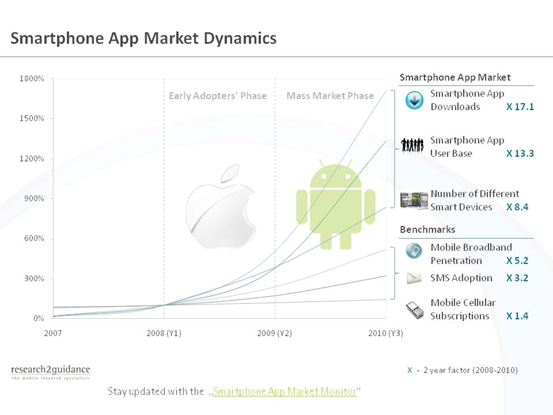
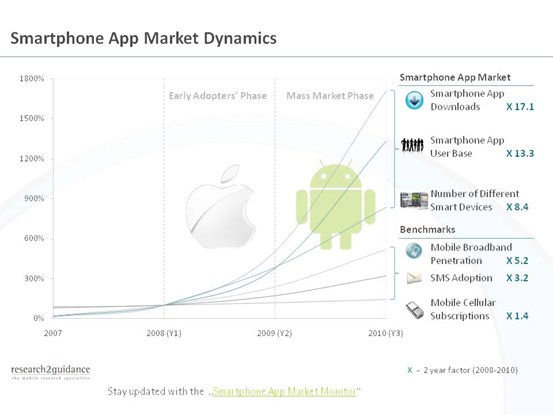
This rethinking process goes hand in hand with the rise of the smartphone app market. In the next 5 years the smartphone app market will help the mobile healthcare industry to reach a new level. mHealth apps will be widely used and will demonstrate the technological possibilities of smartphones. Technology, educated patients/doctors and proof of cost savings for health insurance providers will eventually allow companies to make money with mhealth apps.

Before the smartphone app market brought new life to the mobile healthcare market, mHealth service providers struggled to scale up their solutions. Most of them never made it out of the trial stage. Some of them were just too basic, such as simple pill reminders running on SMS as the primary delivery technology. More complex solutions that were based on eHealth initiatives integrated the features of a mobile device with a database (electronic health records), but failed mainly because of political barriers and low awareness amongst patients.

Assessment 

For more information on the smartphone based mHealth market and its business opportunities for healthcare provides please see our latest report on the mHealth market: “Mobile Health Market Report 2010-2015”.

Contact:

research2guidance

+49 30 609 893 363

markus.pohl@research2guidance.com

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details 

On the US Tax Code Complexity

Recent Ways and Means Committee Meeting

By Children’s Home Society of Florida Foundation

Join Our Mailing List

At an April 13th 2011 hearing on the tax code before the Ways and Means Committee, witnesses noted that there is a general consensus on the complexity of the tax code.

Enter Albert Einstein

One witness quoted Albert Einstein, recipient of 1921 Nobel Prize in Physics. While he was the world expert on the Theory of Relativity, Dr. Einstein also commented that “the hardest thing in the world is to understand the income tax.”

At the hearing, Chairman Dave Camp (R-MI) noted there are “nearly 4,500 changes in the last decade – 579 of them in 2010 alone – the code is too complex.” Other representatives and witnesses agreed that the sheer size and complexity of the Internal Revenue Code make compliance very challenging.

Enter the AICPA

Annette Nellen represented the American Institute of Certified Public Accountants in the hearing. She indicated that there are five specific steps that could be taken to substantially reduce the complexity and cost of complying with the code. These include the following actions.

1. Higher Education Deductions and Credits – Reduce the Hope Credit, American Opportunity Credit, Lifetime Learning Credit, the tuition and fees deduction and other benefits into one simple credit.

2. Education Phase Out – Create one definition for qualified education expenses and eliminate the multiple phase outs under the current system.

3. Kiddie Tax – For children with unearned income under age 18 or students under age 24, simplify the current method where they pay tax at their parents’ rate.

4. Mileage Rates – Create the same mileage rate for business purposes, medical purposes and qualified charitable travel.

5. Alternative Minimum Tax – Repeal the tax because it is too complicated to modify.

Enter the Financial Planner

Financial Planner Mark Johannessen is a CFP™ and Managing Director of a McLean, Virginia financial firm. He was President of the Financial Planning Association in 2008 and suggested that there are a number of Internal Revenue Code issues that make financial planning difficult.

First, there are temporary provisions. For example, the 2011 tax rate on dividends is 15%, but the scheduled tax rate on dividends in 2013 is 43.4%. While it’s possible that Congress could change the law between now and 2013, it makes investment planning very difficult.

Second, many changes are temporary and Congress tends to act very late in the year. Congress passed the IRA Charitable Rollover for 2010 on December 17. By that date, most individuals had already taken their required minimum distribution. Johannessen indicated that the late date “negatively impacted both the individuals’ planned charitable giving” and also the charities who received fewer gifts.

Third, the uncertainty in estate tax law continues to make planning quite difficult. While the current exemption is $5 million and there now is portability for couples, the current law only applies for 2011 and 2012. To do good planning, it is essential to know what the law will be in future years.

Assessment

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

DNR versus [P]MOLST

Of Differences and Distinctions

By Dr. David Edward Marcinko MBA

By Hope Rachel Hetico RN MHA

DNR Definition

A Do Not Resuscitate Order (DNR) is a refusal of cardiopulmonary resuscitation in the event of cardiac or pulmonary arrest.  A DNR, which is signed by a physician upon your consent, applies only if you are in a hospital or nursing home. If you are in your residence, a hospice, a clinic, or anywhere else and do not wish to be resuscitated, you must have a “Non-Hospital” DNR signed by your physician.

Sample form: http://www.ochealthinfo.com/docs/forms/ems_dnr_form.pdf

P-MOLST Definition

A P-MOLST (Physician – Medical Orders for Life-Sustaining Treatment) can be used to document your wishes concerning various forms of life-sustaining medical treatment, including DNR, endotracheal intubation and mechanical ventilation, artificial nutrition and hydration, future hospitalization, antibiotics, and other instructions. It is designed to improve the quality of end of life care for those with serious health conditions or those who wish to define their care wishes when facing the end of life. The form must be completed by both you and your physician. It is intended to apply immediately, and not upon a trigger of future incapacity. The form may be completed in stages as a medical condition deteriorates.

Sample form: http://www.compassionandsupport.org/pdfs/professionals/molst/DOH-5003_06.10_.FINAL__.pdf

Assessment 

Subsequent to the publication of the Institute of Medicine Report “Approaching Death: Improving Care at the End-of-Life”, the Rochester Individual Practice Association and BlueCross BlueShield Rochester Region End-of-Life/Palliative Care Professional Advisory Committee was formed to address these and related issues.

Link: http://www.compassionandsupport.org/index.php/about_us

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Seeking Medical Director [HRMC]

Heartland Regional Medical Center

By Deedra Hartung

CLASSIFIED ADVERTISEMENT

Join Our Mailing List

Dear Dr. Marcinko,

Cejka Executive Search has been exclusively retained by Heartland Health, a physician-led, integrated health care system in St. Joseph, Missouri, to recruit a physician leader who will serve as Medical Director of Heartland Regional Medical Center (HRMC).

About HRMC

HRMC is a 491-bed medical center comprised of a 250-member medical staff, including 125 employed physicians, and is a 2009 Malcolm Baldrige National Quality award winner. Heartland Health is rapidly moving towards becoming an Accountable Care Organization and will likely be a Medicare ACO Pilot Site. Heartland Health includes a large physician clinic, foundation, health plan and other ventures and affiliations.

Responsibilities

In collaboration with the Administrator of HRMC, the Medical Director will be responsible for providing clinical and operational oversight, communicating the vision of the medical center, building partnerships with key stakeholders and advocating quality and safety measures within clinical and ancillary departments. Additionally, the Medical Director will serve as a mentor and coach to the medical staff and the leadership team. The Medical Director position is ideal for a physician leader wanting additional operational experience in preparation for a future in a position as a CEO.

Qualifications

Candidates must be board certified, eligible for a Missouri license and possess a minimum of ten years clinical experience.  An MBA or MHA is highly preferred. Ideal candidates will have experience with peer review, credentialing, population health, clinical research and the development of a residency program.

View Additional Details

Qualified candidates may submit their CV’s or contact:
Deedra Hartung
Executive Vice President, Managing Principal
Cejka Executive Search
800-209-8143, Extension 63518
Email: jkliethermes@cejkasearch.com

www.cejkaexecutivesearch.com

Understanding the Referral Relationship in Medicine

Cultivating a Steady Stream of Patients

By Dr. David Edward Marcinko MBA

[Publisher-in-Chief]

Developing and cultivating a steady stream of referrals involves good planning, an investment of time and energy in the referral relationship, and a keen understanding of referring physicians’ needs and priorities.

According to consultant Carolyn Merriman, enhancing the referral relationship is a step-by-step process, not unlike the clinical process, that begins by identifying target physicians and their needs, prioritizing the list of referral contacts and then determining the best way to reach them.

Link: www.BusinessofMedicalPractice.com

Make it a Win-Win Relationship

For example, a physician may routinely refer patients to a particular specialist because he or she has an out­standing reputation for medical expertise and competence, is more accessible than comparable practitioners or has a convenient location for the referring physician’s patients. The physician may have a relationship with the specialist because of marketing by a local hospital or the specialist’s own practice. And, in some cases the two physicians have a social relationship.

There are many ways to create and maintain these relationships. Physicians should choose the approach that works best for them, put together a plan and stay consistent. Look for ways to make the relationship a win-win for both practices or for the referring hospital or outpatient facility.

Link: Front Matter BoMP – 3

The SHSMD

If you are not comfortable with developing referral relationships for your practice, seek out partners, office staff or hospital partners who can appropriately assist, train or support you in this effort. Many hospitals have staff focused on physician sales and service.

The Society for Healthcare Strategy and Market Development (SHSMD) recently reported that 41% of hospitals had dedicated sales staff support, with more than half of those using their sales staff to support cardiology and radiology.

Assessment

Often, hospitals are seeking physician speakers for community seminars, wellness programs and other outreach efforts. Ask about participating in these venues. Offer to write articles for newsletters, the Web site or local media outlets. All of these expose the physician and the practice to referral sources as well as the public.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:


Ref: “By the Numbers, 2008.”  Society for Healthcare Strategy and Market Development of the American Hospital Association.

Product Details 

Vows of Change at Moody’s

But, the Flaws Remain the Same

By Jesse Eisinger ProPublica | @eisingerj 

Join Our Mailing List

In the aftermath of the financial crisis, nobody has gone to prison and there haven’t been any serious structural changes in the financial system. But at least everyone involved feels bad about it and has vowed to change, right? For Moody’s Investors Service, those pledges are empty, Bill Harrington says.

In this column, co-published with New York Times’ DealBook, I monitor the financial markets to hold companies, executives and government officials accountable for their actions.

A Window to the Debacle

Mr. Harrington was an analyst in the structured finance group at Moody’s for more than a decade, much of it spent rating collateralized debt obligations. He worked at Moody’s until the middle of last year, although he left the C.D.O. group in 2006. In his job, he had a window on the biggest debacle in the history of credit ratings. Companies like his allowed banks to pass off hundreds of billions worth of paper onto investors by waving their magic wands and deeming the securities investment-worthy.

Since then, the government has tried to change the ratings agencies. The Dodd-Frank financial reform law has some bold measures, like making the ratings firms liable for their judgments. Unfortunately, the rules are in danger of not being enforced because of budget constraints and resistance from the agencies.

But the biggest problems at Moody’s may have been cultural. The dominant ethos during the boom, instilled by Brian M. Clarkson, the former president and chief operating officer [1], was that customer service was Job 1. And the customers were the bankers.

Banker Customers

The ability for bankers to run the show has long been an obvious flaw in the ratings system for structured products. Investment banks create the securities and benefit when they receive generous ratings. Banks pay the agencies that supply the ratings. Yet the agencies are somehow supposed to hold the line with the people who are responsible for their paychecks.

To Moody’s credit, Mr. Clarkson is now gone. To Moody’s discredit, however, his philosophy is largely still in place, at least according to Mr. Harrington.

To the last day Mr. Harrington was there, he says, bankers remained hard-charging and aggressive advocates for their deals, sometimes to the point of abusing the analysts.

Wall Street ain’t beanbag, so that’s not surprising. The troubling aspect is that the Moody’s bosses acted like disinterested brokers between two sides in disputes with analysts, instead of standing up for the analysts and defending their independence. “That was the standard operating procedure that got worse and worse. We didn’t get the benefit of the doubt,” Mr. Harrington said.

When I asked Moody’s about Mr. Harrington’s experiences, a spokesman wrote in an e-mail: “We take strong exception to your characterization of Moody’s culture. We have always had an unwavering culture of integrity, analytical independence and objectivity and that culture has only grown stronger since the financial crisis.” He pointed to numerous efforts at Moody’s to improve the ratings process and to bolster Moody’s procedures.

In the spring of 2009, Mr. Harrington was working on a deal and a banker was persistently calling him. He returned the first call, but had other work that day and didn’t return the next two calls right away. “I thought caller ID served a purpose,” he said wryly.

Soon after, his boss alerted him to a call he’d received from Michael Kanef, the head of compliance. Mr. Kanef wanted to know why Mr. Harrington hadn’t returned the banker’s call. Mr. Harrington was shocked. Why was the head of compliance getting involved? But he got the apparent message: Analysts are to lean over backward for the bankers. That had been Mr. Clarkson’s philosophy, and now it was his successors’.

“The culture persists — and it’s being enforced by compliance department,” Mr. Harrington said.

So who is Mr. Kanef? Before he was the head of regulatory affairs and compliance, he was in charge of ratings on residential mortgage-backed securities [2]. Did such an executive deserve a promotion?

And then there is Raymond W. McDaniel, the chief executive throughout the housing boom, the bust and the entire financial crisis. He remains at the helm. And he had to swallow the bitter pill of more than $9 million in compensation last year. Indeed, most of Moody’s top management has been in place through the crisis.

Moody’s didn’t make Mr. Kanef or Mr. McDaniel available for comment.

The Blame Game

So if Moody’s doesn’t think the executives who ran the company were responsible for its collapse in reputation and contribution to the multitrillion-dollar financial crisis, who do they think is to blame? The analysts, Mr. Harrington says. The hard-working, low-level minions with little decision-making power.

Mr. McDaniel has conceded that sometimes “we drink the Kool-Aid.”

But that hardly makes the analysts to blame.

“If some analysts drank the Kool-Aid, it was only because management mixed and stirred it up and threatened that analysts wouldn’t get to heaven on the spaceship unless he or she drank it,” Mr. Harrington said.

Moody’s has recognized it has a disaster on its hands — a public relations disaster. Clients — the investors who use ratings — have been losing faith in the agencies. Mr. Harrington said that Moody’s executives marched analysts into meetings to explain how they were going to tell their clients about how much Moody’s had grown and learned from its mistakes. It was as if they were in “Communist re-education camp,” he said.

At one of these meetings, an analyst asked if they could be given training in how to deal with banker abuse, Mr. Harrington recalls. The suggestion was immediately shot down by the executive running the meeting.

Moody’s says that its retraining efforts are part of its continuing efforts to reach out to investors to improve its ratings.

Assessment

When Moody’s executives make public presentations, as when Mr. McDaniel testified [3] in front of the Financial Crisis Inquiry Commission, the overarching theme is that the agency’s problem was limited to the housing-related structured finance. Few people saw how fast and deep the housing market would crash. How could the ratings agencies?

A few weeks ago, Alan Greenspan penned an instantly notorious line: “With notably rare exceptions,” [4] he wrote, unfettered financial markets have worked well. Moody’s persists in believing that with notably rare exceptions, so too have credit ratings.

Full Article: http://www.propublica.org/thetrade/item/vows-of-change-at-moodys-but-the-flaws-remain-the-same/

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

Launching Partnership for Patients

Better Care, Lower Costs

By Staff Reporters

Join Our Mailing List

Doctors, nurses and other health care providers in America work incredibly hard to deliver the best care possible to their patients.  Unfortunately, an alarming number of patients are harmed by medical mistakes in the health care system and far too many die prematurely as a result.

Just Launched

The Obama Administration has just launched the Partnership for Patients: Better Care, Lower Costs, a new public-private partnership that will help improve the quality, safety, and affordability of health care for all Americans.  The Partnership for Patients brings together leaders of major hospitals, employers, physicians, nurses, and patient advocates along with state and federal governments in a shared effort to make hospital care safer, more reliable, and less costly.

Partnership Goals  

The two goals of this new partnership are to:

  • Keep patients from getting injured or sicker. By the end of 2013, preventable hospital-acquired conditions would decrease by 40% compared to 2010.  Achieving this goal would mean approximately 1.8 million fewer injuries to patients with more than 60,000 lives saved over three years.
  • Help patients heal without complication. By the end of 2013, preventable complications during a transition from one care setting to another would be decreased so that all hospital readmissions would be reduced by 20% compared to 2010.  Achieving this goal would mean more than 1.6 million patients would recover from illness without suffering a preventable complication requiring re-hospitalization within 30 days of discharge.   

Toward a More Sustainable Health Care System

Achieving these goals will save lives and prevent injuries to millions of Americans, and has the potential to save up to $35 billion dollars across the health care system, including up to $10 billion in Medicare savings, over the next three years.  Over the next ten years, it could reduce costs to Medicare by about $50 billion and result in billions more in Medicaid savings.  This will help put our nation on the path toward a more sustainable health care system.

Institute of Medicine

In 1999, the landmark Institute of Medicine study, “To Err is Human,” estimated that as many as 98,000 Americans die every year from preventable medical errors. Despite many successful efforts, this statistic has not improved much in the following decade.  And many more patients get injured or sicker from preventable adverse events after being admitted to a hospital.  After more than a decade of work to understand and address these problems, promising examples of better practices exist, but patients too often are still injured in the course of receiving care.  At any given time, about one in every 20 patients have an infection related to their hospital care.

  • On average, one in seven Medicare beneficiaries is harmed in the course of their care, costing the government an estimated $4.4 billion every year.
  • Nearly one in five Medicare patients discharged from the hospital is readmitted within 30 days – that’s approximately 2.6 million seniors at a cost of over $26 billion every year.

Assessment

There is much more work to be done to prevent unnecessary harm to patients.

Link:  http://www.healthcare.gov/center/programs/partnership/about/index.html

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Will this initiative be a success or another governmental boondoggle? Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details 

Budget Committee Proposes 25% Tax Rate

The Ryan Plan for FY 2012

By Children’s Home Society of Florida Foundation

Join Our Mailing List

On April 5th House Budget Committee Chair Paul Ryan (R-WI) presented his budget proposal for Fiscal Year 2012. The comprehensive proposal included over $4 trillion in reduced spending during the next decade and a plan to reduce both the personal and corporate top tax rates to 25%.

House Ways and Means Committee

The tax reform provisions will be handled by the House Ways and Means Committee. Chairman Dave Camp (R-MI) noted that, “with nearly 4,500 changes in the last decade alone, the code is too complex. And with Americans spending over 6 billion hours and over $160 billion annually to comply with the code, it is too costly and too burdensome. Clearly, the time for comprehensive reform has come.”

Many Loopholes

Both parties have raised the possibility of tax reform this year. At a meeting in Pennsylvania, President Obama was asked about the potential for reforming corporate taxes. He noted that the U.S. has “one of the highest tax codes for corporations in the world.”

However, due to “many loopholes” a number of U.S. corporations pay little or no taxes. Moreover, President Obama suggests that it would be good “to reform our tax code, simplify it, lower the rate for corporations, but eliminate a bunch of the loopholes.”

Assessment

Treasury Secretary Timothy Geithner also indicated to the Senate Committee on Appropriations that he is developing a “comprehensive corporate tax reform plan” and it will be released quite soon. Sec. Geithner indicated his plan would include, “a very strong pro-investment, pro-growth, pro-competitiveness proposal.”

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

On the Anniversary of the Affordable Care Act [A Video]

An Audio-Video Review One Year Later

By Staff Reporters

Join Our Mailing List

Reforms under the Affordable Care Act have brought an end to some of the worst abuses of the insurance industry. These reforms have given Americans new rights and benefits, by helping more children get health coverage, ending lifetime and most annual limits on care, allowing young adults under 26 to stay on their parent’s health insurance, and giving patients access to recommended preventive services without cost.

Link: http://www.healthcare.gov/?gclid=CO72rYyUkKgCFeM85QoddjY3yg

Other Benefits

Many other new benefits of the law have taken effect, including 50% discounts on brand-name drugs for seniors in the Medicare “donut hole,” and tax credits for small businesses that provide insurance to employees. More rights, protections and benefits for Americans are on the way through 2014.

Assessment

See major parts of the law on this interactive timeline, or read the Patient’s Bill of Rights.

And, find out how the Patient Protection and Affordable Care Act [ACA]  provides better benefits and better health.

Video Link: http://www.healthcare.gov/law/introduction/index.html

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Is this post a shill for Obama-Care and the Federal Government? Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details 

Strengthening Physician Hospital Relationships

A PHO Primer 

By Dr. David Edward Marcinko MBA, CMP™

[Publisher-in-Chief]

Contrary to popular belief, physician-hospital relationships are not always driven by formal economics partnerships such as joint ventures, employment or medical director stipends. A concerted physician outreach program demonstrates a hospital’s commitment to working together more effectively.

Example

For example, Bon Secours Hampton Roads Health System in Virginia uses a systematic outreach program in which senior leadership, supplemented by physicians sales staff, meet regularly with physicians to identify critical operational issues that are disrupting their practice. The program is so important to building referral relationships with physicians who have other options for alignment that the system CEO reviews the issues list daily.

Link: www.BusinessofMedicalPractice.com

Key Areas 

Regardless of the partnership model, consultant Carolyn Merriman believes effective physician-hospital relationships call for alignment in four key areas:

  • Leadership – physicians are included in developing the strategic direction of the hospital and its programs and services.
  • Input – physician input is sought from people and areas beyond the traditional medical executive committee, often using younger, informal leaders who are the future leaders of the medical staff.
  • Communication – physicians feel heard and responded to as they identify issues and challenges they encounter as they practice medicine, and they feel that processes are in place for effectively resolving the issues.
  • Relationship Management – executives understand what motivates physicians professionally and personally and use that information to build a solid foundation of trust and mutual respect as they build and foster relationships.

Assessment

In a 2007 survey, the American College of Healthcare Executives (ACHE) found that physician-hospital relations was the third most pressing issue for hospital CEOs, topped only by financial challenges and care for the uninsured. Within the physician-hospital category, specific concerns included creating win-win collaboration, physician requests for payment for service to the hospital, competition with physician-owned facilities/equipment, medical staff structures/leadership and niche providers. 

Certainly from the physician’s perspective, a better relationship with hospital leaders and hospital staff makes life infinitely easier. We do, after all, share a common denominator—the patient. Like the physician, the hospital is equally interested in providing patients with the very best quality and service possible.

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details 

Donating to the Victims in Japan

How the ME-P is Helping Out

By Dr. David Edward Marcinko, MBA CMP™

[Publisher and Editor-in-Chief]

Millions of Japanese are struggling in the cold; without electricity or heat. And, rolling blackouts have been implemented as the earth-quake and tsunami devastated country faces a crippled power grid.

And, of course, all medical professionals realize that there is no “safe threshold” for any amount of ionizing radiation. 

Info Link: http://www.msnbc.msn.com/id/42079799/ns/world_news-disaster_in_japan/?gt1=43001

You Can Help

And so, one way you – our ME-P readers and subscribers can help your fellow physicians who are already on the ground in Japan helping to care for the wounded – is to donate to Doctors Without Borders.

Donors can give between $35 to up to $10,000 or more directly on its website.

Thank you.

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Heathcare Administraton Dictionary Series

ADVERTISEMENT


Product DetailsProduct DetailsProduct Details      

Sample Front Matter Link:

9780826149947_chapter 

About the HCUPnet Data Base

An AHRQ Project

HCUPnet is a free, on-line query system based on data from the Healthcare Cost and Utilization Project (HCUP). It provides access to health statistics and information on hospital inpatient and emergency department utilization.

Link: http://hcupnet.ahrq.gov/HCUPnet.jsp

HCUPnet overview

HCUPnet is an on-line query system that gives you instant access to the largest set of all-payer health care databases that are publicly available. Using HCUPnet’s easy step-by-step query system, you can generate tables and graphs on national and regional statistics and trends for community hospitals in the U.S. In addition, community hospital data are available for those States that have agreed to participate in HCUPnet.

Community hospitals are defined as short-term, non-federal, general and other hospitals, excluding hospital units of other institutions (e.g., prisons). National and regional HCUP data include OB-GYN, ENT, orthopedic, cancer, pediatric, public, and academic medical hospitals. They exclude long term care, rehabilitation, psychiatric, and alcoholism and chemical dependency hospitals, but these types of discharges are included if they are from community hospitals.

The HCUP Project

HCUPnet is part of the Healthcare Cost and Utilization Project (HCUP) of the Agency for Healthcare Research and Quality (AHRQ). HCUPnet generates statistics using data from HCUP’s Nationwide Inpatient Sample (NIS), the Kids’ Inpatient Database (KID), the State Inpatient Databases (SID) and the State Emergency Department Databases (SEDD). These databases and HCUPnet would not be possible without the statewide data collection projects that provide data to HCUP. You can purchase many HCUP databases to do more detailed analyses not possible through HCUPnet. For more information on purchasing HCUP data go to: HCUP Central Distributor Web site

HCUPnet also provides statistics based on the AHRQ Quality Indicators (QIs) which have been applied to the HCUP Nationwide Inpatient Sample. These statistics provide insight into potential quality of care problems. You can download software for the QIs from the Quality Indicators Web site and apply them to your own data.

Assessment

Data from the following statewide data organizations appear in HCUPnet as part of the Nationwide Inpatient Sample (NIS), the Kids’ Inpatient Database (KID), State Inpatient Databases (SID) or as State Emergency Department Databases (SEDD):

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details 

Call for Authors, Contributors, Opinions and Essays

The Network and Forum for Doctors, and their Financial Advisors and Management Consultants

By Ann Miller RN MHA

[Executive-Director

MarcinkoAdvisors@msn.com

Join Our Mailing List 

The Medical Executive-Post publishes material that is practical, versatile, and user-friendly for our target audience in the integrated healthcare industrial and financial services complex. So, if you have an essay, article, op-ed piece or post proposal on a topic that would benefit our readers and subscribers, we would like to hear from you.

Topic Specificity

Or, become part of our ME-P search team and get published for fun and profit! We’ll give you an occasional topic, and you tell us how your life and medical or financial advisory practice has been affected by it. Just send in your best stories and musings in essay form.

Examples:

Doctors: tell us your most interesting Health 2.0 story from the patient clinical examination room.

Financial Advisors: tell us your most interesting Web 2.0 story from a physician-client engagement.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

Understanding MCO Fixed-Rate Contract Negotiations [Case Model]

The Hope Outreach Medical Clinic

By Staff Reporters

The Hope Outreach Medical Clinic (HOMC) is a private, for-profit, single specialty medical clinic in a south-eastern state.  It submitted its bi-annual Request for Proposal (RFP) to continue its current managed care fixed-rate contract.  Upon review of the RFP, however, Sunshine Indemnity Insurance Company, the managed care organization (MCO), denied the contract request for the upcoming year.

CEO Shock

In shock, the clinic’s CEO asked the clinic’s administrator to work with its legal team to develop a defensible estimate of economic damages that would occur as a result of the lost contract.  The clinic intended to bring suit against the MCO for breach-of-contract.  However, the administrator is not an attorney and is loathe to-enter the fray.  After consideration however, he decided to assist in filing the Statement of Claim (SOC) because he realized that changes in patient services (unit) volume would be a valid economic surrogate.  He then requested the following information from his controller, in order to develop a change in economic profit [damages] estimate:

  • Change in patient visits (unit) volume
  • Fees (price) per patient (unit)
  • Marginal (incremental) cost per patient (unit)
  • Change in current fees (prices)
  • Patient volume (units) affected

Key Issues:

1) Fee (price) per patient (units) may be obtained from the fee schedule used by the MCO to pay HOMC.

2) Marginal (incremental) costs per patient (unit) are approximated using variable costs.

3) Higher cost payers exist because lower patient volumes raise the average cost per patient (unit) due to existing fixed costs. The administrator’s financial work-product to estimate monetary damages and assist the legal team is explained as follows.

Assessment

Change in profit estimate by: www.MedicalBusinessAdvisors.com

Change-in-Profit = Change in patient (unit) volume X [Fee (price per patient unit) – Incremental (marginal) cost per patient (unit)] – [Change in current price (fees) X Patient (unit) volume affected].

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

Take the Accountable Care Act Survey

Please Vote

Join Our Mailing List 

QUERY: Should the Supreme Court decide the future of the Accountable Care Act?

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

About the Third and Fourth Stock Trading Markets

On OTC and Private Transactions

dem

By Dr. David Edward Marcinko MBA

http://www.CertifiedMedicalPlanner.org

Join Our Mailing List

In most cases, a market maker of a stock in the NASDAQ system must report his trade in 90 seconds, but there is another circumstance in which the trade must be reported. This is called the third market, and is defined as transactions in exchange listed securities in the OTC market.

For example, even though IBM is listed on the NYSE, an OTC market marking firm can acquire the IBM stock and begin to make a market for it just like an OTC stock. All of these trades are considered the third market, and are reported to the Consolidated Quotation System (CQS) within 90 seconds of the trade.

Fourth Market

The fourth market is defined as private transactions made directly between large investors, institutions such as banks, mutual funds, and insurance companies without the use of a securities firm.

In other words, fourth market trading is usually one institution swapping securities in its portfolio with another large institution. From the stock broker’s viewpoint, there is one problem with the fourth market.

Assessment

Since no broker/dealer is involved, no registered representative is involved and there is no commission to be earned. These trades are reported on a system called Instinet. This is advantageous to larger medial foundations or institutional investors.

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Planning your eMR Escape from IT Hell

Lessons I Learned in B-School

Dr. David Edward Marcinko MBA

[Publisher-in-Chief]

www.BusinessofMedicalPractice.com

Of course, as a doctor, you will spend weeks or months in the “sales and demo cycle” for selecting an EMR. If you’re lucky you will have time to consider all workflows; if you’re even luckier you will test drive the system and make sure training goes smoothly. You will also try to ensure that deployment will be easy. However, another thing not to forget is to plan how to get out of an HIT application or her system after it’s been installed for a while.

Why Get Out?

Why is getting out important? Every application looks better in a demo than in a working environment and every solution becomes “legacy” sooner or later. Every system will be replaced or augmented at some point in time. The cost of acquisition (“barrier to entry”) is well understood now as something we need to calculate. But the “barrier to exit” or switching cost is something you must calculate at the time you decide what systems to purchase.

If you can’t answer the “how, in 6, 18, or 24 months, will I be able to move on to the next-better technology or system?” Question if you’ve not completed your due diligence in the sales cycle. Vendor sales staff are quite reticent to answer the “how do I leave your system” question; you will need to press hard and ask for a plan before signing any contracts.

The Hard Questions

When preparing an RFI or RFP, ask eMR vendors specific questions about how easy it is to get out of their technology (rather than just how easy to it is to deploy and interoperate). Put in specific test cases and have your folks consider this fact when they are looking at all new purchases.

The Expert Speaks

And, according to HIT expert Shahid N. Shah MS, writing for Chapter 13 in the third edition of our book, the “Business of Medical Practice”, here are some specific factors to consider:

Front Matter Link: Front Matter BoMP – 3

  • Do you own your data or does the vendor? If you don’t have crystal clear statements in writing that the data is yours and that you can do whatever you want with it, don’t sign the contract. Look for a new vendor.
  • Is the database structure and all data easily accessible to you without involving the vendor? If only your vendor can see the data, you’re locked in so be very wary. Find out what database the vendor is using and make sure you can get to the database directly without needing their permission.
  • Are the data formats that the system uses to communicate with other vendors open? If not, you don’t own your data. Be sure that at least CCR and CCD formats are available and that all document data is accessible in standard PDF or MS Office friendly formats. Discrete data should be extractable in XML or HL7.
  • How much of the technology stack is based on industry standards? The more proprietary the tech, the more you’re locked in.
  • Are all the programming APIs open, documented, and available without paying royalties or license costs? If not, when you try to get out you’ll pay dearly.

Assessment

In B-school, back in the day, the first thing we learned when writing a business plan and/or seeking banking, angel or VC money was formulating an exit strategy. Or, how do I get my [own] investors money back? A lesson I still remember today and can apply to eMRs. How about you?

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details 

Understanding Workers’ Compensation

Join Our Mailing List

A Primer for the Physician Executive

By Dr. David Edward Marcinko MBA

[Publisher-in-Chief]

Workers’ Compensation is reported to be the largest line of commercial insurance, possibly because it is also a statutory obligation for employers, like doctors, who have common law employees.  Workers’ Compensation provides coverage for lost income due to on-the-job accidents or work-related disability or death, and benefits vary by state.  Its purpose is not only to provide these benefits but also to reduce potential litigation. Employees accepting the benefit payments from a Workers’ Compensation claim generally forego the right to sue their employer. Workers’ Compensation rates are established by job descriptions and commercial rates for the medical professional’s office are some of the lowest available.

The Methods

There are three methods of providing Workers’ Compensation coverage:

1.   Private commercial insurance

2.   Governmental insurance funds

3.   Self-insure

The medical professional may be inclined to the third method, especially in the larger offices. Since the weekly benefits are typically below $500, this would seem to make a lot of sense. But, as in larger groups, the officers and owners can elect not to be covered – it is usually more convenient for the medical professional to cover this risk with personal disability income insurance.

The Monopolistic States

There are, however, seven “monopolistic” states – Nevada, North Dakota, Ohio, Washington, West Virginia, and Wyoming – which do not permit private commercial insurance.

Assessment

Larger offices or companies, which wish to take more direct control of costs and benefit management, should consider self-insuring only after receiving expert advice.  This is one form of coverage that truly requires a trusted, knowledgeable insurance advisor.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

Blog for the ME-P

Informed Writers, Thought-Leaders and Experts Wanted

By Ann Miller RN MHA

[Executive-Director]

Send us your essays, op-ed pieces and /or blogs!

Contact us for more information if you are interested in writing a post or becoming a ME-P blogger. Amateurs, journalists and professionals invited.

Link: MarcinkoAdvisors@msn.com

Subscribe Now: Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Assessing Job [Dis]-Satisfaction Among Primary Care Doctors

Comment Period of Solicitation

By Staff Reporters

Join Our Mailing List 

A recent survey of 3,729 family care physicians found that 40.3% considered leaving their primary care practices, with 16.5% reporting that 2010 was the first year they had considered such a career change.

M3 Global Research

“The poll results are not surprising given the rising financial pressures for family practices,” said Craig Overpeck, chief operating officer of M3 Global Research.

“Only 15.6% hold out hope of 2011 being a better than average year for their personal income, with 17.7% forecasting 2011 to be one of the worst earning years of their career. The survey also reported only three out of five physicians enjoying better job satisfaction than they anticipated on their first day in medical school.”

The ME-P Wants to Know:

  • Are you satisfied with being a primary care physician?
  • Why or why not?
  • What do you think the main reasons are for dissatisfaction among primary care physicians?
  • Would you advise a medical student to go into primary care?

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

What are Exempt Securities?

Exemptions from the SEC Act of 1933

By Dr. David Edward Marcinko MBA CMP™

[Publisher-in-Chief]

Historical Definition

The SEC Act was landmark legislation that established the SEC and gives it authority over proxy solicitation and registration of organized stock exchanges. In addition, the Act sets disclosure requirements for securities in the secondary market, regulates insider trading, and gives the Federal Reserve authority over credit purchases of securities. When established, the Act reflected an effort to extend and overcome shortcomings of the Securities Act of 1933. These two pieces of legislation are the basis of securities regulation in the twentieth century.

Exemptions

Today, there are many securities which are exempt from the Securities Exchange Commission [SAC] Act of 1933, its’ registration and resuting prospectus requirements.

They include the following securities and types:

  • US Government and Federal Agency issues.
  • Municipal, State issues and commercial paper with a maturity not in excess of 270 days.
  • Intra-state offerings (Rule 147) because they are blue-sky chartered within the state.
  • Small Public offerings (Regulation A) if the value of the securities issued does not exceed $5,000,000 in any 12 month period. An issuer using the Regulation A exemption does not make the normal filings with the SEC in Washington. Instead, they file a simplified disclosure document with their SEC Regional Office, known as an Offering Statement. It must be file at least 10 business days prior to the initial offering of the securities.  No securities may be sold unless issuer has furnished an offering circular (full disclosure document) to the purchaser at least 48 hours prior to the mailing of confirmation of the sale, and, if not completed within 9 months from the date of the offering circular, a revised circular must be filed. Every 6 months, issuers must file a report with the SEC of sales made under the Regulation A exemption until offering is completed.
  • Traditional insurance policies are considered to be securities and are exempt, as are fixed annuities. However, some of the newer forms of life insurance, like variable life, as well as variable annuities, have investment characteristics and, therefore are not exempt from registration.
  • Commercial paper and banker’s acceptances (9 month or shorter maturity), since they are money market instruments.

Assessment

What did we miss?

Here is a guide to help understand how to raise capital and comply with federal securities laws.

Link: http://www.sec.gov/info/smallbus/qasbsec.htm

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details  Product Details

Product DetailsProduct DetailsProduct Details  

About the Mobile Health Market

Sensor-Based Mobile Apps Show How M-Health Business Models Could Work

By Markus Pohl

Join Our Mailing List 

Making money with mobile healthcare applications takes much more effort than most developers expected. M-Health apps normally do not get into the app stores’ top ranking lists and thus do not receive high download numbers.

m-Health Applications Business Models

But, there are working business models for the mHealth applications. Within the mobile health app category revenue won’t be generated through app stores. More and more mHealth app publishers have understood that they have to adapt their business model accordingly. Turning away from the “normal” pay-per-download models to practices like charging for medical service (call a doc) or sensor based models.

Sensor Based Models

Sensor based business models seem to have particularly caught the attention of mHealth app publishers over the last 6 months. The idea behind this model is not to sell an app but to use the app to promote the sales of a sensor. Revenue will be generated outside the app store.

Trend Examples: 

Here are some examples to highlight this trend.

  • Health and Wellness Monitoring tools combine fitness-related equipment to track pulse, calories, running speed, heart rate, or use sensor-devices to monitor weight control, fetus observation and eye testing. Target groups for these products are fitness and health-conscious users aged mainly between 35 and 45 years.
  • Chronic Condition Monitoring tools monitor health conditions like heart disease, hypertension, diabetes, asthma and obesity. They generate revenue from selling a sensor-device with a free application. Target groups are healthcare providers, medical personnel and chronically ill people between 30 and 50 years.
  • Diagnosis Tools are mainly targeted at professionals, who increasingly demand more portable and easy-to-use devices for easier communication with patients and peers.
  • Educational and Motivational Tools monitor habit patterns (e.g. sleep monitoring via app/device) or serve as useful didactic instruments for science education (e.g. portable microscopes).

Traditional health care service providers and especially medical device manufacturers should be aware of these trends and start to connect to the smartphone world.

To find a detailed overview of mHealth business models – please see the Mobile Health Market Report 2010-2015. Or, take a look at more mobile healthcare research from research2guidance.

Assessment

Outside app store revenue will drive the market. Sensor-based business models prove how to actually make money with mobile applications.

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details 

Treatment for Plantar Fasciitis is Expensive and Ineffective

Plantar Fasciitis Truth

By Angry Orthopod, MD

There are nearly 2 million cases of plantar fasciitis in the United States every year. As an orthopaedic surgeon, I’m quite familiar with this issue since nearly 20 percent of my patients come to me about plantar fasciitis.

Although there is a surefire way to fix the problem, the current treatments aren’t really addressing the issue, and they are costing millions for those who suffer from the heel pain. Many are quick to blame the chosen treatments on profit, but I’m here to set the record straight.

Two Factors

There are two main factors that are contributors to mistreatment, neither of which is profit. Many doctors dealing with plantar fasciitis think their treatment plans are the right course of action. That is, expensive surgeries, useless orthotics, and temporary relief through medicine. The other factor leading to the mistreatment is that patients are demanding these treatments; despite how medical studies have shown they are ineffective. Many believe that a surgery will fix their plantar fasciitis problems; it’s a misconception that surgery is what they need.

Expensive Treatments

Honestly, I don’t think the patients or the doctors know how expensive these treatments end up. In 2007 alone, there was an estimated $376 million in expenses for third parties. But what about the patient costs?

The authors of this study revealed that this estimate is low, and I have to agree; it’s definitely a conservative number since the patient’s expenses aren’t part of the study. The study doesn’t take into account lost time from work, OTC items, chiropractic visits, acupuncture, night splints, diagnostic studies, among other costs.

Study: 2010_American_Journal_of_Orthopedics

Assessment

So what should we learn from this? An exorbitant amount of money is spent on these treatments every year, but the real issue isn’t just the expense, it’s that most treatments are unnecessary and ineffective.

How much have you paid to relieve your plantar fasciitis problems? Were the treatments effective?

Link: http://www.plantarfasciitistruth.com/

Conclusion: The “Angry Orthopod” is an orthopedic surgeon who blogs at his self-titled site, The Angry Orthopod. And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

   Product Details 

Understanding Over the Counter (OTC) Markets

A Decentralized, Dealer-2-Dealer Market

By Dr. David Edward Marcinko MBA

[Publisher-in-Chief]       

www.CertifiedMedicalPlanner.com

Securities are bought and sold every day by physicians and other investors who never meet each other. The market impersonally enables transfer (or sale) of securities from individuals who are selling to those who are buying. These trades may occur on an organized exchange such as the New York Stock Exchange, or, a decentralized, dealer to dealer market, which is called the over-the-counter (OTC).  Any transaction that does not take place on the floor of an exchange, takes place over-the-counter.

A Negotiated Market

The over-the-counter market is a national negotiated market, without a central market place, without a trading floor, composed of a network of thousands of brokers and dealers who make securities transactions for themselves and their customers. Professional buyers and sellers seek each other out electronically and by telephone and negotiate prices on the most favorable basis that can be achieved. Often, these negotiations are accomplished in a matter of seconds, there is no auction procedure comparable to that on the floor of an exchange.

The over-the-counter market is far the largest market in terms of numbers of securities issues traded. There are over 40,000 issues on which regular quotations are published OTC, while there are less than 5,000 stocks listed on all securities exchanges. There are frequently days when the reported volume of over-the-counter trades exceeds that of the NYSE. What really is the over-the-counter market? Is it where securities of inferior quality trade? Here is a list to remember of the types of securities traded exclusively over-the-counter:

  • All Government bonds .
  • All municipal bonds.
  • All mutual funds.
  • All new issues (primary distributions).
  • All variable annuities.
  • All tax shelter programs.
  • All equipment trust certificates.

Of course, the OTC market is also where all of the “unseasoned” issues are traded and most of them are quite speculative, but there certainly are many high quality issues available over-the- counter. Now, let’s take a look at how this over-the-counter market works.

The Market Maker

Whereas, the “main player” on the exchange is the specialist, his OTC counter part, in terms of importance, is the market maker. In the over-the-counter market, many securities firms act as dealers by creating and maintaining markets in selected securities. Dealers act as principals in a securities transaction and buy and sell securities for their own account and risk. Since they do not act as agents or brokers but instead as principals or dealers in securities transactions, they do not receive any commission for their services but instead buy at one price and sell at a higher price making a profit from “mark-up” on the security price. A dealer is said to have a position in a stock when he purchases and holds a security in his inventory. He, of course takes a risk that the market price of the security he holds may decline in value. This is how dealers make money; they buy wholesale and sell it retail, and the physician investor pays retail.

The OTC market bears little resemblance to the one of the mid-sixties. The major difference has been the electronic technological advances as embodied by the NASDAQ system. NASDAQ stands for National Association of Securities Dealers Automated Quotation system. Back in 1966, if you wanted to find out who was the market maker in the particular security you would go to a brightly colored stack of papers called the pink sheets, containing a listing, alphabetically, of over-the-counter stocks and underneath each issue is listed the name of one or more market makers, securities firms willing to trade that stock. After each firm name is the firm’s telephone number and a ‘bid and ask price”, that is, an approximate price representing what the dealer is asking for the stock and is bidding for the stock. 

Back 35-40 years ago, the only way of locating a market maker was by using the pink sheets, while O-T-C traded corporate bonds are quoted on yellow sheets. Under certain conditions, it could take a good deal of effort to try to get the best deal. Today, with the computer that sits on doctor’s desks, or a mobile device or smart-phone, you can push a few buttons and instantaneously see the best bid and the best offer that exists right now on over 5,000 of the most active over-the- counter stocks. Not only that, you can pull up the names of every market maker in that particular stock and the actual (firm) quotes on those securities right now.

Join Our Mailing List

Electronic Sources of Securities Information

Level 1 service, available on the stock broker’s desk top, provides price information only on the highest bid and the lowest offer (the inside market). No market makers are identified, and since this is an inside quote, it may not be used by the registered representative (stock broker) for giving firm quotes. 

Level 2 service provides a doctor subscriber with price information and quotation sizes of all participating registered market makers. When a trader, or medical investor, looks at his computer screen on Level 2, he sees who’s making a market, their firm bid – or – ask; and the size of the market. One can get firm calls from level 2 information.

Level 3 service takes it one step further; and allows registered market makers to enter bid and ask prices (quotes) and quotation sizes into the NASDAQ system and to report their trades. This is the level of service maintained by market makers.

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details  Product Details

Next Generation Physician Recruitment

Filling the Funnel with Candidates

By Susan L. Theuns; PA-C, CPC, CHC

The best-kept secret about physician recruiting is to keep the funnel filled with a pool of candidates. With the dearth of primary care physicians – and some specialists for example – modern healthcare organizations can’t afford to wait for doctors to beat a path to their door; they have to go after the physicians they want.  That means generating a sizeable list of prospects on the front end to narrow it down to the 100 or so doctors who will be called for an initial conversation.  From there, the team may do some 50 telephone screening interviews to generate five site visits in order to select the one perfectly matched prospect who will sign on the dotted line.

The Prospect List

Depending upon the opportunity, there are a number of ways to generate a list of prospects:

  • Direct mail using a purchased list of physicians culled from criteria such as medical specialty and current geographical location.  The American Board of Medical Specialties, the American Medical Association [AMA], and licensure boards can supply these lists.  The organization sends direct mail announcing the opportunity and then has a team member follow-up with outbound calling.  If the physician is not interested, the caller should ask if s/he knows someone who is.
  • Personal calls following recruitment fairs and specialty meetings.
  • Advertising in medical and specialty journals and on the web, Twitter, etc.
  • Resident campaign using posted flyers and announcements.
  • Physician networking based on group member recommendations.
  • Medical Staff Office contacts at the local hospital.
  • Networking through specialty or group management organizations. Some organizations offer free on-line job postings for members.
  • Affiliations with residency programs.

Screenings and Interviews

From the initial pool of candidates, the internal recruiter must call prospects and conduct preliminary screenings to verify licensure status and board certification, gather professional and personal details about the candidate, and answer his or her questions about the opportunity. Whenever possible, research should be done to secure the prospect’s home or cell telephone number. Calling prospects in the evening at home gives them more time and privacy to talk freely.

www.BusinessofMedicalPractice.com

Assessment

Although this screening step generates a smaller list of credible prospects that meet the search criteria generated at the beginning of the recruitment process, it is a more viable one.

Front Matter: Front Matter BoMP – 3

About the Author: Susan Theuns has an extensive background in healthcare, business management, facilities/operations and compliance that spans three decades. She holds degrees in Allied Health and Business Management and has been a Certified Physician Assistant for 32 years. She is also a Certified Professional Coder and is certified in Healthcare Compliance. Susan has published a variety of articles for Coding Edge, Healthcare Compliance Today, and the Group Practice Journal and serves on the Advisory Board for Ingenix.  Her professional memberships and affiliations include the American Medical Group Association, National Honor Society in Business Administration (Delta Mu Delta), Health Care Compliance Association, American Academy of Professional Coders, and the National Commission on Certification of Physician Assistants. She was MedStar Health’s Compliance Director of the Year in 2003 and is currently Administrative Director of Physician Practices for Union Memorial Hospital in Baltimore, Maryland. 

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details 

Assessing the Affordable Care Act

Comment Period of Solicitation

By Staff Reporters

Join Our Mailing List 

Last week marked the first anniversary of the Affordable Care Act (ACA) being signed into law by President Obama, and one year into the new era of health care reform it’s clear that Americans remain divided in their views on the ACA.

Depending on the source, polls show the public remains confused about many aspects of the law, with mixed support for several provisions and strong opposition to the individual mandate and other parts of the ACA.

Legal Challenges

With several lawsuits challenging the constitutionality of the ACA, governors and state legislators vowing to refuse funding to implement certain ACA programs, and Congress poised to revise or repeal some or all of the law, opponents of the ACA are hopeful that they will have the chance to go back to the drawing board to craft reform legislation more to their liking.

Supporters

Meanwhile, supporters are pointing to widespread public approval of many of the insurance reforms in the law and claiming that once the health exchanges and other major components of the ACA take effect, public support will continue to grow.

The ME-P Wants to Know:

  • Has your support for the ACA changed at all in the year since it was signed into law?
  • Are you pleased with the outcomes to date of the Affordable Care Act?
  • Will the major provisions that have not yet been implemented be able to fulfill the stated goal of covering more patients while reducing overall health care costs?
  • If you are not a supporter of this law, which sections are in most need of revision? Or are you in favor of complete repeal of this law?
  • If you prefer repeal, what alternative approach to health care reform do you favor?

Assessment

Please opine in the comment box below.

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details 

About Physician Executive Bonus Plans

A Primer for Physicians

By Dr. David Edward Marcinko MBA

[Publisher-in-Chief]

An executive bonus plan (or § 162 plan) is an effective way for a medical practice, clinic or other healthcare company to provide valued, select physician or other employees an additional employment benefit.  One of the main advantages to an executive bonus plan, when compared to other benefits, is its simplicity. In a typical executive bonus plan, an agreement is made between the employer and employee, whereby the employer agrees to pay for the cost of a life insurance policy, in the form of a bonus, on the life of the employee.

Benefits

The major benefits of such a plan to the employee are that he or she is the immediate owner of the cash values and the death benefit provided.  The only cost to the employee is the payment of income tax on any bonus received.  The employer receives a tax deduction for providing the benefit, improves the moral of its selected employees, and can use the plan as a tool to attract additional talent.

Example Dr. Stern is a sole practitioner in rural West Virginia.  Among his employees is Nurse Jackson, who has been with him for over ten years.  She is the single parent for two boys.   Although he pays well, and provides additional benefits, he has been looking for a way to selectively reward Nurse Jackson for her years of service and hard work.  Recently Nurse Jackson has expressed a concern for her children if she were to die prematurely.

Dr. Stern chooses to provide an executive bonus plan by allowing Nurse Jackson to purchase a life insurance policy on her life.  Dr. Stern will provide the premium payments in the form of a bonus to her.  Nurse Jackson must simply pay the tax on this additional income.  Dr. Stern’s practice will get a tax deduction for the premium and improve the morale of an important employee.  Nurse Jackson will get needed protection for her family.

Assessment

More info: http://www.jblearning.com/catalog/9780763733421/

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details 

The Truth about Frivolous Tax Arguments

An IRS Warning Report for Doctors and All Citizens

[No Lame Excuses]

By Staff Reporters

Join Our Mailing List 

This IRS report responds to some of the more common frivolous “legal” arguments made by individuals and groups who oppose compliance with the federal tax laws.

Three Parts

The first section groups these arguments under six general categories, with variations within each category. Each contention is briefly explained, followed by a discussion of the legal authority that rejects the contention.

The second section responds to some of the more common frivolous arguments made in collection due process cases brought pursuant to sections 6320 or 6330. These arguments are grouped under ten general categories and contain a brief description of each contention followed by a discussion of the correct legal authority.

A final section explains the penalties that the courts may impose on those who pursue tax cases on frivolous grounds. It should be noted that the cases cited as relevant legal authority are illustrative and are not intended to provide an all-inclusive list relating to frivolous tax arguments.

Link: http://www.irs.gov/taxpros/article/0,,id=159853,00.html

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko 

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

About the Patient Choice Act

On HR 2520

By Staff Reporters

Join Our Mailing List

Austin Frakt PhD, over at www.TheIncidentalEconomist.com has been writing that many of the policy attributes, mechanisms and challenges facing the Affordable Care Act (ACA) are similar to those of the Ryan-Rivlin plan and what Ezra Klein calls Ryan-Coburn. 

http://theincidentaleconomist.com/wordpress/ryan-coburn-ryan-rivlin-and-aca/?utm_source=feedburner&utm_medium=email&utm_campaign=Feed%3A+TheIncidentalEconomist+%28The+Incidental+Economist+%28Posts%29%29

The PCA

Ryan-Coburn is The Patients’ Choice Act (PCA) that was introduced into the last Congress, and is what may be the most comprehensive Republican health reform proposal put into bill form.  Co-sponsor Sen. Richard Burr (R-NC) has said the PCA will be reintroduced in this Congress. 

Assessment

Act Link: Patient Choice Act

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko 

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise


Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details 


Mike Kitces asks: What Can Financial Planners Learn from Suze Orman and Dave Ramsey?

Join Our Mailing List

Follow Paretto’s Law – or Learn Something Unique and Compete?

By Dr. David Edward Marcinko; FACFAS, MBA, CMP™

[Publisher-in-Chief]

Michael Kitces is an industry pundit, and well known certified financial planner [CFP], who writes for a financial advisory and financial planner audience at thewebsite Nerd’s Eye View:

http://www.kitces.com

He is a bright guy, who holds the following professional degrees and designations:

  • MSFS – Master of Science in Financial Services
  • MTAX – Master’s in Taxation
  • CFP – Certified Financial Planner
  • CLU – Chartered Life Underwriter
  • ChFC – Chartered Financial Consultant
  • RHU – Registered Health Underwriter
  • REBC – Registered Employee Benefits Consultant
  • CASL – Chartered Advisor of Senior Living
  • CWPP – Chartered Wealth Preservation Planner

Yet, in a recent essay, he laments that all the CFPs® in the country added together don’t have as much reach, or impact, as three mass marketing gurus: Suze Orman, David Bach, and Dave Ramsey. And, he is correct.

Markets Vary

These gurus, and the CFPs®, serve different markets for sure. The gurus’ products are free or inexpensive. Their messages are simple and actionable. Once you go beyond the simple messages, however, you will find the gurus no longer satisfying. So, it’s no coincidence that the three gurus focus on controlling spending and getting out of debt. Why?

Eighty percent of us do need to get out of debt and control our spending, period!

Link: Do Financial Planners Have Something To Learn From Suze Orman and Dave Ramsey?

Pareto’s Law

Here is where the mass market is located, said economist V. Pareto PhD more than a century ago. The Pareto principle (also known as the 80-20 rule, the law of the vital few, or the principle of scarsity) states that, for many events, roughly 80% of the effects come from 20% of the causes. It is a common thumb-rule in business; e.g., “80% of your sales come from 20% of your clients”.

Look, most clients can’t control their income but they can be taught to control spending and debt habits [needs versus wants]. Most patients need a family doctor; not a brain surgeon.  And, most of us do not have Einstein’s intelligence, Gate’s wealth, or Hercules’s strength.

But, our lives can vastly be improved by 80%, with just 20% more effort and cost. This is what the gurus know – most of us are average – not so the CFPs® who believe we all need a comprehensive financial plan and have the ability to pay for it and the time to execute and monitor it.

Assessment

And so, CFPs® can’t charge an 80% premium – to 80% of the population – when clients don’t need or want a comprehensive financial plan. Or, when clients can be better off by 80%, and such success can be had for 20% of the cost and effort offered by the CFPs®.

Basic supply-demand economics 101! Ford autos are fine – we all don’t need or want a Mercedes.

More confusing is the fact that even the CFPs® themselves are suspect since prior to 2008 a college degree was not required for the certification mark. And, having same allows the practitioner no additional diagnostic or interventional tools.

IOW: Whatever a CFP® can do – a non-CFP® can do.  And, it is increasingly considered by the well-informed …. to be a marketing mark …. to hold a marketing mark. This is akin to being famous; for being famous.  That’s why I resigned my CFP® mark years ago.

Full Disclosure: I am the Founder of the: http://www.CertifiedMedicalPlanner.org online program. CMP™ certificants – like doctors – hold fiduciary accountability at all times and with unique healthcare industry specificity.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:


Product DetailsProduct Details

  Product Details

   Product Details 

Search Guidance for a Chief Medical Security Officer

A Business Case Model

By Richard J. Mata MD MS CIS

Dr. Mata

Join Our Mailing List

The Mighty-Soft Hospital is a futuristic 1,500 bed fortress-like facility operating with a state-of-the-art dual wired-wireless infrastructure complete with computerized physician order entry  system, radio frequency inventory device (RFID) control tags, and integrated electronic medical records (EMRs) that are the envy of its competitors and vendors, and offer a formidable strategic competitive advantage in the marketplace.

Now, imagine the potential liability, PR disaster and chagrin when its enfant terrible CEO is told of a massive security breach similar to the ChoicePoint and Lexis-Nexis fiascos.  The ID theft involves release of critically protected healthcare financial, employment, clinical, and contact information for all of its patients, employees, physicians, business associates, and affiliated medical personnel.

Suddenly, senior management is charged with the task of establishing the new position of Chief Medical Security Officer (CMSO) for Mighty-Soft, and navigating a crisis management dilemma never previously faced by the formerly HIPAA-compliant electronic giant.

The CMSO is to be a senior level management position responsible for championing institutional security.  Awareness of electronic and HIPAA policy and procedure developments, while working to ensure compliance with internal and external standards related to information security, is vital.  The CMSO is to report directly to the CEO and the CIO.

The Search Committee developed the following list of CMSO duties and responsibilities:

  • Chair the hospital’s Information Security and Privacy Committee in its policy development efforts to maintain the security and integrity of information assets in compliance with state and federal laws, and accreditation standards.
  • Provide project management and operational responsibility for the administration, coordination, and implementation of information security policies and procedures across the enterprise-wide hospital system.
  • Perform periodic information security risk assessments including disaster recovery and contingency planning, and coordinate internal audits to ensure that appropriate access to information assets is maintained.
  • Work with the financial division to coordinate a business recovery plan.
  • Serve as a central repository for information security-related issues and performance indicators.  Research security or database software for implementing the central repository, and note that a server based system could be useful for a Wide Area Network (WAN), so this information can be shared with the enterprise-wide hospital system.  Develop, implement, and administer a coordinated process for response to such issues.
  • Function when necessary as an approval authority for platform and/or application security and coordinate efforts to educate the hospital community in good information security practices.
  • Maintain a broad understanding of federal and state laws relating to information security and privacy, security policies, industry best practices, exposures, and their application to the healthcare information technology environment.
  • Make recommendations for short- and long-range security planning in response to future systems, new technology, and new organizational challenges.
  • Act as an advocate for security and privacy on internal and external committees as necessary.
  • Develop, maintain, and administer the security budget required to fulfill organizational information security expectations.
  • Demonstrate effectiveness with consensus building, policy development, and verbal and written communication skills.
  • Possess the clear ability to explain information technology concepts to audiences outside the field.
  • Become the public face for the Mighty-Soft Hospital’s legacy security system.

Minimum Qualifications:

  • MD, DO, DPM, DDS, DMD, with bachelor’s/master’s degree in computer science or related field or equivalent experience.
  • Three or more years of experience in the healthcare industry.
  • Five or more years of experience in information security.
  • Eight or more years of experience in information technology.
  • In-depth understanding of network and system security technology and practices across all major computing areas (mainframe, client/server, PC/LAN, telephony) with a special emphasis on Internet related technology.

Preferred Qualifications:

  • Experience with electronic medical devices.
  • Specific experiences in the healthcare industry.
  • Familiarity with legislation and standards for PHI and patient privacy.
  • Demonstrated successful project management expertise.
  • Professional certification, e.g., CISSP, CISA, PMP.
  • Experience with student record/higher education laws.

Key Issues:

  • What is your IT hardware infrastructure and how are security-related devices deployed?
  • What security requirements are imposed by federal and state authorities on your institution?
  • What would you consider the most important criteria for choosing a CMSO?
  • What relationship will the CMSO have with the CIO, CMIO and CEO?
  • What level of security education/training do you consider necessary for your hospital community?
  • What are the key security issues your CMSO will have to address?
  • What are the key privacy issues?
  • What are the key risk management issues?
  • What are the pros and cons of EHRs for your institution?
  • What do you see as the EHR priorities for your CMSO?
  • What are the security issues of EHRs for your institution?

Assessment

How would you select a CMSO?

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

Understanding MCO-Medical Practice Contract Standards

The Conversion to Negotiated Managed Healthcare is Significant

Dr. David Edward Marcinko, MBA CMP™

Prof. Hope Rachel Hetico, RN MHA CPHQ CMP™

www.BusinessofMedicalPractice.com

The conversion to managed healthcare and capitation financing is a significant marketing force and not merely a temporary business trend. More than 60% of all physicians in the country are now employees of a MCO. Those that embrace these forces will thrive, while those opposed will not.

Developing an Attractive Practice

After you have evaluated the HMOs in your geographic area, you must then make your practice more attractive to them, since there are far too many physicians in most regions today. The following issues are considered by most MCO financial managers and business experts, as they decide whether or not to include you in their network:

General Standards

  • Is there a local or community need for your practice, with a sound patient base that is not too small or large? Remember, practices that already have a significant number of patients have some form of leverage since MCOs know that patients do not like switching their primary care doctors or pediatricians, and women do not want to be forced to change their OB/GYN specialist. If the group leaves the plan, members may complain to their employers and give a negative impression of the plan.
  • A positive return on investment (ROI) from your economically sound practice is important to MCOs because they wish to continue their relationship with you. Often, this means it is difficult for younger practitioners to enter a plan, since plan actuaries realize that there is a high attrition rate among new practitioners. They also realize that more established practices have high overhead costs and may tend to enter into less lucrative contract offerings just to pay the bills.
  • A merger or acquisition is a strategy for the MCO internal business plan that affords a seamless union should a practice decide to sell out or consolidate at a later date. Therefore, a strategy should include things such as: strong managerial and cost accounting principles, a group identity rather than individual mindset, profitability, transferable systems and processes, a corporate form of business, and a vertically integrated organization if the practice is a multi-specialty group.
  • Human resources, capital, and IT service should complement the existing management information system (MIS) framework. This is often difficult for the solo or small group practice and may indicate the need to consolidate with similar groups to achieve needed economies of scale and capital, especially in areas of high MCO penetration.
  • Consolidated financial statements should conform to Generally Accepted Accounting Principles (GAAP), Internal Revenue Code (IRC), Office of the Inspector General (OIG), and other appraisal standards.
  • Strong and respected MD leadership in the medical and business community is an asset. MCOs prefer to deal with physician executives with advanced degrees. You may not need a MBA or CPA, but you should be familiar with basic business, managerial, and financial principles. This includes a conceptual understanding of horizontal and vertical integration, cost principles, cost volume analysis, financial ratio analysis, and cost behavior.
  • The doctors on staff should be willing to treat all conditions and types of patients. The adage “more risk equates to more reward” is still applicable and most groups should take all the full risk contracting they can handle, providing they are not pooled contracts.
  • Are you a team player or solo act? The former personality type might do better in a group or MCO-driven practice, while a fee-for-service market is still possible and may be better suited to the latter personality type.
  • Each member of a physician group, or a solo doctor, should have a valid license, DEA narcotics license, continuing medical education, adequate malpractice insurance, board qualification or certification, hospital privileges, agree with the managed care philosophy, and have partners in a group practice that meet all the same participation criteria. Be available for periodic MCO review by a company representative.

Specific Medical Office Standards

MCOs may require that the following standards are maintained in the medical office setting:

  • It is clean and presentable with a professional appearance.
  • It is readily accessible and has a barrier-free design (see OSHA requirements).
  • There is appropriate medical emergency and resuscitation equipment.
  • The waiting room can accommodate 5 – 7 patients with private changing areas.
  • There is an adequate capacity (e.g., 5,000 – 10,000 member minimum), business plan, and office assistants for the plan.
  • There is an office hour minimum (e.g., 20 hours/week).
  • 24/7 on-call coverage is available, with electronic tracking and eMRs.
  • There are MCO-approved sub-contractors.

Assessment

What have we missed?

Front Matter Link: Front Matter BoMP – 3


Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details 

Learning from a Hospital Cash Flow Management Case Model

Join Our Mailing List

The Mackenzie Hospital Clinic

[By Staff Reporters]


The Mackenzie Hospital Clinic was offered a private fixed-rate MCO contract that would increase revenues by $50,000 for the next fiscal year. The clinic’s 30% gross margin would not change because of the new business.

However, $10,000 would be added to overhead expenses for another part-time assistant. More importantly, the AR collection time would be lengthened to one year, or paid at the end of the contract period.

The cost of services provided for the contract represents the amount of money needed to service the patients produced by the contract. Since gross margin is 30% of revenues, the cost of services is 70% or $35,000.

The financial manager had to decide whether there would be enough internally generated cash flow to accept the contract.

The Financial Facts

The manager knew that adding the extra overhead would result in $45,000 of new spending money (cash flow) needed to care for the patients. He had to further refine his calculations by dividing the $45,000 total by the number of days the contract extends (i.e., 365 days) to determine that the new contract would cost about $123.29 per day of cash flow. Now, the financial manger had to ask: where would the money come from?

He was reluctant to turn away any business for the clinic, so decided he must develop other methods to generate the additional cash. He made the following suggestions:

  • extend AP timelines and reduce AR times; and/or
  • borrow with short-term bridge loans or a line of credit; and/or
  • discuss the situation with vendors for longer or more favorable terms; and
  • do not stop paying corporate taxes.

Key Issues:

1) Consider what changes the Mackenzie Hospital Clinic might implement to ensure that it regularly makes good cash management, budgeting, and risk projection decisions?

2) If the Mackenzie Hospital Clinic is successful and attracts more long-term managed care fixed contracts, the serious nature of the cash flow problem becomes apparent. For instance, adding another nine contracts would multiply the above example tenfold. In other words, the clinic would increase revenues to $1 million with the same 70% cost of services and $100,000 increases in operating overhead expenses.

3) How much free cash flow would be required?

[Using identical mathematical calculations, we determine that $450,000/365 days equals $1,232.88 per day of needed new cash flow.]

4) What happens if the contract only pays off at the end of the year?

Assessment

Any other thoughts?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Healthcare Reform at a Glance

A One-Stop-Look-See with Comparisons

By Staff Reporters

Link: Health-Care-Reform-Comparison-in-Brief

[Courtesy: BuckConsultants]

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details 

Not so Fast – Examining eMR Options and Alternatives

Look Before you Leap

By Shahid N. Shah MS

Because of all the talk about electronic medical records [EMRs] and medical records software, doctors have many reasons to start immediately looking for an EMR vendor.

But, try to resist that urge and look at broader non-EMR solutions that can help remove some of the non-clinical burdens from your staff.

Here are some examples from Chapter 13, in our new book: www.BusinessofMedicalPractice.com

  • Using Microsoft Office Outlook® or an online calendaring system like Google to maintain patient schedules. While most vendors of clinical scheduling will tell you that medical scheduling is too complex to be handled by non-medical scheduling systems, most small and medium sized physician practices can easily get by with free or very inexpensive and non-specialized scheduling tools. By using general-purpose scheduling tools you will find that you can use less expensive consultants or IT help to manage your patient scheduling technology needs.
  • Using off-the-shelf address book software such as those built into Microsoft Office®, the Windows® and Macintosh® operating systems, or online tools such as Google apps you can maintain complete patient and contact registries for managing your patient lists. While a patient registry may not give you all of the features and functions you need immediately they can grow to a system that will meet your needs over time.
  • Using physician practice management systems you can remove much of the financial bookkeeping and insurance record-keeping burdens from your staff. Unlike calendaring or address book functionality which can be adapted from non-medical systems, insurance claims and related bookkeeping is an area where you should choose specific software based on how your practice earns its revenue. For example if a majority of your claims are Medicare related, then you should choose software that is specifically geared towards government claims management. If however your revenue comes less from insurance and more from traditional cash or related means you can easily use small business accounting software like Quicken® or Microsoft accounting.
  • Using computer telephony technology you can integrate automatic call in and call out the services that can be tied to your phone system so that you can track phone calls or send out call reminders.
  • Using integrated medical devices that can capture, collect, and transmit physiological patient data you can reduce paper capture of vital signs and other clinical data so that your staff are freed to do other work.
  • Using e-mail, instant messaging, social networking, and other online advanced tools you can reduce the number of phone calls that your practice receives and needs to return and yet continue to improve the patient physician communication process. One of the most time-consuming parts of any office is the back-and-forth phone calls so any reduction in phone calls will yield significant productivity increases.

Assessment

Any other ideas?

Link: Front Matter BoMP – 3

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product Details 

Self-Branding For Physicians

In the Modern Era

[By Eugene Schmuckler PhD, MBA]

www.BusinessofMedicalPractice.com

Join Our Mailing List 

In 1987 the magazine Fast Company published an article authored by Tom Peters entitled “The Brand Called You.” Although some individuals may shy away from the concept of self-branding in actuality, many of the online social network sites such as Facebook become media by which we in fact brand ourselves. In his article, Peter’s stated. “Regardless of position, regardless of the business we happen to be in, all of us need to understand the importance of branding.

Me, Inc

We are CEOs of their own companies: Me Inc. to be in business today, our most important job is to be head marketer for the brand called you. As a medical practitioner how do you differentiate yourself from others in your specialty and why should a new patient choose your practice above those of the others in the field? Branding is about finding your big idea and building your identity and game plan around it. The bottom line: if you can’t explain who you are, and the value you bring to your practice in a short sentence or two, you have work to do.

Coaching

According to Catherine Kaputa, a personal coach she suggests that there are the objective things: your credentials, the schools you went to, your years of experience, and your skill set, which represent what she refers to as hard power. Then there’s soft power: your image and reputation, your visibility in the community, your network of contacts, supporters and mentors. In today’s competitive marketplace, soft power plays a vital role in attracting people to you and your practice.

Stand Out

Peters suggests that everyone has a chance to stand out. Everyone has a chance to learn, improve, and build up their skills. Everyone has a chance to be a brand worthy of remark. Corporations spend millions of dollars creating and maintaining their distinct brand. The Olympic Rings are representative of a brand which the International Olympic Committee guards zealously.

CMP

Self-Branding

Professional services firms such as McKinsey, foster self-branding among their employees. Major corporations have as employees those individuals who are smart, motivated and talented. Self-branding allows the employees to differentiate themselves from their peers.

For one to engage in self-branding is first necessary to ask the question, “What is it that my practice does that makes it different?” You can begin by identifying the qualities or characteristics that make you distinctive from your competitors-or your colleagues. What have you done lately-this week-to make yourself stand out? What would your colleagues say is your greatest and clearest strength? What would they say is your most noteworthy personal trait?

Assessment

As a medical practitioner does your patient-customer get dependable, reliable service that meets his or her strategic needs?

In addition, ask yourself: “what do I do that adds remarkable, measurable, distinguished distinctive value.”

BRANDING WHITE PAPER: Leadership Self Branding MARCINKO

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: https://medicalexecutivepost.com/dr-david-marcinkos-bookings/

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

   Product Details 

***

Financial Life Planning Defined for Physicians and Advisors

Integrating Financial Planning, Practice Management and Life

By Dr. David Edward Marcinko MBA, CMP™

www.CertifiedMedicalPlanner.com

Life planning has many detractors and defenders. Formally, it has been defined by Mitch Anthony, Gene R. Lawrence and Roy T. Diliberto of the Financial Life Institute, in the following trinitarian way.

Financial Life Planning is an approach to financial planning that places the history, transitions, goals, and principles of the client at the center of the planning process.  For the financial advisor or planner, the life of the client becomes the axis around which financial planning develops and evolves.

Other definitions are: 

  • Financial Life Planning is about coming to the right answers by asking the right questions. This involves broadening the conversation beyond investment selection and asset management to exploring life issues as they relate to money.
  • Financial Life Planning is a process that helps advisors move their practice from financial transaction thinking, to life transition thinking. The first step aiming to help clients “see” the connection between their financial lives and the challenges and opportunities inherent in each life transition.

But, for informed physicians, life planning’s quasi-professional and informal approach to the largely isolate disciplines of financial planning and medical practice management is inadequate. Today’s practice environment is incredibly complex, as compressed economic stress from HMOs, financial insecurity from Wall Street, liability fears from attorneys, criminal scrutiny from government agencies, IT mischief from malicious hackers, economic benchmarking from hospitals and lost confidence from patients all converge to inspire a robust new financial planning approach for medical professionals. Now, add politics and the ACA of 2010.

Our Approach

The iMBA approach to financial planning, as championed by the Certified Medical Planner, integrates the traditional concepts of financial life planning, with the increasing complex business concepts of medical practice management. The former are presented in our textbook on financial planning for doctors. And, the later is in our companion book: “The Business of Medical Practice” www.BusinessofMedicalPractice.com

Others on risk management and insurance; accounting, tax and investing; retirement, practice succession and estate planning, are planned in our future iMBA Handbook series for physicians and their advisors www.MedicalBusinessAdvisors.com

Example

For example, views of medical practice, personal lifestyle, investing and retirement, both what they are and how they may look in the future, are rapidly changing as the retail mentality of medicine is replaced with a wholesale philosophy. Or, how views on maximizing current practice income might be more profitably sacrificed for the potential of greater wealth upon eventual practice sale and disposition. Or, how the ultimate fear represented by Yale University economist Robert J Shiller, in “The New Financial Order”: Risk in the 21st Century, warns that the risk for choosing the wrong profession or specialty, might render physicians obsolete by technological changes, managed care systems or fiscally unsound demographics.

Assessment

Yet, the opportunity to re-vise the future at any age through personal re-engineering, exists for all of us, and allows a joint exploration of the meaning and purpose in life. To allow this deeper and more realistic approach, the advisor and the doctor must build relationships based on trust, greater self-knowledge and true medical business and financial enhancement acumen.

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details

Seeking Healthcare Administration Experts and Contributing Print Authors

Healthcare Organizations [second edition]

By Ann Miller RN MHA

[Executive-Director]

Join Our Mailing List 

Greetings ME-P Readers, Experts and Subscribers,

As you may know, we are now preparing the next edition of our book: Healthcare Organizations [Management Strategies, Operational Techniques and Case Studies]. And so, we solicit your interest in crafting new material or simply updating original chapters for subscriber, ACPE, Barnes & Noble, MGMA, ACHE and related distribution channels.

Tentative Table of Contents [400 pages]

  1. On the Origins and Development of Quality Initiatives in Healthcare
  2. Competitive Analysis of the Contemporary Healthcare Ecosystem
  3. Capital Formation Strategies for Healthcare Entities
  4. Inventory Management and Economic Order Quantity Analysis
  5. Improving Operations and Management to Achieve Objectives
  6. Financial and Clinical Features of Hospital Information Systems
  7. Managing Health Information Technology Security Risks
  8. Monitoring, Managing and Enhancing Hospital Revenue Cycles  
  9. Patient [Customer] Relations Management in Healthcare
  10. Healthcare Organization Compliance Processes and Tactics
  11. Reviewing OSHA Standards and Health Policy Practices
  12. Operational Impact of HIPAA, Sarbanes-Oxley and the USA PATRIOT ACT
  13. Understanding Continuous Healthcare Process Improvement
  14. Using Medical Informatics to Track Health Care
  15. Appreciating Six-Sigma Healthcare Quality Improvement
  16. Hospital-Flow Through Efficiency and Logistics.

Editorial support is available, and you would enjoy increasing subject-matter notoriety, exposure and public relations in an erudite and credible fashion. ME-P expert reader synergy seems ideal and our time line for submission is ample in a prose writing style that is “wide, and deep.”  Scheduled release is 2012.

Assessment [first edition]

Foreword: http://healthcarefinancials.com/aboutus.aspx

Style and format: http://healthcarefinancials.com/Documents/Clinical%20and%20Financial%20Features%20of%20Hospital%20IT%20Systems.pdf

Prior authors: http://healthcarefinancials.com/contributors.aspx

TOC: http://healthcarefinancials.com/Documents/TABLE%20OF%20CONTENTS.pdf

We look forward to working with you and appreciate your continued “crowd-sourced” interest in this important body of work. So, please advise me of your interest: MarcinkoAdvisors@msn.com

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

Product DetailsProduct DetailsProduct Details       

Product Details  Product Details

   Product Details 

Smartphone App Market Outperformes Other Booming Markets – 3 Years Benchmark

The Smartphone Applications Market is Impressive 

By Markus Pohl

Join Our Mailing List 

The mobile applications market made it from ramp-up phase to a mass market in only 3 years. This is much faster than previous mobile market sectors needed.

Berlin, March 8th, 2011 

The numbers regarding the smartphone applications market are impressive: Global app download numbers increased by 1700%, user base by 1300%, number of different smart devices by 800%, number of apps by 500% and even app store number increased by 300% in the first 3 years.

With application numbers increasing by almost 100.000 apps per quarter on all major app stores the competition level in a category and platform can change over night, which has an immediate impact on download numbers. Compared to these trends user behavior and demographics in terms of age, gender, usage time, downloads etc. has not changed so quickly over the last three years but will do when applications are proliferating into the mass market. There will be substantial differences per country and platform any company should be aware of, when formulating their application strategy.

Apple dominated the years 2008 and 2009. Since 2010 the hype moved over to Android. With the partnership of Microsoft and Nokia, this might change again as deteriorating average application download numbers on the Android platform will make developers shift again their priorities. What will be the most promising application types and categories will be the next big question.

When looking at the initial phases of other markets, companies really had a lot of time to decide on if, how and when to enter the market. It seems that industry cycles become shorter and shorter and the ability of a company to react very quickly becomes even more important. To stay updated on current trends subscribe to our new “Smartphone App Market Monitor”. This monitoring subscription service will be updated every quarter. Benefit from the intro offer, which saves you 20% until 31st of March.

Twitter: #smartphone #app market outperformes other booming markets – 3 years #benchmark http://j.mp/hRMi6c

About research2guidance:

research2guidance is a Berlin-based market research company specialized in the mobile industry. The company’s service offerings include comprehensive market studies, as well as bespoke research and consultancy.

research2guidance | The Mobile Research Specialists

phone: +49 (0) 30 60 989 3363

mobile: +49 (0) 178 4007736

fax: +49 (0) 30 60 989 3369

email: mp@research2guidance.com

www.research2guidance.com

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com and http://www.springerpub.com/Search/marcinko

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko 

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Healthcare Organizations: www.HealthcareFinancials.com

Physician Advisors: www.CertifiedMedicalPlanner.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest ME-Ps delivered to your email box each morning? Just subscribe using the link below. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Sponsors Welcomed: And, credible sponsors and like-minded advertisers are always welcomed.

Link: https://healthcarefinancials.wordpress.com/2007/11/11/advertise

About Consent Care.Net

The Case for Fully Informed Consent

By Dr. Martin Young

MBChB, FCS(SA)Otol.

martin@carespace.net

The issue of ‘informed consent’ is an ever present bugbear in all healthcare systems around the world, raising its head time after time in journals, weblogs, healthcare administration policies and, above all, medical malpractice lawsuits. Every mention emphasizes the need for improving this difficult issue, but in spite thereof little seems to change.  ConsentCare is a new initiative aiming at addressing the challenges of facilitating and enhancing informed consent.

Why the big deal?

Medical ethicists have long known that, if trust is indeed the cornerstone of the successful doctor-patient relationship, that subjecting a person to medical or surgical treatment without discussing all aspects thereof wherever possible, i.e. fully informed consent, constitutes a betrayal of that trust.

Common opinion asserts that good informed consent creates better mental preparation for surgery, decreased anxiety, shorter hospital stays, earlier recognition of complications by patients before they become serious, and a generally higher success rate and satisfaction rate for the surgery.

70% of the detail of discussion about surgical detail and risk held in doctors’ rooms is forgotten by patients by the time the consultation is over. Patients are ordinarily asked to consent to surgical procedures ‘on the spot’ without access to the detailed documentation of the risks of those procedures that they can consider in their own time and own comfortable environment.

A person knowing all the information about his or her procedure acts as another measure of control to avoid outright human error, such as the wrong operation, or operating on the wrong side.

Almost every case of litigation following surgery will address the adequacy of the consent process.

The right to full knowledge about medical or surgical interventions is entrenched as a human right, even legally enforceable by inclusion in the constitutions of some countries.

No longer is a successful surgical outcome adequate protection against litigation, particularly where the consent is deemed to have contained inadequate information.

In an environment where litigation is on the increase, and expectations, demands and knowledge by the public have heightened, adequate and fully informed consent is one of the few protections doctors can apply both to their own benefit and to that of their patients.

The challenges

Good informed consent is not just presentation of a form that demands the patient’s signature on the bottom.  The process is dependent on all aspects of a good doctor-patient interaction, i.e. positive and empathetic communication, good bedside manner, open and frank discussion of alternatives and costs, opportunity to ask questions, to seek independent advice, and to make decisions based on full disclosure of relevant facts.  The result can however be a valuable clinical record of benefit to all role-players in the process of having a surgical procedure.

The demands of taking fully informed consent are considerable.  No patient is the same, and a standard ‘one size fits all’ approach cannot take this into consideration. The same can be said for the doctor taking the consent.  All have individual approaches and styles that should facilitated by the consent process.  Again, ‘one size fits all’ is as inappropriate for doctors as it is for patients.  The challenge for doctors is in documenting the process for both their patients’ and their own benefit.  Without technological assistance this is impossible to do, for example, to the satisfaction of a medical malpractice lawyer hell-bent on proving medical negligence.

Solutions

ConsentCare was designed taking all these considerations into account, but preserving the traditional and familiar signed document as a final result .  A web-based platform was used, making the system accessible to both doctors and patients through a doctor portal and a patient portal, and opening the possibilities of direct doctor-patient communication around the specified procedure.  Call it if you like a ‘mini-Facebook’ around the consent process.

On logging in a doctor adds a new patient, and proceeds through progressive steps, selecting procedure name, adding or editing graphics, and having editorial control over the content at all stages.  An “editor’s” function allows preset information to be saved, speeding up the process for subsequent consents.

For all procedures a detailed consent document specific to the doctor, patient and procedure is produced in pdf form within a few minutes. This can be emailed to a patient beforehand, edited digitally using tablet PC’s, or printed out and discussed on the spot, leaving all options open as per the doctor’s preferences.

The potential

No other process leaves better evidence of a doctor’s ethical approach, transparency, patient care and responsibility than the informed consent process.  This is a document that should be in the patient’s possession as well as in the medical record, an ethical yardstick of due diligence.  It gives very little clinical detail away other than a patient’s name, the procedure, and likelihood of expected risks.  As such, this can assist the detailed case management of patients, warn nursing staff of anticipated complications, and allocate patients to different levels of post operative care.  It becomes a valuable nursing tool, not just a medicolegal hassle.

The record of a doctor’s approach to his patients in terms of attention to informed consent can be an ethical yardstick that raises that doctor’s profile above the rest.  In an era of doctor and hospital ratings, rising healthcare costs, rising litigation, and increasingly limited resources, all payers, i.e. patients, funders and insurers, could benefit from recognizing where their money is best spent.

The doctor’s excuse “I don’t have the time” should no longer be relevant. Technology takes care of that issue.  The consent process is so important, and with such cost-saving potential in the long term, that time considerations should be far secondary to ethical considerations.  In an era where low markups on doctors’ services promote the push to do high numbers of procedures, the consent process could be the one determinant to start reversing that process.

So, doctors, please make the time, cut the volumes, but, funders and insurers, make sure the doctor does not pay a financial penalty, and is remunerated properly for work done properly.  And malpractice insurers, please take note, and lower premiums for users.

Herein lies the true potential of facilitated informed consent, a ‘win-win’ for everyone involved.

Our position 

ConsentCare is a working proof-of-concept,  available for ‘reskinning’ to the designs of any users /institutions, with the same design elements applied to the final document, and can be hosted on private servers.

Interested users are invited to sign in on the website at www.consentcare.net for more information and a look around with basic functionality, and to contact me for more information.

Conclusion

And so, your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details