Seeking Vice-President of Medical Management

Join Our Mailing List 

Advocate BroMenn Medical Center and Advocate Eureka Hospital in Normal, Illinois

By Paul Esselman
Executive Vice President, Managing Principal
Cejka Executive Search
4 CityPlace Dr., Ste. 300
St. Louis, MO 63141
pesselman@cejkasearch.com

Dear Dr. Marcinko,

Cejka Executive Search has been retained to recruit a physician executive to be the Vice President, Medical Management of Advocate BroMenn Medical Center and Advocate Eureka Hospital.

The Opportunity

Advocate BroMenn Medical Center, a 221-bed full-service, not-for-profit, Level II trauma center and teaching facility located in Normal, Illinois, is one of the most advanced acute care facilities in central Illinois.  Last year, Advocate BroMenn opened a new 136,000 sq. ft. hospital addition housing state-of-the-art diagnostic and therapeutic services as well as opened a new 84,000 sq. ft. outpatient center, housing imaging, therapy and laboratory services and physician practices.

Advocate Eureka Hospital is a 25-bed critical access facility located 25 miles north of Normal.  With their affiliation with Advocate Health Care in 2010, Advocate BroMenn and Advocate Eureka are now part of the largest integrated healthcare system in Illinois and one of the Top 10 health systems in the country. Advocate BroMenn has been consistently recognized for high performance and awarded the Consumer Choice Award as the “Most Preferred Hospital for Overall Quality and Image” in its region.

Leadership Team

As a key member of the senior leadership team, the VPMM will serve as the clinical strategist to drive improvement in hospital-wide services and quality measures for the two hospitals.  The VPMM will be instrumental in working with the medical staffs and Advocate Health Care’s Clinical Integration division to implement its nationally-recognized approach to patient care utilizing the best practices in evidence-based medicine, advanced technology and quality improvement techniques.  The VPMM will lead the organization in achieving a high level of quality, service, and outcomes and align the culture of physician providers and the hospitals in preparation for healthcare reform.

The VPMM will also coordinate medical affairs and implement consistent policies and practices; manage and develop physician education initiatives; and oversee clinical utilization, case and risk management, and physician satisfaction at both facilities.

###

jobs

Candidates

Successful candidates will have at least five years of experience in clinical practice and at least three years of demonstrated success in a senior medical executive role within a hospital, preferably serving in a similar position.  Current board certification is required.  An MBA/ MMM degree is highly desirable.

Information Requests

For more information or to nominate candidates, kindly contact me. Thank you.

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

The Cost of [Healthcare] Data Storage Through-Out the Years

Join Our Mailing List

A Hard Drive History Infographic

By Mike Thomas historyofharddrives@gmail.com

425 N Prince St
Lancaster, PA 17603
7172079980

Data storage wasn’t as inexpensive as it is today. Technology is always advancing and doing bigger and better things that seemed impossible at one time. With that being said, the price of data storage has only decreased while the size of the storage overall has vastly increased.

The following infographic delves into the price of data storage throughout the years beginning with the first hard drive on the market, the RAMAC 305 that was available in 1956. Follow the timeline throughout history and read about the transformation of these data storing devices. Whether you’re a computer geek, a technology hoarder, or new to the computer world we live in, this infographic is one you will enjoy. Share this on your social media profiles, email it to the IT department at the office, or blog about these outrageously priced data storage devices to gain a new appreciation for the storage capacity we have today.

MD and financial literacy

History Of Data Storage Devices

They just don’t build things quite like they used to. This statement may seem clichéd, but it greatly applies to data – and not in a bad way. Through the years, technology becomes more and more advanced, exceeding expectations and pushing toward new and innovative products and capabilities.

In the case of this infographic, computer memory and data storage have increasingly changed since their beginnings in 1956. If we hadn’t learned how to make memory and data storage servers smaller, then we’d still have rooms solely dedicated to these large machines like the RAMAC 305 that was the size of two large refrigerators. Computers would still be gigantic and immobile, unlike our sleek and portable laptops. Nowadays, our laptops, cell phones, and desktop computers are smaller than years past but are equipped with larger memory capabilities that it once had.

Advances in Computer Data Storage Devices

To gain a better appreciation for the advances in technology, we’ve created an infographic that highlights the data storage throughout the years. Beginning with the RAMAC hard drive, we outline all types of storage devices from 1956 to present. Learn how much money these products cost at the time as well as what the price would be like with inflation factored in. It’s interesting to understand these data storage solutions, particularly how they became smaller in size yet bigger in storage capabilities. Millions of people from school students to business professionals rely on the memory in their computer to save documents, presentations, and other important information.

How crazy would it be if one megabyte of storage still cost $10,000 like in 1956? If that were still the case, laptop prices would be out of this world, and many companies and schools wouldn’t have computers to work on. Sprinkled throughout the infographic are interesting facts on how much a megabyte of storage has cost throughout the years. These amazing statistics demonstrate jut how much the price of storage has decreased since 1956.

RocklandIT Infographic

infographic on the cost of data storage

[click to enlarge]

Save, Store, and Share

Whether you’re an MD, FA, CPA, JD, student, computer geek or just interested in learning more about [medical] data storage devices, feel free to share this information with friends, family, and others. We hope that you enjoy reading this content and we encourage that you blog, tweet, pin, and share this graphic with the world.

Assessment

And, your HIT department, hospital, clinic or office coworker might appreciate viewing this infographic and possibly recollect using one of these storage devices of the past.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.
Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko
Practice Management: http://www.springerpub.com/product/9780826105752
Physician Financial Planning: http://www.jbpub.com/catalog/0763745790
Medical Risk Management: http://www.jbpub.com/catalog/9780763733421
Hospitals: http://www.crcpress.com/product/isbn/9781439879900
Financial Advisors: http://www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Why President Nixon Signed the Controlled Substances Act in 1970

Join Our Mailing List

The DEA History

[By Staff Reporters]

Doctors prescribe harmful and potentially addictive drugs, and they all hold a DEA license to do so.

But, did you know that one of the foundations upon which the Drug Enforcement Administration was created is the Controlled Substances Act (CSA)? It was signed into law as part of a broader set of laws called The Comprehensive Drug Abuse Prevention and Control Act of 1970.

The CSA

As all doctors and nurses know, the CSA created five schedules for controlled substances ranging from Schedule I, the most restrictive classification to Schedule V, the least so.

Schedule I drugs have a 1) High potential for abuse 2) No currently accepted medical use in treatment in the United States and c) Lack of accepted safety for use under medical supervision.

Medicare and Medicaid drug capsules

Definition of Controlled Substance Schedules

An updated and complete list  of the schedules is published annually in Title 21 Code of Federal Regulations  (C.F.R.) §§ 1308.11 through 1308.15.

Substances are placed in their respective schedules based on whether  they have a currently accepted medical use in treatment in the United States,  their relative abuse potential, and likelihood of causing dependence when  abused.  Some examples of the drugs in  each schedule are listed below.

Schedule I Controlled Substances

Substances in this schedule have no currently accepted  medical use in the United States, a lack of accepted safety for use under  medical supervision, and a high potential for abuse.

Some examples of substances listed in Schedule I are:  heroin, lysergic acid diethylamide (LSD), marijuana (cannabis), peyote,  methaqualone, and 3,4-methylenedioxymethamphetamine (“Ecstasy”).

Schedule II Controlled Substances

Substances in this schedule have a high potential for abuse  which may lead to severe psychological or physical dependence.

Examples of Schedule II narcotics include: hydromorphone  (Dilaudid®), methadone (Dolophine®), meperidine (Demerol®), oxycodone  (OxyContin®, Percocet®), and fentanyl (Sublimaze®, Duragesic®).  Other Schedule II narcotics include:  morphine, opium, and codeine.

Examples of Schedule II stimulants include: amphetamine  (Dexedrine®, Adderall®), methamphetamine (Desoxyn®), and methylphenidate  (Ritalin®).

Other Schedule II substances include: amobarbital,  glutethimide, and pentobarbital.

Schedule III Controlled Substances

Substances in this schedule have a potential for abuse less  than substances in Schedules I or II and abuse may lead to moderate or low  physical dependence or high psychological dependence.

Examples of  Schedule III narcotics include: combination products containing less than 15  milligrams of hydrocodone per dosage unit (Vicodin®), products containing not  more than 90 milligrams of codeine per dosage unit (Tylenol with Codeine®), and  buprenorphine (Suboxone®).

Examples of Schedule III non-narcotics include:  benzphetamine (Didrex®), phendimetrazine, ketamine, and anabolic steroids such  as Depo®-Testosterone.

Schedule IV Controlled Substances

Substances in this schedule have a low potential for abuse  relative to substances in Schedule III.

Examples of Schedule IV substances include: alprazolam  (Xanax®), carisoprodol (Soma®), clonazepam (Klonopin®), clorazepate  (Tranxene®), diazepam (Valium®), lorazepam (Ativan®), midazolam (Versed®),  temazepam (Restoril®), and triazolam (Halcion®).

Schedule V Controlled Substances

Substances in this schedule have a low potential for abuse  relative to substances listed in Schedule IV and consist primarily of  preparations containing limited quantities of certain narcotics.

Examples of Schedule V substances include: cough  preparations containing not more than 200 milligrams of codeine per 100  milliliters or per 100 grams (Robitussin AC®, Phenergan with Codeine®), and  ezogabine.

The Nixon Connection

CSA as part of the Comprehensive Drug Abuse Prevention and Control Act was signed into law by President Richard Nixon on October 27, 1970.

RMN

[President Nixon Signs the Controlled Substances Act] 

Assessment

This picture was taken on that day at the White House. Behind the president is Attorney General John Mitchell and next to the president is BNDD Director Jack Ingersoll.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct Details

Workers Memorial Day 2013

Join Our Mailing List 

Workers Celebrate on May First This Year

By Matthew Pelletier

[Director of Public Relations]

Compliance and Safety LLC

marry-harris

“Pray for the dead and fight like hell for the living”

Marry Harris “Mother” Jones

[1837 – 1930]

Dear ME-P,

We’ve just published a page for workers memorial day 2013 (falls on Sunday April 28th, 2013) that I thought you might be interested in posting on the ME-P.

Link: http://complianceandsafety.com/blog/workers-memorial-day-2013/

Assessment

You’re also more than welcome to use any of the content from our memorial page on your website.

Workers Also Celebrate on May First This Year: International Workers’ Day

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Administrative Professionals’ Day

Join Our Mailing List

Difference makers: On the job with admin

By Staff Reporters

In honor of Administrative Professionals’ Day 2013, celebrated just last week, here’s a closer look at the key roles these individuals play in order to keep medical, financial advisory and other offices everywhere – running smoothly.APD

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

The DEA’s [Original] Model Paraphernalia Law

Join Our Mailing List

Drug use in the 60s and 70s

By Staff Reporters

In the 1960’s and 1970’s drug use in the United States continued to grow, peaking in 1979. This was, in part, due to the wide, legal availability of drug paraphernalia like that captured in this picture of a dealer on a street corner near DEA headquarters (then located at 1405 I Street NW in Washington DC) in the late 1970’s.

###

DEA

###

In order to combat this trend, DEA was asked by the White House to create a model Drug Paraphernalia Law to be implemented and enforced at the state and local level, giving DEA and other partners another tool in the fight against drug abuse.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

More on Medical Practice Patient Scheduling Issues

Join Our Mailing List 

And … Waiting Room Wait-Times

By Dr. David Edward Marcinko MBA

Dr. MarcinkoRecently, I read the following post on: 8 surprising thoughts about patient wait times.

And so, I decided to offer a follow-up commentary based on my experiences, and as outlined in our newest book: www.BusinessofMedicalPractice.com

Obviating the Problem

The point here is not to “react” but to avoid the dreaded “waiting time” problem in the first place.

Now, realize that most mature doctors follow a linear (series-singular) time allocation strategy for scheduling patients (i.e., every 15 or 20 minutes). This can create bottlenecks because of emergencies, late patients, traffic jams, absent office personal, paperwork delays, etc. Therefore, as suggested by colleague Neil Baum MD, one of these three newer scheduling approaches might prove more useful.

1. Customized Scheduling

The bottleneck problem may be reduced by trying to customize, estimate or project the time needed for the patient’s next office visit. For example: CPT #99211 (5 minutes), #99212 (10 minutes), #99213 (15 minutes), #99214 (25 minutes), or #99215 (40 minutes). Occasionally, extra time is need, and can be accommodated, if the allocated times are not too tightly scheduled.

2. Wave Scheduling

Some patient populations do not mind a brief 20-30 minute wait prior to seeing the doctor. Wave scheduling assumes that no patient will wait longer than this time period, and that for every three patients; two will be on time and one will be late. This model begins by scheduling the three patients on the hour; and works like this. The first patient is seen on schedule, while the second and third wait for a few minutes. The later two patients are booked at 20 minutes past the hour and one or both may wait a brief time. One patient is scheduled for 40 minutes past the hour. The doctor then has 20 minutes to finish with the last three patients and may then get back on schedule before the end of the hour.

3. Bundle Scheduling

Bundling involves scheduling like-patient activities in blocks of time to increase efficiency.

For example, schedule minor surgical checkups on Monday morning, immunizations on Tuesday afternoon, and routine physical examinations on Wednesday evening, or make Thursday kid’s day and Friday senior citizens day. Do not be too rigid, but by scheduling similar activities together, assembly-line efficiency is achieved without assembly line mentality, and allows you to develop the most economically profitable operational flow process possible for the office.

###

Product Details

###

4. Patient Self Scheduling (Internet Based Access Management)

The traditional linear patient scheduling system is slowly being abandoned by modern medical practitioners; an all venues (medical practices, clinics, hospitals and various other healthcare entireties). New software programs, and internet cloud applications, allow patients to schedule their own appointments over the internet. The software allows solo or individual group physicians with a practice to set their own parameters of time, availability and even insurance plans. Through a series of interrogatories, the program confirms each appointment. When the patient arrives, a software tracker communicates with office staff and follows the patients from check-in, to procedures, to checkout.

Assessment 

Today, many hospitals have even abandoned the check-in or admissions, department. It has been replaced by access management systems.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details


Recent Tax Law Changes and Basic Retirement Planning [video]

Join Our Mailing List

For Healthcare Accountants

By Richard Schwartz CPA

http://schwartzaccountants.com/

Richard Schwartz CPA

Content: Video (mp4) – 105.32MB
Title: Richard Schwartz Webinar 1.23.13 Tax Changes and Retirement

Link: http://www.screencast.com/t/Huco7W8LOl

Richard S Schwartz, CPA, CVA, received a B.A. in Economics from Brandeis University in 1985 and an M.S. in Accounting from the Graduate School of Professional Accounting at Northeastern University in 1990.  Prior to joining his brother at Schwartz and Schwartz,  P.C. in 1993, he worked for the international accounting firm PricewaterhouseCoopers, LLP, in their Emerging Business Services Group.  Since joining Schwartz and Schwartz, P.C. he has worked with individuals providing tax expertise as well as small business owners providing both tax and accounting guidance to help their businesses grow.  In 2006, Rick earned the designation of Certified Valuation Analyst from the National Association of Certified Valuation Analysts (NACVA), which he uses to assist healthcare professionals in their evaluation of whether to purchase a practice.

Conclusion

In any case, early planning is the key to supporting both your kids’ futures and your retirement. Making logical college funding decisions, rather than emotional ones, creates a win/win for everyone.

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Product DetailsProduct Details

Defining Tomorrow’s Doctor [Vote]

Join Our Mailing List 

What does the 21st Century Physician look like – Please tell us your vision?

Doctors

We can’t solve problems by using the same kind of thinking we used when we created them.  Tell us your vision or just view the list of visions so far.

Tomorrow’s Doctor

[This is a collective initiative lead by folks like you] 

Assessment

Why Become A Doctor?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Staffing Level Effects of Health Care Reform‏

Join Our Mailing List

April 2013 edition of Plan Management Navigator
***
By John Park jpark@sherlockco.com
[Health Care Analyst – Sherlock Company]

Greetings:

Please find attached the April 2013 edition of Plan Management Navigator. This month’s Navigator features three estimates of employment by U.S. private health plans:

***

1. The first estimate is of staffing as it exists at present, based on Sherlock Benchmarks.

2. The second estimate calculates the effect of the new private insurance enrollment through Medicaid and through the exchanges, as estimated by the Congressional Budget Office, on health plan employment. This second estimate employs the existing Sherlock Company staffing ratio benchmarks.
3. The third estimate applies the staffing ratios of low cost health plans participating in the Sherlock Benchmarking studies to all insurers.

Estimates

We estate that the combined effect of increased health plan enrollment and heightened efficiency to be a decline of 72,000 FTEs.

new-and-improved-consult-letter-blog

Webinar

On April 17th we held a brief conference call on this topic. You may still contact us to answer any methodological questions you may have.

Assessment

April 2013 Navigator

About

Sherlock Benchmarks help to identify whether your plan has high staffing ratios and which functional area’s staffing should be targeted for a closer look. We invite you to consider participation in the 2013 survey with the nearly 50 organizations that have already committed to this valuable analysis.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Searching for Chief Medical Director [CMD]

Join Our Mailing List

Centene Corporation Seeking CMD

By Jennifer Sonneland jsonneland@cejkasearch.com

Cejka Executive Search www.cejkaexecutivesearch.com

Dear Dr. Marcinko,

I am assisting Centene Corporation in their recruitment for a Chief Medical Director for IlliniCare Health Plan, a wholly owned subsidiary and HMO for the state of Illinois.  The regional headquarters for IlliniCare is in Chicago. 

The Chief Medical Director (CMD) will be responsible for directing and coordinating the medical management, quality improvement and credentialing functions for IlliniCare. S/he will serve as a clinical advisor and educator of the medical management staff, ensuring the clinical quality and efficacy of patient care.

jobs

The CMD will also help identify trends in patient treatment data and proactively develop programs to improve patient health and wellness needs.  As an integral part of IlliniCare’s senior leadership team, the CMD will have an active role in supporting the strategic plans and vision of the organization.  

Ideal candidates will have a minimum of five years of progressive experience in healthcare enterprises and demonstrated success in establishing population health management programs and driving quality outcomes and financial performance for the underserved population. Board certification, preferably in geriatrics, and an unrestricted medical license are required. 

A post-graduate business degree (MBA/MMM) is preferred.

Assessment

More details about this opportunity upon request.

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Introducing Neil H. Baum MD

Join Our Mailing List

Our Newest ME-P “Thought-Leader”

By Ann Miller RN MHA

[Executive-Director]

Dr. BaumDr. Neil Baum is Associate Clinical Professor of Urology at Tulane Medical School and Louisiana State University Medical School, both in New Orleans, LA.

He is also on the medical staff at Touro Infirmary in New Orleans, and East Jefferson General Hospital in Metairie, LA.

Medical Background

Dr. Baum received his medical degree from Ohio State University Medical School in Columbus. He completed an internship at the University of California at Los Angeles, a residency in surgery at Harbor General Hospital, Torrance, California, followed by a second residency in surgery and a residency in urology, both at Baylor College of Medicine in Texas. Dr. Baum is certified by the American Board of Urology.

ME-P Relevance

Dr. Baum often shares his extensive experience from his urologic office and regularly speaks to medical practices, hospitals, and pharmaceutical and manufacturing companies on improving communications between physicians and patients, practice management, guerilla marketing, practice promotion and motivation.

He has also several books on efficient medical marketing. In fact, he is the author of Marketing Your Clinical Practice-Ethically, Effectively, and Economically, 4th Edition (Jones-Bartlett, 2010).

###

Product Details

###

Product Details

###

And so, we are pleased he accepted our invitation as ME-P “thought-leader.” All our readers and subscribers look forward to his essays, comments and insightful contributions.

Essential ME-P Reader Concerns

I recently caught up with Dr. Baum with these two readership questions.

Q: Why Market and Promote Your Practice in the Era of Managed Care?

A: “Often physicians will discuss the current health care situation in their community and believe that their days of practice promotion are over when they have joined all of the managed care plans in the vicinity. The reality is that noting could be farther from the truth. Now marketing and practice promotion is even more important than in the “good ol’ days” of fee-for-service”.

Q: What is the Most Common Medical Practice Disaster?

A: “Natural disasters are not the most common cause of practice failure; man-made disasters such as computer crashes, power outages, and loss of electronic data are more likely to impact a medical practice”.

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details

Foreword.Baum

[Available Now]

A New IRA Withdrawal Limit Proposal

Join Our Mailing List 

Capping Tax-Advantaged Retirement Plans?

By Rick Kahler MS CFP® ChFC CCIM http://www.KahlerFinancial.com

Rick Kahler CFP“Max out your retirement plans every year” has long been standard advice I’ve given to working adults, and all medical professionals, who want to secure a reliable income when they retire.

Individual Retirement Accounts (IRAs), along with 401(k), 403(b), and profit sharing plans offered by some employers, are among the most accessible ways for middle-class workers to provide for retirement and build wealth.

If a proposal in President Obama’s budget plan is approved by Congress, however, retirement plans may no longer be the first and best stop along the road to financial independence.

The New Proposal

The proposal would limit a person’s total withdrawals from all tax-advantaged retirement plans to the amount it would cost to purchase an immediate annuity paying $205,000 a year. And, it appears to not be indexed for inflation. The articles I’ve read and my own calculations suggest this would mean capping retirement accounts at around $3 million.

From the sketchy details available so far, the proposal appears to target traditional IRAs and other tax-deferred retirement plans. Contributions to these accounts are made with pre-tax dollars, and the earnings in the account are not taxed until they are withdrawn.

Since 58% of Americans don’t have any retirement plan, my guess is they will pay little attention to this proposal. Saving $3 million dollars seems well out of reach. While that may be true in today’s dollars, it most likely will not be true in future dollars.

If inflation over the next 40 years matches that of the past 40, a $3,000,000 IRA in 2053 will be equal to $575,000 today. If today’s 25-year-old, retiring then, wanted to be sure the money would last another 40 years, the IRA would provide an income equivalent to about $1,500 a month.

Tax-Advantaged Retirement Plans

Even in today’s dollars, the $3 million maximum isn’t as unreachable as it may seem. Employees can currently contribute a maximum of $5,500 per year ($6,500 for those 50 and older) to Roth or traditional IRAs. Small business owners and the self-employed may have SIMPLE (savings incentive match plan for employees) or SEP (simplified employee pension) IRAs. The maximum annual contribution is currently $17,000 for a SIMPLE and $51,000 for a SEP. A self-employed plumber, business owner, or doctor who was a conscientious saver with a diversified portfolio could certainly accumulate $3 million over a lifetime.

Or, suppose the wife of a small business owner, or doctor, was a self-employed counselor with her own SEP plan. If he died at age 58 and she inherited his IRA, the combined totals could easily put her over the $3 million cap.

###

MD Retirement planning

Unclear Options

It isn’t clear how the proposal would equate the withdrawal rate with the cap. One possibility would be to raise the required minimum distribution amount, which would erode the value of an IRA more quickly.

Another option would be to penalize excess accumulations with a hefty tax of 40% or more. Of course, the President could follow in Argentina’s footsteps and just confiscate any amount over the cap.

Any of these would add to the diminution of retirement plans as a vehicle for income during retirement.

The Caveat

The proposal includes this statement:

“But, under current rules, some wealthy individuals are able to accumulate many millions of dollars in these accounts, substantially more than is needed to fund reasonable levels of retirement saving.”

Assessment

Apparently we, as individual citizens, are not considered capable of defining “reasonable levels” of retirement saving for ourselves. The real goal of this plan appears to be wealth distribution, instead of encouraging more Americans to save and provide for their own retirement.

More:

If this proposal is passed, retirement plans will play a much smaller role in many middle class Americans’ golden years.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

What’s the Chance a Startup Business will Fail?

Join Our Mailing List

On Survival Rates

By Radel Artida (radel@staff.com

Blame it on the media when people seem to think that their hot tech startup will make them a billionaire by their mid-20s. And, doctors are not immune.

Startup

Assessment

On a lesser level, doctors and medical professionals who seek independence and their own practice should be aware of the factors that contribute to a startup’s success. So, we created this infographic on those factors, or chances, that your startup will fail or succeed.

This also includes some research on projections for the best sectors to start your new business, if you seek another industry.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Remembering the Boston Tragedy

Join Our Mailing List

My Thoughts on the Unthinkable

By Dr. David Edward Marcinko MBA

[Publisher-in-Chief]

A POEM

In memory of those who died

[Copyright by Nicholas Gordon]

In memory of those who died.

We weep and walk away.

Tears run into swollen streams.

No trace of us remains.

Even those who grieve are gone, and those that grieve who grieve, and those whose lives are ravaged by afrantic urge to be.

And those who wander silently among the empty rooms – immortality is theirs, though they must vanish, too.

We bear astonished witness to the passage of the soul.

No bridge exists that can connect our passion to the whole.

###

###

Fenway Park Dr. Marcinko

###

###

Assessment

Tragedy is defined as a form of drama based on human suffering that invokes in its audience an accompanying catharsis or pleasure in the viewing.

But, we shall not succumb to it; we shall not give up; we will revisit Boston and run a marathon again. And, as free Americans, we will live, love and … thrive!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

America’s Health Disadvantage

Join Our Mailing List

A Data Analytics Infographic

By Sandy Osorno

[MPH Graduate Student]

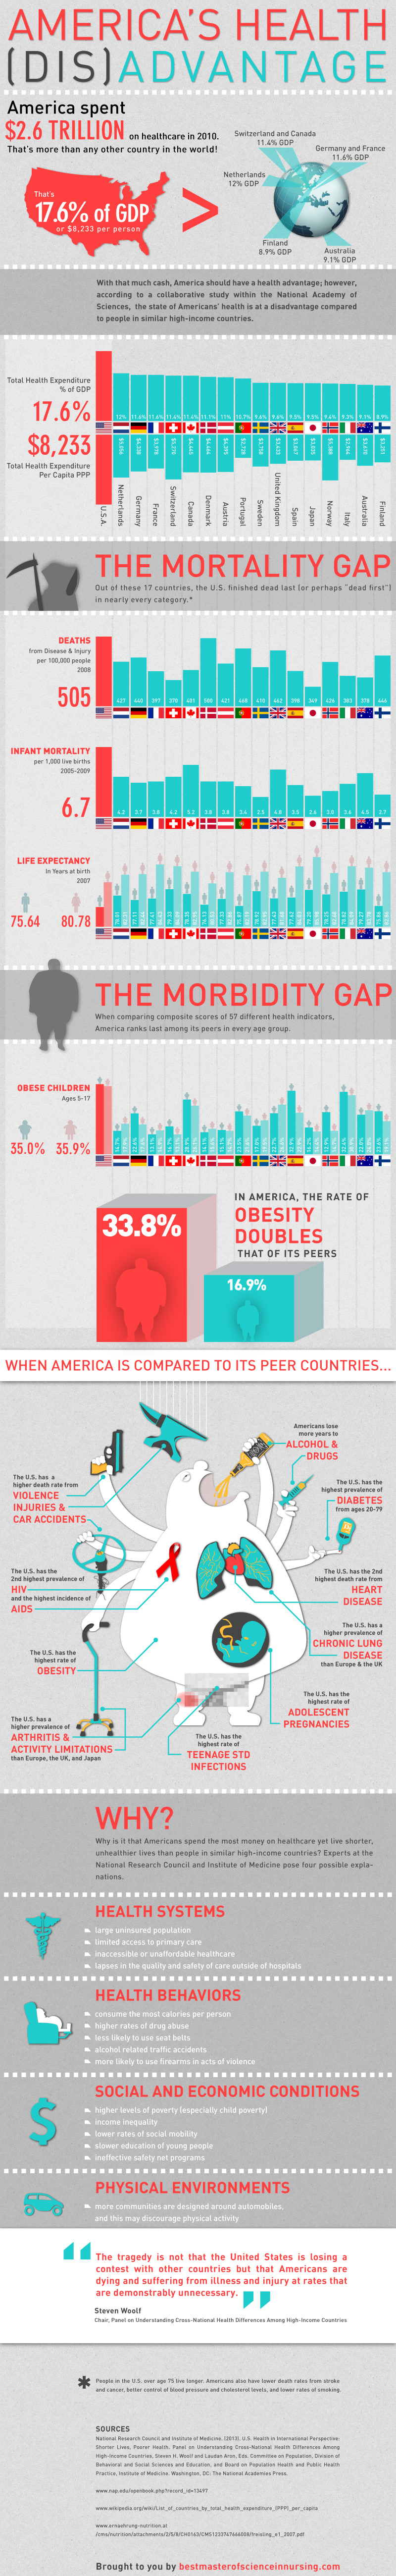
The United States spent $2.6 trillion on health care in 2010 – more than any other country in the world. Yet based on research from a collaborative effort within the National Academy of Sciences, Americans live shorter lives and experience more injuries and illnesses than people in similar high-income countries.

THE MORTALITY GAP

Out of 17 countries surveyed (Australia, Austria, Canada, Denmark, Finland, France, Germany, Italy, Japan, Norway, Portugal, Spain, Sweden, Switzerland, the Netherlands, and the United Kingdom), the U.S. finished dead-last (or perhaps dead first is more appropriate) in nearly every category.*

NOTE: Deaths from Disease and Injury per 100,000 people in 2008

– Japan: 349
– Switzerland: 370
– Australia: 378
– Italy: 383
– France: 397
– Spain: 398
– Canada: 401
– Sweden: 410
– Austria: 421
– Norway: 426
– Netherlands: 427
– Germany: 440
– Finland: 446
– United Kingdom: 462
– Portugal: 468
– Denmark: 500
– United States: 505

NOTE: Average Infant Mortality Rate per 1,000 Live Births in 2005-2009

– Sweden: 2.5
– Japan: 2.6
– Finland: 2.7
– Norway: 3.0
– Portugal: 3.4
– Spain: 3.5
– Italy: 3.6
– Germany: 3.7
– Austria: 3.8
– Denmark: 3.8
– France: 3.8
– Switzerland: 4.2
– Netherlands: 4.2
– Australia: 4.5
– United Kingdom: 4.8
– Canada: 5.2
– United States: 6.7

NOTE: Years of Life Expectancy at Birth in 2007

Males

– Switzerland 79.33
– Australia 79.27
– Japan 79.20
– Sweden 78.92
– Italy 78.82
– Canada 78.35
– Norway 78.25
– Netherlands 78.01
– Spain 77.62
– United Kingdom 77.43
– France 77.41
– Austria 77.33
– Germany 77.11
– Denmark 76.13
– Portugal 75.87
– Finland 75.86
– United States 75.64

Females

– Japan 85.98
– France 84.43
– Switzerland 84.09
– Italy 84.09
– Spain 84.03
– Australia 83.78
– Canada 82.95
– Sweden 82.95
– Austria 82.86
– Finland 82.86
– Norway 82.68
– Germany 82.44
– Netherlands 82.31
– Portugal 82.19
– United Kingdom 81.68
– United States 80.78
– Denmark 80.53

disadvantage

THE MORBIDITY GAP

Out of 57 health indicators (i.e. diabetes, BMI, cholesterol, BP, etc.) divided into four age groups, the U.S. scored lowest in half (28). Furthermore, when compared to its peer countries, the United States’ composite score in each of the four age groups was ranked last.

– Ages 0-4: Last (17 of 17)
– Ages 5-19: Last (17 of 17)
– Ages 20-34: Last (17 of 17)
– Ages 35-49: Last (17 of 17)

“The tragedy is not that the United States is losing a contest with other countries but that Americans are dying and suffering from illness and injury at rates that are demonstrably unnecessary,” said Steven Woolf, Chair, Panel on Understanding Cross-National Health Differences Among High-Income Countries

As of 2010, the United States had the highest prevalence of diabetes (for adults aged 20-79) among the 17 peer countries. Related, the United States has the highest prevalence of adult obesity among the 17 peer countries. As of 2009, the prevalence of obesity in the United States (33.8 percent) was twice the average (16.9 percent).

NOTE: Compared with the aforementioned countries, the United States fares worse in the following nine health domains:

– 1. Adverse birth outcomes. The United States continues to experience the highest infant mortality rate of high-income countries. Additionally, American children are less likely to live to age 5 than children in similar countries.

– 2. Injuries and homicides. Deaths from car accidents, injuries, and violence occur at much higher rates in the United States than in other countries.

– 3. Adolescent pregnancy and sexually transmitted infections. For nearly two decades, the U.S. maintains the highest rate of adolescent pregnancies and its teenagers are more likely to acquire sexually transmitted infections than adolescents in high-income countries.

– 4. HIV and AIDS. The United States has the second highest prevalence of HIV infection among the 17 peer countries and the highest incidence of AIDS.

– 5. Drug-related mortality. Americans lose more years of life to alcohol and other drugs than people in peer countries, even when deaths from drunk driving are excluded.

– 6. Obesity and diabetes. The United States has had the highest obesity rate among high-income countries for decades.

– 7. Heart disease. The U.S. death rate from ischemic heart disease is the second highest among the 17 peer countries.

– 8. Chronic lung disease. Lung disease is more prevalent and associated with higher mortality in the United States than in the United Kingdom and other European countries.

– 9. Disability. Older U.S. adults report a higher prevalence of arthritis and activity limitations than their counterparts in the United Kingdom, other European countries, and Japan.

WHY?

  1. – Experts at the National Research Council and Institute of Medicine posit four possible explanations for the United States’ declining health.
  2. – Health systems. Unlike its peer countries, the United States has a relatively large uninsured population and more limited access to primary care. Americans are more likely to find their health care inaccessible or unaffordable and to report lapses in the quality and safety of care outside of hospitals.
  3. – Health behaviors. Although Americans are currently less likely to smoke and may drink alcohol less heavily than people in peer countries, they consume the most calories per person, have higher rates of drug abuse, are less likely to use seat belts, are involved in more traffic accidents that involve alcohol, and are more likely to use firearms in acts of violence.
  4. – Social and economic conditions. Although the income of Americans is higher on average than in other countries, the United States also has higher levels of poverty (especially child poverty) and income inequality and lower rates of social mobility. Other countries are outpacing the United States in the education of young people, which also affects health. And Americans benefit less from safety net programs that can buffer the negative health effects of poverty and other social disadvantages.
  5. – Physical environments. U.S. communities and the built environment are more likely than those in peer countries to be designed around automobiles, and this may discourage physical activity and contribute to obesity.
  6. – *The panel did find that the U.S. outperforms its peers in some areas of health and health-related behavior. People in the U.S. over age 75 live longer, and Americans have lower death rates from stroke and cancer, better control of blood pressure and cholesterol levels, and lower rates of smoking.

SOURCE: National Research Council and Institute of Medicine. (2013). U.S. Health in International Perspective: Shorter Lives, Poorer Health. Panel on Understanding Cross-National Health Differences Among High-Income Countries, Steven H. Woolf and Laudan Aron, Eds. Committee on Population, Division of Behavioral and Social Sciences and Education, and Board on Population Health and Public Health Practice, Institute of Medicine. Washington, DC: The National Academies Press.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Be Your Own Banker?

Join Our Mailing List 

BYOB—or not

By Rick Kahler MS CFP® ChFC CCIM www.KahlerFinancial.com

Rick Kahler CFPDoctors – I’m not inviting you to a “bring your own beverage” party. I’m warning you away from a get-rich scheme called “Be Your Own Banker.”

This idea has floated around the Internet and late-night television for a while now. One of the latest versions is touted on a website that I’m not going to name because I don’t want anyone getting sucked into what is essentially one step from being a scam.

Once you drill down past the initial layers of ambiguity, the basic concept seems simple enough. You buy a large whole-life insurance policy. After you pay into it for several years, it will accumulate a cash value. Then, any time you make a major purchase like a new car, you can borrow against your insurance policy instead of going to a bank.

Paying Your Self

According to the people selling this concept, you are the big winner here because you’re paying interest to yourself, not the bank.

The BYOB salespeople are incredible marketers. This must be where political campaign managers ply their trade in between elections. They blast our financial system, banks and bankers, mutual fund managers, and financial advisors. They profess to care about the customers they call “clients.”

The half-truths and misstatements from these sellers are enough to elevate the blood pressure of any fee-only financial planner. They use terms like “depositing cash into a life insurance policy” and “having control of your own banking system.”

Amid all this unbelievable double-talk, they forget to mention one little detail. All that money that you “invest” in your whole life insurance policy is paid in the form of premiums. You aren’t paying it to yourself. You’re paying it to large life insurance companies—which, by the way, are an integral part of the financial system they blast.

###

good news

A Closer Look

Let’s look at some actual numbers. You pay $12,500 a year in premiums for a $125,000 whole life insurance policy. In four years, after paying in a total of $50,000, you would have $46,110 dollars in your account. Yes, this is less than you put in, as the fees and premiums add up to be more than the growth rate. You can borrow up to 90% of the net value, or $41,500.

You will pay the company 5% for borrowing your own money. Supposedly, the interest is paid to yourself and adds to the cash value of the policy. But a deeper look shows that the interest you pay yourself must be over and above the interest paid to the company, which is just another name for “premium.” The insurance company charges you interest regardless of the “interest” you pay yourself.

What happens if you don’t pay back the loan? The interest keeps compounding, adding to the amount of the loan and eating up the cash value of the policy. This could eventually leave you facing some nasty tax consequences, potentially including having to pay income taxes on phantom income.

Instead of paying that $12,500 a year in premiums, you could put it into a deductible 401(k) plan and invest the funds in a diversified portfolio. You’d even be better off to put it into a taxable account. Then if you needed a new car or water heater, you’d have cash and wouldn’t have to borrow from yourself or anyone else.

Assessment

After spending hours researching “being your own banker,” my staff and I understand what BYOB really means. It stands for “Bring Your Own Bottle”—of pain reliever. You’ll need it for the headache of trying to understand this slick advertising scheme. It makes no sense for anyone except those selling the life insurance policy.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Events Planner: April 2013

ADVERTISEMENT

Events-Planner: APRIL 2013

By Staff Writers
Calendar Calculator“Keeping track of important health economics and financial industry meetings, conferences and summits”

Welcome to this issue of the Medical Executive-Post and our Events-Planner. It contains the latest information on conferences, news, and relevant resources in healthcare finance, economics, research and development, business management, pharmaceutical pricing, and physician/entity reimbursement!  Watch for a new Events-Planner each month.

First, a little about us! The Medical Executive-Post is still a relative newcomer. But today, we have almost 175,000 visitors and readers each month from all over the country, in addition to our growing subscriber base. We have been a successful collaborative effort, thanks to your contributions.  As a result, we are adding new resources daily. And, we hope the website continues to provide the best place to go for journals, books, conferences, educational resources, tools, and other things you need to establish the value your healthcare consulting and financial advisory intervention.

So, enjoy the Medical Executive-Post and this monthly Events-Planner with our compliments.

A Look Ahead this Month – And now, the important dates:

  • April 25-26: South Florida FPA Conference. Westin Hotel, Ft. Lauderdale, FLA.
  • April 28-30: IMCA Conference. Washington Convention Center, Seattle, WA.

MarcinkoAdvisors@msn.com

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest E-Ps delivered to your email box each morning? Just subscribe using the link below. It’s free. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Product Details  Product Details

Product DetailsProduct Details

Should You Own an Umbrella Insurance Policy?

Risk Reduction for Medical Professionals?

Join Our Mailing List

By Lon Jefferies, MBA CFP™  www.NetWorthAdvice.com

Lon JeffriesAs a financial planner, a good portion of my job consists of identifying and dealing with potential risks and liabilities for which my clients are exposed. One of the most comprehensive, cost-effective tools for reducing risk exposure is an umbrella insurance policy. Quite simply, if you are reading this ME-P, the purchase of an umbrella policy would be a wise decision.

What is an Umbrella Policy?

An umbrella policy protects both your current and future assets against the cost of losing a lawsuit involving your car or real estate property. Such a policy is in addition to your auto and homeowners insurance.

For example, suppose your auto insurance pays $300k of medical expenses per accident, and you have a $1 million umbrella policy. If you are sued for $800k because of an auto accident, your auto insurance will pay the first $300k of damage. This also serves as the deductible on the umbrella policy, so the umbrella coverage would pay the remaining $500k of damages.

Additionally, umbrella policies cover legal expenses involved with a lawsuit. Even better, since it is the insurance company that will be paying any damages, they are likely to assign a strong (expensive) legal team to your case. Consequently, purchasing an umbrella policy is an indirect way of strengthening your legal defense team.

What Does an Umbrella Policy Cover?

An umbrella policy protects you in car accidents for which you are found to be at fault, as well as accidents that occur on your real estate property. Additionally, these policies protect you from personal injury lawsuits arising from slander, defamation, libel, malicious prosecution, mental anguish and more.  Even better, this coverage will protect you from accidents caused by your dependent children.

As you might imagine, certain factors increase your need for an umbrella policy. For instance, if you spend a lot of time in your car, or you own a swimming pool or a dog, the need for an umbrella policy rises.

Some people think they don’t need an umbrella policy simply because their low net worth doesn’t justify it. This is inaccurate because losing a lawsuit can result in the loss of both your current assets, and your future earnings. For this reason, I believe nearly everyone, especially medical professionals, should have an umbrella policy.

###

policy insurance

###

How Do I Purchase Coverage?

In most instances, an umbrella policy can be purchased through your current insurance providers. A $1 million policy usually costs approximately $200 per year, with additional coverage purchased in $1 million dollar increments and costing approximately $100 per year. At such a low cost while providing critical catastrophic coverage, there is no reason for you to not own such a policy.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Health 2.0 Financial Planning for Medical Executive-Post Members

A By-Product of Health 2.0?

By Dr. David Edward Marcinko FACFAS MBA CMP*

[Founder and CEO]

www.MedicalBusinessAdvisors.com

Dr David E Marcinko MBAA decade ago, Editor Gregory J. Kelley of Physician’s MONEY DIGEST and I reported that a 47 year old-doctor with $184,000 annual income would need about $5.5 million dollars for retirement at age 65. Then came the “flash-crash’ of 2007-08, the home mortgage fiasco and the Patient Protection and Accountable Care Act [PP-ACA] of 2010; etc.

No wonder that medical provider career panic is palpable. Much like the new medical home concept, the idea of holistic life planning was born.

Life Planning

Life planning has many detractors and defenders. Formally, life planning has been defined in the following way. 

Financial Life Planning is an approach to financial planning that places the history, transitions, goals, and principles of the client at the center of the planning process.  For the client, their life becomes the axis around which financial planning develops and evolves.

But, for physicians, life planning’s quasi-professional and informal approach to the largely isolated disciplines of medically focused financial planning, was still largely inadequate.

Why? 

Today’s personal financial and practice environment is incredibly more complex than it was in 2007-08, as economic stress from HMOs, Wall Street, liability fears, criminal scrutiny from government agencies, IT mischief from hackers, economic benchmarking from hospitals and the lost confidence of patients all converged to inspire a robust new financial planning 2.0 approach for medical professionals.

Example of a financial planning mistake 

Recall the tale of Dr. Debasis Kanjilal, a pediatrician from New York who put more than $500,000 into the dot.com company, InfoSpace, upon the advice of Merrill Lynch’s star but non fiduciary analyst Henry Bloget.

Is it any wonder that when the company crashed, the analyst was sued, and Merrill settled out of court? Other analysts, such as Mary Meeker of Morgan Stanley, Dean Witter and Jack Grubman from Salomon Smith Barney, were involved in similar fiascos.

Although sad, this story is a matter of public record. Hopefully, doctors now understand that the big brokerage houses that underwrite and recommend stocks may have credibility problems, and that physicians got burned with the adrenalin rush of “self-directed” investment portfolios.

Example of a medical practice management mistake 

Just reflect a moment on colleagues willing to securitize their medical practices a few years ago, and cash out to Wall Street for perceived riches that were not rightly deserved

Where are firms such as MedPartners, Phycor, FPA and Coastal now? A recent survey of the Cain Brothers Physician Practice Management Corporation Index of publicly traded PPMCs revealed a market capital loss of more than 95%, since inception. 

Another Approach?

This disruptive narrative shift was formally noted by the Institute of Medical Business Advisors Inc [iMBA, Inc] and introduced to the medical and financial services industry. This research and corpus of work resulted in hundreds of publications in the Library of Medicine, National Institute of Health (NIH) and the Library of Congress, along with related publications, a dozen textbooks and white papers

http://www.ncbi.nlm.nih.gov/nlmcatalog?term=marcinko

The iMBA approach to financial planning, as championed by the www.CertifiedMedicalPlanner.org professional charter designation, integrates the traditional concepts of fiduciary focused financial planning, with the increasing complex business concepts of medical practice management.

The former ideas are presented in our textbook on financial planning for doctors: Financial Planning for Physicians and Advisors

The later in our companion book: Business of Medical Practice [Edition 3.0]

A textbook for hospital CXOs and physician-executives: Hospitals & Healthcare Organizations

While most issues of risk management, liability and insurance are found in Risk Management and Insurance Strategies for Physicians and Advisors

And, for the perplexed, all definitions are codified in the dictionary glossary Health Dictionary Series

Health 2.0 Paradigm Shift

And so, the ME-P community now realizes that a more integrated approach is needed.  The traditional vision of medical practice management, personal physician financial planning and how they may look in the future are rapidly changing as the retail mentality of medicine is replaced with a wholesale philosophy.

Or, how views on maximizing current practice income might be more profitably sacrificed for the potential of greater wealth upon eventual practice sale and disposition.

Or, how Yale University economist Robert J Shiller warns in “The New Financial Order” [Risk in the 21st Century] that the risk for choosing the wrong healthcare profession or specialty might render physicians obsolete by technological changes, managed care systems or fiscally unsound demographics. 

Physician-Executive

My Assessment

Yet, the opportunity to re-vise the future at any age through personal re-engineering, exists for all of us, and allows a joint exploration of the medicine, business and the meaning and purpose of life.

To allow this deeper and more realistic approach, the advisor and the doctor must build relationships based on fiduciary trust, greater self-knowledge and true medical business and financial enhancement acumen.

Are you up to the task?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Understanding Vacation Time Shares

Join Our Mailing List 

Including Participatory Vacation Exchanges

By Rick Kahler MS CFP® ChFC CCIM http://www.KahlerFinancial.com

Rick Kahler CFPFor residents of places like the Black Hills, where the first day of spring usually brings a snowstorm, timeshares for resorts in Florida or Mexico can have a lot of appeal. They seem like a fun idea for a vacation in the sunshine as well as a good deal financially.

My Research

Over the past 30 years I’ve researched hundreds of timeshare offers. I’ve never bought one. When you take a close look at the numbers and the restrictions, they simply don’t add up to a good value.

One of the biggest problems with timeshares in general is that they can lock you into a specific vacation. Spending a week at that resort in Mexico in February, exploring the local area and relaxing by the pool, might be wonderful for a year or even several years. But eventually you may get tired of going to the same location, doing the same things, and seeing the same people. After a while, even a rut person like me might want to do something different.

PVEs

Some timeshares mitigate this problem by participating in vacation exchanges [PVEs] like RCI, Interval International, and others. These services will add on a fee.

Not Liquid

You might think that, if you get tired of a timeshare, you can just sublease or sell it. These aren’t necessarily easy to do. There may be restrictions on subleasing, which is another good reason to read the fine print before you sign any timeshare contract. Selling is often difficult, and you certainly aren’t likely to get back your original purchase price. Meanwhile, you’re  paying annual fees whether you use the timeshare or not.

Total Costs

In figuring the cost of a timeshare, those annual fees are what really get you. You’re told up front what the fees are at the time you buy a timeshare. Yet you have no control over what the fees may be in five or ten years. The only thing you can count on is that they will increase.

Examples:

To illustrate these points, I recently investigated a resale site that listed a timeshare in a property in Boston, MA. It originally sold for $20,000 and was priced at $1,000. I passed on the opportunity because of the high fees.

In another example, I once took a serious look at a timeshare in a luxury apartment complex in London. It seemed like a possibility for fulfilling one of my dreams, living part of the year in Europe.

It wasn’t. As the salesperson told me, comparing the cost to buy a timeshare versus the cost to stay as a non-member, it would take around 30 years to recoup the purchase price. Then I—or more likely, my heirs—would have ten more years to stay for “free.” Free, that is, except for the annual fees.

Dr. Marcinko at Johns Hopkins University

[ME-P Editor-in-Chief in a Spring Fever Garden] 

Investment in Lifestyle

The sales rep was quite clear that a membership at this complex wasn’t intended as a good financial investment. She described it as an “investment in lifestyle.”

So, when it comes to timeshares; that’s the bottom line. If the lifestyle being sold truly fits for you, and you believe it will continue to fit for the long term, then it’s possible that a timeshare may make sense.

Assessment

For most doctors and folks like us however, my conclusion is that most timeshares are too expensive even if someone gives you one. The annual fees alone will keep it from being a good value. I’ve never found one that was cheaper than getting a nice hotel or resort for a couple of weeks. Paying for a hotel stay will cost less in the long run, and you can enjoy relaxing vacations with no long-term commitment.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

The status of African American insurance coverage

Join Our Mailing List

A Struggling PP-ACA Sector    

By FinancesOnline.com

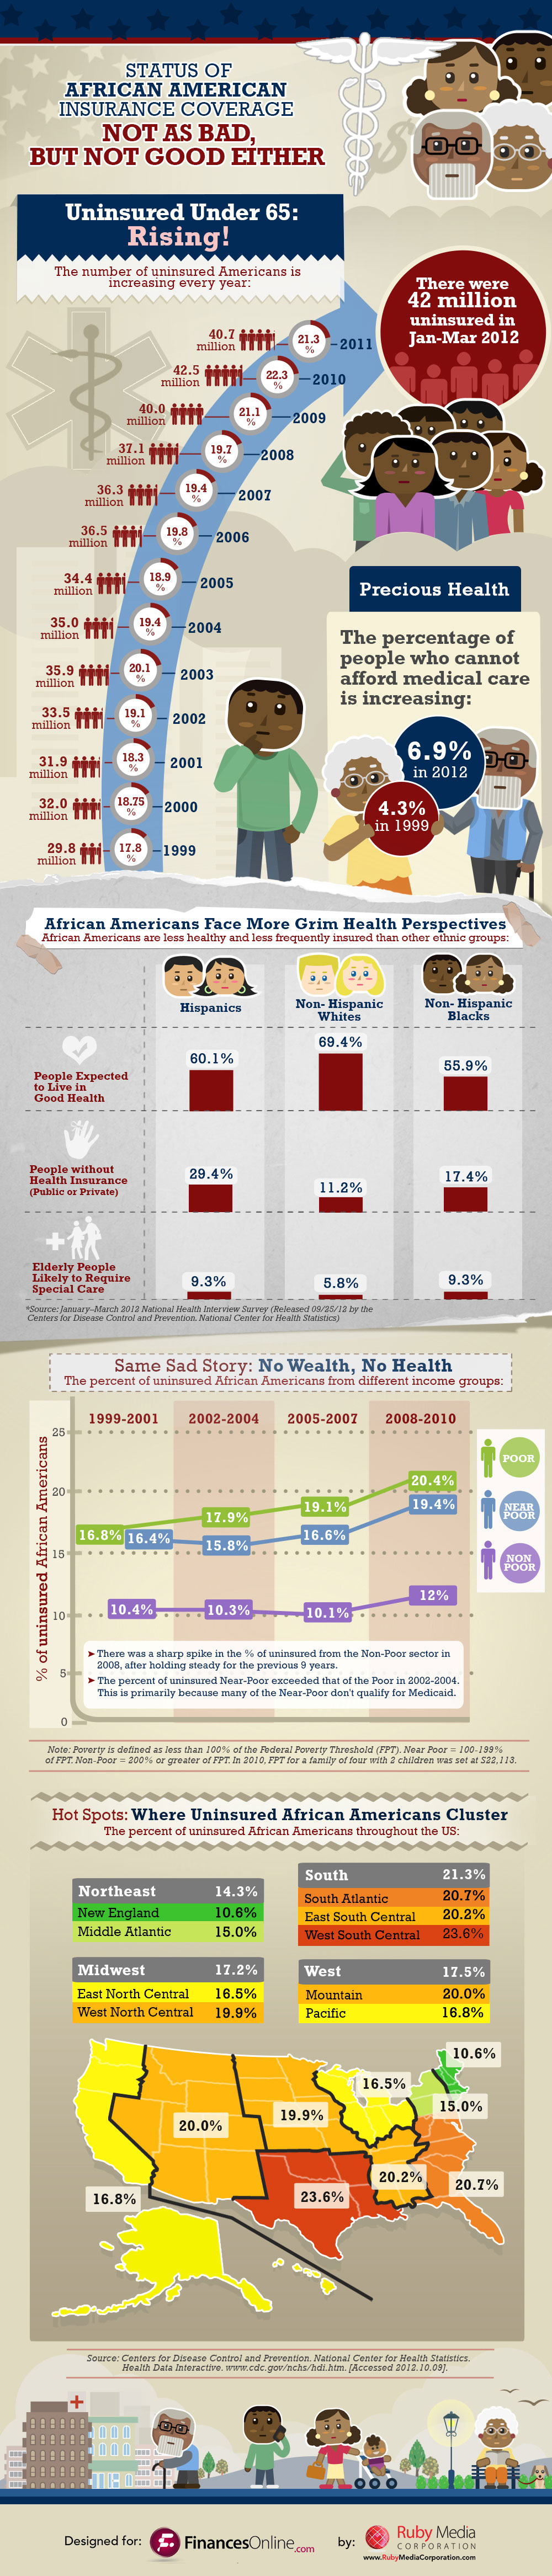
The Affordable Care Act has developed into one of the critical pivots on which the success of President Obama’s second term is expected to turn. Yet, one sector that’s already struggling is African Americans.

In 2012, 17.4 percent of non-Hispanic African Americans were uninsured. More critically, only 55.9 percent of African Americans are expected to continue to live in good health, while a more or less healthy life is expected in 69.4 percen of white Americans.

###

infographic-health-insurance-of-african-americans

###

Assessment

These and other alarming facts were revealed by the National Health Interview Survey of the Center for Disease Control and Prevention, and corroborated by data from the U.S. Census Bureau. Both these agencies were data sources for this infographic, which takes a closer look at the health insurance situation of African Americans.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

But …. enough about me!

Join Our Mailing List

Did you read my interviews?

Dr. David Edward Marcinko MBA

www.MedicalBusinessAdvisors.com

[CEO and Editor-in-Chief]

DEM 2013

AMA News:

Goodwill hunting – what’s your medical practice worth?

AMA News.Valuation.Marcinko

Best practices can help hospitals in recession

Arkansas Medical News:

Arkansas Medical News Interviews Dr. Marcinko

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

About Domestic Asset Protection Trusts

Join Our Mailing List

Is There Stronger Protection in DAPTs?

By Rick Kahler MS CFP® ChFC CCIM http://www.KahlerFinancial.com

Rick Kahler CFPMost financial advisors and attorneys who specialize in asset protection trusts have probably never visited South Dakota. Yet it’s one of their favorite places. A change made by the legislature this year has made them like it even more.

The reason asset protection experts are so fond of our state is that South Dakota is one of a few states (Nevada, Delaware, and Alaska are the others) to offer some of the strongest protections available for Domestic Asset Protection Trusts (About Domestic Asset Protection Trusts).

House Bill 1056

House Bill 1056, passed by the legislature and signed into law by Governor Dennis Daugaard, includes a small change in wording that makes DAPTs even stronger. The relevant section amends South Dakota Codified Law 55-16-15 by adding the five words shown here in all caps:

“Notwithstanding the provisions of §§ 55-16-9 to 55-16-14, inclusive, this chapter does not apply in any respect to any person to whom AT THE TIME OF TRANSFER the transferor is indebted on account of an agreement or order of court for the payment of support or alimony in favor of the transferor’s spouse, former spouse, or children, or for a division or distribution of property in favor of the transferor’s spouse or former spouse, to the extent of the debt.”

This change is not intended to allow divorcing spouses to hide assets from one another, cheat ex-spouses out of alimony, or avoid paying child support. Someone who owes alimony or child support to a former spouse cannot get out of that obligation by contributing assets to a DAPT. Any amounts owed at the time the trust is established must be paid. Attempting to avoid legitimate obligations through a DAPT would be fraud.

On Definitions and Meanings

What the new wording means is that, once a divorce settlement has been agreed upon, former spouses cannot come back later and make new claims against an ex-wife or ex-husband’s protected assets.

For many people, this change is irrelevant. Many divorcing couples, probably the majority, don’t have many financial assets and have never heard of a DAPT. They work out a financial settlement, go their separate ways, and that’s that.

Yet there are cases where this new law could make a huge difference.

Retirement vault

Here are just two examples: 

Suppose that at the time a couple divorce, the husband had just started a construction company. It had more debt than assets and wasn’t making any money yet. Several years later, business is booming and he is well on his way to becoming wealthy. Even though his ex-wife was not involved in building the company, she might try to benefit from his post-divorce success by suing for a share of his assets. He could protect those assets by contributing them to a DAPT.

Or suppose a divorce settlement required the wife to pay her husband a one-time cash amount in exchange for his share of their house and acreage. Several years after the divorce, he isn’t doing so well financially. She’s still living in the house, however, and the value of the property has increased significantly. He might sue to amend the original agreement in an effort to claim part of the real estate. His attempt to change the agreement after the fact couldn’t touch that property if she had contributed it to a DAPT.

Assessment

Until now, Nevada was the only state whose DAPT laws did not make an exception for former spouses. This change in the South Dakota law makes the two states very comparable in their DAPT provisions. It’s one more reason for asset protection professionals to find South Dakota a great place to do business. 

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

A Visual on Health Entitlement Spending

Join Our Mailing List

A Story in Six Charts

By Nancy Chockley PhD www.NIHCM.org

Between the fiscal cliff, sequestration, a potential government shut down and the debt ceiling, Washington is experiencing a seemingly endless succession of budgetary crises.

Although health entitlement programs are often on the table in negotiations, there has been little agreement on the scope and direction of meaningful reform. The recent slowdown in health spending growth may strengthen the impulse on some fronts to delay action, but long-term projections leave little doubt that federal health spending will continue to be a major contributor to our fiscal woes.

Assessment

This chart story pulls together essential facts on how much the federal government is spending on mandatory health care programs, how that spending affects the budget, and the hard spending and revenue trade-offs necessary to improve our fiscal outlook.

chart story

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Are Doctors Protecting their Credit Standing?

Join Our Mailing List

Avoiding Credit Errors

By Lon Jefferies, MBA CFP™  http://www.NetWorthAdvice.comLon Jefferies

A clean, accurate credit history is a critical piece of the personal finance puzzle for doctors and us all. Staying on top of your credit standing over time can mean big savings since credit scores often determine your access to loans, interest rates, and monthly payments. An error on the report of any of the three major credit agencies – Experian, Equifax, or TransUnion – could be catastrophic next time you apply for a loan.

The Services

There are multiple credit-monitoring services you can utilize that charge approximately $15 per month, but these fees likely aren’t necessary. You can order a free credit report from each of the three major credit agencies every year by visiting AnnualCreditReport.com.

Additionally, several services will send you updates from the credit bureaus at no cost. Credit Sesame will track data on your Experian report daily and instantly email you if anything suspicious pops up. There are over 35 triggers for alerts, including new accounts opened, late payments, credit inquires, and address changes. The website also provides a running credit score daily.

Credit Karma has a similar tool that provides free daily monitoring of your TransUnion report. This tool also provides valuable data such as how many lines of credit are evaluated on your credit report and your auto insurance score (used to determine your insurance premiums).

Again, both monitoring tools are free, don’t require a credit card, and take no longer than a couple minutes to sign up for.

stand-out

Assessment

Getting an instant heads-up that there’s been a change in your report could help you fix errors quickly, catch an identity theft at work, or get on top of a delinquent account. As a doctor, you’ve worked hard to establish your credit, so make sure you protect it.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

How to Handle Incurred But Not Reported Health Insurance Claims [Webinar]

Logo

###

Event Information
[Live Audio Conference – Webinar]
Dr. David E. Marcinko MBA
Presenter: Dr. David Edward Marcinko; MBA CMP™
###
Conference Date: Tue, Apr 02, 2013
Aired Time: 1 pm ET | 12 pm CT | 11 am MT | 10 am PT
Length: 60 Minutes
Product Description
###

Here’s How to Augment Bottom-Line Revenues by Understanding IBNR Healthcare Claims

One of most relevant financial issues of the PP-ACA and contemporary healthcare and medical reimbursement is known as Incurred But Not Reported (IBNR) healthcare claims. IBNR claims are an indirect result of prospective payments systems, the insurance industry and commercial risk contracts, and to some extent fee-for-service medicine. IBNR claims represent a risk and an opportunity for managed care companies, healthcare organizations, clinics, physicians and related medical providers alike.

Join this enlightening event presented by expert speaker Dr. David Edward Marcinko MBA CMP™ who will provide you detailed insights on IBNR claims so that you do not face any compliance risk and optimize your organization’s bottom line.

Here is a brief sample of some details you may learn:

  • Historical Review
  • What Is an IBNR Claim?
  • IBNR Problems for Healthcare Organizations
  • IBNR Claims — Management Volume and Consequences
  • Inadequate Cash Flows
  • Reserve Shortfalls and Fiscal Instability
  • Inaccurate Pricing
  • Administrative Cost Increases
  • Regulatory Sanctions
  • Managed Care Organization Exacerbation of IBNR Claims
  • IBNR from a Net Present Value Perspective
  • Tax Strategies for IBNRs
  1. IRS Rules and Regulations
  2. IBNR Tax Qualifications for Managed Care Organizations
  3. How Managed Care Organizations Intensify IBNRs
  4. How Does IBNR Affect Net Present Value?
  • IBNR Challenges and Solutions

1. Tax and Court Penalties

  • IRC Section 4958
  • Excess Benefit Definition
  • Taxes under Section 4958

2.  Tax Deductibility

  • Potential Solutions to the IBNR Challenge
  • IBNR Calculations and Methodology
  1. Actuarial Data Analysis
  2. Open Referral Analysis
  3. Historic Cost Analysis

Ask a question at the Q&A session following the live event and get advice unique to your situation, directly from our expert speaker.

Who should attend? All charge-master coordinators, coding personnel, billing and claims transaction personnel, internal auditing personnel; and financial and compliance personnel! And, all administrators, accountants, comptrollers, office managers, billing clerks and physician-executives, CFOs, CXOs and other interested parties.

IBNRs

###

http://www.audioeducator.com/medical-coding-billing/ibnr_problems-040213.html

ORDER HERE FOR WEBINAR

Beware Automobile Identity Theft and Physician Focused Scams

Join Our Mailing List

Check Your Driver’s License

By Dr. David Edward Marcinko MBA

[Editor-in-Chief]

DEM 2013

WARNING: Did you know that identity theft and physician targeted automobile scams are all the rage.

According to recent FBI reports, and the National Motor Vehicle License Organization [NMVLO], now you can see anyone’s driver’s license on the Internet, including your own! And, medical professionals are the targeted group of choice.

The FIA Culprit

The United States amendment to the Freedom of Information Act, enacted on September 3rd 2008, provides public access to motor vehicle driver’s information in an e-format. Under the Motor Vehicle Operator License Identification  Act (MOLIA), all US states are required  to adhere to the Driver’s statute and store an electronic copy of all valid drivers licenses in their state. And, they do their best to make all license photo’s searchable.

Want Proof?

I just searched for my driver’s license and there it was … picture and all. Thanks Homeland Security!

Go to the web site, and check it out. It’s unbelievable. Just enter your name, city and state to see if your license is on file. After your license comes on the screen, click the box marked “Please Remove.” This will remove it from public viewing, but not from law enforcement.

###

Classic XJ-V8-WB Jaguar

My vintage British 2000 Jaguar XJ-V8-LWB touring sedan 

Jaguar Touring sedan XJ-V8-LWB###

Assessment

As an auto [Jaguar] enthusiast, I am appalled at this situation. Please notify all your friends and ME-P colleagues so they can protect themselves, too.  Believe me – they will thank you for it. Here is the link.

Link: http://www.license.shorturl.com/>http://www.license.shorturl.com/

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Physician Financial Planning IS Medical Risk Management [video]

Join Our Mailing List

By Ann Miller RN MHA

Financial Planning Handbook for Physicians and Advisors

Product Details

Insurance and Risk Management Strategies for Physicians and Advisors

Product Details

[Click on icons for larger image]

###

Business protection strategies for small medical practices

A study recently released by insurance specialist firm The Hartford reveals that small businesses continue to succeed despite challenging economic conditions.

In this video, Ray Sprague, senior vice president for The Hartford’s small commercial insurance segment, shares key takeaways from the study and discusses strategies that small medical practices can implement to protect their business.

VIDEO

http://www.healthcarefinancenews.com/video/business-protection-strategies-small-medical-practices

Gun control dialog

###

Impact of Health Information Technology

Join Our Mailing List

An HIT Infographic

[By HIMSS Clinical Informatics Community]

Practicing clinicians have indicated strong support for the ability of health IT to overcome communication challenges among care providers. Considering that a series of Institute of Medicine reports on errors in healthcare have led to widespread recognition that siloed practices and inadequate communication are primary contributors to medical errors, continued endorsement for health IT will lead to better communication and enhanced quality of care.

The results come from the 2013 iHIT study conducted by HIMSS and HIMSS Analytics, released during HIMSS13, the organization’s annual conference and exhibition. The study was designed to explore the role of health IT from an inter-professional communication perspective. More than 500 clinician respondents working in a care delivery setting provided information on the value of health IT in support of quality care.

Read the Full Study & Final Report

HIMSS 2013 iHIT Study – Final Report
HIMSS 2013 iHIT Study – Executive Summary

 HIT

Assessment

According to the study, the health IT tools in place at the provider organizations of respondents support various clinical processes and provide improved access to the information needed to prepare for delivery of care. This includes having improved access to information needed on patients transferring to a clinician’s unit/caseload, ultimately resulting in enhanced levels of patient care.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Informing Doctors about Automobile Motor Oil Changes

Join Our Mailing List 

What doctors need to know before their next service

[By Dr. David Edward Marcinko MBA and Nalley Lexus-Roswell]

DEM 2013Chances are you might have heard a thing or two about oil prices and all the work it takes to get it out of the ground. You may have even walked into an auto parts store and seen a wall filled with a plethora of different types, viscosities, and brands of oil. Luckily, there are choices to be had, and we’re here to walk you through them.

To Lubricate – Not Burn

Right off the bat, the point should be made clear that motor oil is not meant to be burnt. Sure, oils are used to make the gasoline and diesel fuels that power our vehicles, but motor oil is purely there to lubricate the internals of your engine, not to be burnt as an energy source. It’s that type of burning that causes some of the environmental issues. If you notice a blue smoke emitting from the tailpipe of your vehicle, and the need to add oil every so often, your engine might have a serious problem.

But, for normal motor oil usage, the lubrication of engine internals to keep metal from touching metal while the various bits and pieces move a couple thousand times a minute, there are basically two types – conventional and synthetic.

My Jaguar's engine after a steam

Conventional Oil

Conventional motor oil has done a great job for the past hundred years or so, and is still largely the norm when it comes to servicing your vehicle. Why is this? For the vast majority of drivers in normal vehicles, conventional motor oil meets the vehicle’s needs while being lower cost. In fact, a quart of conventional motor oil will only set you back half of what a quart of synthetic oil costs.

What are some of the benefits of conventional motor oil? First of all, there’s the cost proposition. And if you drive a normal vehicle, conventional oil might actually be a better choice, as it’s a thicker substance. Also, for that same reason, conventional oil is often the lubricant of choice in higher-mileage engines, where some worn components might not have the ability to seal that they once had.

Synthetic Oil

Synthetic motor oil, however, is the new wave of engine lubrication. First designed for aircraft applications in the 1970s, it has also found a home in the engines of many high-performance vehicles. With the requirement of maintaining lubricating abilities at high altitudes and temperatures in aircraft, it was a natural fit. Because of the higher tolerances of aircraft and high-performance engines, the thinner nature of synthetic oil is meant to squeeze into every nook and cranny available, exactly what is needed in these finely-crafted engines.

While synthetic oil might cost twice as much as conventional, it’s thermal properties that keep it from breaking down over time mean that oil changes can occur less often at higher mileage intervals, saving you headaches and recouping some of those costs. Also, due to its thinner nature, it flows easier in cold weather, meaning less warm-up time for your engine, decreasing, once again, headaches and harmful exhaust fumes.

My Kitty Oil

I’ve got a near showroom and mint conditioned 2000 Jaguar XJ-V8-LWB. It  is a full-size luxury sedan, offering sporting drive characteristics, mixed with a classic style and interior comfort. It was available in multiple trims which all came very well equipped with upscale amenities. And, this extended wheelbase version offers much more rear seat leg room for long and winding Georgia road trips. The standard steel engine [not nikasil] in this XJ is a 4.0L V8 which produces 290 hp. The upper and lower timing chain tensioners are original, second generation metal, not plastic.

There is also a supercharged version of this vehicle which bumps output to an impressive 370 hp. Even with all of its power and weight, my XJ-8-L is still rated at over 20 mpg on the highway. Ammenities and upgrades include a mobile phone, Magellan GPS, LoJack theft recovery system, CD and MP-3 players, with internal and external cable antenna for satellite radio.

As for oil, my owners manual calls for 10w30 as preferred, but 10w40 is acceptable for hotter climates like Atlanta. Since my XJ-8 has 90,000 miles on it, I tend to use something a little thicker 15w40 and might used 20-50 come summer if it starts consuming in the high heat.

What a Cat!She is my third favorite female after my intelligent and beautiful wife, and smart and lovely daughter.

Assessment

Now that we know the key differences in the available types of motor oil, which should you choose at your next service? For that, your mechanic will take into account your driving style, vehicle mileage, and other factors, and help you decide what is best for your vehicle.

XJ-V8-LWB Jaguar touring sedan


Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

More on the Doctor Salary “WARS” – er! ah! … CONUNDRUM!

Join Our Mailing List

Compensation Trend Data Sources

cropped-dem

By Dr. David Edward Marcinko MBA

[Editor-in-Chief] www.BusinessofMedicalPractice.com

Related chapters: Chapter 27: Salary Compensation and Chapter 29: Concierge Medicine and Chapter 30: Practice Value-Worth


***

PERSONAL PREAMBLE

***

Physician compensation is a contentious issue and often much fodder for public scrutiny. Throw modern pay for performance [P4P], and related metrics, into the mix and few situations produce the same level of emotion as doctors fighting over wages, salary and other forms of reimbursement.

This situation often springs from a failure of both sides to understand mutual compensation terms-of-art when the remuneration deal was first negotiated. This physician salary and compensation information is thus offered as a reference point for further investigations.

Introduction 

More than a decade ago, Fortune magazine carried the headline “When Six Figured Incomes Aren’t Enough. Now Doctors Want a Union.” To the man in the street, it was just a matter of the rich getting richer. The sentiment was quantified in the March 31, 2005 issue of Physician’s Money Digest when Greg Kelly and I reported that a 47-y.o. doctor with 184,000 dollars in annual income would need about 5.5 million dollars for retirement at age.

Of course, physicians were not complaining back then under the traditional fee-for-service system; the imbroglio only began when managed care adversely impacted income and the stock market crashed in 2008.

Today, the situation is vastly different as medical professionals struggle to maintain adequate income levels. Rightly or wrongly, the public has little sympathy for affluent doctors following healthcare reform. While a few specialties flourish, others, such as primary care, barely move.

In the words of colleague Atul Gawande, MD, a surgeon and author from Brigham and Women’s Hospital in Boston, “Doctors quickly learn that how much they make has little to do with how good they are. It largely depends on how they handle the business side of practice.”  And so, it is critical to understand contemporary thoughts on physician compensation and related trends.

Compensation Trend Data Sources

A growing number of surveys measure physician compensation, encompassing a varying depth of analysis. Physician compensation data, divided by specialty and subspecialty, is central to a range of consulting activities including practice assessments and valuations of medical entities. It may be used as a benchmarking tool, allowing the physician executive or consultant to compare a practitioner’s earnings with national and local averages.

The Medical Group Management Association’s (MGMA’s) annual Physician Compensation and Production Correlations Survey is a particularly well-known source of this data in the valuation community. Other information sources include Merritt Hawkins and Associates; and the annual the Health Care Group’s, [www.theHealthCareGroup.com] Goodwill Registry.

###

Portfolio analysis

www.CertifiedMedicalPlanner.org

Assessment

However, all sources are fluid and should be taken with a grain of statistical skepticism, and users are urged to seek out as much data as possible and assess all available information in order to determine a compensation amount that may be reasonably expected for a comparable specialty situation. And, realize that net income is defined as salary after practice expenses but before payment of personal income taxes.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™ Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

***

Invite Dr. Marcinko

***

A New Test For Alzheimers Disease [Video Humor]?

Join Our Mailing List

A MOVING PUZZLE

By Dr. David Edward Marcinko MBA

[Editor-in-Chief]

DEM at Univ of PittsburghLast month, I had the opportunity to visit and tour the University of Pittsburgh and the Tower of Learning.

While there, I was given this brain teaser by one of the graduate students. I was told that if you can put this moving puzzle together; you may just be able to say goodbye to Alzheimer’s Disease!

Now, this is really clever and a bit challenging. So, much as we middle-aged folks are concerned with Alzheimer’s disease, this puzzle may help dispel some fear. Give it a try. Just remember, I was told that if you can put this puzzle together … you probably do not have to fear Alzheimer’s!

CLICK BELOW:

http://www.brl.ntt.co.jp/people/hara/fly.swf

Hint: you can move the puzzle pieces outside of the box to separate them to get a better look. Use left clicker to move the pieces around.

Assessment

It took me about 5 minutes to put it together. What about you?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

ME-P Book Reviewers Needed

Join Our Mailing List
New Text Book Testimonials Requested
By Dr. David Edward Marcinko MBA
[Editor-in-Chief]
DEM 2013
Greetings all ME-P Readers from Atlanta, Georgia
###
After reading and being inspired by Dr. Atul Gawandi’s December 10, 2007 New  Yorker article, “The Checklist”, as well as the Checklist Manifesto, I am writing to ask that you consider this request to write a 3-5 sentence testimonial review to our upcoming new textbook:  Financial  Management Strategies for Hospitals and Healthcare Organizations: Tools,  Techniques, Checklists and Case Studies

It is the follow up to: Hospitals & Health Care Organizations: Management Strategies, Operational Techniques,  Tools, Templates, and Case Studies

Book Focus

Please realize that the focus of the work is non-clinical in nature, and is replete with managerial case models and administrative checklists following each chapter.

Just as Atul believed the time is right for medical checklists, we believe in a similar philosophy for hospitals, health enitites, and healthcare administration. It is right for any physician or medical practitioner, regardless of degree or specialty designation.

New Book

Ideal Reviewers

Ideal book reviewers are doctors, financial advisors, economists, accountants, nurses, insurance agents, politicians and healthcare CXOs. So, please see the TOC links as we ask you to keep this request confidential.  Regardless of your decision, we remain an apostle of your core vision whenever possible.

Fraternally,

Dr. David Edward Marcinko MBA

[Editor-in-Chief]

INSTITUTE OF MEDICAL BUSINESS ADVISORS, INC.

Suite #5901 Wilbanks Drive Norcross, Georgia, 30092 USA

Phone: 770.448.0769

MarcinkoAdvisors@msn.com

Secrets

###

Strategic Importance of Healthcare Capital Investing

Join Our Mailing List

For Leaders, Governors, Physicians and Hospital Executives

[By Calvin Weise CPA, CMA]

Some of the most important strategic decisions hospital executives make are related to capital expenditures. Almost every hospital has capital investment opportunities that are far in excess of their capital capacity. Capital investments are bets on the future. How these capital bets are placed has long-lasting implications. It is of utmost importance that hospitals bet right.

Hospitals as Business Entity

Hospitals are capital intensive businesses. Hospital buildings are unique structures that require large amounts of capital to construct and maintain. Inside these buildings are pieces of expensive equipment that have fairly short lives. Technological innovations continually drive demand for new and more expensive equipment and facilities. The ability to continually generate capital is the lifeblood of hospitals. In order to compete and succeed, it’s imperative for hospitals to continually invest in large amounts of capital equipment and expensive facilities.

Capital investment is fueled by profit. In order to continually make the necessary capital investments, hospitals must be profitable. Hospitals unable to generate sufficient profit will fail to make important capital investments, weakening their ability to compete and survive.

Hospital managers bear important responsibility in choosing which capital investments to make. There are always more capital opportunities than capital capacity. In many cases, capital opportunities not taken by hospitals create openings for others with capital capacity to fill the vacuum. By not taking such opportunities, hospitals are weakened, and their operating risk increases.

Responsibility

Stewardship is a term that aptly describes the responsibility borne by hospital managers in making capital investments. The New Testament parable of the talents describes this kind of stewardship. In this story, a merchant entrusted three managers with money to invest. One manager was given five units, another two, and a third one. At the end of the investment period, the two managers given five units and two units reported a 100% return. The manager given one unit reported zero return — he was fired and his unit was given to the first manager.

Healthcare Investment Risks

Leadership

This is stewardship — and hospital managers are stewards of their organizations’ assets. Too often, not-for-profit hospital managers hold an erroneous view of the returns expected of them. Like the third manager in the parable, they think zero return on equity is acceptable. They understand capital investment funded by debt needs to cover the interest on the debt, but they view capital investments funded by equity as having no cost associated with the equity. From an accounting perspective, they are right. From a stewardship perspective they are dead wrong — just like the third manager in the parable.

Here’s why: as stewards, they are responsible for managing the entrusted assets. They can either put these assets at risk themselves, or they can put those assets in the market and let other managers put them at risk. If they choose to put them at risk themselves, then they have the mandate of creating as much value from putting them at risk as they would realize if they put them in the market for other managers to put at risk. They have the duty to realize returns that are equivalent to the returns they could realize in the market; otherwise, they should just put them in the market. They can either invest in hospital assets or work the assets themselves, or they can invest in financial market assets so others can work the assets. When they choose to invest in hospital assets, the required return is not zero. That’s the return they get fired for. The required return is equivalent to market returns.

Assessment

Thus, when evaluating performance of hospital management teams, the minimum acceptable performance level is return on equity that is equivalent to the return that could be realized by investing the hospital assets in the market. And when evaluating a capital investment opportunity, it is important to apply a capital charge equivalent to the hospital’s weighted cost of capital — a measure that imputes an appropriate cost to the equity portion of the capital along with the stated interest rate for the debt portion of the capital structure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Market for Mobile Health App Services Will Reach $26 Billion By 2017

Join Our Mailing List

mHealth services start to leverage apps to become commercially successful

[By Markus Pohl]

The market for mHealth services has now entered the commercialization phase and will reach $ 26 billion globally by 2017 says the new “Global Mobile Health Market Report 2013-2017 ”by research2guidance. Smartphone applications have begun to enable the mHealth industry to successfully monetize their services.

The Impending Revolution

Ralf-Gordon Jahns, Head of Research at research2guidance, points out “Our findings indicate that the long-expected mobile revolution in healthcare is set to happen. Both healthcare providers and consumers are embracing smartphones as a means to improving healthcare.”

The Publishers

Top mHealth publishers manage to generate more than 3 million free and 300.000 paid downloads in the USA on the iOS platform. The reach on other platforms and in other countries differ at lot but show also the increase of business potential for mHealth apps.

Not only are consumers taking advantage of smartphones to manage and improve their own health, but also healthcare professionals. A significant number (15%) of mHealth applications are primarily designed for healthcare professionals. These include CME (Continued Medical Education), remote monitoring and healthcare management applications.

The Climate

Currently there are 97,000 mHealth applications in major app stores, 42% of them adhering to the paid business model. With more and more traditional healthcare providers joining the mobile applications market, the business models will broaden to include healthcare services, sensor, advertising and drug sales revenues.

“With the growing sophistication level of mHealth applications, only 9% of the total market revenue in the next 5 years will come from application download revenue”explains Patrick Houck Analyst at research2guidance. “84% of total mHealth application market revenue will come from related services and products such as sensors”.

###

eHRs

Assessment

The “Global Mobile Health Market Report 2013-2017 ”by research2guidance is a business guide for traditional healthcare companies, mHealth specialists as well as for mobile operators wishing to successfully engage into the new mHealth market.

About research2guidance:

research2guidance is a Berlin-based mobile app economy specialist. The company’s service offerings include app strategy consulting, market studies and research.

Link to blog post: http://www.research2guidance.com/the-market-for-mhealth-app-services-will-reach-26-billion-by-2017/

Link to graph: http://www.research2guidance.com/wp-content/uploads/2013/03/the-mhealth-market-has-reached-the-commercialization-phase.png

Link to report: http://www.research2guidance.com/shop/index.php/mhealth-report-2

Contact:

Ralf-Gordon Jahns [+49 30 609 893 362] ralf.jahns@research2guidance.com

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Is your Financial Advisor a Psychopath?

Join Our Mailing List

On Going Rogue?

Research shows the financial industry attracts more than its share of charming, manipulative egotists. Or, does it?

Avatar of Dr. Marcinko Speaking as MSL

Assessment

Here is what to watch for:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Medicare Inpatient Profitability in US Hospitals

Join Our Mailing List

The Impending Need for Cost-Efficiency

[By Objective Health]

Medicare patients often account for the largest proportion of inpatient volume for an average US hospital. With the exception of outlier cases, Medicare inpatient services are adjusted for wage rates and reimbursed as a single predetermined payment across the country.

Over the next few years, Medicare is expected to substantially reduce growth in payment rates, thereby pressuring hospitals to become more cost-efficient.

###

Medicare OH

###

Assessment

This infographic highlights the need for hospitals to manage costs, showing that there is a wide variation in Medicare inpatient profit across US hospitals, which is primarily driven by differences in Medicare cost per case.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

###

Paying for College

Join Our Mailing List

Maybe Not!

By Rick Kahler MS CFP® ChFC CCIM www.KahlerFinancial.com

Rick Kahler CFPDo you want to give your children the best possible chance to do well in college, earn higher salaries, and save more for their retirement? Then, don’t pay for their college education.

One of the most popular money scripts I encounter is the notion that being a good parent means paying for your child’s college. Many parents do this at the expense of taking care of themselves in retirement, which is a very high price to pay.

The most popular reason I hear from clients for funding children’s’ education is empowerment. They want to spare kids the burden of repaying school loans after graduation. They also want them to be able to focus on their studies without the distraction of having to work to put themselves through college. For most parents, allowing students to concentrate on classes so they can perform well, make better grades, and obtain better jobs, is a sacrifice worth making.

The Myth

There’s just one problem with this scenario. It’s a myth.

In most cases, parents who fund their kid’s’ college education are insuring they will actually do worse in school than those who have to pay their own way. This is the finding of new research conducted by Laura T. Hamilton, published January 7, 2012, by The American Sociological Review under the title “More Is More or More Is Less?” Her study shows that students whose education is funded by parents or through student loans actually have lower GPA’s than students who in some way must work to put themselves through school.

Hamilton found that students who have to “do something” requiring them to take personal responsibility for obtaining the funds for their education do best and carry higher GPA’s. This includes those who receive grants, scholarships, or veteran’s benefits, or who participate in work-study programs.

Parental funds or borrowing “provide the time, money, and proximity (i.e., living on or near campus) necessary to delve deeply into college peer cultures,” Hamilton notes. The gift of time that student loans and parental funding provide isn’t usually poured into studies. Instead, students tend to focus that extra time on increasing their social life. The average college student receiving money from loans or parents spends less time on studies in college than in high school. Even though they spend about 28 hours a week attending class and studying, the research found they devote a full 41 hours a week to social and recreational endeavors.

Put more succinctly, students who have to work to pay their way through college spend slightly more time studying and significantly less time partying.

The Results 

The net result in this is a big personal and societal lose-lose. Those of you who have sacrificed your retirement to help your children through college have potentially done harm to both your children and yourselves. Your kids have probably done worse in college, thus obtaining lower paying jobs. This loss of potential income has downsides for both children and parents. Previous research has shown that parents who don’t fully fund their own retirement years will actually end up costing their children five times as much as the kids would have spent by funding their own college education.

Understandably, a few of you are now choking on your last sip of coffee as you read the last paragraph. This is not at all the outcome you intended.

Money

Assessment

The evidence is clear. Parents who take care of fully funding their own retirement instead of sacrificing to pay for their kids’ education are not being selfish. Instead, they give their children something far more valuable than the cost of tuition: the gift of success and achievement.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Understanding the Pre-Reform Impact of Self-Pay Patients

Join Our Mailing List

On Us Hospitals

Source: Objective Health

Pre-reform, many hospitals experience significant uncompensated care costs from self-pay patients.

###

Reform Impact

###

This infographic illustrates the variation in self-pay uncompensated care costs across US hospitals and regions.

Assessment

Despite the uncompensated care risk, 1/6th of self-pay inpatients are scheduled admissions, though their procedures are much less elective than the procedures of the insured.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details

Deducting Un-Reimbursed Professional Expenses

Join Our Mailing List

Tax expenses must be”ordinary” and “necessary”

By Andrew D. Schwartz CPA http://www.schwartzaccountants.com

Andrew SchwartzAccording to the IRS, to be deductible, the expenditure must be both “ordinary” and “necessary” in connection with your medical profession or specialty.

The Definition

The IRS defines “ordinary” as common and accepted in a particular profession and “necessary” as helpful and appropriate for a particular profession.

The List

Here’s a list of 16 professional expenditures commonly incurred by young or mature health care professionals:

  • Automobile expenses
  • Beepers and pagers
  • Books/library
  • Cellular telephones
  • Computer purchases
  • Education, examinations & licenses
  • Equipment & instruments
  • Job search
  • Malpractice insurance
  • Meals & entertainment
  • Parking & tolls
  •  Professional dues, journals & subscriptions
  • Psychoanalysis as part of training
  • Supplies
  • Travel & lodging
  • Uniforms & cleaning

Assessment

Please note: Employees, like hospitalists, may not deduct professional expenses that are eligible for reimbursement from their employer.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product DetailsProduct DetailsProduct Details

Why are Medical Bills so High [video]

Join Our Mailing List______________________________

TIME’s Best Cover Story … Ever?
###
TIME magazine just dedicated its current issue to just one article: “Bitter Pill: Why Medical Bills Are Killing Us.”
###
The article, written by Time contributor Steven Brill, is required reading for all healthcare providers, administrators, legislators, patients — basically, everyone; especially readers of this ME-P.

The article is too comprehensive to summarize in one blurb, but Mr. Brill did a good job of describing its origins to Jon Stewart on The Daily Show.

Throughout all of the discussions during the Obamacare debate, the focus was usually on who should pay the medical bills.  Brill said, “We never asked the first question: Why are the bills so high?”

###

###

Assessment

We wish we could say we thought of this, but it was Matt Yglesias who did.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

***

Hiring a Director of Post-Surgical and Specialty Care

Join Our Mailing List

For an independent community hospital in the Midwest

By B. Kim Woods RN

[National Healthcare Practice Manager]

Dear Dr. David E Marcinko,

GREETINGS!

Our client has engaged the THOR Group to assist them in hiring a Director of Post-Surgical and Specialty Care for their 260-bed, not-for-profit, JCAHO-accredited, independent community hospital located in the beautiful Midwest.

If any of your ME-P readers is a Registered Nurse with supervisory experience interested in furthering their career in an innovative, high- technology organization, and have a passion for leading a professional team in their provision of high quality patient care, this could be just the job for them.  So, if you know of someone who may be interested in this opportunity, please let me know!

Please see the overview and description of the location below and contact: Kim Woods, RN,  at (816) 401-6622 or email your resume to kimberlyw@thorgroup.com today!

OVERVIEW: 

This Nursing Director is responsible for 3 units: a 10-bed orthopedic post-operative unit, a 12-bed OB/GYN unit comprised of 4 surgical rooms and 8 LDRPs, and a 27-bed post-operative unit with a total of 65 FTEs. You will be leading a professional team to ensure the highest quality of patient care in an innovative, state-of-the art facility.  The organization strives to be the Employer of Choice, committed to upholding their core values, providing highly competitive compensation and benefits, as well as remaining focused on their vision of passionately pursuing excellence in collaboration with physicians, staff, and the community.

###

ME-P Careers

###

ABOUT THE LOCATION:

This beautiful Midwest location has a population of approximately 30,000, yet is just 35 miles from the largest city in the state and 50 miles from the state capitol. Educational, cultural, historic, and outdoor activities abound. The retail sector boasts a thriving downtown historic business district with a wide range of shopping choices that fill the needs of the most discriminating shopper. This community is just right for people who want to enjoy good neighbors, a low crime rate, and an exceptional quality of life.

ABOUT THOR:

For nearly 40 years, The THOR Group, Inc. has provided cutting-edge business solutions to 50,000 top companies and leading healthcare providers throughout the United States.

Regards,

Kimberly Woods, RN, BSN, MBA
National Healthcare Practice Manager
Direct Line: (816) 401-6622
kimberlyw@thorgroup.com

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

What to do with a $25,000 Windfall?

Join Our Mailing List

What Do … You Do?

Doctor – Suddenly you receive a check for a large sum of money?

This infographic has some suggestions on what to do with that extra cash that will have a positive effect on your finances in the long-run.

###

mint-windfall-25kkf-copy

Assessment

Now, suppose the windfall was $250,000 or $2,500,000 or even more! What to do?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

  Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™
Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Healthcare Adversaries [video]

Join Our Mailing List

Of HHS and AHIP

By Darrell K. Pruitt DDS

pruitt6If HHS and AHIP continue to give doctors the bum’s rush, what languages can we expect migrant providers to speak well?

The Conference

Last week, I came across a video of a health care conference held a month ago at the University of Miami. During a discussion period, a Miami spinal surgeon named Dr. Nordham warned that more Medicare pay cuts will make small, solo practices like his unsustainable.

Karen Speaks

Panelist Karen Ignagni, who is president and the CEO of America’s Health Insurance Plans (AHIP), reacted defensively in favor of continued unsustainable discounts – but with a hasty, disingenuous response: “We’re seeing out of network charges of 95 times Medicare fees.” While as if on cue, former HHS Secretary Donna Shalala, who is also president of the university, offered her cold interpretation of the small business owner’s legitimate fears: “He’s really complaining that the price is going down [according to law].”

Shalala Speaks

After also ignoring the physician’s plea, “There needs to be more transparency,” Shalala and Ignagni continue an irrelevant, buzzword-filled discussion with each other using flowing hand gestures while shutting out the doctor’s attempts to bring the conversation back on topic. Then abruptly, without giving Dr. Nordham the opportunity to say another word, Shalala slammed the door: “…. I think we’ll take the next question, thank you.” Then she threw him a bone, “It’s a very important question, though.”

###

MD with eHR

Assessment

The 4 minutes of unvarnished disrespect of Dr. Nordham is so transparent that one wonders whether Shalala and Ignagni were even aware that their half-baked PR game was being recorded for C-span.

http://www.c-spanvideo.org/event/214023 (from 2:09:53 to 2:13:42)

They probably thought nobody stays up that late.

More: Chapter 13: IT, eMRs & GroupWare

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details

A Better Approach to [Hospital] Cost Estimation

Join Our Mailing List

Re-thinking the Ratios-of-Costs-to-Charges [RCCs] Financial Meter

By Russ Richmond MD

Russ Richmond MDUsing the ratios-of-costs-to-charges [RCCs] can lead hospitals down a garden-variety strategic path that’s wrong for them.

A strategically safer method of cost estimation can more accurately reveal costs.


At a Glance

  • Using ratios of costs to charges (RCCs) to estimate costs can cause hospitals to significantly over- or under-invest in service lines.
  • A focus on improving cost estimation in cost centers where physicians have significant control over operating expenses, such as drugs or implants, can strengthen decision making and strategic planning.
  • Connecting patient file information to purchasing data can lead to more accurate reflections of actual costs and help hospitals gain better visibility across service lines.

To put it bluntly, there is an almost complete lack of understanding of how much it costs to deliver patient care, much less how those costs compare with the outcomes achieved. Instead of focusing on the costs of treating individual patients with specific medical conditions over their full cycle of care, providers aggregate and analyze costs at the specialty or service department level.

—Professors Robert Kaplan and Michael Porter, “The Big Idea: How to Solve the Cost Crisis in Health Care,” Harvard Business Review, September 2011.

Of all the challenges hospitals face in today’s uncertain healthcare environment, estimating their costs might not be their top concern. However, the method most hospitals use to estimate their costs can have serious strategic and financial ramifications on their bottom line.

More than 60 percent of hospitals today use ratios of costs to charges (RCCs) as their primary cost estimation method, because true cost accounting is viewed as prohibitively expensive. But using RCCs to estimate costs can lead to significant problems for hospitals. For example, results of a recent study disclose that among 184 mid-sized community hospitals (i.e., with roughly 300 beds), the use of RCCs led 85 percent of the hospitals to overestimate the profitability of orthopedic surgery service lines. On average, the overestimates amounted to $1.2 million per year per hospital.

Such incorrect cost estimates can cascade into potentially serious strategic, financial, and operational issues. Because of faulty cost estimates, hospitals can over-invest—or under-invest—in service lines based only on high-level insight into the actual profitability of these areas. Either scenario has the potential to produce negative consequences.

Suboptimal strategic decision making based on faulty data and conclusions leads to suboptimal results. No hospital can afford such results and stay competitive in an industry of increased cost and pricing transparency.

So what’s the solution for hospitals? Even without switching to a full procedural cost-accounting system, hospitals can make adjustments that improve their cost estimating and thus strengthen their decision making and strategic planning. The operative principle is that hospitals should focus on improving cost estimating in cost centers where physicians have the most control of operating expenses—namely, drugs and implants.

Making the Right Cost Connections

Connecting patient file information, where costs are estimated, with purchasing data, which reflect actual costs, can produce a significant impact on a hospital’s pricing methodology. Drugs and implants, which represent 17 percent of a typical hospital’s total costs, are a good starting point for adoption of this approach.

Drugs. To better estimate drug prices, hospitals should make the patient file/purchasing data connection based on generic class, route of administration, and dosage. The patient charge file and the purchasing file can be connected using a common taxonomy. For instance, a hospital’s purchasing file may record a box of 10 Tylenol tablets as “10 Tylenol tablets of 325 mg,” while the charge may be recorded in the patient charge file as “Acetaminophen cap 325.” This results in a direct text mismatch for calculating cost, which can ultimately lead to faulty cost-estimating data. A common taxonomy would group these two entries into a common bucket to produce an accurate mapping of costs.

Implants. Implants are also a major price item for hospitals. To better estimate implant costs, the patient charge file and the purchasing file should be mapped using the implant log, using the same process described for mapping drug costs. The implant log is used by surgeons after an operation to log the type of procedure, detailed description of supplies used, and general comments.

When a physician orders a knee implant, the implant stock-keeping unit (SKU) number is often recorded in the implant log. If the SKU number in the implant log were mapped to the SKU number in the hospital’s purchasing file, the hospital would be better able to determine the actual cost for the implant. The cost could then be assigned to the patient file, resulting in a more accurate cost picture for orthopedic cases.

For example, to assign true implant costs to a patient who has undergone a knee replacement, a hospital would look up the implant SKU recorded in the implant log by the physician—in this example, SKU123. Then, the hospital would open the purchasing file and locate, for that particular month, the description and price for SKU123 (in this instance, XYZ knee replacement part; cost: $4,950). Next, the hospital would map the more detailed description and price for the implant to the patient charge file. This process can help to ensure that the true cost of the implant used by the physician is assigned to the patient’s charge file.

In some hospitals, the implant log, purchasing file, and patient charge file are part of the same system. For the majority of hospitals, however, the implant log is a separate electronic file, not connected with the other file system or systems. And in some hospitals, the implant log is manually managed.

A hospital can complement this process by comparing its drug and implant costs with price benchmarks from subscription-based national databases or with databases maintained by consulting firms. In our experience, a 65 percent match can be achieved by connecting the drug and implant purchasing files with the detailed charge files, as outlined above. By comparing these costs with price benchmarks from subscription-based or consulting-firm databases, a hospital can better determine how the prices it is paying for drugs and implants compare with national averages.

By connecting these data sets, hospitals can gain better visibility of what they are really spending across various service lines and operational functions.

Understanding a Rural Hospital’s True Costs

The experience of a 250-bed rural hospital in the north central United States provides a good example of the pitfalls of using RCCs to estimate costs. This hospital found itself making key strategic planning decisions based on misleading cost data.

In analyzing the drug usage data from two physicians (A and B) at the hospital, physician B appeared more cost-efficient than physician A at treating the same disease. However, on examining physician B’s actual drug expenditures, hospital leaders realized this physician’s costs were in fact higher than those of physician A (see the exhibitbelow).

###
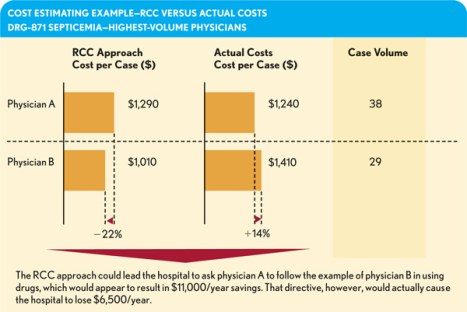
f-richmond

###

If RCC costs are considered, physician A seems to be treating patients at a higher average cost per case than physician B. But if actual costs are considered, physician A is actually treating at a lower cost per case than physician B. Strategically, based on the RCC analysis, if the hospital encouraged all of its physicians to emulate physician B’s treatment approach, it would lose the opportunity to save money on every case.

The data generated by RCCs can be especially problematic in measuring the profitability of various hospital services lines. Because of these misleading cost data, the team at this rural hospital was under the impression it was making a healthy $477,000 profit annually from its orthopedic surgery group.

The reality was the hospital’s profit from this key service line was about $170,000 less—a material difference for a rural community hospital.

For years, the provider thought it was making money on hip replacement surgery, but those profits were much lower because costs of implants used in these orthopedic procedures were continually underestimated. An incorrect profitability picture such as this can wreak havoc on vital strategic-planning efforts.

The rural hospital is by no means an outlier in regard to its problems with cost estimation. The research finding cited at the beginning of this article suggests institutions regularly underestimate costs per orthopedic procedure (and the costs of implants) because of their use of RCCs.

Rising costs are at the heart of the cost challenges that are prevalent in health care. Healthcare reform was designed, in part, to help alleviate this persistent cost problem, but much work still needs to be done to fully understand the true costs of health care. Once these costs are better understood, the goal then must be to manage costs more effectively, efficiently, and sustainably. A critical starting point is for healthcare providers to have a more accurate and realistic picture of what their current costs are, not what they think costs may be.

By connecting key data sets and analyzing costs in a more systematic way, hospitals can develop a stronger and more accurate understanding of their actual costs. This system will provide more data visibility to enable hospital leaders to enhance strategic decision making related to key service lines, improving value.


About the Author

Russ Richmond, MD, is CEO, Objective Health, Waltham, Mass., and a member of HFMA’s Massachusetts-Rhode Island Chapter (russell_richmond@mckinsey.com).


Footnotes:
a. This amount is based on an average overestimation in contribution per orthopedic surgery case of $1,200 multiplied by an average of 1,000 cases annually per hospital.


###
Sidebar 1:  A Step-by-Step Guide to Improving Hospital Cost-Estimating Processes

Hospital leaders should follow four relatively easy-to-implement steps to improve their cost-estimating processes related to drugs and implants—two cost centers where physicians have significant control over operating expenses.

Step 1: Establish the Data Foundation
Ensure that the hospital has core data sets on which to develop. Keep the following practices in mind:

  • All encounters and detailed charges should be available in corresponding files.
  • All purchased drugs, implants, and other medical/surgical products should be available in a purchasing file (often provided by the group purchasing organization or distributor).
  • All implants should be tracked in electronic implant logs (e.g., in the operating room, intensive care unit, and cath lab).

Step 2: Assemble a Cost-Estimate Improvement Team

This team, which will lead the project, should include the following representatives:

  • Director of pharmacy, to provide guidance and sign-off on drug cost estimates
  • Materials manager, to provide guidance and sign-off on implant cost estimates
  • Chargemaster manager, to incorporate input from pharmacy and materials departments into the granular charge codes that are charged to patients
  • Analytics expert, to connect purchasing files, implant logs, and patient charge files
  • Strategy and finance leaders, to leverage the improved cost accounting to derive savings and align on growth strategy. 

Step 3: Connect the Data Sets

The analytics expert connects the data sets as described in the “Making the Right Cost Connections” section of this article. 

Step 4: Leverage Insights from True Cost Data

Three areas of understanding or capability can ensure that a hospital can put the cost data to effective strategic use.

Understanding of actual profitability of service lines/departments and definition of growth strategies.

A hospital with true cost data can understand which service lines drive most of its profit and which departments lead to maximum losses. This understanding enables hospitals to strategically define departments they should invest in and areas where they should become leaner. On the other hand, a hospital that uses ratios of costs to charges (RCCs) can, at best, give average estimates of service-line profitability, with the potential for categorizing unprofitable service lines as profitable and vice versa. 

Ability to accurately measure clinical variation in the hospital and use the measurements to guide meaningful conversations with your physicians.

A hospital with true cost data can run physician-level data profiles, such as average cost per case for each physician treating a particular disease. Such insight can support meaningful discussions with physician outliers that can influence changes in behavior and thus potentially reduce costs. Hospitals using RCCs cannot approach physicians with the same level of credibility, as seen in the rural hospital example on page 89. If hospitals instead focus on using actual costs in specific strategic costs centers, physicians once considered the hospital’s most cost-efficient may be exposed as the  organization’s most costly. 

Understanding of the impact of macro-purchasing factors such as drug shortages on the profitability of key service lines.  

A hospital that tracks actual costs can take macro-purchasing actors, such as drug shortages, and assign true costs on a daily or monthly basis, thereby allowing the effects of drug shortages on service-line profitability to be quantified. Alternatively, hospitals using RCC-based costing would average out the effects over a year, leading to inaccurate service-line profitability insight during times of drug shortages.


Sidebar 2: Improving Cost Estimates for Drugs: Action Steps by Department

IT Department

  • Create a taxonomy-based categorization tool. Assign each drug description into broad therapeutic class, dosage, and route of administration categories. This can be a string search and categorization tool, using regular expressions, to match a specific set of characters in a string (word).
  • Maintain a central database of drugs and categorizations to be used each month.

Pharmacy Department

  • When documenting purchased drugs, be sure to include compound, dosage, and route of administration information in the entry.
  • Ensure the detailed charge file has charge codes that reflect the individual drugs purchased each month.

Sidebar 3: Improving Cost Estimates for Implants: Action Steps by Department

IT Department

  • Bridge the implant log and the purchasing file. Identify the SKU number for the implant in the purchasing file as well as the implant log. Maintain or create a central database of implants and their SKUs (both the implant-log SKU and the purchasing-file SKU).
  • Connect the detailed charge file with the implant log, using the patient account number.

Purchasing Department

  • Ensure that purchased implants are assigned an internal SKU that can be mapped to the implant log SKU.
  • Ensure that the detailed charge file has charge codes that reflect the individual implants purchased each month. 

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

How Banks Make Money From Home Loans

Join Our Mailing List

Understanding the Fractional Reserve US Banking System

The following infographic explains how banks make money from the deposits of customers. Fractional Reserve Banking is a banking system where banks keep a fraction of deposits from a customer, then use the rest for loans to other customers.

###

banks-money-home-loans

###

Assessment

Wiki: http://en.wikipedia.org/wiki/Fractional-reserve_banking

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

What Happens if the Stock Market Crashes – Doctor?

Join Our Mailing List

There is No Investing Crystal Ball

Lon JeffriesBy Lon Jefferies, MBA CFP CMP™

As the Dow has risen greatly since March 9, 2009, some physicians and investors worry that the market is overheated and due for a severe pullback; as recently experienced very minor events have illustrated.

But, an opposing view is that the current price of the S&P 500 is comparable to its value in 1999, despite the fact that its earnings and dividends have doubled since that time, and suggesting the market has additional room to grow.

The Future is UnKnown

There is no crystal ball. What the stock market will do in the near future is anyone’s guess. As uncertainty is always a factor when investing, developing a portfolio that represents your risk tolerance and investment time horizon is critical.

Many physicians and investors realize they need to scale back the assertiveness of their portfolio as they approach retirement, but why is this important? The mechanics of an investment portfolio are very different for a portfolio in the distribution phase than for a portfolio still accumulating assets. If an investor is taking withdrawals from their account, it is much more difficult to recover from losses because distributions only serve to exacerbate the market decline.

crystalball2

Dr. Israelsen Speaks

As Craig Israelsen PhD points out in the February 2013 issue of Financial Planning Magazine with the following illustration, a portfolio enduring annual 5% withdrawals faces a much steeper climb back to break even after a loss than does an accumulation portfolio:

Clearly, the conclusion is if you are taking distributions from your account, or intend to do so soon, it is vitally important to avoid large losses. As it may be realistic for investors still accumulating assets to recover from a -20% loss by obtaining an average annualized return of 7.7% for three years, it is unlikely that a retiree taking distributions from his account will get the 16.5% annual return required for three years in order to recover from a similar loss.

Diversify

Protect yourself from unsustainable losses by maintaining adequate diversification within your portfolio. Bonds serve as a buffer against volatility and will likely decrease your loss during stock market corrections.

Additionally, ensure your portfolio has sufficient exposure to various asset classes: large cap, mid cap, and small cap stocks; US, international, and emerging market stocks; government, corporate, international, and emerging market bonds. Investing in multiple asset categories will protect your portfolio from a catastrophic loss next time a bubble in a market sector pops.

chart

Assessment

Speak with a Certified Medical Planner™ or fiduciary and physician focused financial advisor to ensure your portfolio is assertive enough to meet your retirement goals while maintaining an acceptable level of risk. If you wait for the market to turn before taking action, it may be too late.

www.CertifiedMedicalPlanner.org

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com
***

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

“The Doctor’s Dilemma”

Join Our Mailing List

On Hospital Monopolistic Powers

By Ann Miller RN MHA

As George Bernard Shaw, whose works include “The Doctor’s Dilemma” might have put it, that any lawmaker would grant hospitals monopolistic powers plus the freedom to price as they see fit is enough to make one despair of political humanity.

C.O.N.

And, here is a post on Certificates of Need, too.

http://www.ncsl.org/issues-research/health/con-certificate-of-need-state-laws.aspx

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct Details