Hear Dr. Marcinko on Audio-Educator [Do you Need Money to Start or Grow Your Medical Practice?]

Join Our Mailing List

Crafting a Business Plan and Starting a Medical Practice [A “Live” Audio-Conference]

Conference Registration: http://www.audioeducator.com/hospitals-and-health-systems/business-plan-for-medical-practice-013012.html

Wednesday, Jan 30th, 2013 at 1 PM, EST for 60 minutes

Order

By Staf Reporters www.CertifiedMedicalPlanner.org

Dr David E Marcinko MBAThe “Business Plan” is a key tool for raising start-up capital for a new medical practice, or financing a medical / surgical service line extension for a mature one. It is also used for acquiring loans to finance growth of an existing practice.
Although long recognized as a quintessential business tool, its’ formal structure and mental rigor are only now being recognized in the medical community as competition increases in the healthcare industrial complex.

Reasons for the Plan

There are many reasons to write a medical practice business plan. The process of gathering, compiling and analyzing information is an invaluable experience to the beginning practitioner, or experienced veteran physician. Our expert Dr. David E. Marcinko MBA CMPwill discuss all these, step by step in this 1-hour enlightening event.

See the steps below:

  • Determine the feasibility of a new practice start-up.
  • Raise money from investment bankers for a new practice.
  • Obtain financing to expand an existing office or turn-around a declining satellite.
  • Develop an operational strategic plan and conduct due diligence.
  • Create a budget, time frame or business direction for a practice.
  • Unmask potential problems, risks or benefits of a medical practice.
  • Focus on market opportunities by determining revenue centers or cost drivers.
  • Persuade third party payers, networks and insurance carriers that your practice has a future and represents a viable synergistic partner for their organization.

Medical Office Business Plan

As an attendee you will get:

  • Power Point slide presentation.
  • Time-line checklist to new medical office launch.
  • Topical comprehensive white paper.
  • Electronic blog forum for further information.

Dr. Marcinko in this 60-minute conference will present to you:

  • Executive Summary: Where you concisely state the purpose of the loan, the exact amount of money required, an explanation of what the loan will be used for and why it’s needed.
  • Pro-forma Cash Budgets and Financial Statements: You’ll learn to how effectively use your data and underlying assumptions to prepare information that your banker can easily read and buy into.
  • Doctor’s Personal Financial Statements: Learn how to use copies of the last 3 years of personal tax returns for the bank as well as identify the collateral being pledged as security for the loan.
  • Representation: Here is where this presentation is invaluable.

Ask a question at the Q&A session following the live event and get advice unique to your situation, directly from our expert speaker.

Who should attend? Medical students, interns, residents and fellows, New, mid-career and mature medical practitioners, Office managers, clinic administrators, healthcare CXOs and physician / nurse executives, All doctors who wish to be employers; not employees.

http://businessofmedicalpractice.com/chapter-3-2/

Why use AudioEducator?

  • Save money on travel. Our conferences are available from the comfort and convenience of your own office or meeting room.
  • Meet your specific training needs. Whether you attend a live event, load up one of our encore broadcasts, or purchase a CD or PDF transcript — you’ll get the information you need on your schedule.
  • Keep learning after the event. Every conference purchase includes the speaker’s materials so you can keep learning long after the conference is over.
  • Save time training your whole staff. Gather around a speaker phone or computer and enlighten your entire team for one low price.
  • Do you work with a virtual team or multiple locations? Ask our customer specialists about discounts for your whole staff.

REGISTER HERE

http://www.audioeducator.com/speakers/index/speaker/600

###

 Product Details

www.BusinessofMedicalPractice.com

Order


Selected NBER Papers of Note for MDs and FAs

Join Our Mailing List

National Bureau of Economic Research

www.NBER.org

The 2012 No. 3 Bulletin includes the articles below:

1)  The Value of Planning Prompts
by Katherine Milkman, John Beshears, James Choi, David Laibson, and Brigitte Madrian
http://www.nber.org/aginghealth/2012no3/w17994.html

2)  The Effect of the Earned Income Tax Credit on Infant Health
by Hilary Hoynes, Douglas Miller, and David Simon
http://www.nber.org/aginghealth/2012no3/w18206.html

3)  Can Health Explain Differences in Employment of Older Men Across Countries?
by Kevin Milligan and David Wise
http://www.nber.org/aginghealth/2012no3/w18229.html

Assessment

Abstracts of Selected Recent NBER Working Papers:
http://www.nber.org/aginghealth/2012no3/WorkingPaperSummaries.html

###

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

An Economic Picture of Domestic Healthcare Spending

Join Our Mailing List

By the Numbers

The healthcare component of the U.S. economy continues to expand, with per-capita spending projected to reach $13,000 by 2020. But, at the same, the industry continues to create jobs: 10 of the fastest-growing occupations are in healthcare-related fields.

Driver of the Economy

As one of the largest segments of the US economy, health care accounts for trillions of dollars in spending, both by governments and private individuals. And so, Top Masters in Healthcare decided to take a closer look at where the money goes in this infographic

###

health

[The Calculus]

Billing Department

So who does the spending?

  • 21% of healthcare spending is done by private businesses
  • 28% of healthcare spending is done by individual households
  • 16% of healthcare spending is done by state and local governments
  • 29% of healthcare spending is done by the Federal government

Where did the spending go?

  • 37% of healthcare spending went towards hospital care
  • 23.6% of healthcare spending went towards physician and clinical services
  • 5.9% of healthcare spending went towards other residential / health / personal care services
  • 4.9% was spent on dental services
  • 3.3% was spent on home health care
  • 3.2% was spent on “other” professional services

Per capita spending

Between 1960 and 2011, per capita health care spending rose by about 5,400 percent from $147 in 1960 to $8,311 in 2011. If other prices rose like that, here’s what it might look like today:

  • Family Dinner: $176.58
  • Tube of Toothpaste: $13.50
  • Volkswagen Beetle: $95,526
  • Gallon of gas: $13.50
  • Average income: $287,010
  • Electric can opener: $479.52

Emergency Department

The top 5 causes of death are heart disease (24.5%) cancer (23.3%) chronic lower respiratory diseases (5.6%) stroke (5.3%) accidents (4.8%) Alzheimer’s disease (3.2%).

Cardiology

  • 470,000 is the number of people who have a second or subsequent heart attack
  • 785,000 is the annual estimate of the number of people who have their first heart attack
  • $444 billion is the cost of heart disease, from health care services to medications to lost job productivity

Oncology

  • One in two men will get cancer during their lifetimes
  • One in three women will get cancer in their lifetimes
  • $226 billion is the annual cost of cancer, including treatment and lost income

Ongoing Care

  • Nearly 1 billion annual physician visits per year. If you had a doctor visit every minute of every day, it would take 1,902 years to have that many trips.
  • One out of 2 adults has a chronic illness
  • Seven out of every ten deaths are a result of a chronic illness

Obesity

  • The heaviest states by obesity rate are Mississippi (34.4%) West Virginia (32.2%) Alabama (32.3%) Tennessee (31.9%) and Louisiana (31.6%)
  • The lightest states by obesity rate are Hawaii (23.1%) Massachusetts (22.3%) Connecticut (21.8%) District of Columbia (21.7%) and Colorado (19.8%)

Diabetes

  • Diabetes can lead to a slew of other serious health problems including neverous system diseases, blindness and eye problems, heart disease and stroke, kidney disease and hypertension.
  • 25.8 million people are current affected by diabetes, 8.3% of the population.
  • 35% of people older than 20 have pre-diabetes
  • $174 billion is the total cost of treating and ealing with diabetes each year

Personnel Department

  • Healthcare provided 14.3 million jobs in 2008. And that number is only going to grow. In fact, health care is expected to be the single fastest-growing sector of the US economy through 2018.
  • Ten of the twenty fastest growing occupations are in healthcare related fields.
  • 4.01 million new jobs are expected to be created in the health care industry by 2018. Compare that to 2.67 million in science/engineering, 1.68 million in education, 1.43 million in administration support and waste management and 1.3 million in construction.
  • Healthcare professionals earned a combined $886 billion in total salaries in 2010

IT Department

  • As our world becomes more connected by technology, doctors and patients are increasingly using the Internet and data storage.
  • 57% of doctor’s offices use electronic medical records.
  • 6 out of 10 adults have looked up health information online.

Pharmacy Department

  • Almost half of Americans take at least one prescription drug.
  • $35.22 is the average price of a brand name drug which is almost 4x as much as the generic price.
  • Spending on prescription drugs has gone from $40.3 billion in 1990 to $259 billion in 2010 and is expected to grow to $457.8 billion by 2019.
  • The cost to bring a new drug to market is between $55 million and $1 billion
  • The cost of patented drugs in the United States is 35-55% higher than other industrialized nations
  • 80% of FDA approved drugs have a generic counterpart
  • Only 23% of doctor visits don’t include a prescription.

Assessment

The impact of the healthcare industry on everyday Americans continues to grow, whether they see it in their insurance bill or whether they earn their salaries from the health care industry. The issue also continues to dominate the political conversation… there’s no escaping it.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

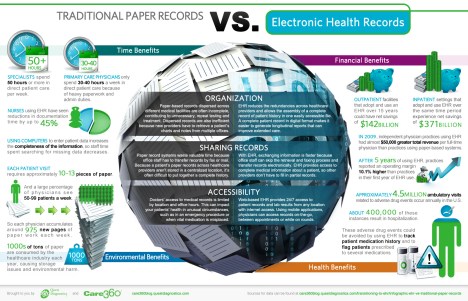
Medical Records [Time Benefits versus Financial Benefits]

Join Our Mailing List

Paper versus eMRs [Organization – InterOperability – Accessibility]

www.BusinessofMedicalPractice.com

MRs

Assessment

Chapter 13: IT, eMRs & GroupWare

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

US Health Spending by Service and Age

Join Our Mailing List

By: Deloitte and h/t Bruce Bartlett

National Health Expenditure Projections, 2012–22: Slow Growth Until Coverage Expands And Economy Improves

Abstract

Health spending growth through 2013 is expected to remain slow because of the sluggish economic recovery, continued increases in cost-sharing requirements for the privately insured, and slow growth for public programs. These factors lead to projected growth rates of near 4 percent through 2013.

However, improving economic conditions, combined with the coverage expansions in the Affordable Care Act and the aging of the population, drive faster projected growth in health spending in 2014 and beyond. Expected growth for 2014 is 6.1 percent, with an average projected growth of 6.2 percent per year thereafter.

Over the 2012–22 period, national health spending is projected to grow at an average annual rate of 5.8 percent. By 2022 health spending financed by federal, state, and local governments is projected to account for 49 percent of national health spending and to reach a total of $2.4 trillion.

Link: http://content.healthaffairs.org/content/early/2013/09/13/hlthaff.2013.0721#aff-

Assessment

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Fixing the Mental Health Infrastructure of the US

Join Our Mailing List

The Political Topic Du Jour

By David K. Luke MIM CMP™ www.NetWorthAdvice.com

David K. LukeThe sad events of the recent tragedy which occurred in at Sandy Hook Elementary School in Connecticut where 20 children and 6 adults were killed painfully reminds us of two problems that are not going away in the United States: continued gun violence and untreated mental illness.

As a Father I could not bear to watch the news coverage. Resolving the problem of high gun violence in this country typically leads to an emotional debate over gun control and gun rights, a debate that in the past has ended with both sides drawing the line and little being accomplished. Politicians that would like to be reelected avoid this emotionally charged hot potato like a leper colony with the hope that the Topic Du Jour will change quickly back to how they can reduce taxes, increase entitlements, or frankly any other issue that will ensure their livelihood for the current elected term. In the meantime, this stalemate is unnecessarily costing the lives of our innocent children and productive citizens that happen to be in the wrong place at the wrong time.

Commonalities

The common thread to almost all of the tragic public gun violence episodes in the past few decades is that the shooter is suffering a serious mental illness. An estimated 26.2 percent of Americans suffer from a diagnosable mental disorder in a given year according to the National Institute of Mental Health (http://www.nimh.nih.gov/health/publications/the-numbers-count-mental-disorders-in-america/index.shtml).

Unique among the developed countries is the position of the United States that those with mental illness, like those with any other disease, can receive treatment as long as they pay for it. Those that can’t or choose not to pay for it often end up in dire straits in one of our emergency rooms (the de facto health care solution in the United States for the uninsured) forcing our overworked and understaffed emergency room health professionals to deal with the problem and our hospital systems with spiraling unpaid ER bills. As a country that was founded on the principles of self-reliance and freedom of choice, we recognize the fact that some individuals may prefer not to pay for their health care by electing to not have private health insurance. Lest we become too judgmental of our fellow citizens that do not have health insurance, we should be reminded that our for-profit health insurance industry in the United States that provides the largest portion of payment for healthcare services also precludes individuals that are unhealthy from purchasing coverage. This is done by hiking premiums to unaffordable levels or simply by flat issuing a denial of coverage. So individuals with mental illness, even those diagnosed with mild depression, are often branded by the system that considers mental health issues as preexisting conditions.

Which brings about the question:  How does an individual with a mental health illness in the US normally get medical treatment?

Link: Chapter 07: Workplace Violence

Standard Protocol

Normally, the individual sees their primary care physician, talks about the problem, is diagnosed by the physician and receives treatment, which often includes prescription medications. The individual’s private health insurance plan (or Medicare or Medicaid, depending on the age or financial qualification of the individual), covers all this with typically a small or no copay at the doctor’s office. If a medication is prescribed, the drug (often a generic) is covered typically by a small copay at the pharmacy. Further checkups and treatment are all typically covered by insurance with little money out-of-pocket.

Here are the complications to the “normal” answer regarding an individual with a mental illness in the United States seeking help:

Reasons Mental Illness Goes Untreated That Involve Lack of Access to Medical Care

  1. The individual does not have insurance.  The cost to treat the problem may be considered unaffordable.
  2. The individual has insurance but the mental illness has been ruled a preexisting condition and is not covered under the policy. The cost to treat the problem may be considered unaffordable.
  3. The individual does not see a health service provider on a regular basis and may not realize that they are sick with a mental illness or consider that it is just stress or a temporary mood change.

Reasons Mental Illness Goes Untreated In Spite of Access to Medical Care

  1. The individual considers seeing a physician for such an issue to be a hassle or too time consuming. Some primary care practices in some parts of the country require a long wait to be scheduled and then a long wait in the waiting room to be seen.
  2. The individual would like to receive treatment for their mental illness, but knows that such treatment will be recorded on their medical records and likewise have repercussions that could include such events as losing their job, tarnishing their reputation in their community, family, church, or other organization, or denying them access to a gun license, pilot’s license, medical licenses, etc. Military service people and police officers, for example can be rightfully disqualified from their positions if certain mental illnesses were revealed on a medical record. Also having a mental illness on their medical record could increase their cost to get life insurance or their ability to get new health insurance should they leave their current employer. Likewise many of these individuals may seek help “off the record” or may avoid seeking help all together and simply “man up” as expected.
  3. The individual, for reasons mentioned above and regardless of medical care access, avoids professional medical care and self-diagnoses their mental illness. Likewise, an individual suffering from severe depression may decide that they have only mild depression and based on “Dr. Google” may start a regimen of Vitamin B, a chromium supplement, and some St. John’s Wort. Self-treatment of mental illness issues with easy access to information and prescription drugs through the internet lulls some individuals into a false sense that they are on the road to recovery when their condition can actually worsen.
  4. The individual may know they need help, may have access to qualified medical help, but may be discouraged from seeking help due to a trusted family member or friend that assures them professional medical help is not necessary. I have even witnessed a loving father tell his diagnosed schizophrenic son who had just experienced a manic episode to “shake it off and be happy”. Can you imagine telling your child who suffers from a serious chronic disease such as heart disease, cancer, or diabetes to just “shake it off and be happy”?
  5. The individual perceives that continued medical treatment of their mental illness could threaten their personal freedoms, by resulting in a court ordered commitment to a psychiatric facility for example. Fearing such restrictions, the individual cuts off all medical treatment. In fact recent news is now coming forth that Adam Lanza, the 20-year-old Sandy Hook shooter, had been taken to a psychiatrist by his mother and was in fear of being committed to a facility, which may have been part of the motive for the mass shooting spree, which included the killing of his mother.

[Re-Thinking our Gun Control Dialog]

Gun control dialog

Will the PP-ACA Fix Our Maligned Mental Health Care System?

Mental health services are a part of the services provided under the Affordable Care Act. The Mental Health Parity and Addiction Equity Act, which was signed into law in 2008, also helped increase coverage that includes mental health services by requiring employers with more than 50 workers to cover them at the same level as other medical conditions offered by the insurance plan.

In other words, the plan could not provide fewer inpatient hospital days or require higher out-of-pocket costs for mental health conditions. It is still possible however for larger employers to not offer mental health coverage in their insurance plans even after 2014. The ACA will require small group and individual plans however to offer the coverage in 2014 through health exchanges created under the law. An individual that earns less than 138 percent of the federal poverty level may be eligible for Medicaid coverage in 2014, which offers mental health benefits.

It is estimated that as many as 30 million people will gain insurance coverage and likewise mental health care beginning in 2014. Some estimates are lower, with the expectation that many will forgo the mandated insurance coverage and pay the “tax” instead. Even with more Americans having access to mental health care, many will opt to forgo such care as outlined above in “Reasons Mental Illness Goes Untreated In Spite Of Access To Medical Care”.

For those folks we can fault the independent American spirit, good old fashioned stubbornness, the desire to avoid any stigma attached to mental illness, or simply the desire to be unencumbered by a system that threatens to “lock you up and put you away” for your disease. As with the case of Adam Lanza, access to mental health care does not mean the disease is cured or that the patient is an obedient, willing participant.

Assessment

Sadly, preventing another Sandy Hook from occurring is impossible. Whether or not the gun debate this time around will produce any results remains to be seen. Where is the limit of personal freedoms? However, with increased mental health access beginning in 2014 and with increased mental health awareness and acceptance we can hope that such events in the future will be less common.

About the Author:

David K. K. Luke focuses on helping physicians and successful retirees with financial planning, investment and risk management. In the past 24 years of industry experience, David has held licenses including general securities registered representative, registered investment advisor, Branch management supervision, and Life, Accident, and Health Producers.  David, a fee-only advisor, is able to help his clients to achieve peace of mind and greater assurance with their financial goals by giving advice and providing investment management that is in their best interest, untainted by commissions or sales objectives. Likewise, in a true fiduciary capacity, he is able to help investors determine the reliability and suitability of products and services that they have been sold by other advisors. David began his career managing money in 1986 in the General Motors of Canada Banking and Investments department where he was engaged in cash management, foreign currency hedging, and the debt issuance of a $100 million Eurobond and a $300 million Note Issuance facility. In 1988 as Supervisor of Borrowings for GMAC Canada David was responsible for the daily average issuance of $125 million in short-term Commercial Paper. David worked as a stock broker and portfolio manager for 2 major national brokerage firms (A.G. Edwards and Wachovia Securities) from 1989 to 2008. Additionally, at Wachovia Securities David was among an elite group of financial advisors approved as a PIM (Private Investment Management) Portfolio Manager. Prior to joining Net Worth Advisory Group in 2010, David managed his own independent firm, Luke Wealth Strategies, working as a registered representative and investment advisor.

He is also a Certified Medical Planner™ charterholder: www.CertifiedMedicalPlanner.org

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
BLOG: www.MedicalExecutivePost.com

Buy from Amazon

Learn How to Profit and Thrive in the PP-ACA Era

BOOK FOREWORD / TESTIMONIAL

The Monetary Value of Human Life

Join Our Mailing List
How Much are We Worth?
By Matthew Pelletier
[Director of Public Relations]
Compliance and Safety LLC

###

Monetary-Value-of-a-Human-Life
 Assessment

• Japan places the highest value on a human life, spending $11,728,000 to save a single life through improvements in public safety.
• South Korea spent the least, at a measly $878,000.00 per life saved.
• Health insurance companies value life at $50,000 per year of quality life, a depressingly low number compared to what government entities will pay. Keep your workforce healthy with proper Health & Wellness training.
• The families of suicide bombers receive just $25,000 per suicide.
• While the families that lossed a loved one on 9/11 received an average of $2.1 million per death, families of fallen soldiers receive a maximum of just $400,000. Rush Limbaugh did an interesting piece about this huge disparity back in 2002.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

  Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™ Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Invite Dr. Marcinko

A Mobile Health Enterprise [Audio] Conversation with Shahid N. Shah

Join Our Mailing List

“Just because we have apps for smartphones doesn’t mean we have real mobility in healthcare

By Ann Miller RN MHA

Product Details

www.BusinessofMedicalPractice.com

App47 CEO and co-founder Chris Schroeder hosts a great podcast series called “What’s Happening!” in which he covers topics around enterprise-grade Mobile Application Management for securely deploying, managing, and analyzing business-critical mobile apps.

The Expert

Recently, Chris interviewed Shahid N. Shah MS, a ME-P “thought-leader” and The Healthcare IT Guy, for an episode in which they spoke at length about the management of enterprise healthcare apps, what mobility means in healthcare, and why technically-savvy clinicians are the only real salvation for the healthcare IT industry.

The Conversation

The audio version of the podcast is available on theApp47 site

More from the Expert

http://businessofmedicalpractice.com/chapter-13-2/

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

LEXICONS: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
BLOG: www.MedicalExecutivePost.com

creativity

Doctors and Speeding Tickets [Myth versus Reality]

Join Our Mailing List
Maximum Speed by State

By Matthew Pelletier [safety consultant]

By Dr. David Edward Marcinko MBA

Dr. Marcinko 1972 VetteThe need for speed across the United States means 100,000 drivers will have a police officer write them a ticket for speeding every day. That works out to 36,500,000 speeding tickets to Americans yearly.

Now, with the average cost per ticket at $150.00, it’s easy to understand the revenue that can come from catching those who disobey the maximum speed limits on the road. 95% of drivers never even contest their speeding tickets, they just pay it and continue on down the road.

Many drivers ignore the fact that speeding tickets raise car insurance rates and drop fuel economy.

The Big Ticket Pay-Off

Because there are so many drivers who break the speed laws, states are required to employee officers who are paid higher salaries than school teachers because each officer writes an average of $200,000 dollars worth of tickets annually. It is safe to say the tickets pay for their salaries.

The Graphic

The infographic below backs up the above information and shows us how the maximum speed limits in states across America differ.

###

 max-speed-limit-by-us-state

Review

  • 1 state, Utah, has a maximum speed limit of 80 mph.
  • 1 state, Texas, has a limit of 85mph which is 25mph faster speed allowed than Hawaii.
  • 19 states have a limit of 70mph, this is the highest majority for a speed limit.
  • 14 states have a 75mph speed limit.

Safety Training

Many states have dot safety training and by requiring driving safety training the importance of obeying speed limit laws and hopefully reducing the number of speeding tickets written can begin to take place. Gradually over time Americans have seen speed limits increase, this is due also to safer cars being manufactured.

Assessment

Doctors and medical colleagues; How do you feel about being the number one target of the traffic cops?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

On Googling Myself [Oh My]

Join Our Mailing List

A Solitary Pursuit?

By Dr. David Edward Marcinko MBA CMP™ www.CertifiedMedicalPlanner.org

Dr. MarcinkoI am a doctor, financial advisor, editor, publisher, health economist, teacher, runner and a few other things, as well. A real diletant!

But, there is something else I must admit to you. It is sinister. Something I often do at night, in the dark, when no one else is around. Not even my wife.

What is It? …. Why Googling my self, of course! Also known as “ego surfing.”

Ego Surfing

Have you ever Googled yourself or your financial advisory, management or medical practice? Did you know that you have an ever growing online reputation? Whether you know it or not, Financial Advisors and Doctors have an online presence. When you type your name in a search engine you may be surprised by what you find.

Digital Footprints

Everything you do professionally, or socially, creates a digital footprint. If you are involved in social media then you are contributing to your online reputation. If not, your online reputation is being written for you. There is a conversation taking place about you online, but unfortunately you may not be included in it.

google-chrome-logo

So Much Information

A simple Google search of your name will likely show your practice website. Your name will also appear in numerous third party review sites. Take the time to read a few. You may be surprised. You will find your name and your practice appearing on people’s Facebook and Twitter pages too.

And, you may see comments from clients and patients [both satisfied, and not so much], too. So, keep abreast of your digital bona fides. Google yourself regularily …. Just, dont go blind.

Assessment

While at first this may be disturbing, I view it as an opportunity to get the [positive] word out. How about you? Sinister, or no?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

Protecting Patient Privacy

Join Our Mailing List

How Important Is It – Really?

By Dr. David Edward Marcinko MBA

DEM blue

By Matthew Pelletier [safety consultant]

The U.S. Health Insurance Portability and Accountability Act (HIPAA) is the federal law protecting the privacy and security of patients’ health information and was enacted in 1996.

HIPAA laws also protect electronically communicated information. Understanding the significance and importance of HIPAA laws is vital to all medical and health organizations. Companies are required to follow HIPAA laws and protect patient privacy.

Share and Share Alike – NOT!

The privacy rule is an important aspect of HIPAA and makes it illegal for patient’s private health information to be shared by health professionals unless the patient consents. This encompasses patient information which is written, verbal or electronically communicated. Many health care and medical organizations use healthcare training videos in order to educate their workforce on the importance of patient privacy laws.

###

privacy

Review

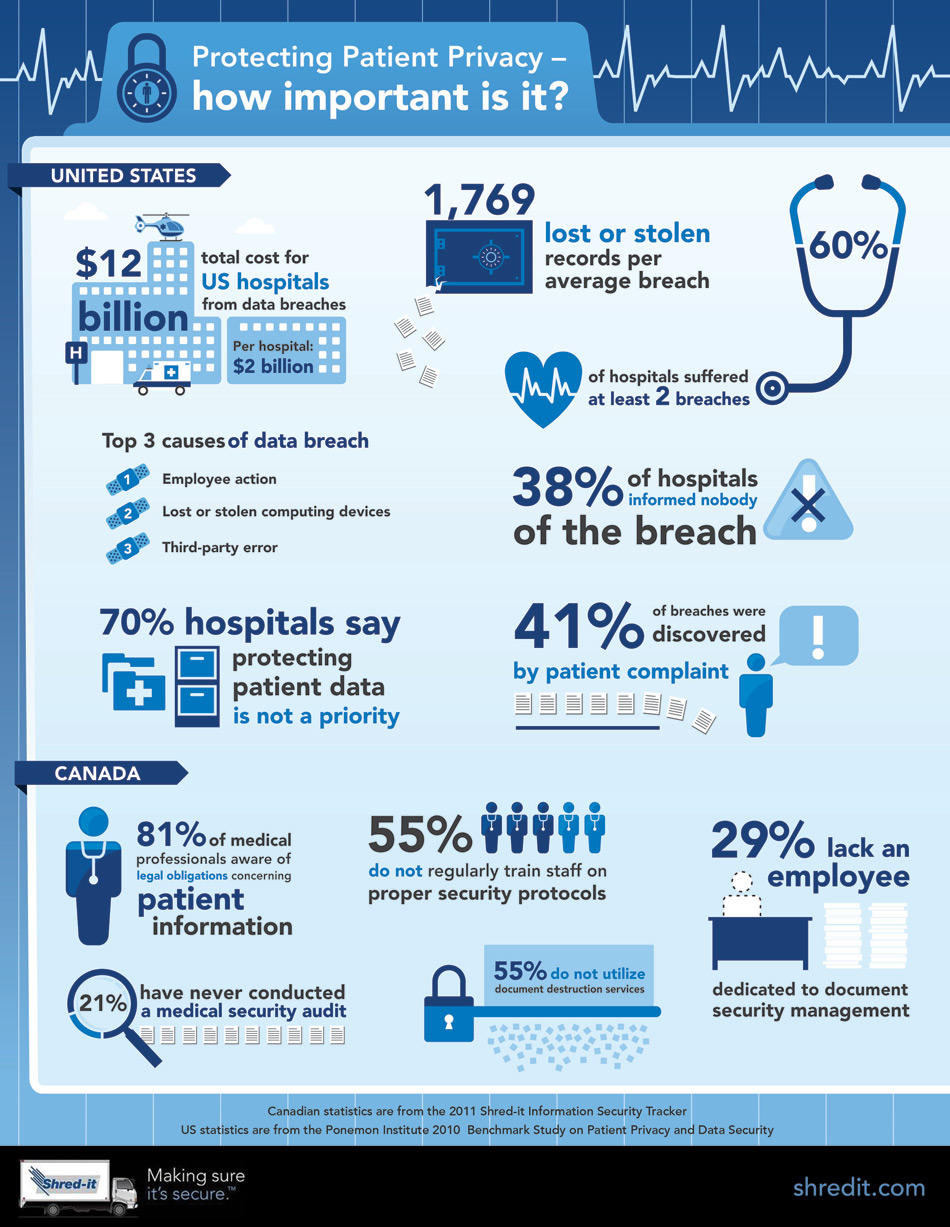
As the infographic above illustrates, patient privacy is very important and the cost in breach of privacy can be costly:

• With 60% of hospitals having a minimum of 2 breaches in privacy the cost per hospital is estimated at $2 billion dollars.
• The average number of records which are lost or stolen in each violation of privacy is 1,769.
• The main causes of electronic patient information breaches is due to employees, portable electronic devices and third-party errors.
• 7 out of 10 hospitals don’t view patient privacy as a priority though it costs them money if breached.

With 38% of hospitals choosing not to inform anyone of patient privacy breaches while over 40% of breaches are only reported by the patients themselves, HIPAA violations can result in being very costly to medical and healthcare organizations, not just hospitals. HIPAA training videos are a solution to help the workforce understand the importance of patient privacy laws.

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. And, are these issues a moral equivalency? Does privacy even exist anymore in an era of social media, the Internet, Google Earth and Google Maps, etc.

Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

About Average Hospital Stay Costs

Join Our Mailing List

About $33,079 … plus gratuity?

The cost of the average American hospital stay nearly doubled from 2000 to 2010 while average stay length declined. The decade was a period of low inflation, but some sectors of the economy didn’t get the memo. Charges for a hospitalization soared from an average $17,390 in 2000 to $33,079 in 2010.

Link: http://www.BusinessofMedicalPractice.com

The USA

In the U.S. we spend almost three times as much on a hospital stay as other industrialized countries, even though their average stay tends to be longer.

###

Hospital costs

Source: www.FaceThe factsUSA.org

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Our Newest Textbook Release

Buy from Amazon

Learn How to Profit and Thrive in the PP-ACA Era

BOOK FOREWORD / TESTIMONIAL

Explaining the New Taxpayer Relief Act

Join Our Mailing List

aka … The Fiscal Cliff Deal Wake-Up Call

By Lon Jefferies MBA CFP®

www.NetWorthAdvice.com

Lon JeffriesBelow is a brief summary of the major implications of the Taxpayer Relief Act that was passed by congress. The changes under the act are permanent and do not expire like the previous round of Bush tax cuts. Note, however, that laws can always be changed.

The Tax Increase That Will Impact Us All

As of December 31, 2012, the Payroll Tax Cut expired. The cut reduced the FICA tax rate by 2% in 2011 and 2012. Consequently, this Social Security tax rate will return to 6.2% for employees (as opposed to the 4.2% rate during the last two years). This tax will apply to any income below the Social Security Wage Base of $113,700.

Essentially, this change will cause an average taxpayer earning $50k per year to pay $1,000 more in federal taxes.

Income Tax Brackets

The top tax bracket will increase from 35% to 39.6% and will apply to individuals with taxable income in excess of $400k and married couples with incomes over $450k. No other changes were made to the federal income tax.

Income Tax Brackets

Taxpayers in the 10% or 15% or income tax bracket will continue paying 0% tax on long-term capital gains and dividends. A 15% capital gains and dividend tax will continue to apply to all other taxpayers not in the highest tax bracket (again, individuals with incomes above $400k and married couples with incomes above $450k). For taxpayers in the top tax bracket, the capital gains and dividend tax effectually rises to 23.8% – consisting of 20% for capital gains or dividends plus an additional 3.8% Medicare tax to boot.

Phaseout of Deductions and Exemptions

Total itemized deductions are reduced by 3% of any excess income over an established limit. That limit is adjusted gross income (AGI) of $250k for individuals and $300k for married couples. Personal exemptions are also phased out once AGI is above the same limits. The exemptions are reduced by 2% for each $2,500 of excess income over these limits.

Professional Wake Up Call

Estate Taxes

While the top estate tax rate has been increased from 35% to 40%, individuals will continue to pay no taxes on estates less than $5,120,000. This figure will continue to rise with inflation. Note: couples essentially get two of these exemptions, allowing them to pass $10,240,000 to heirs without paying estate taxes.

Alternative Minimum Tax

The new AMT exemption amount will be $50,600 for individuals and $78,750 for married couples. These figures will be adjusted annually for inflation. Speak to an account to determine how this impacts your tax return.

Bonus – Potential 401k to Roth 401k Conversions

If your employer offers Roth 401k accounts, you can now convert your traditional 401k investments to the Roth plan while still employed. This process will be similar to converting a traditional IRA to a Roth IRA and taxes will be due upon conversion. However, your employer isn’t required to offer a Roth 401k, so speak to your employer’s HR department to determine if this is an option. Further, speak with your financial planner for information on whether this is a strategy you should explore.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product Details

The Doctors and Guns Controversy

Join Our Mailing List

Let the Editorialists Opine

Dr. David Edward Marcinko FACFAS MBA CMP

[Publisher and Editor]: http://www.jbpub.com/catalog/9780763733421

Dr David E Marcinko MBAIn late December, three of the nation’s most respected medical journals  published accounts of the gun lobby’s efforts to squelch federally  funded research on gun-related injuries, and to silence physicians who  would talk to their patients about gun ownership or use.

Writing in the  Journal of the American Medical Assn., the Archives of Internal Medicine and the Archives of Pediatric and Adolescent Medicine,  editorialists suggested it is time for researchers and physicians to  link arms and in the interest of the nation and their patients, let  knowledge about guns lead the way.

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Here are my own: Letter from the Editor on Sandy Hook Elementary School Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details

Product Details 

How Physicians Use Digital Media for Interaction

Join Our Mailing List

A Break-Down by Medical Specialty

www.BusinessofMedicalPractice.com

Taking-the-Pulse-US-2012

Assessment

Chapter 13: IT, eMRs & GroupWare

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details

What’s Next for Healthcare Information Technology Innovation?

Join Our Mailing List

A Video Panel Discussion

By Shahid N. Shah MS

Dr. David Edward Marcinko MBA

http://www.healthcareguy.com/

Shahid N. Shah MSIn Nashville a few weeks ago, at the Vanderbilt Healthcare Conference, I gave a short talk on a panel focused on the question “What’s next for healthcare information technology innovation?”

The Key Questions

The talk focused on answering a couple of key questions:

  • What does innovation in healthcare mean?
  • Where are the major areas in healthcare where innovation is required?

The Take-Aways

And it had a few key takeaways:

  • Understand health tech buyer fallacies
  • Understand PBU: Payer vs. Benefiter vs. User
  • Understand why healthcare businesses buy stuff so you can build the right thing

Assessment

My speaker deck is found below (if you’re reading this through a feed reader you should click into the blog so that it is visible). You can download the PDF here. After you’ve flipped through it, let me know what you think by dropping some comments below.

Editor’s Note: Mr. Shah is a ME-P thought-leader and an internationally recognized enterprise software analyst that specializes in healthcare IT with an emphasis on e-health, EHR/EMR, Meaningful Use, data integration, medical device connectivity, health informatics, and legacy modernization. He contributed CH 13 to: www.BusinessofMedicalPractice.com and Chapter 13: IT, eMRs & GroupWare

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

Doctors Uniquely Giving Locally in 2013

Join Our Mailing List

On Innovative Charitable Giving

By Rick Kahler MS CFP® ChFC CCIM www.KahlerFinancial.com

Rick Kahler CFP“Shop locally.” “Eat locally.” Do a quick Internet search for either of these terms and you get a host of results. Plenty of people are interested in saving energy and supporting locally-owned businesses by doing their buying close to home.

So, many doctors – like other folks – are committed to eating locally grown food that there’s even a name for them: locavores. Being a locavore in South Dakota in the wintertime, by the way, can be a challenge.

If buying locally matters to you, here’s another aspect of it to think about: giving locally as we begin the new year 2013.

The Holiday Season

This time of year especially, we are flooded with requests from worthwhile causes. Many of these are well-known national or international organizations with sophisticated fund-raising efforts. Amid their appeals, requests from local charities may be easy to overlook. Yet many small organizations do a great deal of good in their home towns.

Issues to Consider

Before you decide whether giving locally or nationally is a better option for your gift budget, here are a few things to consider:

1. No matter whether an organization is local or international, always check to see how much of the money it raises goes to administrative costs and how much actually reaches the people the charity serves. Most charities have websites where this information is readily available.

2. What kind of giving matters most to you? If you want to support the arts, chances are that a local organization like your community theatre or concert association will make good use of your funds. If you’d rather support agencies that help with natural disasters, an international organization is probably the most effective place for your money.

3. Do you want to give actual items rather than money? If so, local charities would usually be better choices. Many places, for example, use “Angel Trees” to ask for gifts for children or the elderly. If you’d prefer to help the hungry with canned goods rather than cash, you’ll want to give to your local food bank or homeless shelter.

4. Find out whether you can specify that your gift is used locally. Many national organizations like the Red Cross, Salvation Army, or food banks are happy to receive gifts that are designated for your local chapter.

5. Just as local government is closer to the people it serves, local charities may be more in touch with specific community needs. If you give locally, you can talk to people in charge and find out exactly where your money goes.

6. Giving locally allows you to combine financial giving with hands-on service that may be more satisfying than just giving money. You could help serve meals at a shelter, pack gift boxes, volunteer at a food bank, or distribute gifts.

7. Just because a charity is local, however, don’t automatically assume it uses its money wisely or efficiently. Always check. Sometimes a small organization may be trying to duplicate what an older or larger organization can do more efficiently. Sometimes local organizations are run by people who are well-meaning but don’t necessarily have the skills or contacts to make the best use of the donations they receive.

8. Remember that giving is an individual decision. Choose the level and type of giving that fits best for you, instead of trying to match what others do or give what someone else thinks you should.

charity

Assessment

Finally, keep a balanced perspective. There are many worthwhile organizations, and you can’t possibly give to them all. Don’t waste energy feeling guilty about the ones you skip. Instead, appreciate the giving you do in your own way and let it add joy and satisfaction to your holiday season.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details


US Income Distribution [Doctors versus Laymen]

Join Our Mailing List

Fortunate Medical Professionals

www.CertifiedMedicalPlanner.org

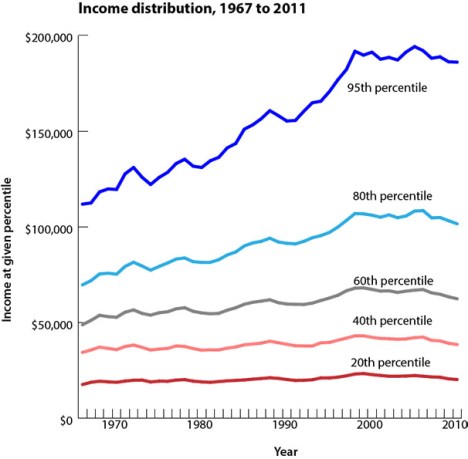
The income gap between the 95th percentile and 80th percentile grew by $1,424 from 2010 to 2011. Indeed, income distribution appears to be widening, and fast, according to the graphic below.

income distribution

Inequality Grows

Okay, we don’t have inequality figures for 2012 yet. But, we do have income data for 2011, and it suggests that the post-war trend of widening income gaps show little sign of abating.

Assessment

And so, the gap between the top 5 percent and the rest of the country just kept growing. But, what about doctors and related medical professionals?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

Building Up to the Fiscal Cliff

Join Our Mailing List

A Historic Review

Fiscal Cliff

Assessment

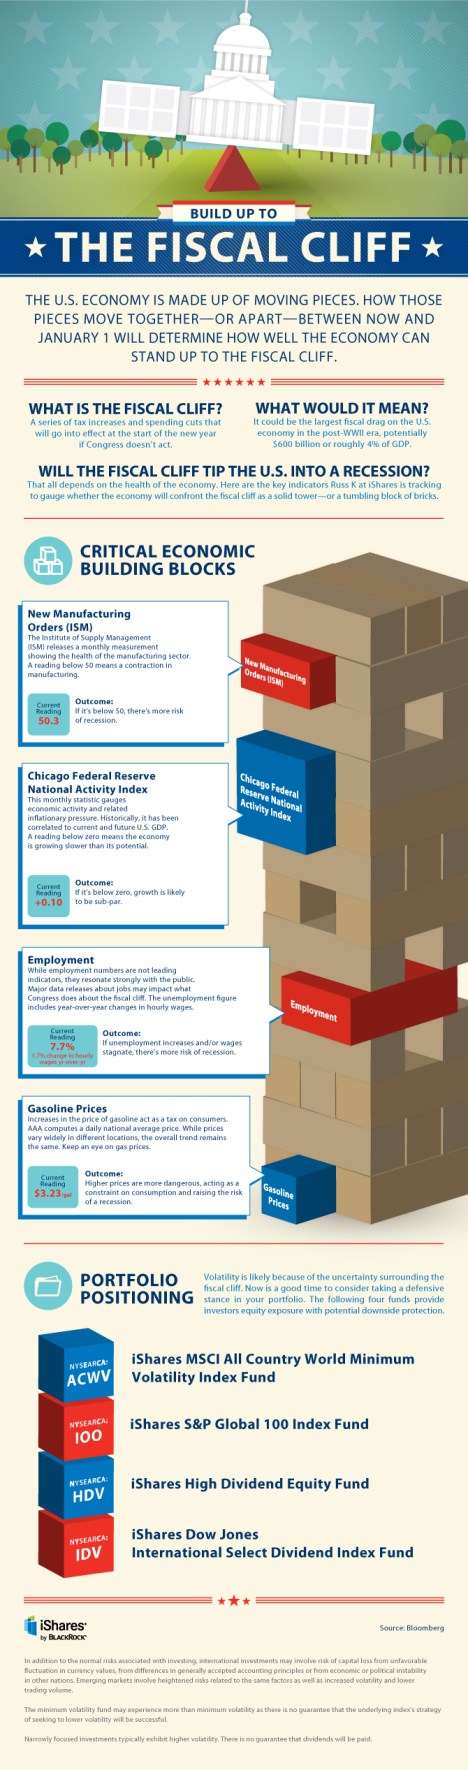
Doctors, FAs and all ME-P readers. What is your strategy for the fiscal cliff situation?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Fighting Mid-Level Medical Providers

Join Our Mailing List

Scope of practice’ stories vary according to state laws

One of the interesting stories to watch in the coming months in the states is the fight over “scope of practice.” That means: who gets to do what, and under whose supervision. It basically pits doctors against other health care providers — nurses, nurse practitioners, physician assistants, etc. They are sometimes called “extenders” or “non-physician providers.” (There are also big fights within dentistry.)

Dental Therapists [Emerging New Providers?]

The PP-ACA

These fights would heat up even without the Affordable Care Act — you’ve heard about the shortage of primary care physicians and you know there is an aging population that is going to need access to primary care. Throw in the health care law — millions of newly insured people entering the system — as well as delivery system reforms and care innovations that encourage more primary care, care coordination and team-based medicine that invites a larger role from those “extenders.”

Role of Retail Medical Clinics

Association of Health Care Journalists

Joanne Kenen, AHCJ’s health reform topic leader, writes about the questions and issues to be addressed and offers some resources to help reporters follow the story in their own communities. In a blog post tomorrow, she will point to two articles that have been done about the role nurses, physician assistants or other providers can have in providing primary care in underserved areas.

Next Generation Physician Recruitment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details

How Bad Is Our National Debt Problem, Anyway?

Join Our Mailing List

And … Will a Deal Fix It?

By Theodoric Meyer
ProPublica, Dec. 28, 2012, 12:34 p.m.

President Obama will meet with congressional leaders today [1] in another attempt to avert the fiscal cliff — the automatic tax increases and spending cuts set to take effect Jan. 1st unless Congress can strike a deal. The cuts and tax hikes, which total more than $500 billion, are so large and so sudden that many economists fear they would plunge the country back into recession.

As Washington tries to hash out a deal, we’ve taken a step back to break down the numbers behind our deficit — how it grew so big, why it is actually shrinking and whether a deal can bring it under control.

How much are we in debt?

The federal debt is just shy of $16.4 trillion [2] at the moment, which also happens to be the debt limit that Congress set in 2011. Treasury Secretary Timothy F. Geithner announced on Wednesday [3] that the nation would hit the limit on Dec. 31. The Treasury can take some “extraordinary measures” to keep paying its bills for a few weeks, but it’ll run out of cash by February or March unless Congress raises the limit again.

And that’s different from the deficit, right?

Yes. The debt is the total amount of the government’s outstanding obligations. The deficit is how much the government is in the red in a given year. In the 2012 fiscal year, which ended Sept. 30, the deficit amounted to $1.1 trillion [4].

That seems like a huge number. How did the deficit get so big?

The 2012 deficit was actually the smallest one since 2008. But it’s still a giant shortfall.

As Binyamin Appelbaum noted in The New York Times [5], the federal government has run a deficit in 45 of the last 50 years. (The exceptions were 1969 and 1998 through 2001.) The financial crisis in 2008, however, caused the deficit to skyrocket, as tax revenues fell because of the slump in incomes and production, and government spending on the stimulus and safety net measures such as unemployment insurance shot up. The deficit for the 2008 fiscal year was $455 billion. In 2009, it surged to more than $1.4 trillion.

Since then, the deficit has been falling, albeit very slowly. The government took in 6.4 percent more in taxes in 2012 than in 2011, as the economy improved a bit and several tax breaks expired. And it spent less on Medicaid, unemployment insurance and the continuing operations in Iraq and Afghanistan.

What about the total debt? How much of that is President Obama’s fault?

The debt has grown by nearly $6 trillion since Obama took office, from $10.5 trillion to $16.4 trillion.

Figuring out how much of that is due to Obama is tougher. The Washington Post’s Ezra Klein, working with the Center on Budget and Policy Priorities, calculated in January [6] that the legislation Obama had actually signed — as opposed to factors like the economy — had added about $983 billion to the debt.

Klein has also rounded up several charts [7] that break down exactly what’s caused our debt to grow so large. The biggest single factor has been the weak economy; President George W. Bush’s tax cuts and the wars in Iraq and Afghanistan also fueled the debt buildup, as did President Obama’s stimulus.

Have debt levels ever been this high before?

Yes, proportionally. Economists like talk about a country’s debt in relation to its gross domestic product (a measure of the economy’s total annual output). And instead of using a country’s total outstanding debt to calculate this debt-to-GDP ratio, economists typically use the amount of debt held by the public. (Somewhat confusingly, the federal government holds about $5 trillion in obligations to itself, most of which is money owed to the funds that support Social Security and other programs.)

Using this measurement, our debt was about 67.7 percent of GDP last year. As this chart compiled by Quartz’s Ritchie King shows [8], that’s the highest our debt-to-GDP ratio has been since the 1940s, when the need to finance World War II caused the debt to surge to 112.7 percent of GDP. But the economy grew fast enough after the war that the debt soon became a much smaller percentage of the country’s GDP.

It’s worth noting that a number of other developed countries have higher debt-to-GDP ratios [9] than the U.S. Germany’s public debt is 80.6 percent of GDP, and Canada’s is 87.4 percent. The euro zone’s most troubled countries fare even worse: Italy’s debt is 120.1 percent of GDP; Greece’s is 165.3 percent.

US Capitol

At least we’re not Greece. How much longer can we keep borrowing?

That’s a tough one. Some commentators — including Paul Krugman, the Nobel-winning economist and columnist for The New York Times — have argued that our current deficits are mostly a product of the sluggish economy. The deficit, Krugman wrote last week [10], “is a side-effect of an economic depression, and the first order of business should be to end that depression — which means, among other things, leaving the deficit alone for now.”

Other economists — including Carmen Reinhart and Kenneth Rogoff, who studied eight centuries’ worth of financial crises for their book “This Time Is Different” — argue that countries with debt-to-GDP ratios above a certain level tend to experience slower economic growth. Reinhart and Rogoff suggest the level is around 90 percent of GDP [11] — which the U.S. is rapidly approaching. A recent Congressional Research Service report [12] concluded that while the debt-to-GDP ratio can’t keep rising forever, “it can rise for a time.” The report continued:

It is hard to predict at what point bond holders would deem it to be unsustainable. A few other advanced economies have debt-to-GDP ratios higher than that of the United States. Some of those countries in Europe have recently seen their financing costs rise to the point that they are unable to finance their deficits solely through private markets. But Japan has the highest debt-to-GDP ratio of any advanced economy, and it has continued to be able to finance its debt at extremely low costs.

How does all this fit into the fiscal cliff?  Would a deal to avert it fix our debt problem?

Actually, going over the fiscal cliff would almost singlehandedly erase the deficit. Tax rates would shoot up, and the fiscal cliff’s indiscriminate budget cuts would slash military and safety-net spending alike.

The problem is that all those tax increases and spending cuts would likely throw the economy back into a recession, causing the deficit to balloon again. “The economy will, I think, go off a cliff,” said Ben Bernanke [13], the Federal Reserve chairman.

(For more detail, see The Washington Post’s exhaustive fiscal cliff explainer [14].)

What the two sides are trying to do is identify cuts that are ultimately deep enough to bring down the deficit — and thus, eventually, the debt — without stalling the economy. But negotiations collapsed last week [15] after John Boehner, the Republican House speaker, tried and failed to pass a “Plan B” alternative to the president’s proposal in the House. Obama is set to meet with congressional leaders today to try to strike a deal to block at least some of the cliff’s impact by Monday night. But its prospects seem dim.

“I have to be very honest,” Sen. Harry Reid, the majority leader, said on Thursday. “I don’t know timewise how it can happen now.”

Assessment

Of course, some analysts have pointed out that people on both the Republican and the Democratic sides may actually want to move the cliff just slightly down the road into the next Congress, which convenes Thursday, Jan. 3. The advantages: Boehner can be safely re-elected as Speaker before he has to do serious twisting of arms of fellow GOP House members to get their votes for any compromise plan. And there will be a few more Democrats in the House and the Senate for the White House to rely on in enlisting the votes it needs to ratify any such deal. The disadvantage: Delay makes the risk of miscalculation greater for either or both sides — and for the public.

Link: http://www.propublica.org/article/how-bad-is-our-debt-problem-anyway-and-will-a-deal-fix-it

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors


Product Details  Product Details

Product Details


A Guide to Patient Loyalty

Join Our Mailing List

A Multi-Factorial Visual Approach

Link: Chapter 15: I-Doctors I-Patients

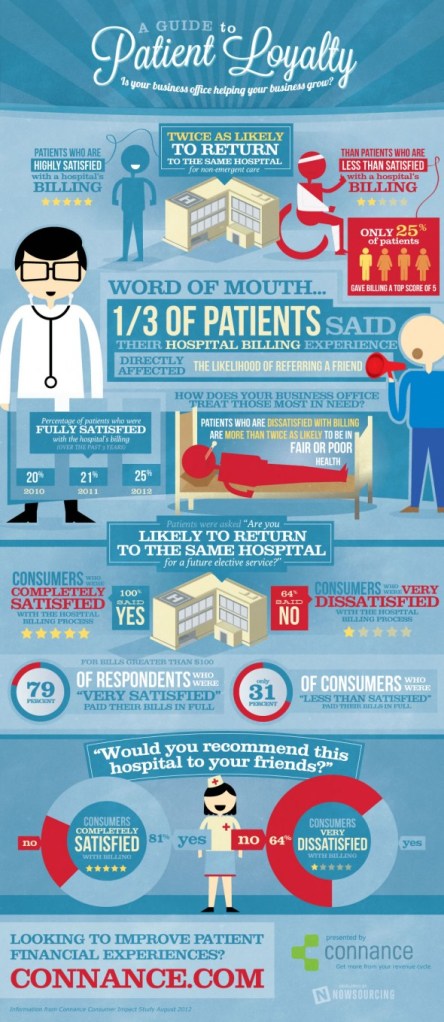
Many factors are involved when a patient has a good experience at a hospital, clinic or medical practice. One huge component in patient loyalty and satisfaction is the billing process.

This infographic colorfully shows what factors to consider in gaining and keeping loyal patients.

###

patient loyalty

Source:  www.connance.com and www.BusinessofMedicalPractice.com

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details

The Perils of Distracted Driving

Join Our Mailing List

Risks Varied and Increasing this Holiday Season

By Dr. David Edward Marcinko MBA

[ME-P Editor-in-Chief]

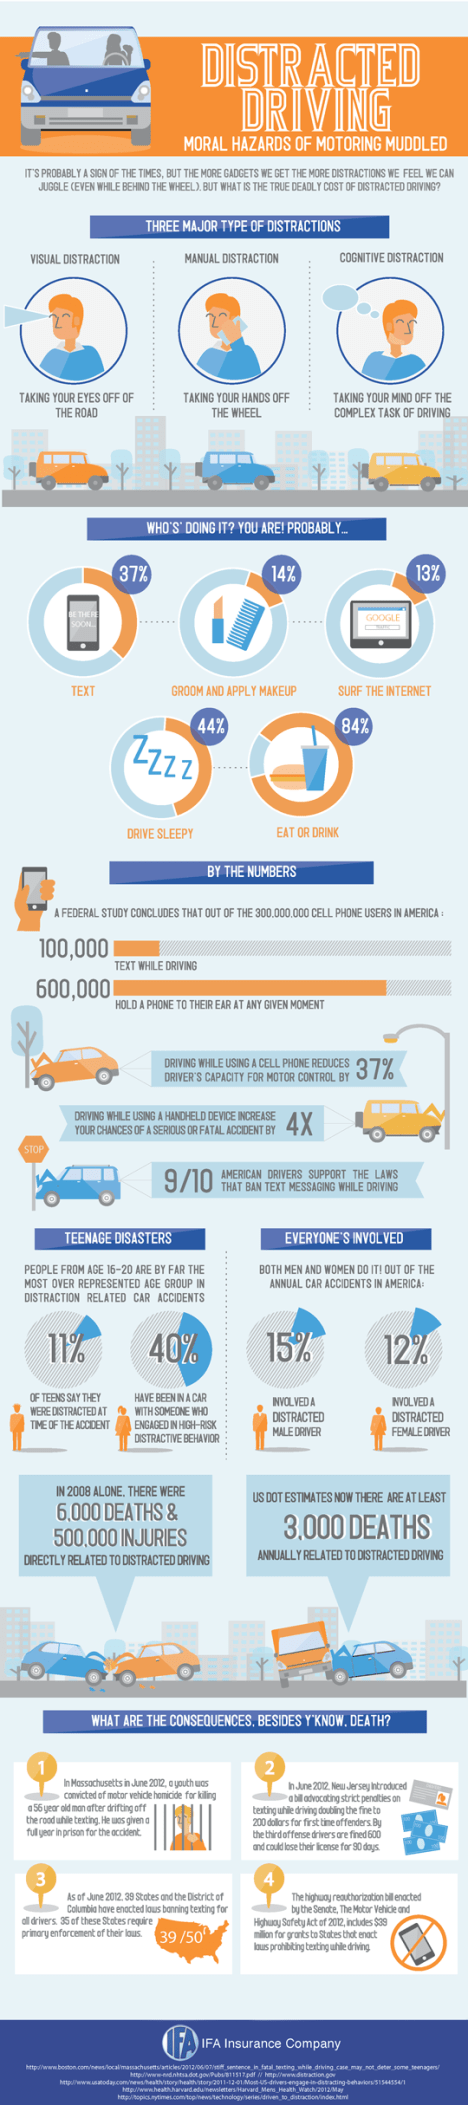
Editor-in-ChiefOur daily lives have become easier over the years. Just take a look at the gadgets we own and the amount of corners we cut.

One of the major problems of this new daily ease is high distractions. These distractions can be deadly when it comes to driving, in which case, there should not be any corners to cut.

So, here is a visual guide to the true cost of driving while distracted. It may be especially important during this holiday season.

###

Distracted-Driving

Assessment

Are doctors especially culpable with their tablet computers, smart phones, eHRs, PCs and CPOESs, etc?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details

Spending for Private Health Insurance in the United States

Join Our Mailing List

Health Costs Doubled in the Past Decade

By NIHCM Foundation www.NIHCM.org

The total cost of health care for a typical family with employer-sponsored coverage has more than doubled in the past decade to nearly $21,000 per year, outpacing both inflation and income growth.

Skyrocketing health care costs are already straining budgets and could jeopardize the availability of affordable coverage under the ACA. To shed light on the factors behind increased spending on private insurance, this brief examines

  • trends in premiums and cost-sharing in the group and non-group markets,
  • how premium dollars are spent by insurers,
  • which sectors are driving premiums upward, and
  • the importance of price increases in explaining spending growth.

healthcare costs

Assessment

Read more…

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

Merry Christmas 2012

All ME-P Readers and Subscribers

HAPPY HOLIDAYS

Holiday Greetings

###

 In warm appreciation of our association during the  past year, we extend our very best for a happy holiday season.

Best wishes for a happy New Year in 2013 filled with health, happiness, and spectacular success.

JOIN US IN 2013

Join Our Mailing List

The Medical App Debacle

Join Our Mailing List

Regulating the App Store

[By Adam Ghosh]

Back when Apple first released the idea of the app store to the public, they probably had no idea how proliferate it would be and how it would weave itself into countless workplaces and individuals’ hands.  A quick look on the store today will return you with some 700,000 apps of which 13,000 are health-related.  With so many apps being released on a weekly basis, the credibility as well as the usefulness of some of these applications began to be called into question (a good example of which is an “x-ray” app which just shows pre-rendered images and responds to movements made by the smartphone).

Enter the FDA

To combat this, the FDA has been working on a set of rules and guidelines that will better weed out the less than ideal applications that could potentially lead to misdiagnosis, as well as a host of other problems associated with individuals receiving information that has not been upheld by a healthcare professional or a credible source.

The problem with these apps comes down to one of categorization.  The FDA has the ability to regulate apps that enter the app store that have tags as “medical software,” but not those that have been submitted under the category of “wellness.”  As you can imagine, apps that have not had their credibility upheld generally don’t get submitted under the first category, but rather the second.  The real problem with this happens when a “wellness” app suggest or recommends healthcare advice that has not been backed up an industry professional and consequently may lead to some serious health problems.

Example:

Let’s take a closer look at a good example of this in action.  A ways back, a large number of software companies were capitalizing on the idea of the pedometer and the ability to track one’s footsteps throughout the day.  It was only a matter of time before the app store saw its versions enter the hands of iPhone users across the globe. The issue?  Some of these apps were just fine, giving users the ability to track their steps and better calculate the amount of calories burned over a given period of time.  However, if the same app has any wording linking the amount of steps you take to weight management or obesity then it moves out of the realm of simply being a wellness application and instead becomes a medical app that has not been thoroughly regulated.

Even though it is a suggestion that has become common knowledge (exercise leading to weight loss) the application has indeed violated the app stores regulatory language.  Often times, the software companies behind these aren’t even aware a violation has occurred until they receive a message detailing the removal of said app from the store. It is this exact problem that the FDA seeks to correct but the changes won’t come overnight.

The process will start with an evaluation of a given app to determine the risk level it poses and if the information given is inaccurate or not fleshed out enough.  Representatives in charge of this movement have stated several times that the process won’t be as all encompassing as once imagined.  The pedometer example is a good indicator of apps that might be passed by when a decision is being made.  While a certain pedometer app may not have a licensed professional substantiating its health claims, the risk an obese person has from exercising is fairly low and thus not a priority of the FDA to regulate said app.

smart phone mobile ME-P

Real Issues

The real issue lies with apps that are more closely tied to high-risk adverse health conditions like cancers, heart problems or acute viruses.  If an app gives you a series of pictures of individuals with a certain kind of rash that is indicative of “X” virus and a user then takes medical advice on the assumption that they share the same symptoms, a serious problem has occurred.

With such a high propensity for misdiagnosing, the FDA isn’t asking that you blatantly ignore or cease to use all applications that have not been backed up by an expert.  The FDA is rather suggesting that individuals use their best judgment when seeking out advice via the app store.  If something appears serious visit a physician or a doctor, not an automated response from an app you paid .99 cents for.

Assessment

The FDA hopes to put the final touches on their regulatory guidelines sometime in the next two months.  When the guidelines go live, you can expect to see a huge change to the quality and quantity of the medical apps that are released onto the iOS store.

About the Author:

Adam Ghosh has over twenty years experience as a researcher in the medical field. In that time he has worked with allergists and vascular surgeons, and everyone in between. Now he supplements his early retirement by contributing to: http://www.weatherbyhealthcare.com

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details

How To Stay Within Your Holiday Budget

   Yes – it Can be Done with these Secrets!
 By Dr. David Edward Marcinko MBA CMP
 www.CertifiedMedicalPlanner.org

Join Our Mailing List

For some doctors and many Americans, the holiday season is all about excess, and all the gifts, travel, drinks, decadent food, and party dresses can leave a gaping hole in your personal finances. And so, as a Certified Medical Planner, I know that a holiday budget is a helpful tool for managing your spending during the holiday season, so that you don’t start out the New Year in the red. Of course, a holiday budget is only effective if you stick with it, and these shopping tips can help you do just that.

Hallelujah!

Shorten your gift list

Sure, the holiday season is about generosity, but that doesn’t mean you need  to buy an extravagant gift for everyone on the neighborhood block or office floor. Gifts are easily one of the largest expense categories during the holiday season, so the fewer gifts you have to buy; the easier it is to stay within your holiday budget. When times are tight, it’s okay to scrutinize your gift list and cut out anyone whom you don’t really need or even want to buy for. This important step should be done before you even make your holiday budget.

Set a spending limit for each person

Once you’ve whittled down your gift list, set a spending limit for each person on that list. You may want to spend the most on family and friends, but these are also the relationships that leave the most room for creativity.

For example, it might be fun to have your family make gifts for one another this year or create a challenge among friends to see who can find the best gift for the least amount of money. Your boss, CMO or CXO on the other hand, may not appreciate inexpensive gifts like your homemade fudge or a handcrafted ornament.

Shop ahead for deals

When the holiday season is fast approaching, you’re pretty much forced to pay whatever prices the stores are offering, although you can sometimes save money by shopping online at websites like Amazon and eBay. However, if you’re smart, you’ll start your holiday shopping early, leaving yourself time to hunt down only the very best deals.

Shop with cash

Putting the credit cards away and shopping with cash is another smart way to stay within your holiday budget. In fact, shopping with cash is a good general rule for living within your means year-round, but it’s especially effective during the holiday season, when impulse purchases really go through the roof. If you only bring a designated amount of cash with you on each shopping trip, you’ll be forced to stick within your budget. Setting a time limit on your holiday shopping can also have the same budget-bolstering effect.

ME-P Classified Blast!

Simplify holiday parties

For many medical professionals, lavish parties are another major expense of the holiday season. If you’re invited to tons of holiday parties every year, you can stay within your holiday budget by choosing to RSVP to only a few; this saves on party attire, gas, cab fare, parking, host/hostess gifts, drinks, and more.

If you plan to host your own party, forget about all the unnecessary decadence that your guests will have forgotten by mid-January; instead, keep things simple, but classy, and keep your guest list small to help stay within your holiday budget.

Assessment

These are just a few of the many ways that you can stay within your holiday budget this season. Nearly any money-saving tips that you employ year-round can be tailored to help you save on your holiday shopping. As long as you take the time to create a holiday budget, and then stick to that plan, you should save major green and subsequently stay out of the red.

How very festive of you!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:


Product Details  Product Details

Macro-Economics and What the ‘Chained CPI’ Could Mean for Social Security?

Join Our Mailing List

Definition of Chain-Weighted CPI

By Dr. David Edward Marcinko MBA

Dr David E Marcinko MBAAn alternative BLS measurement for the Consumer Price Index (CPI), removing the biases associated with new products, changes in quality and discounted prices.

The chain weighted CPI incorporates the average changes in the quantity of goods purchased, along with standard pricing effects. This allows the chain weighted CPI to reflect situations where customers shift the weight of their purchases from one area of spending to another.

Read more: http://www.investopedia.com/terms/c/chain-linked-cpi.asp#ixzz2FdiMs25f

information

Investopedia Example:

The chain weighted CPI incorporates changes in both the quantities and prices of products. For example, let’s examine clothing purchases between two years. Last year you bought a sweater for $40 and two t-shirts at $35 each. This year, two sweaters were purchased at $35 each and one t-shirt for $45.

Standard CPI calculations would produce an inflation level of 13.64% 

((1 x 35 + 2 x 45)/ (1 x 40 + 2 x 35)) =1.1364

The chain weighted approach estimates inflation to be 4.55%

((2 x 35 + 1 x 45)/ (1 x 40 + 2 x 35)) =1.0455.

Using the chain weighted approach reveals the impact of a customer purchasing more sweaters than t-shirts.

Read more: http://www.investopedia.com/terms/c/chain-linked-cpi.asp#ixzz2FdiceVyv

BLS Application

  • What is the C-CPI-U and when did the Bureau of Labor Statistics (BLS) begin publishing it?

BLS began publishing the Chained Consumer Price Index for All Urban Consumers effective with the release of July 2002 CPI data. Designated the C-CPI-U, the index supplements the existing indexes already produced by the BLS: the CPI for All Urban Consumers (CPI-U) and the CPI for Urban Wage Earners and Clerical Workers (CPI-W).

The C-CPI-U employs a formula that reflects the effect of substitution that consumers make across item categories in response to changes in relative prices.

Read more: C-CPI-U data can be found on the BLS web site at http://data.bls.gov/cgi-bin/surveymost?su

Substitution Bias

  • What is substitution and substitution bias? And does the C-CPI-U eliminate it?

Traditionally, the CPI was considered an upper bound on a cost-of-living index in that the CPI did not reflect the changes in consumption patterns that consumers make in response to changes in relative prices.

Since January 1999, a geometric mean formula has been used to calculate most basic indexes within the CPI; this formula allows for a modest amount of substitution within item categories as relative price changes.

The geometric mean formula, though, does not account for consumer substitution taking place between CPI item categories. For example, pork and beef are two separate CPI item categories. If the price of pork increases while the price of beef does not, consumers might shift away from pork to beef. The C-CPI-U is designed to account for this type of consumer substitution between CPI item categories. In this example, the C-CPI-U would rise, but not by as much as an index that was based on fixed purchase patterns.

With the geometric mean formula in place to account for consumer substitution within item categories, and the C-CPI-U designed to account for consumer substitution between item categories, any remaining substitution bias would be quite small.

Assessment 

Link: What ‘chained CPI’ could mean for Social Security

White Paper: http://www.bls.gov/cpi/super_paris.pdf

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details

Doctor’s and the Fiscal Cliff

Join Our Mailing List

What’s a Physician-Investor to Do?

By Rick Kahler MS CFP® ChFC CCIM www.KahlerFinancial.com

Rick Kahler CFPSo the economic train is speeding faster and faster, and the edge of the fiscal cliff is getting closer and closer, and the passengers are starting to scream. Meanwhile, the guys in the cab of the engine are arguing about whether to hit the brakes or blow the whistle.

What’s the best thing for any investor to do?

Nothing!

Based on my emails this week from clients and readers of my column, there seems to be widespread concern among investors that we’re on the verge of panic and the markets are about to head south.

It reminds me of the good old days, back in the fall of 2008, when the markets were dropping 900 points a day. I’m sensing that the fear among investors about going over the fiscal cliff is similar to the fear of four years ago. The only difference is that the markets aren’t falling today.

Those who assume the markets are about to drop may be right. If that’s the case, what should you be doing to your portfolio to prepare? Assuming it is globally diversified, not a thing.

The News

Many investors, and medical professionals, already are sitting on the sidelines in bonds, shifting through a plethora of bad news and waiting for markets to tank. They have good reason for their expectations. There has been a steady stream of bad news over the past year: a feeble global economic recovery, the near certainty the US will raise taxes and cut spending (a/k/a the fiscal cliff), staggering budget deficits around the globe, the prospect of a EuroZone breakup, a highly negative and divisive presidential election, banking scandals, and a nationwide drought.

Bonds

Considering all the uncertainty, it’s easy to explain why investors have generally favored bonds over stocks during the past 12 months.

With all this bad news, one could expect stocks to be down significantly. For the 12-month period ending September 30, 2012, however, 40 markets had positive returns, with six countries—including the US—delivering a total return in excess of 30%. This is according to the investment analysis firm Morgan Stanley Capital International.

While most investors think successful investing requires constant attention to current events, research says the opposite is true. The more that investors pay attention to the breaking news and adjust their portfolios, the lower their returns.

Fiscal Cliff

Bailing Out

But, with the looming fiscal cliff, shouldn’t a wise investor bail out now and then buy back in at the bottom? It would be like jumping off the train before the crash, then waiting until it has hit the ground, been repaired, and is back on track before you get on again. The only problem is there’s no way to know whether the markets will go down, or if they do, how to know when they hit bottom and it’s time to get back in.

Going to Cash?

The worst action you could take right now is to sell out your portfolio and go to cash.

If you have a globally diversified portfolio, the US decision to tax more and spend less will have much less impact.

For example, our typical 60/40 portfolio only has 13.5% in US stocks and 25% in US bonds. Over half of it is in international stocks, bonds, and non-US correlated investment strategies. It’s designed to cushion even extreme fluctuations in the markets.

Assessment

Anyone who is appropriately diversified has no need for fear as we get closer to plunging off the fiscal cliff. To protect your investments, don’t sell out. To preserve your peace of mind, don’t panic. Above all, don’t jump. The best possible response is to simply stand by and watch the train wreck.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product Details

Publications Related to Behavioral Finance, Economics and Money

Join Our Mailing List

Interesting Articles by Dan Ariely PhD

NOTE: Dan is the Irrational Economist: He blogs at: http://danariely.com/

By Staff Reporters

LIST:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

Letter from the Editor on Sandy Hook Elementary School

Join Our Mailing List

A Painful Op-Ed Piece

By Dr. David Edward Marcinko FACFAS, MBA, CMP™

[Publisher and Editor-in-Chief]

Dr David E Marcinko MBAThe tragedy which struck the Sandy Hook Elementary School in Newtown, Connecticut last Friday left this Medical Executive-Post, and the entire nation, stunned. So many deaths of far too young victims! It is difficult to comprehend, explain or manage. It is not so difficult to feel some of the enormous loss of the parents, families and friends of the victims.

And, I’m sure it is unnecessary for me to encourage you to keep them in your thoughts and prayers. You, like me, have probably thought of little else since Friday.

At the ME-P, we will remember the people and families in Newtown, CT. Like the rest of the nation, our home-page flag will be at half-staff through this week.

If you have children of elementary school age, you may need some opportunities to process their reactions to this tragedy. Perhaps all they need is someone to listen, or to reassure them that these tragedies are rare events. We trust your local clergy, pediatricians and counselors are available to assist you or your child if that would be helpful.

More: www.CertifiedMedicalPlanner.org

In closing, I would like to share with you a Judeo-Christian reading which might bring some comfort during these difficult days:

A Prayer

The Spirit of the Lord God is upon me, because the Lord has anointed me to bring good news to the poor …  to comfort all who mourn; to grant to those who mourn in Zion— to give them a beautiful headdress instead of ashes, the oil of gladness instead of mourning, the garment of praise instead of a faint spirit; that they may be called oaks of righteousness, the planting of the Lord, that he may be glorified.

Assessment

ME-P Textbook: Chapter 07: Workplace Violence

We trust the deep knowledge and expertise on this topic by ME-P thought-leader Gene Schmuckler is available to you, as needed.

Fraternally,

David Edward Marcinko

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Product Details

Product Details

The Newtown, Conn School Massacre [Lessons to Learn?]

Join Our Mailing List

REPRINT: This re-publication is provided as a service to our readers, as we mourn the children and victims of the Newtown, Conn massacre. The workplace – healthcare setting analogy is self-evident.

Hospital Workplace Violence Risk Factors

[An NIOSH Summary and Review]

By Dr. Eugene Schmuckler MBA CTS

By Dr. David Edward Marcinko MBA CMP™

www.CertifiedMedicalPlanner.org

Domestically, the impact of workplace violence in the US became widely exposed on November 6, 2009 when 39 year old Army psychiatrist Maj. Nidal M. Hasan MD, a 1997 graduate of Virginia Tech University who received a medical doctorate in psychiatry from the Uniformed Services University of the Health Sciences in Bethesda, Maryland, and served as an intern, resident and fellow at the Walter Reed Army Medical Center in the District of Columbia, went on a savage 100 round shooting spree and rampage that killed 13 people and injured 32 others.

In April 2010 he was transferred to Bell County Jail in Belton, Texas. An Article 32 hearing, which determined whether Hasan would be fit to stand trial at court martial, began on 12 October 2010. Hasan subsequently deemed fit, was arraigned on July 20 2011 and trial was scheduled for March 2012. It was rescheduled again, but is now ongoing and in the news; almost daily.

The NIOSH

The National Institute for Occupational Safety and Health (NIOSH) summarizes the risk factors for occupational violence to hospital workers. These include:

  • working directly with volatile people, especially if they are under the influence of drugs or alcohol or have a history of violence or certain psychotic diagnoses;
  • working when understaffed — especially during meal times or visiting hours;
  • transporting patients and long waits for service;
  • overcrowded, uncomfortable waiting rooms;
  • working alone;
  • poor environmental design;
  • inadequate and/or ineffective security;
  • lack of staff training and policies for preventing or managing crises with potentially volatile patients;
  • drug and alcohol abuse;
  • access to firearms;
  • unrestricted movement of the public; and
  • poorly lit corridors, rooms, parking lots, and other areas.

Occupational Violence 

Violence occurring in other occupational groups is most often related to robbery. In healthcare settings, however, acts of violence are most often perpetrated by patients or clients. Family members who feel frustrated, vulnerable, and out of control; and colleagues of patients (especially when the patient is a gang member) are also identified as perpetrators of abuse! However, the presence of co-workers has been identified as a potential deterrent to assault in healthcare.

Healthcare and social service workers face an increased risk of work-related assaults stemming from several factors, including:

  • the prevalence of handguns and other weapons — as high as 25% among patients, their families, and friends. Handguns are increasingly used by police and the criminal justice system for criminal holds and the care of acutely disturbed, violent individuals;
  • the increasing number of acute and chronically mentally ill patients now being released from hospitals without follow-up care, who now have the right to refuse medicine and who can no longer be hospitalized involuntarily unless they pose an immediate threat to themselves or others;
  • the availability of drugs or money at hospitals, clinics, and pharmacies, making staff and patients likely robbery targets;
  • situational and circumstantial factors such as:
    • unrestricted movement of the public in clinics and hospitals;
    • the increasing presence of gang members, drug or alcohol abusers, trauma patients, or distraught family members;
    • long waits in emergency or clinic areas, leading to client frustration over an inability to obtain needed services promptly;
  • low staffing levels during times of specific increased activity such as meal times, visiting times, and when staff is transporting patients. This also includes isolated work with clients during examinations or treatment;
  • solo work, often in remote locations, particularly in high crime settings, with no back up or means of obtaining assistance such as communication devices or alarm systems;
  • lack of training of staff in recognizing and managing escalating hostile and assaultive behavior; and
  • poorly lighted parking areas.

OSHA

The Guidelines established by the Occupational Safety and Health Administration (OSHA) seek to set forth procedures leading to the elimination or reduction of worker exposure to conditions causing death or injury from violence by implementing effective security devices and administrative work practices, among other control measures. Healthcare professionals need to be aware that violence can occur anywhere and in any practice settings.

In hospitals and clinics, which are more likely to report incidents of violence than private offices, the most frequent sites are:

  • psychiatric wards;
  • acute care settings;
  • critical care units;
  • community health agencies;
  • homes for special care;
  • emergency rooms; and
  • waiting rooms and geriatric units.

Impact

The impact of workplace violence is far-reaching and affects individual staff members, co-workers, patients/clients, and their families. Those who have been affected, directly or indirectly, by a workplace violence incident report a broad spectrum of responses — anger is the most common. There are also reports of:

  • difficulty returning to work;
  • decreased job performance;
  • changes in relationships with co-workers;
  • sleep pattern disturbance;
  • helplessness and symptoms for post-traumatic stress disorders;
  • fear of other patients; and
  • fear of returning to the scene of the assault.

Assessment

Link: Chapter 07: Workplace Violence

More: Medical Workplace Violence

BREAKING NEWS: 3 shot in Alabama hospital *** Two die in Nev. hotel shooting

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

From Our Newest Textbook Release

Buy from Amazon

Learn How to Profit and Thrive in the PP-ACA Era

BOOK FOREWORD / TESTIMONIAL

Health Economics Defined

Join Our Mailing List

How We Use and Allocate Scarce Resources

Sex Voucher

Asseessment

A sex voucher – delayed gratification?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Confusion About “Meaningful Use” Reigns

Join Our Mailing List

Are Doctors Embracing or Ignoring ARRA?

By D. Kellus Pruitt DDS

pruittAre physicians embracing ARRA Meaningful Use cash incentives or ignoring them? That depends on whom one asks.

Doctors versus the Feds

National progress towards Meaningful Use of expensive EHRs depends on whether one talks to federal employees whose jobs depend on the stimulus mandate, or doctors who purchase EHRs to improve care rather than to use them … Meaningfully.

The Feds

Today, Joseph Conn, writing for ModernHealthcare, posted a rosy outlook for MU adoption according to researchers working for HHS’ Office of the National Coordinator (ONC). They base their optimism for job security on a recent National Center for Health Statistics (NCHS) survey:

“A growing number of office-based physicians are using more-robust EHRs that have higher-level functions needed to help the doctors qualify for federal EHR incentive payments [for Meaningful Use] and assist them in providing better, safer care for patients, the researchers reported.” (See “Researchers: More doctors using more-sophisticated EHRs”).

http://www.modernhealthcare.com/article/20121212/NEWS/312129956/researchers-more-doctors-using-more-sophisticated-ehrsJust

eMR and HIT Security

The Doctors

However, yesterday, in an InformationWeek article by Ken Terry titled, “Meaningful Use Doesn’t Drive Doctors’ EHR Selection,” doctors suggested a more depressing future for MU sophistication based on the same NCHS survey:

“Jason Mitchell, MD, assistant director of the Center for Health IT at the American Academy of Family Physicians (AAFP), told InformationWeek Healthcare that he found [the lagging adoption of MU-capable EHRs] puzzling. While there’s no doubt that Meaningful Use has driven much of the increase in EHR use, he said, it seems strange that so many physicians would buy and implement EHRs that could not be used to show Meaningful Use.”

http://www.informationweek.com/healthcare/electronic-medical-records/meaningful-use-doesnt-drive-doctors-ehr/240144093

Assessment

Whom should doctors believe – HHS employees who give away billions of stimulus dollars for Meaningful Use, or family physicians who have determined that the subsidy isn’t worth the cost and effort?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors


Product Details

What’s the Difference between a Millionaire and a Billionaire?

Join Our Mailing List

Three Zeroes … and a Comma

By Rick Kahler MS CFP® ChFC CCIM www.KahlerFinancial.com

Rick Kahler CFPNo, this isn’t a bad joke. It takes one thousand millions to make one billion. That’s a huge difference. And, how many doctors have arrived there?

A Political “Hot-Button”

Over the past couple of years, especially during the presidential election, one of the hot-button issues has been whether the wealthy are paying “their fair share” in taxes. A great deal of the media coverage and political rhetoric, from President Obama on down, has lumped “millionaires and billionaires” together.

That makes as much sense as putting a housecat and a tiger into the same cage and saying they’re just the same.

Who Wants to be a Billionaire?

The first issue to clarify is the definition of “millionaire” and “billionaire.” Is it someone with a net worth of $1 million or $1billion, or is it someone earning a million or a billion in a year?

According to wild.answers.com, only 80,000 Americans make $1 million or more a year. I couldn’t find a source listing how many people make over $1 billion a year, but I can guess. If you earned 6% on your investments, you would need a net worth of about $16 billion to provide an annual income of $1 billion. According to Forbes (March 2012), only 40 people in the entire world have a net worth of over $16 billion. Obviously, all those references we keep hearing to billionaires must refer to net worth, not income.

This is in line with the Merriam Webster dictionary, which defines millionaire (or billionaire) as “a person whose wealth is estimated at a million (or billion) or more.”

The Life-Style

What kind of lifestyle can you have with a net worth of a million as opposed to a billion dollars? Experts tell us the most reasonable sustainable withdrawal rate is 3%. That means your $1 million will provide $30,000 a year. Adding in Social Security of $18,000 a year means a millionaire can retire on an income of $48,000 a year. If you need assisted living, in-home care, or nursing home care in your later years, which at today’s rates cost a minimum of around $84,000 a year, you’ll be spending down your principal.

Three percent of $1 billion, on the other hand, will give you a retirement income of $30 million a year. At that rate, you could probably get by without bothering to file for Social Security.

MDs

Aiming High

Accumulating $1 million over a lifetime is certainly possible for middle-class earners who are willing to live on less than they make. If you started saving about $1,750 a month at age 25, you’d have your million by age 65. That’s about the same as a married couple each maximizing their 401(k) contributions.

To accumulate $1 billion by age 65, on the other hand, if you started at age 25 you’d need to save a mere $21 million a year.

Equating a millionaire with a billionaire is the same as equating the population of Rapid City, South Dakota (70,000) to the combined populations of California, Texas, and Virginia (70,000,000). There is simply no comparison.

Rich?

The point here is that in today’s world, a millionaire, especially one who is retired, isn’t “rich.” Accumulating a net worth of $1 million dollars by age 65 is a completely reasonable and achievable goal for anyone wanting a comfortable and secure retirement.

Assessment

Lumping “millionaires and billionaires” together might roll off the tongue with a rhythm that makes a nice sound bite. That doesn’t mean it makes sense. For anyone willing to do the math, the comparison is ludicrous. There’s a world of difference in earnings, wealth, and potential lifestyle in those extra three zeroes.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product Details

Physician’s Personal Income Tax Review for 2013

Join Our Mailing List

Are Dramatic Increases Ahead – For us All?

By Children’s Home Society of Florida Foundation

Following the November election, Congress will return for a “lame-duck” legislative session. Major decisions are needed on both taxes and spending. If Congress does not take action, there will be dramatic tax increases on January 1, 2013.

These potential changes include personal income taxes, long term capital gains tax, dividend tax, a new Medicare tax and the estate tax.

Personal Income Taxes

The major change in personal income taxes is that the rates will return to the 2003 schedule. The tax reductions passed in 2001 and 2003 are no longer applicable after 10 years. Therefore, tax rates are scheduled to increase. The table below shows the rates for 2012 and the new increased rates scheduled for 2013.

###

2012 Rates 2013 Rates
10% 15%
15% 15%
25% 28%
28% 31%
33% 36%
35% 39.6%

Long-Term Capital Gains

The long-term capital gains rate for 2012 is 15%. Most investment property held more than one year qualifies for the 15% rate. In 2013, long-term capital gains will be taxed at 20%. However, the new 3.8% Medicare tax will apply to capital gains for higher-income persons. Their top rate will be 23.8%.

Dividend Taxes

Dividend taxes in 2012 are at a reduced level for payments from U.S. corporations and some foreign corporations. In 2012, most dividends are taxed at the 15% long-term capital gain rate. If the law is not changed, in 2013 they will be taxed as ordinary income. The top rate for dividends could be 39.6%. In addition, the 3.8% Medicare tax applies to dividends, producing a potential tax on dividends of 43.4% for higher-income taxpayers.

New Medicare Tax

The Patient Protection and Affordable Care Act (PPACA) creates a new Medicare tax in 2013. The tax is 3.8% on the amount of income that exceeds $200,000 for a single person and $250,000 for a married couple. The tax is generally applicable on interest, dividends, passive income from a business, sales of property and other income from financial instruments.

Fortunately, IRA and other pension income are not subject to the increased Medicare tax. However, this retirement income may increase your total income levels. If total income exceeds the $250,000 or $200,000 levels, then your IRA distributions may cause other investment and capital gain income to be subject to the Medicare tax.

Other Personal Tax Changes

There are other changes that will affect individuals. Under PPACA, individuals with incomes over $200,000 (single) or $250,000 (married couples), will pay an additional payroll tax of 0.9% on the excess amount. The personal exemption phase out and limitations on itemized deductions will be reinstated.

Finally, the medical expense deduction floor increases from 7.5% to 10% for most taxpayers. It is retained at 7.5% for persons age 65 and older. Only qualified medical expenses in excess of the floor are deductible.

Estate Tax

In 2012, the applicable exclusion amount for gift and estate taxes is $5.12 million. In addition, a spouse may pass away and transfer his or her available exemption to a surviving spouse. The surviving spouse therefore could have an estate exemption up to double the standard amount.

If there is no tax bill, the exemption reverts to $1 million plus indexed increases over the past decade. In addition, the current 35% estate tax rate will increase to a top rate of 55%, starting at a $3 million estate. Estates from the $1 million plus indexed amount to $3 million will pay tax at a reduced rate. The marital portability, or option to transfer your exemption to a surviving spouse, will not apply unless extended by Congress.

Editor’s Note: It is probable that there will be significant tax changes on January 1, 2013. Because the November legislative session is very short, Congress may change some provisions, but is not likely to change all of these tax rates. It will be important for all Americans to be in contact with their tax advisor to take appropriate action to reduce taxes in December of 2012.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details


Another Property-Casualty Insurance Claims Experience

Join Our Mailing List

A Personal Scenario

By Rick Kahler MS CFP® ChFC CCIM www.KahlerFinancial.com

Rick Kahler CFPHurricane Sandy attacked the East Coast, did her worst, and disappeared. Yet cleaning up the mess she left behind will take months and even years. And, even dealing with damage from much smaller disasters can take a long time.

As an example, in July 2011 a severe storm with baseball-sized hail moved through southern Rapid City. It only took nature a few minutes to flatten gardens, beat up vehicles, and damage buildings. It will probably take until the second anniversary of the storm to repair all the damage to our house.

Such a delay isn’t unusual. The most common reasons are finding a contractor and negotiating with your insurance company.

Reporting Claims

Moving quickly to report a claim after a disaster is important. In fact, you should probably call a contractor even before you call your insurance agent. Insurance companies are fast to respond to disasters and easily move adjusters in from other areas. Local, credible contractors, on the other hand, fill their schedules fast. We spent hours on the phone to get bids from beleaguered roofers, painters, and carpenters.

These bids were worth our time, because they showed us that the initial repair estimates from our insurance company were low—usually by 50% to 66%.

For example, our roof had cedar shake shingles. The company’s replacement estimate was for much cheaper asphalt shingles. Estimates to repair our siding and deck were also low. It took us 15 months to come to an agreement on the cost of replacing the deck. The work probably won’t be done until summer of 2013.

Switching Companies?

Does this difficulty in getting a full settlement mean it’s time to switch insurance companies?  Certainly, I thought so more than once during the negotiating process. However, that isn’t necessarily the case. It’s important to remember that getting compensation from an insurance company is just business. And good business means not necessarily accepting the first offer. Negotiating will take time and effort, but it eventually should get you full compensation.

When you file a claim, you and your insurance company have competing interests. The company is not your advocate. You want as much money as possible from them for repairs, while they want to repair your damage for the lowest cost. There’s nothing out of place with either motivation.

Once I understood that the insurance company and I were natural adversaries, not friends, it helped me feel less victimized and more empowered. While getting the money we needed to make the repairs certainly took time and perseverance, the company readily acquiesced when we presented the facts. After all, their best interest also included keeping us as customers. We did not have to threaten a lawsuit or go to court.

Certainly, when it’s time to renew my home insurance I will ask my agent to investigate other companies. That’s just business. However, I won’t change companies just because I had to argue with this one.

policy insurance

The [Doctor’s] Claimant Role

Understanding your role in negotiating an insurance claim helps bring a healthy perspective to your relationship with any service provider. Unless they are a fiduciary to you (like an attorney, a doctor, or a fee-only financial planner), they have no responsibility to look out for you. Someone selling you something has no duty to put your interests before theirs. Protecting your interests is your duty and yours alone.

Assessment

When a natural disaster strikes, whether it’s a hail storm or a hurricane, we are certainly victims of nature’s whims. When it’s time to clean up the mess, though, we’re not victims. We’re our own advocates, with the responsibility and ability to look out for our own best interests.

Related: Dr. Marcinko Invites Mr. Wilson [CEO Allstate] to Debate

Related: As an Ex Agent – Why I’m Still Protesting My Open Allstate Home Owner’s Insurance Claim

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

The “Price” of eHRs

Join Our Mailing List

Race to electronic health records may come with a price

By Fred Schulte

Amid all the enthusiasm over increasing the use of information technology in health, politicians and policy makers paid little attention to the implications of a gold rush sparked when billions of taxpayers’ dollars suddenly came up for grabs. Hundreds of medical technology companies scrambled to sell digital systems — often by promising doctors and hospitals they could boost revenues by billing higher rates to Medicare and other health insurers.

The fallout from those early decisions could be coming back to haunt taxpayers, according to a three-part investigative series from the Center for Public Integrity. The series documented that thousands of medical professionals steadily billed Medicare for more complex and costly health care over the past decade — adding $11 billion or more to their fees — despite little evidence elderly patients required more treatment.

In this essay, reporter Fred Schulte explains how the project came about, how the Center did its reporting and provides plenty of background on medical coding, Medicare billing and the potential fallout as health care providers install and use electronic systems.

Assessment

Full link: Race to electronic health records may come with a price

Publisher’s Note: Fred Schulte is a four-time Pulitzer Prize finalist, most recently in 2007 for a series on Baltimore’s arcane ground rent system. Schulte’s other projects exposed excessive heart surgery death rates in veterans’ hospitals, substandard care by health insurance plans treating low-income people and the hidden dangers of cosmetic surgery in medical offices. He spent much of his career at The Baltimore Sun in Maryland, where I first noted his work, and then the South Florida Sun-Sentinel. Schulte has received the George Polk Award, two Investigative Reporters and Editors awards, three Gerald Loeb Awards for business writing and two Worth Bingham Prizes for investigative reporting. The University of Virginia graduate is the author of Fleeced!, an exposé of telemarketing scams. Schulte can be reached at fschulte@publicintegrity.org or 202-481-1210.

eHRs

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details

Your Private Medical Practice “Game-Plan”

Join Our Mailing List

Get Our “Game-Plan” for Modern Private Medical Practice Success

Product Details

Assessment

Link: www.BusinessofMedicalPractice.com Online “live” Social Network Community

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Benchmarking Small Business Financial Fitness

Join Our Mailing List

A Small Business Snapshot

Small Biz Finances

Source: Intuit

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product Details

Will Higher Taxes Damage Your Portfolio?

Join Our Mailing List

Discussing Stock Market Performance

By Lon Jefferies CFP® MBA

Net Worth Advisory Group

Lon Jeffrieslon@networthadvice.com

www.networthadvice.com

Do higher taxes equate to negative stock market returns? Does anyone economic variable accurately predict stock market performance?

A number of our Net Worth Advisory Group physician and lay clients have indicated they are concerned about the impact higher taxes could have on the stock market. News organizations and campaign rhetoric create the impression that there is a cause and effect relationship between taxes (or whatever the hot discussion topic is) and stock market performance. Since 1926, the stock market has obtained positive returns during a calendar year 72% of the time.

Economic Variables

Here are the facts about how various economic variables have impacted investment returns:

  • PERSONAL INCOME TAXES: From 1926-2011 there were 20 years where personal income taxes (for incomes over $150,000, adjusted for inflation) increased over the previous year. The stock market went up 13 of those years, or 65% of the time.
  • CORPORATE TAXES: From 1926-2011 there were 11 years where corporate taxes increased over the previous year. The stock market went up 6 of those years, or 55% of the time.
  • LONG-TERM CAPITAL GAINS: From 1926-2011 there were 11 years where the long-term capital gains tax rate increased over the previous year. The stock market went up 9 of those years, or 82% of the time.
  • INTEREST RATES: From 1956-2011 there were 27 years where interest rates (measured by the Treasury Bill) increased over the previous year. The stock market went up 24 of those years, or 89% of the time.
  • INFLATION: From 1926-2011 there were 43 years where the inflation rate increased over the previous year. The stock market went up 33 of those years, or 77% of the time.
  • NATIONAL DEBT: From 1940-2011 there were 38 years where the national debt as a percentage of gross domestic product (GDP) increased over the previous year. The stock market went up 30 of those years, or 79% of the time.
  • DEFICITS SPENDING: From 1926-2011 there were 38 years where deficit spending increased over the previous year. The stock market went up 30 of those years, or 79% of the time.
  • COMPANY PROFITABILITY: From 1961-2011 there were 25 years where the earnings of S&P 500 companies increased over the previous year. The stock market went up 21 of those years, or 84% of the time.
  • COMPANY DIVIDENDS: From 1961-2011 there were 21 years where S&P 500 companies increased their dividends over the previous year. The stock market went up 17 of those years, or 81% of the time.
  • UNEMPLOYMENT: From 1948-2011 there were 20 years where the unemployment rate increased over the previous year. The stock market went up 9 of those years, or 45% of the time.

Investing and Taxes

Predictions?

As the data indicates, there is no single economic variable, positive or negative that consistently predicts stock market performance. The market may produce positive or negative returns in 2013, but it’s not likely to be because the personal income tax for high income families increased.

The Unemployment Figures

It’s worth noting that the only economic factor that led to a declining market more frequently than not is rising unemployment. While the unemployment rate remains at 7.8%, high by historical standards, it has been steadily decreasing since October of 2009 when it reached 10%.

Additionally, the only other individual indicator that seems to have even a marginally significant negative impact on stock market returns is an increase in the corporate tax rate; if President Obama can get Congress to agree with him, he would like to decrease that rate from 35% to 28% next year. Consequently, history indicates that neither rising unemployment nor increased corporate tax rates will apply in 2013 and should not hamper stock market returns.

Suggestions

History has taught us over and over again that time in the market is much more important than timing the market. It has also taught us that one of the biggest mistakes investors make is to say “these conditions have never existed before and this time is different.”

Need a recent example? Remember the general consensus investors reached about Europe near the beginning of the year? It may surprise you that Europe (as measured by the Vanguard MSCI Europe ETF) has returned over 17% year to date, significantly outpacing the growth of the S&P 500.

Assessment

I personally believe the best game plan for medical professionals is to develop a fundamentally sound diversified portfolio, only investing money you don’t anticipate spending for at least 10 years in stocks, and stay the course.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details  Product Details

Product Details

Helping Doctors Understand Multi-Point Automobile Check-Up Inspections

Join Our Mailing List

Some Tips and Terms for Medical Professionals to Know for Keeping Your Car Healthy … and Saving Money!

By Dr. David Edward Marcinko MBA

Via Source: Nalley Lexus – Roswell, GA

Taking your vehicle in for service is often like going to the doctor for a routine checkup. As a car, and especially Jaguar, enthusiast I should know. There is a photo of my vintage 2000 XJ-V8-L below. My wife calls her “Ellie“; short for elegant.

If your car is having problems, it may be the human equivalent to the flu. It just goes to show how similar cars are, and while their blood may be made up of oil and gasoline, taking care of your car is still a very important task.

Regular Care

Neglect to take care of yourself or your car, and you could be staring down some pretty expensive bills.

When you take your vehicle in for service, the technicians will often perform a multi-point vehicle inspection. Just as a doctor would make notes in your medical chart, the repair technician has a list of areas to check on your vehicle. This record is given to you when service is complete so you can judge for yourself when to make repairs, and prepare accordingly.

The only problem is that many people simply don’t know what these records mean. While the inspections are intended to improve safety and save money in the long run, many owners ignore them and are forced to pay the consequences. No worries, as we’ll take a look at what the multi-point inspection form means and why it’s so important.

Checklist

At the top of the multi-point checklist inspection form are often the vehicle’s make, model, mileage, and the name of the technician performing service. The owner’s contact information is also noted here, as well as the vehicle’s identification number, or VIN for short. This is the vehicle’s version of a social security number and is just as important to your car for legality reasons.

From here on out, you’ll likely see a lot of green, yellow, and red boxes with check marks scattered throughout. To keep things simple, just think of it as a traffic signal: Green boxes that are checked mean that the component was inspected and found to be in good condition, while yellow means that the part will need attention and service in the future, and red boxes denote components requiring immediate attention for safety’s sake.

Issues

What kinds of things and issues are checked? Perhaps the most prevalent item on any inspection sheet is the condition of the vehicle’s tires. You’ll see conditions marked for each tire regarding tread depth, tire pressure, damage, and wear patterns, and whether an alignment check is necessary. You’ll also notice that brake condition is highly important on the inspection sheet. Again, the color of the marked box denotes overall condition of the braking system, and whether or not components such as brake pads need to be replaced.

Jag sedan

***

[The publisher’s classic automobile]

Even More Issus

Aside from the major components such as tires and brakes, other things being inspected are just as important, if a bit smaller and tougher for the normal owner to notice. All fluids such as coolant, transmission fluid, engine oil, brake fluid, and power steering fluid are checked, which is helpful as most owners don’t think to check the condition and levels of these fluids on a normal basis. Other components inspected include windshield wipers, air filters, steering linkage, lighting components, and suspension and steering pieces, among other things.

Assessment

Take it from me – it sure may all sound like a complex task, and one that seems pretty important. That’s because it is. It may just be a piece of paper, but it’s one that can give a great glimpse into the condition of your vehicle.

After all, wouldn’t you want to know if you had health problems?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

A Financial eMR “Got-Ya” from Uncle Sam?

Join Our Mailing List

CMS and the Feds Want to Verify Docs eMR Info Before Meaningful Use Payment

By ME-P Staff Reporters

The conversion to electronic medical records [eMRs] is “vulnerable” to fraud and abuse because of the failure of Medicare and CMS officials to develop appropriate safeguards, according to a sharply critical report just issued by federal investigators.

###

[mobile eMR in clincal use]

###

Full Report: https://oig.hhs.gov/oei/reports/oei-05-11-00250.pdf

Assessment

Requiring an audit before paying hospitals and doctors could  significantly delay payments to providers.

Ya think!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product Details

Doctors Selecting the Wrong Financial Advisor [Video]

Join Our Mailing List

Does it Seem Like this … Sometimes?

MD versus FA

Link: http://www.youtube.com/watch?v=Vv4HQG2Hz0I

Assessment

Visit: www.CertifiedMedicalPlanner.org

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

On the Herpes Simplex Virus (Type 1 HSV-1 & Type 2 HSV-2)

Join Our Mailing List

Many Thanks 1980s

herpes

Sophisticated Ladies

###

Brothel

And … Not So Sophisticated

###

Assessment

herpes stats

50 Years of Herpes Stats

###

Info Link: http://www.cdc.gov/std/herpes/STDFact-herpes.htm

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Events Planner: December 2012

Join Our Mailing List

ADVERTISEMENT

Events-Planner: DECEMBER 2012

By Staff Writers

“Keeping track of important health economics and financial industry meetings, conferences and summits”

Welcome to this issue of the Medical Executive-Post and our Events-Planner. It contains the latest information on conferences, news, and relevant resources in healthcare finance, economics, research and development, business management, pharmaceutical pricing, and physician/entity reimbursement!  Watch for a new Events-Planner each month.

First, a little about us! The Medical Executive-Post is still a relative newcomer. But today, we have almost 175,000 visitors and readers each month from all over the country, in addition to our growing subscriber base. We have been a successful collaborative effort, thanks to your contributions.  As a result, we are adding new resources daily. And, we hope the website continues to provide the best place to go for journals, books, conferences, educational resources, tools, and other things you need to establish the value your healthcare consulting and financial advisory intervention.

So, enjoy the Medical Executive-Post and this monthly Events-Planner with our compliments.

A Look Ahead this Month – And now, the important dates:

  • December 05-06: Predictive Modeling Summit. Washington, DC
  • December 09-12: National Forum on Medical Quality Improvement. Orlando, FLA

MarcinkoAdvisors@msn.com

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Subscribe Now: Did you like this Medical Executive-Post, or find it helpful, interesting and informative? Want to get the latest E-Ps delivered to your email box each morning? Just subscribe using the link below. It’s free. You can unsubscribe at any time. Security is assured.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Our Newest Textbook Release

Buy from Amazon

Learn How to Profit and Thrive in the PP-ACA Era

BOOK FOREWORD / TESTIMONIAL

Understanding Modern Healthcare Market Competition

Join Our Mailing List

Updating Competitive Strategy Theory in Healthcare

By Robert James Cimasi; MHA ASA FRICs MCBA AVA CM&AA
By Todd A. Zigrang; MBA MHA ASA FACHE
By Anne P. Sharamitaro; Esq.

www.HealthCapital.com

Michael Porter[i] is considered by many to be one of the world’s leading authorities on competitive strategy and international competitiveness.  In 1980, he published Competitive Strategy: Techniques for Analyzing Industries and Competitors,[ii] in which he argues that all businesses must respond to five competitive forces.

(1) The Threat of New Market Entrants

This force may be defined as the risk of a similar company entering the marketplace and winning business.  There are many barriers to entry of new market entrants in healthcare including: the high cost of equipment, licensure, requirement for physicians and other highly trained technicians, development of physician referral networks and provider contracts, and other significant regulatory requirements.

Certificate of Need (CON) laws, which require governmental approval for new healthcare facilities, equipment, and services have been in place since they were federally mandated in 1974.  State CON laws create a regulatory barrier to entry.  New medical provider entrants commonly face substantial political opposition by established interests, which is manifested in the CON review process.

(2) The Bargaining Power of Suppliers

A supplier can be defined as any business relationship upon which a business relies to deliver a product, service, or outcome.  Healthcare equipment is a highly technical product produced by a limited number of manufacturers. This reduces the range of choices for providers and can increase costs.

(3) Threats from Substitute Products or Services

Substitute products or services are those that are sufficiently equivalent in function or utility to offer consumers an alternate choice of product or service.  An illustration of this in healthcare would be diagnostic imaging as a substitute for surgery, which is often a more costly and risky option for patients. The threat of less invasive or less expensive diagnostic tests other than diagnostic imaging is relatively small for the near term future.

(4) The Bargaining Power of Buyers

This force is the degree of negotiating leverage of an industry’s buyers or customers.  The buyers of healthcare services are ultimately the patients. However, the competitive force of buyers is manifested through healthcare insurers including the U.S. and state governments through the Medicare, Medicaid, TRICARE, and other programs; managed care payors (e.g., Blue Cross/Blue Shield affiliates); workers’ compensation insurers; and, others.  In addition to the government, many of these healthcare insurers are large, national companies, often publicly traded, commanding significant bargaining power over healthcare provider reimbursement.

(5) Rivalry Amongst Existing Firms

This is ongoing competition between existing firms without consideration of the other competitive forces which define industries. Healthcare providers face pressure from other existing providers to obtain favorable provider contracts; maintain the latest technology; increase efficiencies; and, lower prices.

References:

[i]  A professor of Business Administration at the Harvard Business School, Michael Porter serves as an advisor to heads of state, governors, mayors, and CEOs throughout the world.  The recipient of the Wells Prize in Economics, the Adam Smith Award, three McKinsey Awards, and honorary doctorates from the Stockholm School of Economics and six other universities, Porter is the author of fourteen books, among them Competitive Advantage, The Competitive Advantage of Nations, and Cases in Competitive Strategy.

[ii]  Porter, M.E. Competitive Strategy: Techniques for Analyzing Industries and Competitors. The Free Press, 1980.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
ADVISORS: www.CertifiedMedicalPlanner.org
PODIATRISTS: www.PodiatryPrep.com
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors



Our Newest Textbook Release

Buy from Amazon

Learn How to Profit and Thrive in the PP-ACA Era

BOOK FOREWORD / TESTIMONIAL

Video on Physician Loans and Doctor Mortgages [Why Over-Pay Big Banks?]

Join Our Mailing List

Bank Offers a Zero Down Payment Physician Mortgage Loan in Kansas and Missouri

Doctors mortgage programs are offered as a benefit in many hospitals. Banks use these physician mortgage loans as an entry point to gain checking, savings, investment, and Home Equity Line of Credit accounts.

It’s important for physicians to realize that a Big banks objective is assets under management and not necessarily the best mortgage for them.

Many banks offered  special  zero down doctor loans and below market mortgages for physicians.  With the upheaval in the mortgage and secondary market requirements (the people who bought those special physician loans), most of the doctors mortgage programs advantages went away, or became no different than what is available to every other borrower.

Get a second opinion

For this reason, it is prudent for physicians to be aware of the changes in doctors loan programs and seek expert independent 2nd Opinions consultations.

Link: www.MedicalBusinessAdvisors.com

Assessment

Many physicians needlessly over pay $10’s of thousands of dollars in interest to big banks. Over a career of homes and refinances, this could add up to well over $100K that could stay in their account.

Video link: http://www.youtube.com/watch?v=ygs81Rsk-Zw

Source: http://www.Physician-Loans.org

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product Details  Product Details

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

How Doctors Might Buy a Pre-Owned Car?

Join Our Mailing List

Used Automobile Purchasing

This infographic on used car purchasing demonstrates the technical and detailed facts which are presented in a unique design.

Pre-Owned Vehicles

The Infographic shows what you should look for when buying a used car.

Source: DandLock

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com
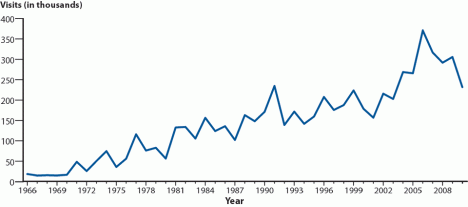
OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Health IT Vendors Ponied-Up Political Cash to Both Parties

Join Our Mailing List

The Presidential Election 2012

This November saw healthcare executives pay big campaign money to both political parties.

Health IT vendors, however, upped the ante this election year, paying out some hefty donations of their own. Judith Faulkner, CEO of Epic, and Allscripts CEO Glen Tullman are among this year’s top spenders.

Source: http://www.govhealthit.com/news/infographic-health-it-vendors-pony-political-cash-both-parties?topic=75

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

Our Other Print Books and Related Information Sources:

Health Dictionary Series: http://www.springerpub.com/Search/marcinko

Practice Management: http://www.springerpub.com/product/9780826105752

Physician Financial Planning: http://www.jbpub.com/catalog/0763745790

Medical Risk Management: http://www.jbpub.com/catalog/9780763733421

Hospitals: http://www.crcpress.com/product/isbn/9781439879900

Physician Advisors: www.CertifiedMedicalPlanner.org

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details