Obama Nominates Robert McDonald as VA Chief [VOTE]

Join Our Mailing List 

But – Will He Succeed? [Opinion Poll]

RMRobert McDonald has been nominated as Secretary of Veterans Affairs, and will turn his mind to the aftermath of conflict and the 9 million former American service people enrolled for care.

If confirmed by the Senate, he’ll succeed Eric Shinseki, a retired general who resigned last month amid explosive charges of mismanagement, falsification of records and a toxic culture that left patients waiting indefinitely for treatment.

Earlier this month, the acting head of the agency confirmed that 35 veterans left off a list died before seeing a doctor, perhaps as result of the delay.

OPINON POLL

Assessment

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

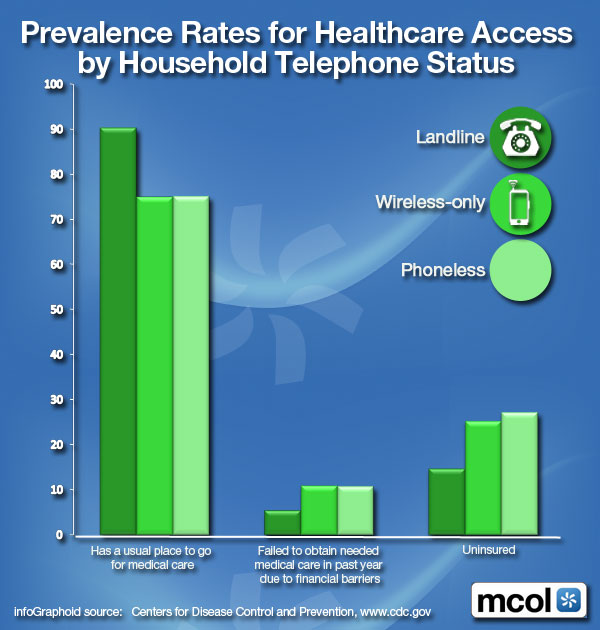
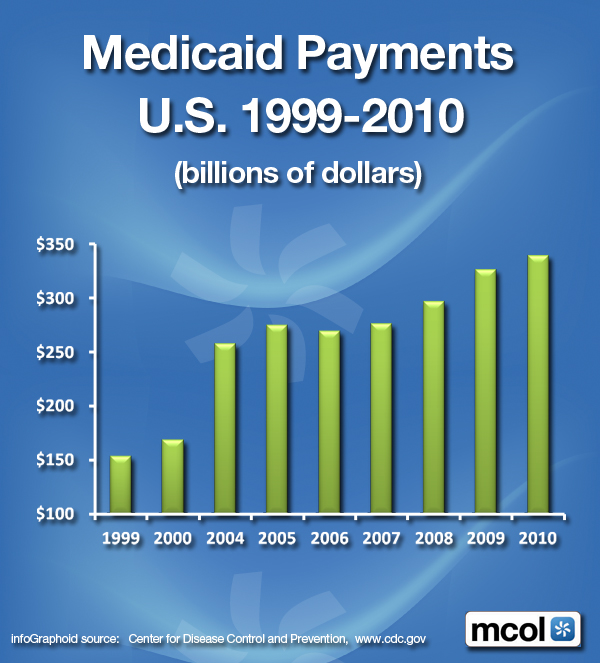
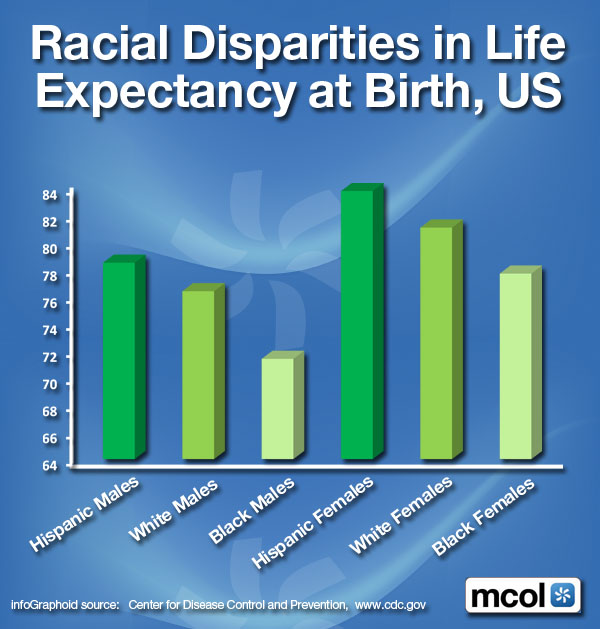
Prevalence Rates of Healthcare Access?

Join Our Mailing List

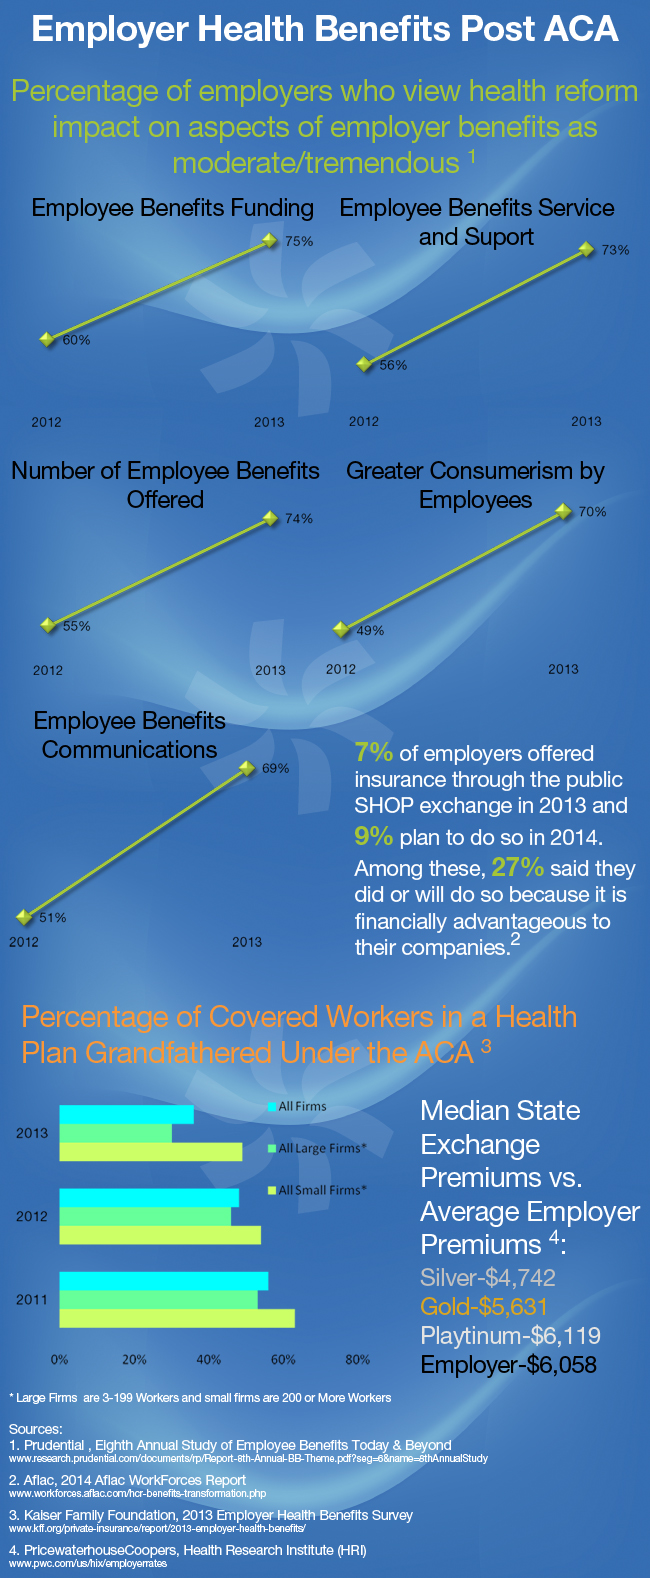
Household Telephone Status

By http://www.MCOL.com

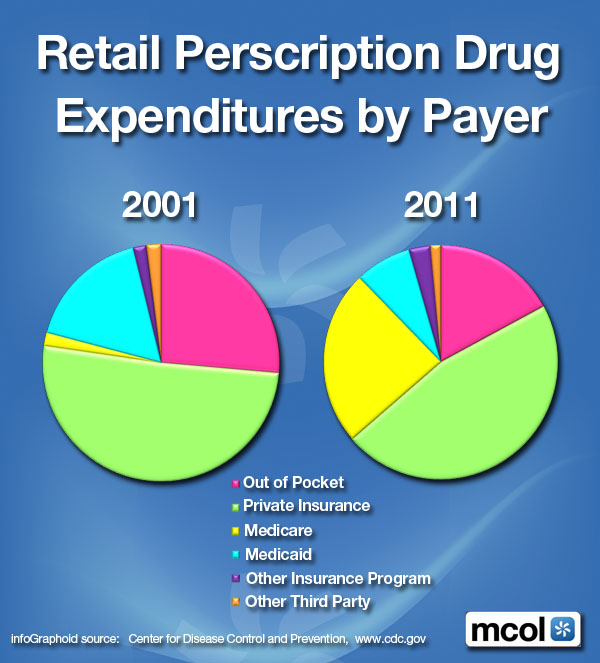
Tele Health

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

How Much Social Security Is Actually Taxed?

Join Our Mailing List

As much as 85 percent may be taxable

By Lon Jefferies  MBA CFP®

Lon Jefferies

If Social Security is your only source of income, it is unlikely that your monthly benefit is subject to taxation.

However, people like doctors and other medical professionals with substantial income outside of Social Security may have to pay federal income taxes on their benefits. In fact, it is possible that as much as 85 percent of your Social Security payout is taxable.

The Determination

To determine whether you are required to pay taxes on your benefit, the first step is to determine what the federal government deems your “combined income.” Your “combined income” is one-half of your Social Security benefit, plus all other income received during the year. Other income might include wages earned, capital gains recognized, dividends and interest collected, pension benefits received, and IRA funds distributed during the year.

Example:

For instance, consider a retired couple that receives an annual pension benefit of $20,000, takes an IRA distribution in the amount of $10,000, and receives $15,000 in Social Security benefits. This couple’s other income would total $30,000 (the pension and the IRA distribution). One-half of the Social Security benefit, or $7,500 would then be added to the other income to create a “combined income” of $37,500.

If a couple filing a joint tax return has a “combined income” of less than $32,000 ($25,000 for individuals), then all Social Security benefits are free of taxation. However, if the figure is between $32,000 and $44,000 ($25,000 and $34,000 for individuals), then as much as 50 percent of the Social Security benefit may be taxable. Further, if the “combined income” is greater than $44,000 ($34,000 for individuals), than as much as 85 percent of the Social Security payout may be taxable.

The “Combined Income” Threshold

So should couples do everything necessary to keep their “combined income” below $32,000 (the 50 percent threshold), or even $44,000 (the 85 percent threshold)? Fortunately, the tax system is progressive, meaning that just because a couple might fall in the bracket causing as much as 50 percent of their Social Security benefit to be taxable, not all of their benefit is necessarily taxed as such.

Example:

For instance, our sample couple with a “combined income” of $37,500 might be concerned that they are paying taxes on 50 percent of their Social Security benefit because that is the bracket they fall in. This would cause half of their $15,000 Social Security benefit, or $7,500, to be taxable. Fortunately, it is only the $5,500 of benefits received that pushes the couple’s “combined income” over and above the $32,000 threshold that is actually considered 50 percent taxable. As a result, only $2,750 (half of the $5,500 of “combined income” over the $32,000 threshold) of Social Security benefits is taxable. In this instance, the taxpayers are only paying taxes on 18 percent ($2,750/$15,000) of their Social Security benefits.

Getting Granular

Now suppose our imaginary couple received not $15,000 in total Social Security benefits, but $15,000 each, leading to a total benefit of $30,000. Assuming the same $20,000 pension benefit and $10,000 IRA distribution, the couple’s “combined income” would now be $45,000 (half of the $30,000 in Social Security benefits received plus the $30,000 of other income).

This provides another illustration of how the progressive tax system prevents higher-income taxpayers from feeling the need to do everything they can to get their “combined income” under the $44,000 threshold just to avoid the 85 percent bracket. First, a “combined income” of $45,000 clearly fills the entire 50 percent bracket of $32,000 – $44,000. Consequently, the entire $12,000 of Social Security benefits received within that range will be 50 percent taxable (or $6,000 of benefits received will be taxable). Additionally, another $1,000 of benefits over and above the $44,000 threshold will be 85 percent taxable, meaning another $850 of benefits are taxed. This means a total of $6,850 ($6,000 from the 50 percent taxable bracket, and $850 from the 85 percent taxable bracket) of Social Security benefits received will be taxable. Still, however, of the $30,000 of Social Security payments received by our couple, only 23 percent ($6,850/$30,000) ends up being taxable.

Taking this one step further, we can deduce that income outside of a Social Security benefit (the combination of pension benefits, IRA distributions, capital gains, etc) must be greater than $44,000 for there to even be a possibility that as much as 85% of a Social Security benefit would be taxable. If this other income portion of the “combined income” is less than $44,000, then at least some of our Social Security benefit will fall in the 50 percent threshold, if not the 0 percent threshold.

Benefits

The Calculations

Here is a useful calculator to determine the taxability of your Social Security benefit.

The point of this exercise is twofold. First, understanding the factors that may cause a Social Security benefit to be more or less taxable provides us with an advantage from a financial planning perspective. Second, it is important to realize that just because our “combined income” passes a threshold causing some of our Social Security benefit to be taxable doesn’t mean that the resulting tax liability is catastrophic.

Assessment

In fact, once realizing that the increase in tax liability from having some additional income is so inconsequential, some retirees may be more likely to spend and enjoy their retirement, which is the point of financial planning in the first place.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

Six groups that will shape mHealth apps of the future

Join Our Mailing List 

A Special ME-P Report

The Distinct Segment Publishers

By Ralf-Gordon Jahns and Markus Pohl

ralphmarkus


Introduction

Dr. Marcinko and ME-P Readers and Subscribers,

Did you know that mHealth app publishers can be grouped into 6 distinct segments?

Segments differ mainly by goals, business approaches and performance. Their desire to help others distinguishes them from the rest of the app community. Knowing these segments is a pre-requisite for all those who wish to successfully participate in the new mHealth app ecosystem.

The Publishers

So, who is behind the 100,000 mHealth apps published in today’s app stores? How do the publishers differ in terms of motivation, development tool usage and satisfaction about goals achieved? The mHealth app publisher segmentation distinguishes 6 groups of current mHealth app publishers. This segmentation is based on the results of themHealth App Developer Economics 2014study.

A deeper knowledge about the mHealth app publishers is essential to all health market participants who wish to successfully navigate inside the newly emerging mHealth app ecosystem.

mHealth app publishers are not like game or tool app developers. 46% publish apps, because they want to help others. They also have objectives like revenue generation or raising brand awareness, but this “altruistic” attitude clearly distinguishes them from the rest of the app economy.

Within the six mHealth app companies, publishers with a strong medical background and those who leverage existing app development tools & APIs seem to accomplish their goals better than those who do that to a lesser extent.

Traditional healthcare players like Pharma, Med-tech or insurance companies have not been able to define their role in the market yet. Established Healthcare Players are the only segment “mainly not” satisfied with their goal achievement.

These are the profiles of the 6 distinct mHealth app publisher segments:

1) Established healthcare players:

This group includes Pharma, hospitals, health insurance and Med-tech companies, representing 3.4% of the total number of app publishers. These players usually belong to the mHealth app publishers with > 5,000 employees. Their primary objective for being in the market is to raise brand awareness and they have published the largest number of mHealth apps. Nevertheless, average reach in terms of downloads is far below the market’s average. App publishers in this group are so far the least satisfied with the achievements in the mHealth app market. The usage of tools and APIs to improve the efficiency of the app development process and app monitoring as well as the value of the app is below its competitors.

2) App specialists:

App specialists are small companies, which typically hire 3-10 employees. They have entered the mHealth app market in order to benefit from its potential. They have an app developer background and are familiar with available development and support tools. The share of medical experts on board is relatively low. This group constitutes 14% of the mHealth app publisher community.

3) Helpers:

Helpers’ primary motivation for publishing apps is to help others and they are usually organized into small companies of 3-10 employees. Revenue generation is only a minor factor. Typically Helpers have already achieved or over-achieved their goals. In terms of downloads, they have the highest share of companies (61%) that achieved less than 5,000 downloads last year. Helpers represent 32% of the market.

4) Medical specialists:

Medical specialists leverage their medical know-how to develop mobile apps. Similar to the Helper group, Medical specialist have a large share of members who publish apps to help others. By far they have partly reached their goals. They have the highest share of companies, which in 2013 earned more than USD 1m with their mHealth app portfolio. They represent 20% of the market.

5) Fitness specialists:

This group of app developers represents around 10% of the total mHealth app developer community. They primarily develop fitness apps with a clear objective to generate revenue. They connect more often to medical databases and sensors and use app development tools above average. The usual company size is 11-100 employees.

6) Connecters:

This group of mHealth app publishers represents 18% of the total mHealth app developer community. Their strategy is to create value rich apps by enabling connection to other apps, sensors and databases. This group generates the highest average revenue and has the highest goal achievement level.

Apps

Assessment 

The mHealth app publisher segmentation is a snapshot of the current state of the market. It will change as segments become more important (medical specialists) or new groups appear.  One of the main questions will be if and how traditional healthcare players will be able to compete with these small and agile companies that are driving the market today.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

References:

Link to blog post:

http://mhealtheconomics.com/mhealth-segmentation-of-app-publishers-business-approaches/

Link to graph:

http://mhealtheconomics.com/wp-content/uploads/2014/05/research2guidance_mHealth_6_segments_business_approaches.jpg

Link to free report:

http://mhealtheconomics.com/mhealth-developer-economics-report/

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details

Product DetailsProduct Details

A 2014 Stock Market Mid-Year Review

Join Our Mailing List 

What Do We Know?

[A SPECIAL R&D REPORT FOR THE ME-P]

By Lon Jefferies MBA CFP®

Lon JefferiesIf you pay close enough attention to the news media you’ll eventually learn that much emphasis is placed on pundits’ forecasts, but very little consideration is given to how accurate the projections turn out.

When 2014 started, there were some pretty widely-accepted expectations regarding the investment environment. Let’s take a minute to review those anticipations and analyze how precise they turned out to be.

Interest Rates

One of the most universally accepted beliefs going into 2014 was that interest rates were on the cusp of rising, and that consequently, bond returns would drop. (Of course, this has been the expectation for around five years now, but that is a discussion for a later time.) Investors were questioning whether they should reduce or eliminate the bond portion of their portfolios until the rate increase occurred.

So, have we experienced the rise in interest rates we were expecting? On 1/2/14, the yield on the 10-year Treasury note was 3%. As of 6/30/14, the yield on the same note was 2.516%.

That’s right — interest rates have actually decreased over the last six months. Did those who stuck with their investment strategies and maintained their bond positions experience a decline in their portfolio’s value?

Here is how a variation of different bonds have performed year-to-date (as of 6/30/14):

  • US Government Bonds (IEF): 4.89%
  • US TIPS (TIP): 5.25%
  • Corporate Bonds (LQD): 5.37%
  • International Bonds (IGOV): 5.66%
  • Emerging Market Bonds (LEMB): 6.42%

Equities

How about the equities side of the portfolio?

In January, predictions for stocks were all over the map — some predicted a full out correction (a loss of more than -20%), some predicted that we would keep chugging along at 2013′s pace, and most predicted something somewhere in between. There were, however, many factors that were a common cause of concern.

So, was the reduction of the Fed’s Quantitative Easing a legitimate fear? In fact, this possibility has come to fruition. In December, the Fed was buying $85 billion per month of financial assets from commercial banks and other private institutions. The Fed has reduced this monthly amount during every meeting it has held this year, and that amount is now down to $35 billion per month. However, the key question is what impact has this had on the stock market.

Here is how a wide basket of equities have performed year-to-date (as of 6/30/14):

The most widely accept fear among equity investors was the phasing out of the Fed’s Quantitative Easing (QE) program. Investors worried that the Fed would begin lowering the amount of loans the government would buy from commercial banks each month, which would lower the availability of capital in the economy.

Historically, less money in the system leads to less investing in new businesses, less innovation, and fewer jobs created.

  • Large Cap Stocks (IVV): 7.08%
  • Mid Cap Stocks (IJH): 7.57%
  • Small Cap Stocks (IJR): 3.30%
  • Foreign Stocks (IEFA): 4.34%
  • Emerging Markets (IEMG): 4.70%
  • Real Estate (IYR): 16.09%
  • Commodities (DJP): 7.32%
  • Gold (GLD): 10.27%

Volatility

The last widely-held viewpoint at the beginning of the year was that 2014 was likely to be a year more volatile than anything we had experience in 2012 or 2013. There was a lot of clatter about valuations and PE ratios being too high, concern about the war in Ukraine, a consensus that China was about to experience a drastic decline in both imports and exports, and a general feeling that the market was due for a significant (if not healthy) pullback.

Additionally, how much have we heard about unfavorable weather patterns over the last six months?

Managing a Stock Portfolio

Lessons Learned

Of course, all of this is not to say that interest rates will never rise, that bond values will never decline, and that the market won’t return to the roller coaster it is.

In fact, all those things are certain to happen. Unfortunately, anyone who contends to know the uncertain part of this equation — when — likely doesn’t actually know anymore than you or me. For this reason, having and sticking to a diversified investment strategy that coincides with a detailed financial plan is the most likely path to financial success.

The most significant lesson inherent in these numbers is that market expectations are essentially useless. Near the beginning of the year, the vast majority of experts anticipated interest rates to rise, bond values to drop, and volatility to increase. Unfortunately, pundits making projections are rarely held to their inaccurate forecasts and are allowed to continue making a living showing they have no greater knowledge than the average investor.

Assessment

So, has 2014 been a wild ride?

The S&P 500 dropped by -5.51% from 1/22/14 – 2/03/14, and by -3.89% from 4/2/14 – 4/11/14. These are the only declines of more than 2% that the S&P 500 has experienced all year!

Additionally, as of 6/30/14, the S&P 500 has now gone 54 consecutive trading days without an up or down move of greater than 1%, the longest stretch since 1995! By historical standards, 2014 is considered to be a very smooth ride.

More:

Stock Market at New Highs!

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

Summer Tips for Physicians to Maintain their Vehicle

Join Our Mailing List

Keeping your luxury vehicle running smoothly with these Hot-Weather “tips and pearls”

[By Dr. David Edward Marcinko MBA CMP™]

[By Nalley Collision Center]

Dr. Marcinko

You and your car survived the harsh winter. Thanks to your preparation and careful driving, you stayed on the road and emerged from the thaw without incident. But, before breathing that sigh of relief and going on your way, make sure you know how to maintain your vehicle in the warmer temperatures with these tips and pearls.

Why? Warm weather can stress cars as much as the cold, so take steps now to prepare you and your car for the spring and summer by following these important tips.

Check the Climate Control System

Many doctors forget about their air conditioner while relying on the heater during the winter months. During that time, air conditioners can leak refrigerant and experience other mechanical failures without notice. Before getting caught without relief in the heat, take your car to your dealer for an AC checkup.

Inspect Windshield Wipers

During the winter, windshield wipers can stick to the windshield and tear before breaking free. Don’t let damaged wipers catch you off guard when the spring rains hit. Inspect your wipers and replace them if they look damaged or worn. If you need help with this, stop by your dealer for assessment, parts, and installation.

***

Jag

***

Inspect Tires

Your tires were fine before winter. Several months and possibly thousands of miles later, your tires may not be in such good shape now. Cold temperatures make the air inside tires shrink; that’s why you inflated your tires for winter driving. As the air warms, however, the air expands, often causing overinflated tires that can wear unevenly and prematurely. Check the tires on your car for proper air pressure and adjust them if necessary.

According to the National Highway Traffic Safety Administration, more than 3,000 deaths and 116,000 injuries between 2005 and 2009 resulted from tire-related problems. Don’t become part of those statistics.

Replace Air Filter

During the winter weather, salt and sand that are used to keep roads safe affect your car’s air filter. So, check it yourself or ask your dealer to check your air filter for signs of problems. By restoring free airflow into your engine, you can boost the fuel efficiency of your car by one-tenth or more. You will also improve acceleration, so take it easy on the gas.

Time for a Carwash

The melting snow, salt, and sand on winter roads covers your car and its undercarriage with a corrosive mixture, setting the stage for rust and marred paint. With winter weather past, take your car to the car wash for a thorough cleaning to prevent lasting damage from the winter. Better yet; wash it yourself. With some intentional care, you can keep your car looking great for a long time to come.

***

Jag console

***

General Inspection

The break between winter and summer is a great time to give your car a good once-over. Verify your registration and inspection stickers are up-to-date and that your insurance cards and all your paperwork are in order.

Also, check fluid levels for the oil, transmission, brakes, power steering, and windshield wash. If your car is due for scheduled maintenance, take it to your dealer now to have it done. Routine maintenance and prompt repairs will help your car beat the challenges of the heat.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details

The Dating and Money Conversation for Medical Students

Join Our Mailing List 

Honey, We Need to Talk … About Finances!

By Rick Kahler MS CFP® http://www.KahlerFinancial.com

Rick Kahler CFPWe are al aware of the student debt load crisis in this country.

But, one of the challenges at the beginning of a romantic relationship is having “the conversation” about an equally important issue for any couple: money.

Even more so for medical students, interns, residents, nurses, young doctors and medical professionals!

For example:

  1. What is okay to ask a potential partner about money, and when?
  2. How do you bring the subject up without seeming like a braggart, a coldhearted miser, or someone looking for a meal ticket?

There really ought to be some rules of etiquette for exploring this essential topic; something like, “by the sixth date, it’s appropriate to start undressing financially.” Unfortunately, we don’t have such guidelines.

The Money Minefield

Money is a topic fraught with emotional richness. In other words, it’s a minefield. Money is one of the top sources of conflict for couples, so if you’re dating, it’s crucial to learn a potential partner’s earnings, net worth, money habits, and financial beliefs. At the same time, talking specifically about money is so forbidden in our culture that we have no idea how to initiate a conversation about it.

Here are a few suggestions that might help:

1. Figure out your own money beliefs first. Before you even sign up with a dating site or accept your friend’s offer to set you up with her brother-in-law’s second cousin, think about what you want and need financially from a partner. Do you care if someone’s net worth is much higher or lower than yours? Is a certain level of debt a deal-breaker? What lifestyle are you comfortable with?

2. Tell before you ask. Begin with appropriate self-disclosure, in small steps, about your earnings, your long-term financial goals, or your beliefs about debt or spending. See how potential partners react. If they don’t disclose in turn, seem very uncomfortable with the conversation, or have beliefs or money habits much different from yours, you may be seeing red flags.

3. Observe. Watch how people handle money. Are there any patterns around spending or the use of credit cards that seem to indicate either overspending or excessive frugality? Do they throw cash around, or do they leave restaurant tips that Ebenezer Scrooge would be proud of?

Does someone’s home show signs of hoarding or stinginess? (A candlelight dinner of takeout Chinese at a card table is one thing for college students, but quite another for middle-aged professionals.) Do their cars or houses seem poorly maintained? Does their lifestyle seem more lavish than the typical earnings in their career field would support?

4. Listen. Despite the taboo on talking directly about money, we indirectly reveal a lot about our money beliefs by what we say. Notice how dates talk about saving or spending. Do they seem worried about money or reluctant to spend it even on basic needs? Do they seem angry about money or resentful of successful people? Do they boast about financial successes, things they own, or get-rich-quick schemes?

5. Ask. Even if everything else is all moonlight and roses. When you meet someone who seems like “the one,” don’t set aside everything that matters to you about money. Instead, remember how important this issue is to the long-term health of a relationship. Even if you can’t do it gracefully, ask the money questions. Talk frankly about debt, spending, saving for retirement, and each other’s expectations around lifestyles and careers.

Dating Currency

Assessment

Being the one to initiate that difficult money conversation doesn’t mean you’re coldhearted, unromantic, or greedy. It simply means you recognize that money is too important a topic to ignore. When we enter into a romantic relationship, it’s tempting to think that love means not having to talk about money. In truth, love means having the courage to talk about money.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

  Product Details

***

Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™8Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

***

Invite Dr. Marcinko

***


State Requirements for Individual Market Benefit Design and Cost-Sharing

Join Our Mailing List

For Health Benefits

By http://www.MCOL.com

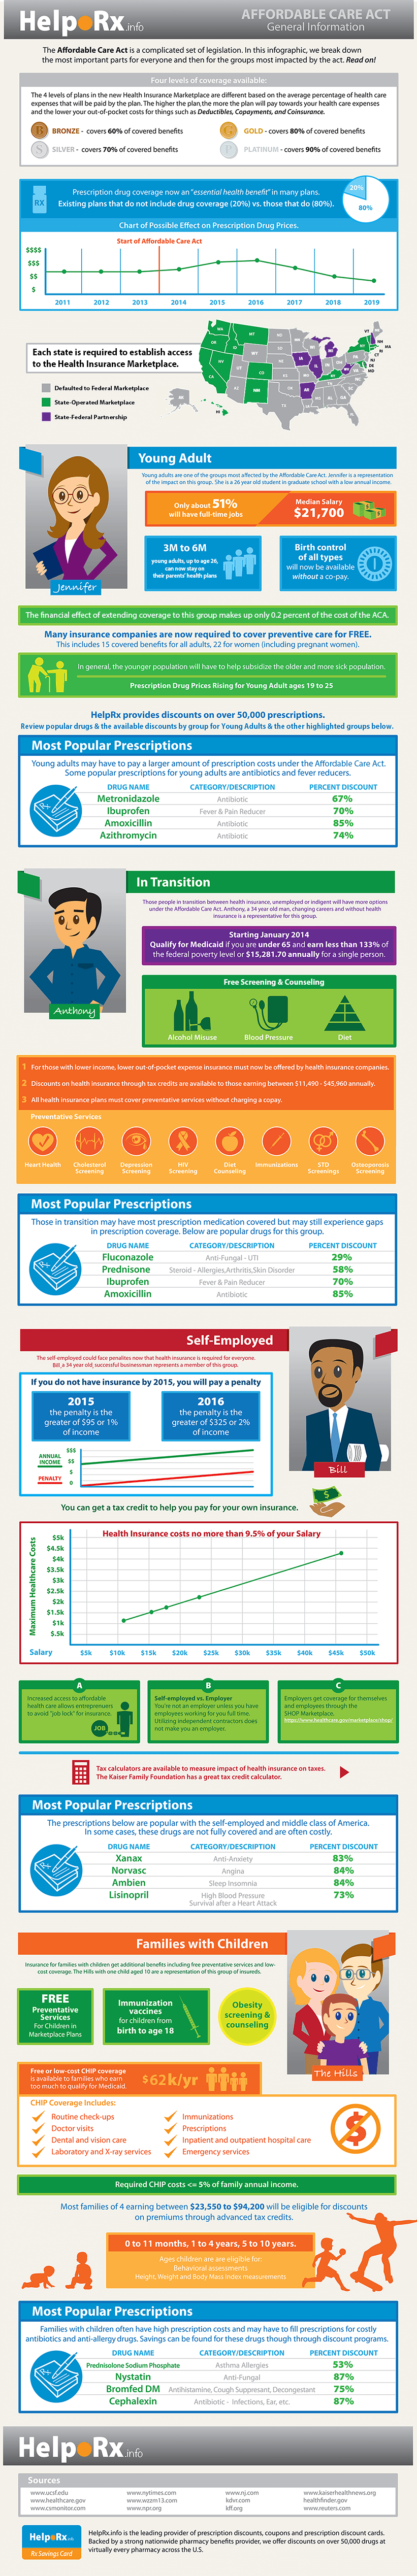
ACA State Requirements

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details


Understanding Healthcare Employment Benefits that are NOT Taxed at Full Economic Value

Join Our Mailing List 

On Entirely Legal AUTOMOBILE Employment Fringe Benefit Strategies 

[By Perry Dalessio CPA]

perry-dalessio-cpaWhen an employment fringe benefit does not qualify for exclusion under a specific statute or regulation, the benefit is considered taxable to the recipient.  It is included in wages for withholding and employment-tax purposes, at the excess of its fair market value over any amount paid by the employee for the benefit.

Examples:

For example, hospitals often provide automobiles for use by employees. Treasury regulations exclude from income the value of the following types of vehicles’ use by an employee:

  • Vehicles not available for the personal use of an employee by reason of a written policy statement of the employer
  • Vehicles not available to an employee for personal use other than commuting (although in this case commuting is includable)
  • Vehicles used in connection with the business of farming [in which case the exclusion is equal to the value of an arbitrary 75% of the total availability for use, and the value of the balance may be includable or excludable, depending upon the facts (Treas. Regs. § 1.132-5(g)) involved)]
  • Certain vehicles identified in the regulations as “qualified non-personal-use vehicles,” which by reason of their design do not lend themselves to more than a de minimus amount of personal use by an employee [examples are ambulances and hearses].
  • Vehicles provided for qualified automobile demonstration use
  • Vehicles provided for product testing and evaluation by an employee outside the employer’s work place

If the employer-provided vehicle does not fall into one of the excluded categories, then the employee is required to report his personal use as a taxable benefit. The value of the availability for personal use may be determined under one of several approaches.

jag346_SWHT

Assessment

Under any of the approaches, the after-tax cost to the employee is substantially less than if the employee used his or her own dollars to purchase the automobile and then deducted a portion of the cost as a business expense.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

The World Cup LifeStyle

Join Our Mailing List

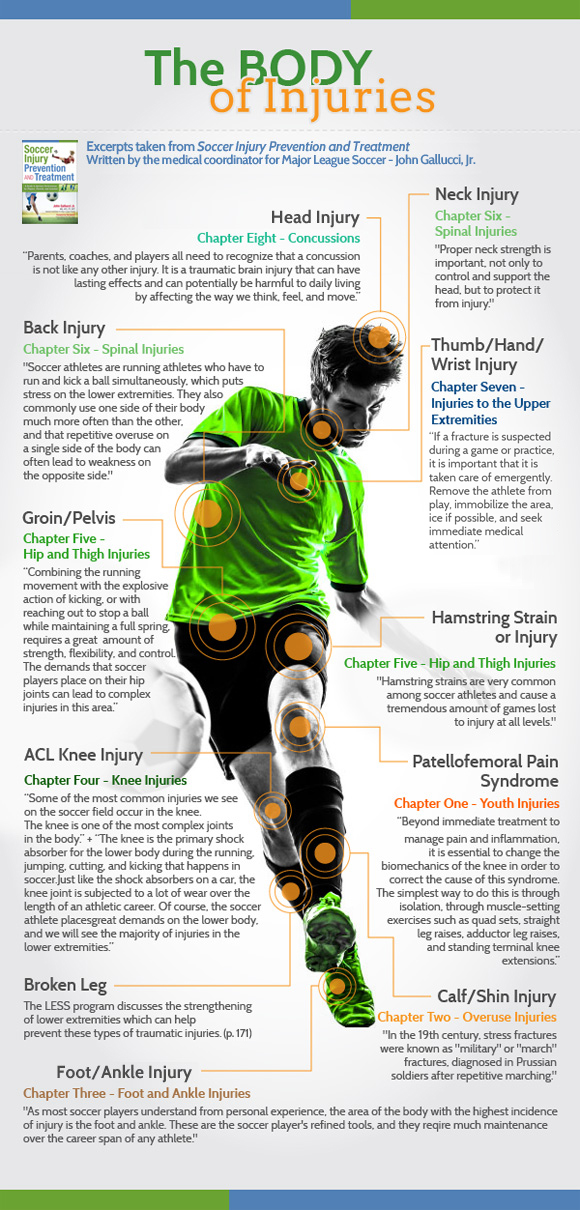
The Body of Injuries

[By Dr. David Edward Marcinko MBA]

[By Springer Publishers]

Did you know that this ME-P has a leisure and lifestyle vertical? Maybe; maybe not! So, with the publication of this info-graphic on the World Cup soccer matches; we invite all readers and subscribers to submit their own hobby activities.

1

2

3

4

5

Assessment

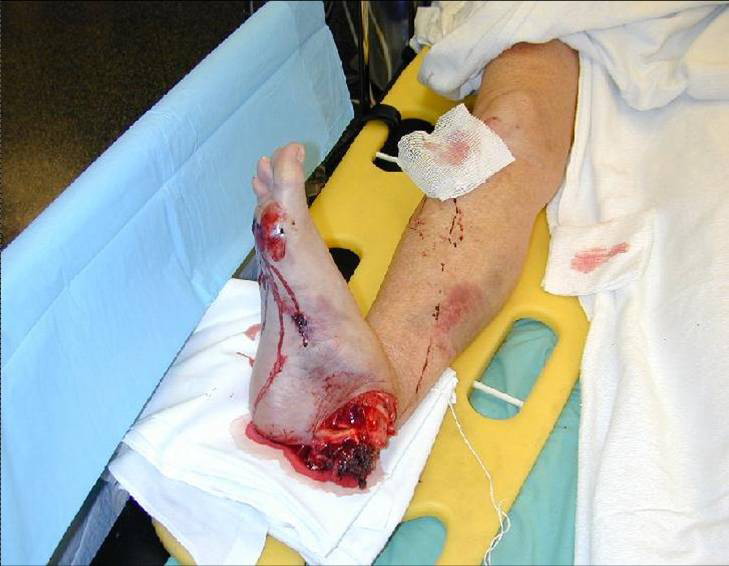
Ankle-Leg Trauma

[Copyright Dr. David E. Marcinko, and iMBA Inc. All rights reserved]

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Understanding Some Common Portfolio Payout Methods

   Certified Medical Planner

By Dr. David Edward Marcinko MBA CMP™

Recognizing the risk that market volatility represents to long-term portfolio health, investment accounts and endowment funds utilize a variety of methods to calculate periodic payouts.

  • Investment Yield: An investment portfolio using this method spends only its dividends and interest and re-invests any unrealized and realized gains. There would appear to be two primary disadvantages of this method. First, the payout amount will be extremely volatile as yields on equity and fixed income investments fluctuate. Second, the endowment manager could be encouraged to adopt a short-term focus on yield to the detriment of purchasing power preservation.
  • Percentage of the Prior Year’s Ending Market Value: An endowment using this method would withdraw some fixed percentage of the prior year’s market value. As with the Investment Yield method, disbursements from the endowment can be somewhat volatile under this method.
  • Moving Average: This approach, which is most common among educational institutions, generally involves taking a percentage of a moving average of the endowment market value. The percentage commonly approximates 5% over a 3-year period.
  • Inflation Adjusted: This portfolio method simply adds some factor to the applicable rate of inflation for the institution or investor.
  • Banded Inflation or Corridor: This account method is similar to the Inflation Adjusted method except that it establishes a corridor or band of minimum and maximum increases in an attempt to limit the volatility of the disbursement amounts.

payout

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Happy Independence Weekend

Happy Independence Weekend Greetings to our Readers and Subscribers for 2014

From the Medical Executive-Post

***

Product DetailsProduct Details

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details

How Doctors Select a Cloud Services Provider?

Join Our Mailing List

The Top Ten [10] Factors to Consider

By http://www.MCOL.com

cloud

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Are You Addicted to Your Smartphone-Doctor?

Join Our Mailing List 

Changing the Way we Communicate

[By An Anonymous Physician]

Anonymous DoctorRemember the old on-call beeper system?

Well, smartphones have changed the way people communicate. In fact, I do not know a single doctor, nurse or healthcare professional that does not have one. They let you quickly stay in touch with patients, the hospital, ER or medical clinic through calling, texting, emailing, or social networking tools.

But, a smartphone is also much more than a communication device. There are apps that help you manage your life, learn about the world around you, or simply keep you entertained. It’s easy to see why users are so impressed with their new tech, but can it go too far?  So, how do you know if you’ve become addicted to your smartphone?

Here are a few indicators of concern:

It’s Always With You

One of the first steps to spotting an addiction is assessing how often you use your smartphone and how you feel when it’s not glued to your hand or resting in your pocket. Do you get nervous when your smartphone is out of sight or sitting more than an arm’s length away? Can you leave your phone in another room while you sleep, take a shower, or get dressed? You have voice mail for a reason, and it’s okay to occasionally be unreachable.

You Can’t Wait Without It

Without a doubt, a smartphone makes it easier to pass the time while waiting. You can play a game, read a book, check your email, or even catch up on some work. That’s great for sitting in your own doctor’s waiting room, but it shouldn’t become a need for the brief moments of downtime that crop up during your day. If you can’t wait two minutes for a cashier to ring up your groceries without pulling out your smartphone, you might have an addiction.

It Tracks Your Every Move

Smartphone apps often help you become more productive. You can monitor your diet and exercise, pay your bills and create virtual to-do lists. However, it’s easy to take this too far. You might have an addiction if you feel like you can’t eat, sleep, exercise, or go to the bathroom without logging it on your smartphone. (Yes, there are apps for all of that!)

You Call or Text People in the Same House

It’s easy to see how smartphones can help families stay in touch. But do you really need to text your kids when it’s time to come downstairs for dinner? Your family plan might make it free to call and text within your immediate family, but that doesn’t mean you need a fancy device to communicate when you are actually in the same house.

You Choose Your Phone Over Live Company

A smartphone can be great company when you’re bored and have some time on your own, but is it really better company than your actual friends? Twiddling with your smartphone while attempting to simultaneously carry on a face-to-face conversation is not multitasking! It’s just plain rude.

***

Phone MD

***

Assessment

I am not a psychiatrist by training, but if you find yourself frequently playing with your phone during social gatherings, there’s a pretty good chance that you may have a problem.

If you think you may be addicted to your smartphone, try taking a break from it. Put down the phone and give living, breathing people a chance. You will soon see that the world can be a fascinating place, even without augmented reality.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Does the Summer Sun Damage your Luxury Vehicle’s Paint Job?

Join Our Mailing List 

Protecting your vehicle from the effects of sunlight

[By Dr. David Edward Marcinko MBA CMP™]

[By Nalley Lexus Roswell, GA]

Dr. DEMSunlight is dynamic. It keeps us warm, allows plants to grow, and can even be converted into electricity.

Unfortunately, sunlight has an equally harmful side on human skin. As a result, the ultraviolet rays in sunlight, also known as UV rays, can burn unprotected skin and blister it. This is well known by doctors, especially plastic surgeons, dermatologists, you and me.

UV Damage

But, did you know that UV rays can seriously damage the paint on your luxury car or truck, too? Yes – it’s true.

During the warm weather seasons, exposure to UV rays actually breaks down the molecules that give your vehicle’s paint its color and shine. Though modern automobile paint includes additives to resist these effects, the paint’s effectiveness only lasts for a limited time period. So, when a car spends much of its life entrenched in sunlight, its paint will gradually fade and become dull.

Temperature too!

While sunlight is harmful, temperature can be a problem, as well. When a car sits out in the fierce midday sun, it gets hot and its body panels expand. Such expansion causes the paint to contract at a microscopic level, which may ultimately crack your car’s paint or dry out and crack leather seats. Over time, the gradual effects of the sun’s heat diminish your car’s gleaming showroom finish. As the sun is ubiquitous, it may seem as though sun damage is inescapable.

However, it is possible to extend the life of your car’s paint job by following these tips.

***

My Jaguar

***

Tips and Pearls

Seek shade

Whenever possible, keep your ride out of sunlight. Park in a covered garage or use a car cover for an immediate solution. You may also park your car under the shade of a tree for a short period of time, but it is important to remember that tree sap and bird droppings can also damage your paint finish.

Wax

Modern vehicles are finished with a layer of “clear coat” over the actual paint color. This gives the paint its deep gloss and helps protect the pigment from UV rays, however it doesn’t last forever. Regular waxing provides additional protection for your car, filling in cracks that form as a result of sunlight exposure.

A simple way to see if your car needs waxing is by performing the water beading test. To perform this test, drip water onto your paint. If the water forms beads on the paint surface, your car is perfectly waxed. However, if the water spreads on the paint surface, your car is in need of a new wax job.

***

My Jaguar XJ-V8

***

Assessment

As a classic British Jaguar XJ-V8-L sedan aficionado; can you think of any more ways to protect my car, and your car, from the sun?

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details

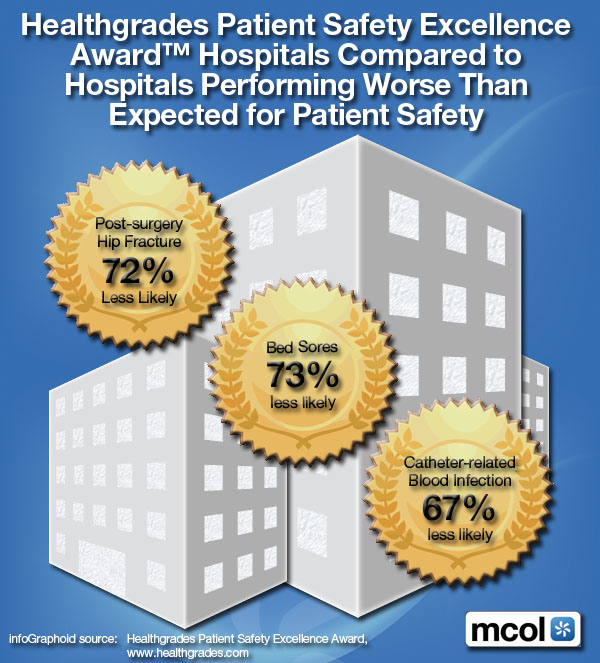
Healthgrades™ Patient Safety Award

Join Our Mailing List

Hospitals Compared to Hospitals Performing Worse than Expected for Patient Safety

By http://www.MCOL.com

dem

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Is the CFP-BOD, and the CFP® mark, in Jeopardy? [VOTE]

Join Our Mailing List

Early CFP® Board Leader Says Future of Certification in Jeopardy

[By Staff Reporters]

The CFP® Board’s strategy of punishing some certificate holders over compensation disclosure issues in what critics charge is an arbitrary manner threatens the future of the CFP® designation, according to one of the early leaders of the board who also chaired its disciplinary commission.

Please vote

And so, we ask this question.

Assessment 

Link: http://www.financial-planning.com/news/early-cfp-board-leader-says-future-of-certification-in-jeopardy-2686698-1.html?ET=financialplanning:e14975:86235a:&st=email&utm_source=editorial&utm_medium=email&utm_campaign=FP_Weekend__092713

Read More:

Read even more:

2016 Update:


Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

DICTIONARIES: http://www.springerpub.com/Search/marcinko
PHYSICIANS: www.MedicalBusinessAdvisors.com
PRACTICES: www.BusinessofMedicalPractice.com
HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731
CLINICS: http://www.crcpress.com/product/isbn/9781439879900
BLOG: www.MedicalExecutivePost.com
FINANCE: Financial Planning for Physicians and Advisors
INSURANCE: Risk Management and Insurance Strategies for Physicians and Advisors

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product DetailsProduct Details

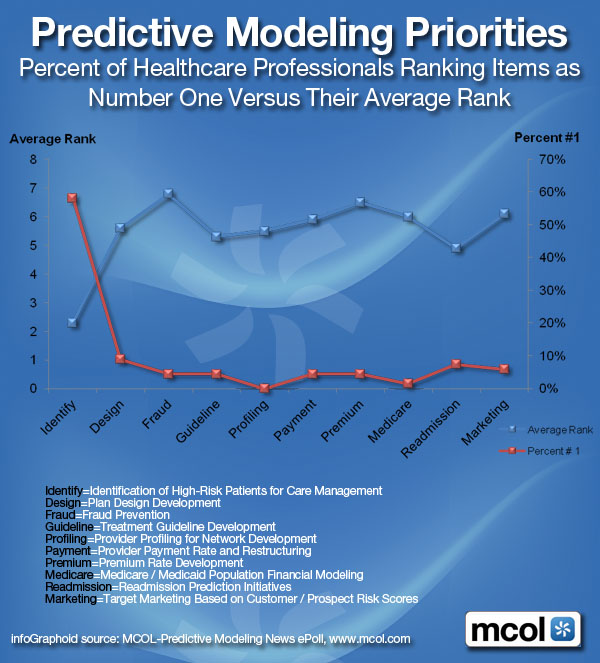
A Look at Predictive Health Care Modeling Priorities

Join Our Mailing List

Healthcare Professional Rankings of Average Risk

http://www.MCOL.com

PM

Definition 

According to Wikipedia,predictive modelingis the process by which a model is created or chosen to try to best predict the probability of an outcome. In many cases the model is chosen on the basis of detection theory to try to guess the probability of an outcome given a set amount of input data, for example given an email determining how likely that it is spam.

Models can use one or more classifiers in trying to determine the probability of a set of data belonging to another set, say spam or ‘ham’.

Assessment

Nearly any regression model can be used for prediction purposes. Broadly speaking, there are two classes of predictive models: parametric and non-parametric. A third class, semi-parametric models, includes features of both.

Parametric models make “specific assumptions with regard to one or more of the population parameters that characterize the underlying distribution(s)”, while non-parametric regressions make fewer assumptions than their parametric counterparts.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

How Much Money Do You Make – Doctor?

Join Our Mailing List

Ruminations on the Last Taboo!

By Rick Kahler MS CFP® http://www.KahlerFinancial.com

Rick Kahler CFP“How much money do you make?”

We don’t ask people, let alone doctors and medical professionals, that question; but we’d love to know the answer.

In this country, we’re fixated on a person’s annual income. That’s the primary measure we use to determine social status and define success.

Income Qualifier?

Income also is the qualifier for government welfare programs. It defines people as poor, middle class, or rich. And, of course, it determines how much of your income the government will take. The more you bring in, the higher the percentage of your earnings you will pay in federal, state, and local taxes.

Income as a Poor Indicator of Net Worth

While we project a lot of things onto someone’s income, most of what we project is untrue. Income is not the best indicator of a person’s wealth or net worth.

Examples:

Last year Dr. Brent’s tax return showed an adjusted gross income of $20,000. Dr. Bill’s was $2 million. Who is richer? Most people would say Bill. The US and state governments also would say Bill. Actually, Brent is far and away the wealthier of the two.

Why and How?

Consider these two real-life examples:

  • Dr. Bill lives in New York, New York, which has both high property taxes and a city income tax. Paying city, state, and federal income taxes, plus property taxes on his luxurious home, takes around half of his salary. With take-home pay of about $1 million, Bill spends $1.2 million a year on his mortgage payments, college and private school tuition, and his lifestyle. He overspends his net income by $200,000 a year. He owes more on his condo than it’s worth, and he has significant credit card debt. When you total his assets and liabilities, he has a negative net worth of $1 million. He has managed to hold everything together so far, but technically, Bill is bankrupt.

Jaguar XJ

  • Dr. Brent lives in Rapid City, South Dakota. He is retired, owns a modest home which is paid for, and lives on about $40,000 a year. He didn’t pay any income taxes last year, partly because some of his income is from tax-free municipal bonds and mostly because he wrote off a large investment loss which left him with $20,000 of adjusted gross income. Brent has no debt. His net worth is $5,000,000.

Steering Jaguar

The truth is that what people make tells us very little about whether they are rich or not. In these examples, judging from income alone, it would be easy to reach the inaccurate conclusion that Bill must be far wealthier than Brent. His lifestyle is certainly more lavish—which of course is part of the reason he isn’t wealthy.

Many people who have high incomes but are heavily in debt might have lifestyles lower than others who make significantly less but have no debt. It’s not uncommon that people with high incomes choose to live a lifestyle that is far below what they could afford. In fact, this is one of the best ways to build real wealth.

The Income Non-Indicator

Income is a poor indicator of whether someone is rich. Even more important, it’s a poor indicator of how they handle money. I once worked with a family with an annual income of around $5 million who had a net worth of minus $3.5 million. They may have looked like “millionaires,” but they were not.

On the other hand, I work with many clients who have annual incomes around $100,000 a year, spend $60,000 a year, and are worth $2 to $5 million.

Assessment

The bottom line is that wealth is defined by net worth, not income. A high income doesn’t equal wealth; it equals a better opportunity to build wealth. Not everyone is wise enough to take advantage of that opportunity.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

“Retirement Investors Flock Back to Stocks”

Join Our Mailing List 

WSJ Front Page Headlines

[By Rick Kahler MS CFP® http://www.KahlerFinancial.com]

Rick Kahler CFP“Retirement Investors Flock Back to Stocks” was the front page headline of The Wall Street Journal on May 2, 2014.

I retweeted it to my Twitter feed, adding, “Just In Time to Ride Them to the Bottom Again.”

Introduction

Five years ago some of those same investors were abandoning stocks in sheer panic. In early March 2009, the Dow Jones Industrial Average hit a low of 6700. Many financial advisors spent hours listening to frightened clients wanting to sell out their entire portfolios and go to cash. It was an exhausting and traumatic period for doctors, financial advisors and clients.

Calm and Steady

Those who followed advisors’ recommendations to stay the course certainly came out on top. Their portfolios recovered nicely, with double-digit annualized returns for the past five years. Even over the past 10 years, most diversified portfolios earned very respectable returns far in excess of bank CD’s or bond yields.

Panic and Fear

Unfortunately, those who panicked and sold out paid an incredibly high price for the momentary relief of getting off the market roller coaster. Many of them kept their money on the sidelines until recently, waiting until “things were better” to reinvest.

Today-Bubbles?

Apparently that time has come. Here are some numbers from the WSJ article:

Retirement investors have recently increased their stock holdings by almost 40% from the market lows. Today, bond and money market funds make up only 25% of retirement plans, and 67% of new 401(k) contributions go toward purchasing stocks.

In 2007, bond and money market funds accounted for 21% of retirement plans. At the market top in October 2007, the average new 401(k) contribution going into stocks was 69%. Within 18 months stocks had declined almost 60% from their highs.

Correlations?

Do you see any potential correlations here? I have little doubt these individual investors, mistiming the market once more, are setting themselves up to get slaughtered all over again.

But, what about those who did get out of the markets five years ago and now realize they made a big mistake? Suppose you’ve learned the wisdom of staying in the market with a well-diversified portfolio. How do you get back in without waiting for the next crash?

Three Strategies:

Here are three strategies to rebuild your portfolio.

First, don’t go all in, but move into the market gradually with “dollar cost averaging.” Over the next two years, methodically (monthly or quarterly) buy into a diversified mixture of asset classes. If the market turns downward, which carries a high probability, you will buy into a falling market. You will also reduce the possibility of a huge market drop that might cause you to panic and sell out again.

Second, allocate your purchases to a mixture of US and international stocks, as well as options such as real estate investment trust (REIT) funds, commodity funds, managed futures funds, Treasury Inflation Protected (TIPs) bond funds, high yield bond funds, and high quality bond funds.

Finally, once your two-year dollar cost averaging is done and you are fully invested into your asset classes, rebalance at least once a year to maintain your original allocations as the values of the assets change.

For example, if you have allocated 30% of your portfolio to stocks, purchase more if stocks add up to less than 30% or sell some if they are over 30%.

Bull markets

Assessment

The research suggests there is a high probability that things will end badly for individual investors who try to time the markets. A few will succeed, but will confuse their “skill” with the fact they just got lucky. A methodical approach, however, provides a strategy to help you hold on, even in the face of market ups and downs.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details

FOR SALE: Physician E-mail Lists with NPI Numbers

Join Our Mailing List

Sensitive Data for Sale

[By Dr. David Edward Marcinko MBA]

Dr. DEMI received this email recently. Are you as incensed over it, as I? OR, am I being overly sensitive? Feel free to call or email John Edward, the sender, to tell him what you think: pro or con?

Hi ME-P,

I’m writing to check if you would be interested in reaching Physicians or Healthcare Executives?

We at AccurateB2Blist maintain a permission passed email list for physician practitioners with NPI numbers.

Our Lists

Below given are few additional lists we maintain within Medical Industry

  • Nurses
  • Dentists
  • Veterinarians
  • Healthcare Executives Email List
  • Physicians – Offices and Clinics of Doctors of Medicine
  • Physicians – Offices and Clinics of Doctors of Osteopathy
  • Doctors, Physicians and Surgeons Email List with NPI Number

Healthcare executives: 518,900 out of which 123,200 contacts are senior management level contacts.

Assessment

Please let me know if you would like to discuss further on your target audience? Looking forward to hearing from you. And, please do not print this email unless it is absolutely necessary. To opt out reply with ‘Leave out’ in the subject line!

By John Edward [Business Development Executive] AccurateB2Blist

+1951-373-6718

For Sale

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details

A Word on Automobile Cabin Air Filter Maintenance

Join Our Mailing List

Not Just for Physician-Allergists

[By Dr. David Edward Marcinko MBA CMP™]

DEM 2013Cabin air filtration is easily the most forgotten automobile maintenance item in passenger or luxury cars.

Since their introduction in roughly the early 1990s, more and more cars are equipped with cabin air filters – from a sub-compact to a full-sized luxury car, nearly all cars available in North America now come equipped with them and thus there’s a pretty good chance your car is equipped with one, and a fair to middling chance that it needs replacement.

Now is the time to Inspect

So now, following pollen, grass and hay-fever, season, is a great time to learn more about your cabin air filter. Cabin air filters tend to be buried deep within the dashboard of your vehicle, where the heating, air conditioning and ventilation system are located. They are usually about the size of a standard sized sheet of computer paper, and can vary in terms of material, most common being a cellulose mesh.

The cabin air filter is responsible for removing particulate from the air, which can include a whole litany of things you don’t want to be breathing; diesel exhaust, rubber particles, pollen, dust and general air pollution among other things.

***

00t0t_3LK6BwGPBcB_600x450

***

Since the air entering the car through the heating and air conditioning system has to pass through the cabin air filter, the filter can get clogged quite quickly depending on environmental conditions, and a clogged cabin air filter drastically reduces the overall effectiveness of your HVAC system as it struggles to get air flow that a clean cabin air filter would provide.

Other excellent reasons to change your cabin air filter, besides better circulation, include fresher smelling air and fewer allergens entering the cabin. Many cabin air filters accumulate leaves and other debris that your car winds up ingesting which can lead to musty or stale odors. Ultimately, switching out your cabin air filter is a small expense that keeps you from inadvertently sneezing months later.

***

DEM's Jaguar

***

As your cabin air filter is “out of sight, out of mind”, it’s definitely a good idea to get in the habit of having it inspected and replaced regularly. What are the right intervals for you? It all depends where (and how much) you drive. It’s a small and affordable maintenance item that will ensure you have many miles of driving comfort ahead.

More:

Assessment

I replace the cabin filter in my classic 2000 Jaguar XJ-V8-L touring sedan each Spring. What about you?

***

filter

[Cabin Filter]

***

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

Product Details

Stock Market at New Highs!

Join Our Mailing List 

Is this a Bubble?

[A SPECIAL R&D REPORT FOR THE ME-P]

By David K. Luke MIM, MS-PFP, CMP™ [Certified Medical Planner™] http://www.networthadvice.com

David K. LukeThe market news has been replete with the phrase “new market high“ in the business news every couple of weeks as of late. The corresponding message is often that the stock market is likewise in a bubble. The S&P 500 index and the Dow Jones Industrial Average index are at all-time highs. The indexes have surpassed the 2007 peak.

The reality is however that the S&P 500 is up less than 6% from the beginning of the year, and the Dow is up about 2%. Most investors, of course, do not invest just in these two indexes, as these two indexes represent very large capitalized companies.

I am reminded of the customer in 1995 when I worked at a national brokerage firm that called me to liquidate his entire stock portfolio. “The stock market was too high,” he said. He was 5 years too early.

Risk Mitigation

Most investors will have a diversified portfolio that includes mid-cap stocks, small-cap stocks, and international stocks as well as large cap stocks such as found in the S&P 500.

Of course, these equity investments are also typically subdivided into the broader categories of “Growth” and “Value.” Which means most investors that believe in diversification will own four different “types” of stock, each divided into two different categories for eight different baskets of stock if you will. The typical daily news will focus only perhaps on the S&P 500, which is a portfolio of large capitalized growth stocks. This is only one of the eight different types of stock that an investor would typically own.

  Product Details

In strong bull markets, typically all eight categories of stock go up together with some degree of correlation. This is also true in strong bear markets with all eight categories of stock going down in some degree of correlation. Portfolio managers typically try to offset high correlation of investments by owning investments in asset classes that typically do not all correlate together. This is a major technique used to reduce the volatility in an account.

However as you can see so far this year, most all of the eight stock indexes with the exception of small-cap growth are up slightly in line with the S&P index.

***

[As of June 13, 2014] 

Name Ticker % Total Return YTD % Total Return 12 Month
Large Cap iShares S&P 500 Growth IVW 5.59 22.55
iShares S&P 500 Value IVE 5.76 18.39
Mid Cap iShares S&P MidCap 400 Growth IJK 2.69 18.24
iShares S&P Mid-Cap 400 Value IJJ 7.66 23.19
Small Cap iShares S&P Small-Cap 600 Growth IJT -0.52 20.8
iShares S&P Small-Cap 600 Value IJS 2.3 21.37
Foreign Large Blend iShares Core MSCI EAFE IEFA 3.75 19.25
Barclays Aggregate Bond Index iShares Core US Aggregate Bond AGG 3.26 2.39

Source: Morningstar

***

Inflation

The buying power of the US Dollar has changed over the years. The Consumer Price Index (CPI), a common measure of inflation, has averaged around a 3% annual increase from 1913 – 2014 according to the U.S. Department of Labor Bureau of Labor Statistics.

In fact, an item purchased for $5.00 in 1913 would have a cost of $119.73 today, or a cumulative rate of inflation for the past 100 years of 2,294.7%. The cost of living rising each year is a safe bet. Inflation has increased every year in the past 50 years with one exception: 2009 when inflation fell -0.4%.

Product Details

Update: 06/17/2014 04:10 ET

[Market Update]
Symbol Last Change
DOW 16,808.49 +27.48
NASDAQ 4,337.23 +16.13
S&P 1,941.99 +4.21

Conclusions:

  1. The Market Indexes at new highs does not indicate a bubble. In fact, the market should, relatively speaking, regularly be hitting new highs because of the consistency of positive inflation. Prices of goods and services today are at all-time highs. Does that mean we are in an “inflation” bubble? No. This is normal.
  2. The S&P 500 is not an accurate measure of the US economy. While the S&P 500 is the common “market” indicator in the US, only about 55% of the earnings of the index come from the US. (Source: RBC Capital Markets Research, Capital IQ 2012). This is because mainly large multinational companies such as Google, IBM, and Apple that have a significant amount of overseas revenues weight the index.
  3. The S&P 500 or the Dow Jones Industrial Average (DJIA – 30 stocks) is most likely not an exact reflection of your personal stock portfolio, which would expectantly be more diversified. A typical well-diversified long-term investment portfolio would include not just large cap stocks (such as found in the S&P 500 or DJIA), but mid, small, and international stocks from the growth and value camp, as well as a diversified bond holding.
  4. Overpriced stocks, just like overpriced real estate, are more prudently ascertained by value measures, not simply by raw index numbers. A stock hitting new highs could still be quite undervalued. Meaningful variables such as earnings growth, price to earnings ratio, dividend yield, price-to-book, price-to-sales, and other metrics should be considered.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

On m-Health App Therapeutic Business Potential

Join Our Mailing List

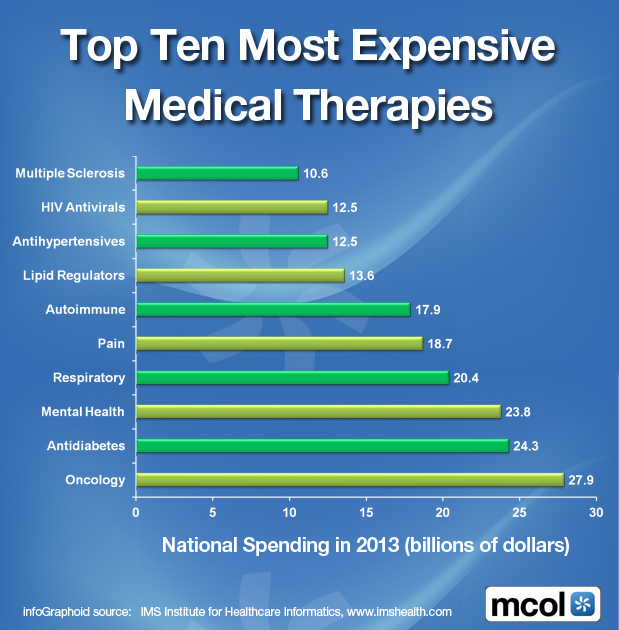
Top Ranked Therapy Areas

By http://www.MCOL.com

mHealth Publishers

Related:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

How EMR Vendors Mis-Lead Doctors [Part 2 of 2]

Join Our Mailing List

A SPECIAL ME-P REPORT

Practical “Tips and Pearls” from the Trenches

[Part Two]

By Shahid Shah MS http://www.healthcareguy.com

Shahid N. ShahAs your practice’s CIO it’s your job to challenge the vendors’ assertions about why you need an EMR, especially during the selection and production demonstration phase.

The most important reason for the digitization of medical records is to make patient information available when the physician needs that information to either care for the patient or supply information to another caregiver.

Electronic medical records are not about the technology but about whether or not information is more readily available at the point of need. In no particular order, the major reasons given for the business case of EMRs by vendors include:

  • Increase in staff productivity
  • Increase of practice revenue and profit
  • Reduce costs outright or control cost increases
  • Improve clinical decision making
  • Enhance documentation
  • Improve patient care
  • Reduce medical errors

Let’s tackle each potential benefit and see how they can be realized or left unfulfilled based on how a practice uses the technology solutions available to it. While thinking of the benefits, keep in mind that all automation solutions have voracious appetites for data entry and information. If you do not enter the data (either manually, through scanners, or integration with external systems) the value of the solutions cannot be realized. That’s why it’s crucial to consider how much time and effort you’d like to invest in data entry and if you’re not willing or able to take the time to enter the data into the system then the system is not going to work for you.

Increase in staff productivity

The first benefit often cited by vendors is improvement of your staff’s productivity. In a well-designed and properly implemented solution, an EMR can reduce the amount of time it takes for staff to locate records and find particular information about patients as well as generally conduct their tasks in a more efficient manner. However, actually achieving productivity improvement is much more difficult than vendors often make it sound. This is because the actual improvement in productivity is directly related to the amount of detailed data that is collected for patients across the entire practice workflow. Unless your practice has identified all or at least most major workflow steps and has created appropriate automation steps is unlikely that your productivity improvement will match what the vendor promises.

Ask your vendors specifically where the staff productivity improvements come from; in a demonstration have the sales person show you how specific functions of their software can improve staff effectiveness at particular tasks. Instead of citing just studies performed in large institutions, have the vendor show you how their benefits apply to your smaller setting. Ask specifically what happens if certain data is not entered in the way the vendor requires it; does it break the software, reduce the staff productivity benefits, or something else?

Product Details

Increase of practice revenue and profit

Most physician practices make money by seeing patients and charging fees for services; but when a vendor promises an improvement in revenue or an increase in profit, you must be very reluctant to believe the claims without specific evidence. An increase in revenue can only come when the number of patients seen per day per physician can be increased. An increase in profit can only be achieved if the costs associated with seeing patients can be reduced. Unless an EMR actually reduces the number of steps involved in seeing a patient and reducing the time associated with the non-clinical aspects of patient care there is no way that the introduction of the technology itself will increase revenue. Likewise, unless an EMR is designed to significantly remove staff burden and reduce the number of people in your office that you need to perform tasks associated with patient care, realizing an increase in profits will be tough.

During the software demonstration, ask the vendor about how the revenues increases come because of specific features. Dubious responses like studies performed in academic medical institutions or a reference to another client shouldn’t be enough – they should be able to demonstrate methodically how revenues will go up in your practice.

Reduce costs outright or control cost increases

In some fairly sophisticated implementations the reduction of costs has been proven to be possible; however outright cost reduction is still tough to gain. Controlling cost increases, however, is quite possible and is usually easier to attain because as your staff becomes familiar with their technology solutions they become more efficient over time and they are able to do more work with the same resources and staff therefore you may be able to increase the number of patients that you can see over time without increasing costs. Again, while immediate cost reductions are tough in a medical practice given that a large portion of your costs are associated with personnel, long-term cost reduction through either attrition or not having to hire new staff while still being able to increase their workload allows you to control costs better.

During the software demonstration, make sure you see how specific software features will reduce costs. You will get plenty of softballs being thrown your way about how other customers saw their costs go down or studies showing that large companies have seen the benefits. Your job as the CIO will be to force the vendor to tie cost savings specifically to use of their software, not computers in general.

Improve clinical decision making

Improving clinical decision-making is often a dubious endeavor and should not typically be the first reason you choose to implement an EMR; this is because clinical decision-making is and will remain a knowledge –based activity requiring significant training and teaching of computers before they can actually begin to improve clinical decisions. Physicians are some of the worlds’ best trained knowledge workers and they honed their clinical decision-making skills over a long period of time in very specialized training regimens that cannot easily at this time be duplicated by computers. When a vendor promises that an implementation of any EMR will improve decision-making from a clinical standpoint remain very skeptical.

Enhance documentation

Many vendors claim that their EMR’s will help improve and enhance clinical documentation. While this is very true for lead-based EMR is they are often creating much more documentation as far as quantity is concerned while likely reducing the actual quality of the information contained in the documentation. When implementing a template-based solution keep in mind that what a physician could normally easily write down in a couple of sentences will turn into many paragraphs in many pages of boilerplate text and boilerplate documentation that must then be stored red and understood by colleagues. So the promise of enhanced documentation is actually usually easy to achieve because you will get more pages of documents that are automatically generated but those pages that are generated may not necessarily be the most favorable from a clinical usefulness perspective.

Product DetailsProduct Details

Improve patient care

Many vendors proclaim that the installation of an EMR sometimes by itself will improve patient care; if by improvement of patient care they mean actually moving patients through the different steps associated with patient care in your office in a faster and more customer friendly manner then there is some truth to that. However if by improvement of patient care the promise is to actually make people’s healthcare better or truly improve a patient’s health itself then those claims must also be seen with a skeptical eye. This is similar to the clinical decision making enhancement promises that are often made; just like clinical decisions, patient care is a very human activity and simply introducing a better record keeping system will not improve people’s health. We are an improvement in health can occur however is in the tracking of clinical goals and helping patients meet those goals by reminding patients for regular tasks.

Reduce medical errors

Reduction of medical errors is a laudable goal; and in fact many EMR’s and the use of computerized physician order entry systems can help reduce medical errors by ensuring that common clerical types of errors do not occur. When looking at medical and clinical errors those errors that can easily fit well established and known rules can be automated in a somewhat friendly and easy manner and by using such automated tools error reduction is possible.

Assessment

However, when rules become difficult to define or are not widely agreed-upon then errors associated with such rules would not be caught.

PART ONE: How to Demo and Buy an EMR Office System [Part 1 of 2]

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

How to Demo and Buy an EMR Office System [Part 1 of 2]

Join Our Mailing List 

A SPECIAL ME-P REPORT

Practical “Tips and Pearls” from the Trenches

[Part One]

By Shahid Shah MS http://www.healthcareguy.com

Shahid N. Shah MSWhen getting demonstrations from vendors, the only way to understand the value for the money being spent or invested is to measure and communicate the productivity improvements that IT is supposed to deliver.

If you cannot measure how much time something takes before technology is implemented you will never know whether or not the purchase of any technology was a wise investment.

Some of the measurements you should consider are:

  • how long it takes to pull up a patient chart
  • how long it takes to update common data elements within a chart (meds, problems, etc.)
  • how long an appointment takes to schedule
  • how many patients are seen on a daily basis
  • how much data is being captured per patient visit
  • how long the check in and check out processes take
  • how much time spent on non-essential phone calls (better handled by automated email?)
  • how much time a physician spends on non-clinical activities

The actual items that you measure will depend on the tasks that you would like to automate; the simple listing of the tasks that you would like to automate often provides enough basic measurement metrics that you can perform a before and after comparison.

Vendor Demonstrations

When bringing vendors and for demonstrations or discussions you should lay out your workflow and your processes and share with them the kinds of tasks you would like to automate and the kind of staff productivity you are looking to improve and make your vendors focus on what’s important to you and not what features and functions they have in their solutions. Just remember the rule if you don’t measure you will never know whether you made an investment or simply spent money on something you didn’t need. If you don’t know how well you’re doing and where you want to improve vendors can give you any numbers and they will sound good to you.

Product Details

Here are some general tips for making sure you get good demo’s:

  • Demonstrations from vendors should not be about their software, but about how their solution benefits you. Make sure they spend most of their time talking about you, your practice, how their solution matches your practice, why each feature they are showing is important to your specialty and staff, and why they won’t fail in your office. Each time they talk about a general feature or function, bring them back to your practice.
  • When vendors talk about saving money and increasing productivity keep in mind that some money comes in the form of hard cash for the purchase of equipment and software but even more money will be spent in terms of early loss of productivity as new solutions are installed and staff becomes acclimated to it and potential loss in productivity forever if the wrong processes and steps are automated.
  • Force vendors in their demonstrations to talk about their failures in past installations – how many times were they removed/deinstalled, why did failures occur in the past, how did they recover from inevitable problems? The more a vendor can talk about why things go wrong and how they can help right the ship, the more likely they can help you out the jams you will get into.

To save you time, take 30 minutes and create a document that will tell vendors what you want them to show you in a demo and make the follow your script, not theirs.

Here are some tips for helping vendors demo to you:

  • See if you can do the first demo over the phone and web meeting software like WebEx or GotoMeeting. Remote demonstrations make more efficient use of time – the second or third demonstrations when you’re narrowing down selections are better in person.
  • Tell them there is no need for detailed company introductions and that you have no desire to hear that the vendor’s founders have found the secret sauce to healthcare technology that will save the healthcare industry. Vendors think you care about that stuff and will waste much of your time unless you make sure your wishes to not hear that are known in advance. They will not think you’re rude, they will thank you.
  • All medical records software do generally the same thing, they just do them in sometimes different ways and that’s what you care about – how they’re different. You’ll want to tell them to focus on how they different from other EMRs but not let them focus on competitors early on. Do this towards the end when you better understand their product and can ask more specific questions.
  • If the sales person wants to talk about the company, ask him to focus on the size of their service staff relative to their R&D staff, whether they provide in person phone support, do they have web-based support with screen sharing, and how much it will cost you to get support when you need it. While you’ll never talk to the CEO or founders of a vendor, you’ll definitely talk to their service staff so do ask about it.
  • Take the keyboard from the sales person. Never let a sales person drive the keyboard in a demo, you should do it yourself or have a computer-proficient staff member drive it.
  • Within the first 30 seconds of the demo, make sure you are shown how to lookup a patient by name and date of birth. If it takes more than 30 seconds to launch the app, log in, and type in a patient name or date of birth, and get to a chart then you should be disappointed.
  • Once you’re at the demo patient screen, try to make sense of it without letting the sales person talk and show you around. If there are too many fields and you’re getting confused, it’s probably not intuitive and you should be cautious. Again, don’t let the sales person show you what you don’t understand – try to figure it out yourself.
  • In the demo patient screen, can you find the face sheet, meds, problem lists, procedures, past documents, faxes, lab results, and other documents without help from the vendor?
  • Within the first three minutes of the demo, make sure you see how to add meds, problems, and procedures to an existing patient. These are common tasks and shouldn’t take long.
  • Within the first seven minutes of the demo, make sure you see how to add a note to the chart. This is how you’ll start to interact and input data into the system.
  • Within the first fifteen minutes of the demo, create a new patient record and try to reproduce a sample patient chart in the system. Use an anonymized patient chart and try to recreate it during the vendor’s demo.
  • Now is the time to ask about all the other features that you care about and want to see demonstrated. Try not to ask about features just to see if they have it; tie it to one of your metrics and tell them why you need it.
  • If you liked what you saw, now is the time to ask them what other customers they have and their recent customer wins, how they compare with competitors, how much they cost, and related questions. You’ll understand the vendor better once you’ve tried the software.

Key focus areas for your demonstrations

Sales people for vendors give demo’s hundreds of times and each demo is the same for almost everyone and it focuses on their product. Your job is to focus them into the following key areas that are of concern to you:

  • Chart access. You will want to know how patient charts indexed, searched, and stored. Ask how they handle lost charts and multi-user access to the same chart (meaning can multiple people simultaneously view and update a chart). Inquire about how charts can be accessed on a mobile phone, on a web browser at your house, on a workstation at a hospital you have privileges at, or on your laptop while you’re in CME training. An EMR that doesn’t give you fast access to your charts from everywhere on any kind of device is going to limit you. Ask them to allow you to point your iPhone to a sample chart and see how it will look.
  • Data entry and document creation. Ask over and over again how data gets into the system; will it be a model that allows you to dictate into a phone and have the results show up in the EMR or will it be through voice recognition where the computer is trained and tries to understand what you say and automatically and immediately converts your speech into text for the EMR? Be sure to ask to what extent your voice can create notes in their system. The most common input mechanism outside of voice dictation is “point and click” templating where you choose between many options by pointing and choosing patient symptoms, observations, and other details and the computer creates the notes for you. For all normal findings the software can create the standard notes but for all abnormal findings you either enter free text or dictate. The point and click model is very popular but is a time-consuming activity. Another technique is handwriting recognition on a tablet – if you can write fast enough on touch screen device or can point and click fast it can be something that you can use. All these techniques are important to cover in a demo so you can decide what’s best for you.
  • Data backups. If they are a cloud provider, ask them during the demo to show you how you can easily get access to the database behind the user interface to get your data out anytime you want to. Ask the cloud vendor their disaster recovery strategy – what happens if their primary site is inaccessible, how do you access the data? If your EMR is on-premises on a server, ask them about how they help you perform backups of the server either locally or over the Internet. If the EMR vendor says backups are your problem and doesn’t give you a strategy or guidance you’ll have more to worry about.
  • Patient portals and personal health records (PHRs). Patient engagement and ability for patients to directly connect with you and view their records through your EMR is an important capability. During the decision-making process be sure that for no extra cost patients should be able to see their personal health record (PHR) as another view of your EMR.

Product DetailsProduct Details

Other considerations for your demonstrations

When you are looking to capture metrics and figure out which areas of your practice needs to be automated, take a look at the following general areas and make sure that when you are getting a demonstration you do so in a manner that fits the actual needs of your practice rather than what the software developers and consultants might think you need. If you don’t focus on your business problems than the vendors and consultants will focus you on what they think is important rather than what actually might be important to you. You’re better off reducing the number of areas you get demonstrated versus expanding.

PART TWO: How EMR Vendors Mis-Lead Doctors [Part 2 of 2]

RELATED:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Are you Over Paying for Your 401(k) Plan – Doctor?

Join Our Mailing List 

Checking it Twice

By Guy P. Jones CFP® http://www.guypjones.com

Guy P. Jones CFPMany of the doctor and medical professionals I meet are surprised to find that their 401(k) plan has hidden fees. They often don’t have or take the time to learn all the aspects of setting up a new plan.

As a consequence, they often times buy what I call “The 401(k) in a Box” from the first provider that comes along or from a current vendor that is providing ancillary services for them.  Many plans have significant hidden fees and this is especially true of 401(k) plans offered to small businesses like a medical practice or clinic.

According to a recent study, the average 401(k) plan has hidden fees of 0.72% per year. That may not seem like much but it costs the average participant about $11,000 over the lifetime of their participation. That’s $350 per year – and the fees are extracted directly from the 401(k) your account!

But, what about doctors and small business owners whose 401(k) plans have fewer than 20 employees and less than $1 million in total assets?

Well, their situation is much worse. For these small 401(k) plans, hidden fees can jump from 0.79% to 1.89%, or up to $920 per plan participant per year. This can mean paying an estimated $28,000 in hidden fees over the lifetime of their participation. If you selected one of these 401(k) for your employees, you could be unknowingly costing them $350 – $920 per year in hidden fees.

What are 401(k) Plan Fees and Who Pays for Them?

401(k) plan fees and expenses generally fall into three categories:

  • Plan Administration Fees – The day-to-day operation of a 401(k) plan involves expenses for basic administrative services – plan recordkeeping, accounting, legal and trustee services – that are necessary for administering the plan as a whole. Generally the more services provided, the higher the fees.
  • Investment Fees – the largest component of 401(k) plan fees and expenses is associated with managing plan investments. Your net total return is your return after these fees have been deducted.
  • Individual Service Fees – Individual service fees are charged separately to the accounts of participants who choose to take advantage of a particular plan feature. For example, individual service fees may be charged to a participant for taking a loan from the plan or for executing participant investment directions.We all evaluate our vendors occasionally. I find most doctors and small business owners do not evaluate their retirement plans because they do not know what questions to ask:

Questions

  • When was the last time you reviewed your retirement plan for cost savings or plan improvements?
  • Is it time to find out how to get a plan started?

Retirement

Assessment

Getting education from a physician focused fiduciary financial advisor is an important step in the process to either grow the profitability of your current plan or realize the benefits of a 401(k) Plan.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Product Details

On Medicaid Payment Amounts

Join Our Mailing List

In the USA 1999-2010

http://www.MCOL.com

Medicaid

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Introducing US Treasury Floating Rate Notes

Join Our Mailing List

What they Are – How they Work?

[By Staff Reporters]

Back in January 2014, the US Treasury announced that it would hold an inaugural Floating Rate Notes (FRNs) auction this year, making FRNs the first new Treasury security since they introduced Treasury Inflation-Protected Securities (TIPS) more than 15 years ago.

Complimentary Products

FRNs will complement Treasury’s existing suite of securities, which include Treasury bills, notes, bonds, and TIPS.

The Treasury’s introduction of FRNs will provide a number of benefits to taxpayers including assisting Treasury in managing the maturity profile of the nation’s marketable debt outstanding, expanding Treasury’s investor base and, most importantly, helping to finance the government at the lowest cost over time.

Assessment

FRNs are a unique and attractive option for investors because the security features an interest payment that can adjust over time.

***

US Capitol

***

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Developing the Millionaire’s Mindset [Part 2]

Join Our Mailing List

Three More Components

By Rick Kahler MS CFP® http://www.KahlerFinancial.com

Rick Kahler CFPIn a previous ME-P, we looked at the first three components of a millionaire mindset: how to spend like a millionaire by living frugally, budget like a millionaire by putting essentials and savings first, and work like a millionaire by loving what you do and investing in your career.

All three of these are vital habits for anyone wanting to build financial independence and lead a satisfying life. But the millionaire mindset doesn’t stop there. Here are three more aspects of it.

4. Fail like a millionaire

The classic book, The Millionaire Next Door, by Thomas J. Stanley and William D. Danko, points out a statistic that initially seems backwards. The average millionaire makes 3.1 major financial, career, or business mishaps in a lifetime. The average non-millionaire makes 1.6 such mistakes.

Why do successful people fail so much more often? They don’t give up. They try again, and again, and again. As Steve Jobs, who had his own failures, said, “I’m convinced that about half of what separates successful entrepreneurs from the non-successful ones is pure perseverance.”

My own observation is that those who succeed also learn from their failures. A millionaire mindset means being willing to take risks, but also being smart enough not to keep making the same mistakes.

5. Network like a millionaire.

Those who succeed in starting businesses, building careers, and accumulating wealth aren’t afraid to ask for help. Millionaires know better than to rely solely on their own expertise. They are experts at building an expansive network of friends and acquaintances that they can turn to for help and advice. They understand that the more people you know, the more access you have to people you can learn from.

This, of course, is only one aspect of networking. Contrary to the projections of “greed” and “selfishness” often thrust upon them by public opinion and the media, successful people are also generous in giving back. The millionaire mindset includes an awareness that no one becomes successful in a vacuum. Millionaires are typically quick to acknowledge those who have helped them. They tend to pay it forward by mentoring, helping others to succeed, and sharing both their money and their wisdom.

6. Think like a millionaire

Having a millionaire mindset does not mean having a life goal of being rich. Millionaires think of money as a tool, not a goal. They don’t value wealth for its own sake. In fact, for many successful people, becoming rich is almost incidental. Their primary focus is succeeding at work they are passionate about.

A millionaire mindset is based on an attitude of gratitude, not one of entitlement. It includes the awareness that experiences and relationships are more valuable than things when it comes to creating sustainable happiness.

Successful millionaires understand that money itself will never give you meaning or make you happy. Yet they also understand that money is important. It is inseparable from our quest for meaning and happiness, because it touches everything we do. Financial planner Dick Wagner calls money “the most powerful and pervasive secular force on the planet.”

***

Classic Jaguar

***

If you are struggling to pay the bills on a meager income, overwhelmed by debt, or living in chronic financial chaos, it’s highly unlikely that you’ll feel fulfilled and satisfied with your life. Money is an essential tool in today’s world, and learning to use that tool wisely is as important as learning the skills required for your career.

Assessment

No matter what direction your life or medical specialty takes you, developing a millionaire mindset will serve you well. It’s a crucial set of values to help you achieve your goals and realize your dreams.

PART ONE: Developing the Millionaire’s Mindset [Part 1]

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:


  Product DetailsProduct Details

Employer Health Benefits Post PP-ACA

Join Our Mailing List

Percentage of Employers who View Health Reform Impact on Aspects of Employer Benefits as Moderate / Tremendous

By http://www.MCOL.com

ImageProxy

 HealthcareWebSummit Events

Upcoming Webinars:

On Demand: IBM Webcast: Using Analytics to Improve Outcomes at the Point of Care
On Demand: A Fresh Approach to CDH: 5 Ways to Get In It to Win It
Predictive Modeling Web Summit June 4, 2014
Large Employers and Exchanges: Minimum Standards and Private HIX Considerations June 5, 2014
Cigna’s Collaborative Care Strategy: Engaging Healthcare Professionals June 18, 2014
Provider Contracts and Quality Measurement June 19, 2014
Understanding Medicare DSH Changes-Hospital/Medicare Advantage Plan Implications June 24, 2014
Accountable Care at a Tipping Point: Oliver Wyman ACO Research Findings June 27, 2014
2015 Medical Cost Trends & Implications: PwC Research Behind the Numbers July 15, 2014
Readmissions Web Summit August 14, 2014
Accountable Care Web Summit December 11, 2014

Flash Drives of Past Events

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details


Developing the Millionaire’s Mindset [Part 1]

Join Our Mailing List 

To Build a Solid Financial Foundation to Support your Goals

By Rick Kahler MS CFP® http://www.KahlerFinancial.com

Rick Kahler CFPIf you’re a new graduate, nursing or medical student, taking your first steps into the adult world, here is the most important financial advice I can offer: Develop a millionaire mindset.

This absolutely does not mean making wealth your life goal. But, thinking like a millionaire will help you build a solid financial foundation to support you in reaching your life goals.

Definitions

First of all, let me define “millionaire.” A millionaire is someone with a net worth of one million dollars. That amount would generate an income of around $30,000 a year. In today’s world, that’s not even close to lavish-lifestyle wealth.

You probably know several millionaires. If you don’t think of them as rich, it’s most likely because they practice the millionaire mindset.

Here’s how:

1. Spend like a millionaire

The number-one common denominator of wealth accumulators is frugality. Millionaires shop sales, clip coupons, read labels, compare prices, and bargain. People who build wealth usually don’t wear designer clothes, drive luxury cars, live in extravagant houses, or shop at Neiman Marcus. They typically wear jeans bought on sale, drive used Toyotas, live in middle class neighborhoods, and shop at Walmart.

There’s no place in a millionaire mindset for credit card debt. Pay cash for everything but your home. Use a credit card only for convenience and pay it off every month. If you ever find yourself unable to pay the full amount, cut up your card. Pay off the balance as quickly as you can, and then don’t use a credit card for at least one year.

2. Work like a millionaire

Most millionaires work long hours, and most of them love what they do. They often have some “skin in the game” by owning part or all of their own businesses. As much as possible, find a job and career you love. When you do, your work becomes play. Invest time and money to keep your career skills and knowledge current. The millionaire mindset knows that your career is your most valuable financial asset.

3. Budget like a millionaire

Most college students live on budgets that allow only a Ramen noodle lifestyle. When you start getting career paychecks, keep that lifestyle for a time. Don’t increase your budget when you get a new job, a raise, or a promotion. Always have your lifestyle at least one step below your income.

***

Millionaire's Jaguar

***

To budget like a millionaire, follow these steps on every gross dollar you earn:

  • First, pay your taxes. Estimate your total tax liability and be sure your employer withholds enough to cover it. If you are self-employed, deposit a percentage of every check into a savings account that you use solely to pay your quarterly estimated taxes. Never “raid” these funds.
  • Second, put away at least 20% or more of every gross dollar you earn until you have six months to one year of living expenses in an emergency account. Then continue to invest that 20% of your gross pay in qualified retirement plans like 401ks, 403bs, or IRAs.
  • Third, pay your fixed expenses like housing and utilities.
  • Fourth, set up short-term savings accounts for foreseeable future “unexpected” lump-sum expenses like car and home repairs, vacations, holiday giving, college tuition, and medical emergencies.
  • Fifth, go ahead and blow the rest any way you wish. For most people, this means living on 30 to 60 cents out of every gross dollar you earn.

Assessment

The ways you spend, budget, and work are only part of the millionaire mindset. In a future ME-P, we’ll look at other ways you can build a fulfilling life by thinking like a millionaire.

PART TWO: Developing the Millionaire’s Mindset [Part 2]

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Introducing Physician-Focused Consumerism [PFC]

Join Our Mailing List 

A New Process or Just a New Term?

[By Staff Reporters]

According to Javier Sanabria, Physician-Focused Consumerism is a set of initiatives designed to align physician decision making with high-quality healthcare outcomes provided in a cost-efficient manner.

 manage

Physician-focused consumerism can include the redesign of financial incentives, greater access to patient data, decision support tools, ongoing education about treatment alternatives, and an understanding of the financial impact of alternatives on patients. It can be the basis for collaborative efforts between employer health plan sponsors, provider systems, and physicians to help achieve high-quality care in a cost-effective manner.

Assessment

See more at: http://www.healthcaretownhall.com/?p=7450#sthash.AgjagVO7.dpuf

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Two Healthcare Sectors the Stock Market Got Wrong on Election Day 2012

Join Our Mailing List

How various sectors in the Health Care Industry fared under the PP-ACA legislation?

[A SPECIAL R&D REPORT FOR THE ME-P]

By David K. Luke MIM, MS-PFP, CMP™ [Certified Medical Planner™]

Website: http://www.networthadvice.com

David K. LukeThere has been a lot of speculation since the words “Affordable Care Act” were first whispered years ago on how the various sectors in the Health Care Industry would fare under such legislation. I proposed that a good indicator would be to look at the performance of the individual health care sector stocks on the first trading day after the election.

(See With Obama Election Win, “Mr. Market” Weighs in on the ACA Equity Winners and Losers by David K. Luke on November 16, 2012).

Link: With Obama Election Win “Mr. Market” Weighs in on the ACA Equity Winners and Losers

The day after Pres. Obama’s reelection on Wednesday, November 7, 2012 the stock market was down over 2% as measured by the S&P 500 and the Dow Jones Industrial Average (DJIA). The common reason given was increased doubt that the impending “fiscal cliff” issue, which was splitting the House and the Senate, would be resolved. There was however, another big concern on investor’s mind: the future of the Affordable Care Act. While the election was close when measured by the popular vote with President Obama earning 51.06% versus Mitt Romney with 47.20%, the electoral vote showed a hands-down Obama victory with 332 versus 206 votes. Investors voted with their pocketbooks with that first trading session following the election showing certain healthcare sectors up in price, other healthcare sectors with moderate returns, and certain healthcare sectors down in price.

Disparate Health Care Sector Returns

It is interesting to look back now over a year and a half later and see how accurate those investor votes were on that first day of realization that health care reform was continuing forward at a much faster pace now that President Obama would be serving a second term. Keeping in mind that the day was a very negative day as a whole in the stock market, a number of healthcare sectors were up in price. This group includes Hospital Stocks and Medicaid HMOs. Note the phenomenal one-day returns (in a down 2% market!) on the sample stocks in these two groups:

Hospital Stocks

  • Health Management Associates (HMA) +7.3%
  • HCA Holdings Inc. (HCA) +9.4%
  • Community Health Systems Inc. (CYH) +6.0%
  • Tenet Healthcare Corp. (THC) +9.6%

Medicaid HMOs

  • Molina Healthcare Inc. (MOH) +4.6%
  • Centene Corp. (CNC) +10.1%
  • WellCare Health Plans Inc. (WCG) +4.4%

Such positive returns on a big down day in the market indicates investors assessing these healthcare sectors being good investments under an Obama presidency and a positive outlook for the implementation of the Affordable Care Act. The other up sector on that day was the Drug Wholesalers, up almost 1% on that negative day. (See “Selected Health Care Performance” Chart – below).

The market had a tepid response to the Pharmacy Benefit sector, as well as the Generic Pharmacy, Testing Labs, and Big Pharma. In my sample group, these sectors were down -.4%, -7%, -1.7%, and -1.4% respectively. It is important to note however that these sectors while slightly positive or barely negative still performed better than the general market that day.

Two Sectors

But, the two healthcare sectors that the stock market severely punished with the voting of substantially more sellers than buyers by investors on that first post-election day were the Medical Device Companies (down 2.5% in the sample group) and the Medicare Part D Companies (down 4.7% in the sample group). The thought at the time was that Medical Device Companies, facing an impending medical device excise tax of 2.3% on the sale of most medical devices in the United States, would be devastated, and that Medicare Part D Companies would face severe profit constraints with tighter-fisted government regulations imposed by the ACA.

***

Stock_Market

***

The Retro-Specto-Scope

In hindsight, investors were correct on two out of the three predictions based on stock market prices on the various healthcare sectors. Hospital Stocks, Medicaid HMOs, and Drug Wholesalers, the leading sectors indicated to be winners with the impending implementation of the ACA, are up 69.8%, 63.6% and 76.5% respectively in the sample groups since November 7, 2012. This remarkable and closely parallel return for these three sectors seemed to prove that the stock market on November 7, 2012 correctly picked the three winning health care sectors! The S&P 500 index for the same time is up 32.02%, a nice return for 1 ½ years but about half the return of these apparently huge benefactors of the ACA. The healthcare sectors that investors felt less positive about (but more positive than the general stock market) on that first postelection day were Pharmacy Benefit Companies, Generic Pharmacy Companies, Testing Labs, and Big Pharma. These four health care sectors are up 43.8%, 40.5%, 6.4%, and 20.5% respectively. Again, in terms of ranking the sectors, these four sectors performed in line based on the comparative returns of the other healthcare sectors.

Wisdom of Crowds

Amazingly, it appears that the emotional Mr. Market predicated quite accurately on Wednesday, November 7, 2012, in one day of trading, not just which health sectors would be good investments for the near future, but the actually ranking of the future performance of the sectors! It seems as though the stock market, as one large voting machine, precisely dissected the over 20,000 pages + of resulting legislation created from the original 906 pages (pdf here) of the PPACA law and distilled it down to profits and losses with the resulting winners and losers in the health care industry in one trading session.

Two [2] Big Misses

Investors however were way off on their concerns about Medical Device Companies and Medicare Part D Companies. The two sample groups were up 71.3% and 66.4% in the time of November 7, 2012 to May 19, 2014 respectively, more than double the S&P 500 for the same period, and in line with the best performing sectors! This is spite of the fact that stock sample of these two groups were the two worst performers on post-election day trading. What happened?

***

Bear + A Falling Stock Chart

***

The “Medical Device Excise Tax” Fable and the “Private Insurers Will Control Costs” Fairy Tale

Wall Street has sharpened their pencils in the last year and a half and realized they have gravely underestimated the profit potential of the Medical Device makers and the Managed Care Health Insurers, in spite of the ACA. Based on stock price performance of the sample group of major players in the past 18 months, fewer sectors look as profitable as the Medical Device Industry and the Medicare Part D Industry. What happened?

The Medical Device industry states that the tax will cost the US “tens of thousands of jobs” and that those jobs will be shipped overseas. A number of issues that are involved here however refute these claims (http://www.factcheck.org/2013/10/boehner-and-the-medical-device-tax/. It appears that any targeted reductions were not related to the implementation of the tax, which became effective January 1, 2013, in spite of heavy protest by the industry. Medical technology continues to have a bright future regardless of the tax.

The notion that the “Affordable” Care Act will help reign in the rampant cost increases of Medicare’s “Part D” program seem to be elusive. Private insurers have done a poor job of keeping drug prices down, especially when compared to the discounts the government gets for Medicaid. Medicare Part D companies wield significant influence on Capitol Hill, and impending steeper discounts look unlikely.

Everybody Wins, Except …

Before the ACA implementation, about 85% of Americans had health insurance. Currently with an additional 7 million Americans with health insurance thanks to Obamacare, an additional 2.2% of Americans now have coverage, or about 87% of all Americans. How can such a slight increase in new health care consumers be responsible for such large anticipated profits in the health care sector? It cannot. Wall Street is telling us that the new health law is not about new customers, but about increased profit margins for the health care industry. I can draw three conclusions:

  1. The Affordable Care Act may not be so affordable for health consumers
  2. Most companies in the Health Care Industry stand to gain financially with ACA. There is one sure loser with ACA: The physician, who can only look forward to increased workloads and mpending Medicare SGR pay cuts.

THE CHART [Research and Development]

Selected Health Care Sector Stock Performance Random Sampling of Publically Traded Companies From President Obama Re-election Date to Present

Chart

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details  Product Details

Product Details

Retail Perscription Drug Expenditures

Join Our Mailing List

By Payer 2001-2011

http://www.MCOL.com

Retail Drugs

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details


2014 Healthcare Innovation Conferences

Join Our Mailing List

The List for 2014

By Staff Reporters

On Hospital Price Transparency and Estimating Out-of-Pocket Expenses

Join Our Mailing List

When it comes to health care, determining medical costs can be complicated

[By Dr. David Edward Marcinko MBA CMP™]

Dr David E Marcinko MBAAt Baptist Memorial Health Care, they’re trying to make things a little easier to understand. That’s why they built Expense Navigator, an out-of-pocket medical cost estimator tool. As a doctor, patient and financial advisor, this is vital information.

Expense Navigator is a key step in Baptist’s effort to become a leader in price transparency in U.S. health care. Patients can use the medical cost estimator tool to estimate out-of-pocket costs for hundreds of hospital inpatient or outpatient procedures.

They can also get a customized estimate for care at Baptist Memorial Hospital-Memphis or 13 other affiliated hospitals in West Tennessee, North Mississippi and East Arkansas.

So, whether you have Medicare, other insurance or are uninsured, the Expense Navigator may help you better plan for Baptist medical expenses.

Some of the Procedures Listed

  • MRI
  • CAT Scan (CT)
  • Emergency Visits (ER)
  • Mammogram
  • Orthopedic Procedures
  • X-Ray
  • Ultrasound
  • Childbirth
  • Bone Imaging
  • Cardiac Procedures
  • Appendectomy
  • Chemotherapy
  • Laparoscopy (Scope)
  • Pulmonary Procedures
  • Upper GI
  • Lower GI
  • Spinal Tap
  • Lab Tests
  • Diabetes Treatment

Free, out-of-pocket medical cost estimates are available for the following hospitals in Tennessee, Mississippi and Arkansas

Tennessee

Mississippi

Arkansas

Keyboard

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

Why Hospitals Must Look to the Cloud?

Join Our Mailing List

A Key Solution to Meeting the Healthcare Mandates

By http://www.Innotas.com

hospital clouds

Assessment

Healthcare and Insurance Partial Client List:

  • Adventist Health
  • RelayHealth
  • SCAN Health Plan
  • University of Missouri Health System
  • Johns Hopkins Healthcare LLC
  • Maxim Healthcare Services, Inc.
  • Catholic Health System
  • Noven Pharmaceuticals, Inc.
  • Nyack Hospital

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

Should Eric Shinseki – and others – Resign?

Join Our Mailing List 

Who he Is – Wither the VA Imbroglio

ShinsekiAccording to Wikipedia; Eric Ken Shinseki (/ʃɨnˈsɛki/; born November 28, 1942) is a retired United States Army four-star general who has served since 2009 as the seventh United States Secretary of Veterans Affairs.

His final U.S. Army post was as the 34th Chief of Staff of the Army (1999–2003). He is a veteran of combat in the Vietnam War, where he sustained a foot injury.

Assessment

Veterans Affairs Secretary Eric Shinseki testified on Thursday May 15, 2014 for the first time since a burgeoning scandal broke on allegedly deadly health care delays in the VA system, as he faces calls for his resignation and demands that the VA immediately improve the way it treats America’s vets.

And so we ask in this opinion poll:

Prior ME-P Polls

Members of the ME-P community called for the resignation of former HHS Secretary Kathleen Sebelius.

Link: Should HHS Secretary Kathleen Sebelius be Replaced?

Will our ME-P readers make the correct call; or not?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details


Making Medical [Financial] Advice Memorable?

Join Our Mailing List 

Can Physician [Advisor] Body Language Assist Patient [Client] Adherence

[By Dr. David Edward Marcinko MBA CMP™]

DEM at Drexel

Recently, I was at Drexel University which is a private research university in Philadelphia. It was founded in 1891 by Anthony J. Drexel, a noted financier and philanthropist. Drexel offers over 70 full-time undergraduate programs and accelerated degrees. At the graduate level, the university offers over 100 masters, doctoral, and professional programs, many available part-time.

Now, I know DU well because as a student from Temple University back in the day, I visited frequently. It was there that I first learned of the work of H. Ebbinghaus on the nature of emotions and the human memory.

Two [2] Examples

As doctors, we usually want to make a memorable impression on our patients and encourage them to remember our medical advice or instructions.

OR, as financial advisors, we want our clients to follow our informed advice. But how?

One suggestion is to take advantage of the Serial Position Effect.

Definition

The Serial Position Effect is a term coined by German psychologist Hermann Ebbinghaus PhD.

Hermann Ebbinghaus (January 24, 1850 — February 26, 1909)

According to Wikipedia, Dr. Ebbinghaus was a German psychologist who pioneered the experimental study of memory, and is known for his discovery of the forgetting curve and the spacing effect. He was also the first person to describe the learning curve. He was the father of the eminent neo-Kantian philosopher Julius Ebbinghaus.

Through his studies, he found that people have a tendency to remember the first (primacy) and last (recency) things to occur, and scarcely the middle.

The graph below demonstrates the Serial Position Effect in recalling a list of words. However, this psychological effect can be applied to many things – from job interviews to television commercials to physician advice.

***Graph

 ***

So, during your next patient interaction or client-advisor relationship, instruct your target either at the beginning or end of the event; or patient encounter. They are much more likely to remember you, and recall the topic, conversation, medical advice or instructions.

Assessment

If you want to be remembered, don’t be in the middle! And, this will make your next patient interaction; or client meeting, much easier.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

3 Reasons Doctors Are Ditching Insurance And Offering Care For Cash

Join Our Mailing List 

Moving away from public healthcare and towards private models

[By Jessica Socheski]

jsWith the new healthcare system in effect, many doctors are moving away from public healthcare and towards private models. Instead of taking insurance, programs like the corporate wellness plans from MDVIP and other direct primary care doctors are choosing to deal in cash only with their patients. And in essence, they are cutting out the expense of a middleman insurance company.

Many doctors have taken it upon themselves to create a model that helps more than it hinders. Here are three reasons why doctors are choosing private healthcare over public.

1. The Patient Comes First

For many people, the new healthcare insurance price has skyrocketed, making it difficult to pay for healthcare let alone use it when needing a doctor. Direct primary care doctors provide their basic or preventative care that their patients can afford without using their insurance and meeting high deductibles.

Doctors who have embraced this model find they are able to offer their patients a variety of services for less money. This offers people the chance to receive quality care without paying an exorbitant amount. Without this model, many people would avoid the doctor all together, which could lead to serious undiscovered health problems.

2. Waiting Game

Since the Affordable Care Act, hospitals, urgent care, and public healthcare offices have noticed an increase in patients, leaving both waiting rooms and doctors inundated with patients. Unfortunately, this leaves doctors and nurses trying to juggle too many patients without enough help to accommodate them. Doctors are overworked and rushed, unable to spend a proper amount of time with a patient.

Consequently, the current healthcare model has pushed many public healthcare doctors towards privatized hair, leaving an even larger doctor deficit and nurse shortage in the public sector. But since these doctors have turned to private healthcare as their new business model, doctors have the time and availability to meet with their patients and build a relationship with them.

Under private healthcare, patients can schedule appointments with their doctors to have a proper visit where both the physician and patient feels they been given an adequate amount of time—the doctor for diagnosing and the patient for quality care.

3. Doctor Freedom

The direct primary healthcare model is not something entirely new. But it is just now growing in popularity as doctors and patients search for relief from a problematic system. Before congress passed legislation in 1973 that led to the expansion of prepaid health plans, the majority of physicians operated in a fee-for-service model.

Under insured health plans, physicians had little flexibility in determining what services they could provide and how to cut costs for their practices. Some insurance companies even dictate the hours during which doctors can be paid.

 Three Reasons Doctors Are Ditching Insurance And Offering Care For Cash

Image Source: http://www.newyorkmedicalservices.com

Assessment

By moving away from insured health, doctors are able to remove the shackles and dictate how they believe their patients should be cared for. Dr. Villarreal, a doctor in Laredo, Texas, states in regards to his direct primary business model, “To me, there’s no other way I would practice medicine. You feel like you’re a doctor again.”

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

Racial Disparities in Life Expectancy at Birth

Join Our Mailing List

For the United States

By http://www.MCOL.com

Life Spans

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details


On the Future of Nursing Practice

 Join Our Mailing List

Focus on Scope of Practice

[By Staff Reporters]

Transforming the health care system to meet the demand for safe, quality, and affordable care will require a fundamental rethinking of the roles of many health care professionals, including nurses. The 2010 Affordable Care Act represents the broadest health care overhaul since the 1965 creation of the Medicare and Medicaid programs, but nurses are unable to fully participate in the resulting evolution of the U.S. health care system. This is true for nurses at all levels, whether they practice in schools or community and public health centers or acute care settings. A variety of historical, cultural, regulatory, and policy barriers limit nurses’ ability to contribute to widespread and meaningful change.

In 2008, the Robert Wood Johnson Foundation (RWJF) and the Institute of Medicine (IOM) launched a two-year initiative to respond to the need to assess and transform the nursing profession. The IOM appointed the Committee on the RWJF Initiative on the Future of Nursing, at the IOM, with the purpose of producing a report that would make recommendations for an action-oriented blueprint for the future of nursing.

As part of its report, the committee considered the obstacles all nurses encounter as they take on new roles in the transformation of health care in the United States. While challenges face nurses at all levels, the committee took particular note of the legal barriers in many states that prohibit advance practice registered nurses (APRNs) from practicing to their full education and training. The committee determined that such constraints will have to be lifted in order for nurses to assume the responsibilities they can and should be taking during this time of great need.

***

RN

***

The Changing Health Care System

In the 21st century, the health challenges facing the nation have shifted dramatically. The health care system is in the midst of great change as care providers discover new ways to provide patient-centered care; to deliver more primary care as opposed to specialty care; and to deliver more care in the community rather than the acute care setting. Nurses are well poised to meet these needs by virtue of their numbers, scientific knowledge, and adaptive capacity, and health care organizations would benefit from taking advantage of the contributions nurses can make.

Assessment

As the health care system has expanded over the past 40 years, the education and roles of APRNs, in particular, have evolved in such a way that nurses now enter the workplace qualified to provide more services than had been the case previously. Yet while APRNs are educated and trained to do more, some physicians challenge expanding scopes of practice for nurses. The committee stresses that physicians are highly trained and skilled providers and that some services clearly should be provided by physicians, who have received more extensive and specialized education and training than APRNs. However, given the great need for more affordable health care, nurses should be playing a larger role in the health care system, both in delivering care and in decision making about care.

The committee argues that APRNs are not acting as physician extenders or substitutes. They work throughout the entirety of health care, from health promotion and disease prevention to early diagnosis to prevent or limit disability. APRNs sometimes provide services that many people associate with physicians, such as assessing patient conditions or ordering and evaluating tests, but they also incorporate a range of services from other disciplines, including social work, nutrition, and physical therapy.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.
Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:


Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details

How Your 2013 Federal Tax Dollars Were Spent

Join Our Mailing List 

A Spreadsheet Breakdown

By Lon Jefferies MBA CFP

Lon JeffriesClick here for a calculator that shows you how the tax you paid in 2013 was spent.

Simply input the amount you paid in federal income tax in 2013 and you’ll see a breakdown of how your money was utilized.

  1. What would you cut in the budget?
  2. What areas would you spend more, or less, on?


Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com
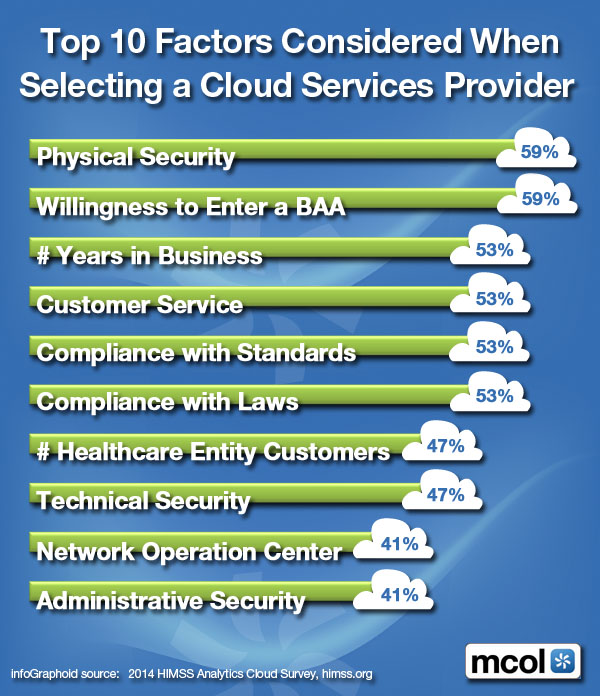
OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Dysfunction and Accountability in Health Care

Join Our Mailing List

A Pod Cast

Charles Ornstein talks with David Goldhill author of “Catastrophic Care: Why Everything We Think We Know about Health Care Is Wrong” about excess, poor oversight, and how new data may help spur change.

***

anatomy-physiology-student-tutorial-800x800

***

Link: http://www.propublica.org/podcast/item/podcast-dysfunction-and-accountability-in-health-care/?utm_source=et&utm_medium=email&utm_campaign=dailynewsletter

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

The Superior Retirement Account – Will that be Traditional or Roth?

Join Our Mailing List 

Weighing the Costs

Lon Jeffries[By Lon Jefferies MBA CFP®]

As an informed investor and reader of this ME-P, you’re likely familiar with the difference between a traditional IRA/401(k) and a Roth IRA/401(k).

While the traditional account enables you to postpone taxes on both the income invested and its growth until the funds are withdrawn, a Roth account does not provide an initial tax benefit but investment growth is tax free. So which is better?

Let’s answer the question with some simple math. Suppose an investor in the 25 percent federal tax bracket invests $1,000 of pre-tax income, obtains an 8 percent annual return over the next 10 years, and is still in the 25 percent tax bracket in the future. Would this investor profit more investing in a traditional or a Roth account?

As the chart below illustrates, the investor in this scenario would end up with the exact same amount in either a traditional or a Roth account.

So does the decision to invest in a traditional or Roth retirement account not matter? Not so fast.

Constant Tax Rate
Traditional Roth
Initial Tax Bill (25%) $0 $250
Invested Amount (after-tax) $1,000 $750
Future Investment Value $2,159 $1,619
Future Tax Bill (25%) $540 $0
After-Tax Value in 10 Years $1,619 $1,619

Lower Tax Bracket in Future

Let’s assume our investor will have a reduced income when she retires in 10 years, causing her to be in the 15 percent tax bracket in the future. Perhaps the worker is in her prime earning years and will have less income during retirement. In this scenario, due to the up-front 25 percent tax bill, investing the funds in a Roth would lead to the same after-tax value of $1,619. But investing the funds in a traditional account would allow the full $1,000 to experience growth for 10 years, with a reduced future tax bill of 15 percent, leaving $1,835 of after-tax value in the account. This investor would benefit from delaying taxes into the future when she would be in a lower tax bracket.

Lower Tax Rate in the Future
Traditional Roth
Initial Tax Bill (25%) $0 $250
Invested Amount (after-tax) $1,000 $750
Future Investment Value $2,159 $1,619
Future Tax Bill (15%) $324 $0
After-Tax Value in 10 Years

$1,835

$1,619

Higher Tax Bracket in Future

On the other hand, if the investor was in the 15 percent tax bracket this year but expected to be in the 25 percent bracket during retirement (potentially a young employee expecting his earnings to rise), paying taxes now at 15 percent would allow $850 to be invested, which after 10 years of 8 percent growth would be worth $1,835 tax free.

Higher Tax Rate in the Future
Traditional Roth
Initial Tax Bill (15%) $0 $150
Invested Amount (after-tax) $1,000 $850
Future Investment Value $2,159 $1,835
Future Tax Bill (25%) $540 $0
After-Tax Value in 10 Years $1,619 $1,835

Roth Advantages

What if you expect to pay a comparable tax rate both now and in the future? A Roth account offers several advantages in this scenario.

First, as taxes have already been paid on a Roth account, the government doesn’t require investors to take required minimum distributions (RMDs) from these accounts, whereas RMDs are required from traditional retirement accounts beginning at age 70½. Without RMDs, Roth accounts can grow tax free for the investor’s entire lifespan.

Additionally, upon death, Roth accounts pass to an investor’s heirs without any tax liability, while those who inherit a traditional retirement account must pay taxes on the assets.

***

IRA

***

Second, money withdrawn from a traditional retirement account before the investor is 59½ may be subject to a 10 percent penalty. Yet contributed funds to a Roth account (but not the growth on the contributed funds) can be withdrawn at any time without penalty. While withdrawing funds before retirement isn’t advisable, the added liquidity of the Roth account can prove useful in emergencies.

Finally, even if your income is expected to remain constant, investing in a Roth account allows you to lock in your taxes at today’s rate as opposed to taking the risk that national tax rates might be raised in the future.

If you’re unsure how your future tax bracket will compare to your current rate, diversify. Nothing prevents you from having both a traditional and a Roth retirement account. This not only allows you to hedge your bets, but puts you in a position during retirement to take distributions from your tax-deferred account in low-income years and from the tax-free account in years when you are in a high tax bracket.

Assessment

http://www.utahbusiness.com/articles/view/weighing_the_costs/?pg=1

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details  Product Details

How the ACA Affects Your RXs

Join Our Mailing List

On Four Large Groups of Import

By http://www.HelpRx.info

To give you a jumpstart about how the Affordable Care Act will impact you and your prescription drug coverage we’ve researched the major impacts on four large groups of people who could see the greatest impact.

Review the info-graphic below to learn about the benefits and requirements of the ACA and share it with your friends and family that still have questions about how the ACA will affect them.

***

infographic

***

Assessment

See more at: http://www.helprx.info/blog/infographics/infographic-how-the-affordable-care-act-impacts-you#sthash.6bk5zU0D.dpuf

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details

Why You Should [Still] Know Your Marginal Tax Rate?

Join Our Mailing List

And … Other Financial Planning Topics of Import

Lon JefferiesBy Lon Jefferies MBA CFP®

In 2014, the federal tax brackets are 10%, 15%, 25%, 28%, 33%, 35%, and 39.6%. For a taxpayer who is married and files jointly, regardless of how much the household makes, the first $18,150 of income after accounting for deductions and exemptions will only be taxed at the 10% rate.

Similarly, any income the household makes that is more than $18,150 but less than $73,800 is taxed at the 15% rate. At that point, the next $75,050 is taxed at 25%, and so on.

Consequently, not all income a household makes during the course of the year is taxed at the same rate. A marginal tax bracket is the tax rate that applies to the last dollar the household made.

It is crucial for all taxpayers to know their marginal tax rate. This information can help a client identify which type of investment accounts fits their situation best, how to structure an investment portfolio, and how to determine the value of certain deductions when filing their tax return.

Roth or Traditional Retirement Accounts

Contributions to traditional retirement accounts like IRAs and 401(k)s allow taxpayers to avoid recognizing income earned during the tax year and push the need to acknowledge the revenue into a future year. This is valuable because many people are in a higher tax bracket during their working years than they are during retirement. For instance, for a person who is currently in the 25% marginal tax bracket, it may be advantageous to delay recognizing the income until the investor retires and has less income, causing him to be in only the 15% marginal tax bracket. Doing this would enable the taxpayer to pay taxes at only 15% as opposed to 25%.

Alternatively, a Roth IRA or Roth 401(k) allows an investor to pay taxes on contributed income during the year it was earned but the money then grows tax-free. Consequently, a Roth retirement account is great for someone who believes they may be in a higher marginal tax bracket in the future. For example, a young employee in the early stages of his career who is in the 15% tax bracket but believes he may be in the 25% or 28% bracket in the future would benefit from paying all taxes on the income at his current rate of 15% and then getting tax-free investment growth. This would prevent the investor from having to pay the higher future tax rate of 25% or 28% on the invested dollars.

Knowing your marginal tax bracket can help you determine if you would favor paying taxes on your invested dollars at your current tax rate or if you believe you may benefit from pushing the need to recognize the income into a future tax year. This is a critical decision when planning for retirement and it can’t accurately be made without knowing your marginal tax rate.

Capital Gains Rate

A long term capital gains tax rate is the rate that applies to the growth of any asset held for longer than a year that is not within a tax-advantaged account. If you buy stock outside a tax-advantaged account, or purchase investment property, any growth in the value of the investment will be taxed as capital gains when sold.

An investor’s capital gains tax rate is determined by the investor’s marginal tax rate. For most taxpayers the long term capital gains tax rate is 15%. However, if a taxpayer is in the 10% or 15% marginal tax bracket, the long term capital gains tax rate is an amazing 0%! Additionally, many taxpayers in either the 35% or 39.6% tax bracket may end up paying capital gains at a rate of 20%.

Clearly, knowing your marginal tax bracket will help you analyze the appeal of making investments outside of tax-advantaged accounts. People who qualify for the 0% capital gains tax should actively search for ways to take advantage of this benefit.

Additionally, knowing your marginal tax rate can help you determine the best time to recognize long-term capital gains. If your marginal tax rate will be 25% in 2014 — leading to a capital gains tax rate of 15% — but you believe your marginal rate will be 15% in 2015 — leading to a capital gains tax rate of 0% — it would save you money and lower your tax bill to defer recognizing long-term capitals gains until next year.

***

FP

***

Annuities

Annuities are promoted as a way for invested dollars to obtain tax-deferred growth. However, when money is withdrawn from an annuity it is taxed at the investor’s marginal tax rate as opposed to his long term capital gains tax rate. Knowing your marginal tax bracket can help determine whether an annuity adds any value to your portfolio, or whether it could actually be detrimental.

Suppose an investor is in the 15% marginal tax bracket. If this person invests in an annuity, he will avoid paying taxes on any of the investment’s growth until the funds are withdrawn from the annuity. However, at that point the investment’s growth will be taxed at the taxpayer’s marginal income tax bracket of 15%. Alternatively, if this same investor utilized a taxable investment account rather than an annuity, the investment’s growth would be taxed at the investor’s capital gains tax rate of 0% when sold. In this case, investing in an annuity actually created a tax bill for this investor!

Clearly, knowing your marginal tax rate and your resulting capital gains tax rate can help you determine the best type of investment accounts for your personal situation.

Itemized Deductions

The value of your itemized deductions is essentially determined by your marginal tax bracket. For a simplified example, consider a taxpayer who could generate an additional $10,000 of deductions. Doing so would mean the individual would pay taxes on $10,000 of income less than he would without the deduction. If the individual is in the 15% tax bracket, generating the deduction would lower the person’s tax bill by $1,500 dollars ($10,000 x 15%). However, if the individual is in the 25% tax bracket, the same deduction would lower the person’s tax bill by $2,500 ($10,000 x 25%).

Consequently, knowing your marginal tax bracket can help determine when large itemized deductions should be taken. If you would like to donate funds to your favorite charitable institution, knowing which year you will be in the highest marginal tax bracket can help you determine the best time to make the contribution.

***

FA

***

Marginal Tax Rates Change

Many people’s income is relatively constant year-after-year. For these people, there may not be much fluctuation in their marginal tax bracket. However, any time you have a significant increase or decrease in income recognized during a year, your marginal tax rate may change. Whenever possible, it is best to anticipate how your current marginal tax rate might compare to your future marginal tax rate.This is another strong factor that can impact all the key financial decisions effected by your marginal tax rate.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details

Identifying the Most Expensive Medical Therapies

Join Our Mailing List

A “Top-Ten” List

http://www.MCOL.com

ImageProxy

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details


How to Safely Clean an Auto Engine Bay

Join Our Mailing List

Thoughtfully … with Some Care!

[By Dr. David Edward Marcinko MBA]

Dr David E Marcinko MBA

I’ve been washing the engine bay of my Jaguar XJ-V8-L for the past several years. How did I get started? Isn’t this really bad for my car? Why did / do I bother?

History

I worked with a neighbor who was seriously obsessed with keeping his 1986 Thunderbird clean – way more so than I ever was; or currently am. He popped the hood one day and I marveled at the near showroom appearance of the ~ 28 year old engine bay. I asked the same questions many of you have about getting the various components and systems wet.

The owner of the car was quite talented with most things automotive, especially the electrical systems as he was a professional car audio install technician with a high end audio shop. The sound system in that car was phenomenal even by today’s standards. He was quite confident that the water would not cause problems. That engine bay got a rinse with nearly every car wash and a regular washing. I was still skeptical. I carefully tried it myself starting out away from wiring and the alternator gradually becoming more confident until the entire engine bay was squeaky clean. It looked great then and still does.

I’ve never had a problem with getting any electrical items wet – even a distributor. A modern engine bay is engineered to get somewhat wet during normal use. Assuming your engine bay is in reasonably good shape, with no defects in the electrical, crankcase ventilation and intake systems you will most likely have no problems as well. This works best and is easiest when a car is new as dirt and oxidation never have a chance to start. Even an older engine – dare I say a Jaguar – bay can be transformed with a little extra work.

***

Jag DEM (2)

***

Jag DEM (1)

***

This ME-P is being provided as a guide only – I cannot guarantee you will not experience difficulties. Wash your engine bay at your own risk.

This is what works very well for me …

Start with a cold engine. A warm or hot engine will cause any detergent you spray on to quickly evaporate. Letting it sit and soak is what gets things clean. I cover electrical components, and have put a plastic bag over open exposed conical air filters.

Obviously, do not spray liquid directly into the air intake. Use a garden hose with a variable nozzle to go from a fine spray to a concentrated stream depending on what you are hosing down. A pistol grip style of nozzle is the easiest and fastest to use. A high pressure car wash hose is asking for trouble. Common sense is called for here.

I wash the underside of the hood first. I removed the fiber insulation the day I got my Jaguar home as I have with all of my previous cars. I personally believe the insulation is largely for sound suppression. It becomes a dirt magnet if left on and seems logical to assume it also promotes heat soak. I have not observed any engine heat related effects on the exterior hood paint with/out it.

But, the Jag is not my daily-driver. Hose down the hood, fenders, windshield and engine hosing off loose debris. Spray liberal amounts of full strength Simple Green all over, especially in the inaccessible areas. You would probably see good results with diluted Simple Green as well. Hose off any overspray from the fenders as Simple Green is too harsh for polished waxed surfaces. Let soak for ~5 minutes or so.

***

bay

***

While I wait – I have a few odd brushes I use to scrub around where I can. Thoroughly hose off all areas (with common sense) until all traces of the detergent are gone. Some areas can take higher pressure, like the intercooler and around the firewall. Once the car / engine wash has been completed I take the car on a drive to heat and dry the engine bay out. I repeat this maybe twice a year – that’s all it takes to keep everything looking showroom clean. The Jaguar under engine cover does a great job in keeping dirt out of the engine bay. 

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Link: http://feeds.feedburner.com/HealthcareFinancialsthePostForcxos

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details