What’s New with Renter’s Insurance?

Join Our Mailing List 

Affordable and Ideal for Future Physicians

[By Thomas A. Mudlowney MSFS CLU AIF® CFP® CMP™]

http://www.SavantCapital.com

Muldowney

Renters insurance can protect you from damage caused by weather events like wind, rain, snow or lightning, as well as fire, vandalism or theft.

Some policies also include liability protection. This would be valuable if someone got injured in your home and sued you; doctor’s are at high-risk for this sort of liability.

Costs

Renters insurance tends to be cheap. For a low payment, usually annually, you can often get replacement coverage for your belongings and living expenses if you are displaced.

This means that you can get money to replace a damaged or stolen item as well as paying for a hotel or alternative rent if you are forced to leave your home because of damage.

Assessment

Renter’s insurance may be ideal for medical residents, fellows and interns etc; as they travel around the country for education and post-graduate training; etc.

Renter's Insurance

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

More: http://www.CertifiedMedicalPlanner.org

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

Overview of Hospital Information Systems Architecture

Join Our Mailing List 

On Configurations and Varieties

[By Brent Metfessel MD MIS]

Dr. Metfessel

Hospitals can use a variety of configurations for HIS implementation depending on business needs and budgetary constraints.

Staffing needed for these systems can range from a few full-time equivalents (FTEs) per 100 beds for very basic off-site processing systems to 15 or more FTEs per 100 beds for sophisticated systems that attempt to combine several architectures into one system (e.g., combination of client-server systems with mainframe processing). Resource use and customizability tend to vary in tandem; the greater the flexibility of the system to meet unique user needs, the greater the cost outlay for capital and/or additional FTEs.

***

Relationship of Resource Use and Customizability Based on System Architecture Selected

Values range from one (low) to four (high) stars
Architecture Hospital resource use Customizability
Off-site processing * *
Turnkey systems ** **
Mainframe systems *** ***
Client-server *** ****

***

The Possibilities

The basic system architecture possibilities are as follows:

Off-site (remote) processing: In this case the hospital contracts with a vendor external to the hospital. The hospital sends data over to the vendor site where the actual processing takes place. When processing is complete, the vendor sends the data back to the hospital, usually in electronic form.

Turnkey systems: A vendor provides the hospital with systems that are “pre-packaged” so that hospital-based system development is minimal. Limited customization of the system is possible using systems analysts or programmers.

Mainframe systems: Most applicable to large hospitals, this configuration is highly centralized. A large and powerful computer performs basically all the information processing for the institution and connects to multiple terminals that communicate with the mainframe to display the information at the user sites. Hospital IT departments usually use in-house programmers to modify the core operating systems or applications programs such as billing and scheduling programs.

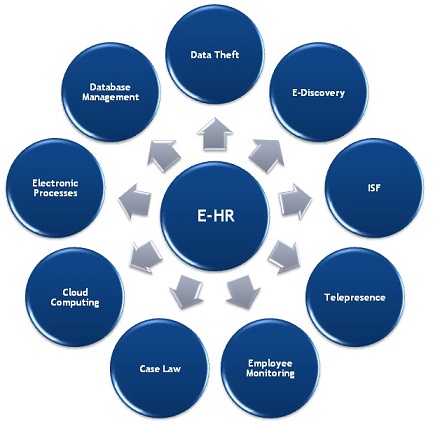
eHR diagram

Client-server systems: In this configuration one or more “repository” computers exist, known as “servers,” that store large amounts of data and perform limited processing. Communicating with the server(s) are client workstations that perform much of the data processing and often have graphical user interfaces (GUIs) for ease of use. Both customizability and resource use is high, depending on the desired sophistication.

Many clinical information systems that process data directly related to patient care use this configuration.  For instance, the Veterans Health Administration, which has implemented what is likely the largest integrated healthcare information system in the United States, uses client-server architecture.  Known as the Veterans Health Information Systems and Technology Architecture (VistA), this system provides technology infrastructure to about 1,300 care facilities, including hospitals and medical centers, outpatient facilities, and long-term care centers.  VistA utilizes a client-server architecture that links together workstations and personal computers using software that is accessed via a graphical user interface.

Overall, for hospitals that have the financial and manpower resources for a significant investment in IT, client-server architectures are the fastest-growing and typically the most preferred of the system architectures, due in large part to their local adaptability and flexibility to meet changing hospital and medical center needs.

Broad Categories

The above architectures are broad categories.  Modifications and combinations of the above also exist, such as the use of client-server technology with mainframe systems and the addition of wireless technology, smart phones, laptop PCs and tablets,  and various personal digital assistants (PDAs) to supplement the core computing functionality.

In considering the optimal architecture for a hospital, management needs to take into account factors such as size of the institution, desired sophistication of the application, IT budget, and anticipated level of user community involvement.

Assessment

EHR

Another important aspect of HIS is the need for integration.  Often, different hospital departments have their own stand-alone systems — such as a Laboratory Information System (LIS) and pharmacy systems — that do not communicate with each other.  Duplicate data may be kept in separate systems, creating additional work to enter the data multiple times.

In an integrated system, each departmental system communicates with the other systems through either a centralized or decentralized. A computerized physician order entry (CPOE) system, for example, would be much less effective if it did not communicate electronically with the pharmacy system that would process the medication orders.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

NOTES: Resource use refers to the need for FTEs and hospital capital expenditure. Customizability refers to the ability for users to alter the system structure or function to meet the unique needs of the institution.

Product Details

Product DetailsProduct Details

Product Details

On Money Withdrawn from Tax-Deferred Accounts before Age 59½

Join Our Mailing List 

For Doctors … Un-Locking the Money

By SHIKHA MITTRA; MBA, CFP®, CRPS®, CMFC®, AIF®

Shikha-MittraWithdrawing funds from a tax-deferred retirement account before age 59½ generally triggers a 10% federal income tax penalty; all distributions are subject to ordinary income tax.

However, there are certain situations in which you are allowed to make early withdrawals from a retirement account and avoid the tax penalty. IRAs and employer-sponsored retirement plans have different exceptions, although the regulations are similar.

IRA Exceptions

  • The death of the IRA owner: Upon death, your designated beneficiaries may begin taking distributions from your account. Beneficiaries are subject to annual required minimum distributions.
  • Disability: Under certain conditions, you may begin to withdraw funds if you are disabled.
  • Unreimbursed medical expenses: You can withdraw the amount you paid for unreimbursed medical expenses that exceed 10% of your adjusted gross income in a calendar year. Individuals older than 65 can claim expenses that surpass 7.5% of adjusted gross income through 2016.
  • Medical insurance: If you lost your job or are receiving unemployment benefits, you may withdraw money to pay for health insurance.
  • Part of a substantially equal periodic payment (SEPP) plan: If you receive a series of substantially equal payments over your life expectancy, or the combined life expectancies of you and your beneficiary, you may take payments over a period of five years or until you reach age 59½, whichever is longer, using one of three payment methods set by the government. Any change in the payment schedule after you begin distributions may subject you to paying the 10% tax penalty.
  • Qualified higher-education expenses: For you and/or your dependents.
  • First home purchase, up to $10,000 (lifetime limit).

lock

Employer-Sponsored Plan Exceptions

  • The death of the plan owner: Upon death, your designated beneficiaries may begin taking distributions from your account. Beneficiaries are subject to annual required minimum distributions.
  • Disability: Under certain conditions, you may begin to withdraw funds if you are disabled.
  • Part of a SEPP program (see above): If you receive a series of substantially equal payments over your life expectancy, or the combined life expectancies of you and your beneficiary, you may take payments over a period of five years or until you reach age 59½, whichever is longer.
  • Separation of service from your employer: Payments must be made annually over your life expectancy or the joint life expectancies of you and your beneficiary.
  • Attainment of age 55: The payment is made to you upon separation of service from your employer and the separation occurred during or after the calendar year in which you reached the age of 55.
  • Qualified Domestic Relations Order (QDRO): The payment is made to an alternate payee under a QDRO.
  • Medical care: You can withdraw the amount allowable as a medical expense deduction.
  • To reduce excess contributions: Withdrawals can be made if you or your employer made contributions over the allowable amount.
  • To reduce excess elective deferrals: Withdrawals can be made if you elected to defer an amount over the allowable limit.

Assessment

If you plan to withdraw funds from a tax-deferred account, make sure to carefully examine the rules on exemptions for early withdrawals. For more information on situations that are exempt from the early-withdrawal income tax penalty, visit the IRS website at www.irs.gov.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

About the Author 

Shikha Mittra has two decades industry experience working with physicians, dentists and top level executives in both public and private sector businesses and foundations; with several awards for her work. She was rated one of the top Financial Planners in the Country from 2006 – 2013. As a Certified Financial Planner®, she is also a Chartered Mutual Fund Counselor®, Chartered Retirement Plan Specialist® and Certified Cash Balance Consultant. Ms. Mittra is Adjunct Professor of Finance and Business, Rutgers University, New Brunswick, NJ; Regional Board Member of the National Association of Personal Financial Advisors NAPFA (2011-2013)  Board of Trustees of Financial Planning Association of New Jersey Chapter (2008-2011), Advisory Board Member of the ”Journal of Financial Planning” (2008-2009). Medical Economics listed her as a best financial advisor for doctors in 2012. Ms. Mittra is also an Accredited Investment Fiduciary® helping employers reduce their fiduciary liability by following global fiduciary standards of care in managing their retirement plans.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

UNDERSTANDING THE ALLOCATION OF MEDICAL PRACTICE PURCHASE PRICE

Join Our Mailing List

Delineation of Various Practice Assets

[By Dr. Charles F. Fenton III JD PC]

fenton

The final purchase price of a medical practice upon sale will actually be the amalgamation of various assets of the practice.

These assets include the tangible and intangible assets. The tangible assets include the hard assets (such as computers, treatment tables, chairs and furniture, DME and x-ray machines, etc) and the soft assets (such as Q-tips, paper and cotton balls). The intangible assets will include going concern value, goodwill, and the value of any restrictive covenant.

The parties should delineate the allocation of the purchase price amongst those various categories to reach a mutual best fit with the potential tax obligations. The buyer is the one who should strive to make the allocation fit his needs as best as possible.

Generally, the sale of the assets will be ordinary income to the seller and taxed at the seller’s usual rate. The buyer will be able to depreciate the purchased items. However, the characterization of those assets and the allocated portion of the purchase price will determine how much can be depreciated and over what time period the items can be depreciated.

As a general rule, soft assets can be depreciated fully in the year of purchase. Generally, hard assets can be depreciated over a three to seven year time period, depending upon the class of the asset. Also, under Section §179, a certain dollar amount can be “expensed” or deducted in the year of purchase. The sooner and the faster that the assets can be deducted the less current taxes that the buyer will be required to pay. However, intangible assets generally must be deducted over a 15-year period. This prolongs the tax benefits of any payments characterized as such.

***

hospital

***

Nonetheless, purchase of the assets results in better tax consequences that purchase of the stock of the practice. When stock is purchased, there is no depreciation allowance allocated in the current or subsequent years. Instead, the cost of the stock becomes the “basis” of the buyer in the practice. Any gain or loss from that basis will only have tax benefits or tax consequences in the year that the stock is sold or becomes worthless.

Because of the tax consequences of the characterization of the allocations of the purchase price, it is important that the agreement delineate the portion of the practice price which is allocated to each category. Each party should further agree never to claim a different allocation in any future tax filings.

Assessment

Generally, the soft and hard assets will be valued at their current actual cash value. In no event should the purchase price allocated to the soft and hard assets exceed the actual initial cost that the seller paid for the item. The only exception to the foregoing would be if the sale involved the transfer of an appreciable asset.

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

Beware Dubious Insurance Policies for Doctors

Join Our Mailing List

Careful Consideration is Required

[By Dr. David Edward Marcinko MBA MBBS] http://www.CertifiedMedicalPlanner.org

Dr. David E. Marcinko MBAThe following insurance policies should be carefully considered before purchase, since they may be unnecessary, too expensive, provide only minimal benefits, or be duplicated in your other policies.

The Culprits

Disclosure: I was a licensed insurance agent for more than a decade.

So, the culprits include: credit life or home mortgage insurance  (decreasing term), life insurance for children, accident policies for students, hospital indemnity policies, dread disease insurance, credit card insurance, pet health insurance, life insurance for the elderly, funeral insurance, flight insurance, pre-paid legal insurance and most extended warranties on automobiles, televisions, stereos, home computers; other gadgets and the like.

New wave Health 2.0 culprits include: terrorist insurance, cyber security insurance and reputation management policies.

Assessment

On the other hand, the following types of coverage may be important, for some medical professionals, and in selected cases: trip cancellation insurance, termite insurance and flood and earthquake insurance.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

***

Insurance

***

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

*** Risk Management, Liability Insurance, and Asset Protection Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

The Cost of Headaches

Join Our Mailing List

Treatment Expenses 1999-2010

By http://www.MCOL.com

Headaches

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

An Educational Niche Resource Supporting Doctors and their Consulting Advisors

Join Our Mailing List

By Eugene Schmuckler PhD MBA MEd CTS [Academic Provost]

About the Medical Executive-Post

We are an emerging online and onground community that connects medical professionals with financial advisors and management consultants.

We participate in a variety of insightful educational seminars, teaching conferences and national workshops. We produce journals, textbooks and handbooks, white-papers, CDs and award-winning dictionaries. And, our didactic heritage includes innovative R&D, litigation support, opinions for engaged private clients and media sourcing in the sectors we passionately serve.

Through the balanced collaboration of this rich-media sharing and ranking forum, we have become a leading network at the intersection of healthcare administration, practice management, medical economics, business strategy and financial planning for doctors and their consulting advisors. Even if not seeking our products or services, we hope this knowledge silo is useful to you.

In the Health 2.0 era of political reform, our goal is to: “bridge the gap between practice mission and financial solidarity for all medical professionals.”

More: Letterhead.iMBA_Inc.

***

niche

 ***

Enter the Certified Medical Planners™

There is no certification program, course of study or professional designation for FAs who wish to enter the lucrative financial planning space serving physicians and healthcare professionals.

That’s why the R&D efforts of our governing board of physician-directors, accountants, financial advisors, academics and health economists identified the need for integrated personal financial planning and medical practice management as an effective first step in the survival and wealth building life-cycle for physicians, nurses, healthcare executives, administrators and all medical professionals.

Now – more than ever – desperate doctors of all ages are turning to knowledge able financial advisors and medical management consultants for help. Symbiotically too, generalist advisors are finding that the mutual need for extreme niche synergy is obvious.

But, there was no established curriculum or educational program; no corpus of knowledge or codifying terms-of-art; no academic gravitas or fiduciary accountability; and certainly no identifying professional designation that demonstrated integrated subject matter expertise for the increasingly unique healthcare focused financial advisory niche … Until Now!

Enter the Certified Medical Planner™ charter professional designation. And, CMPs™ are FIDUCIARIES, 24/7.

FAs

Video: http://vimeo.com/84247360

An Interview with Bennett Aikin AIF®

Physician-Investors and the “F” Word

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

How may we assist you?

← Back

Thank you for your response. ✨

On Nursing Assistants

Join Our Mailing List

Occupational Injuries for 2013

By http://www.MCOL.com

***

nursing accidents***

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details


2015 Could Be Rough on Stocks?

Join Our Mailing List

Here’s Why!

Daniel Crosby PhDBy Daniel Crosby, Ph.D.

“In the short run, the market is a voting machine but in the long run, it is a weighing machine.” – Benjamin Graham

***

Believing as I do in the sage advice of Mr. Graham, I recently set out to quantify my growing unease with the heights obtained by the bull market of the last five-plus years. As you read below, please realize that this is not a forecast or prognostication about what will happen – especially not in the short term. Timing the market on any sort of a short-term basis is a fool’s errand, as is deviating from your specific financial plan on the advice of a stranger.

Consider this more of a “Where are we at?” with respect to market valuations, secure in the knowledge that times of sensational highs and lows tend to be fleeting and that the market has a tendency to mean-revert (that is, become a weighing machine) in the long term. Having now sufficiently hemmed and hawed my way through the legal stuff – let me say that I find the market significantly overvalued and think that some sort of defensive measures will be wise for most investors in the year(s) to come.

The Levels

To corroborate this belief, I’d like to present you with four measures of market value, all at historically high levels. They are:

  1. Shiller Cyclically Adjusted Price to Earnings Ratio (CAPE)

What it is – The work of Nobel Prize winning behavioral economist Robert Shiller, the CAPE is the price/earnings ratio based on average, inflation-adjusted earnings for the previous ten years.

What it says – The CAPE currently sits at 27.2, 63.9% higher than its’ historical mean of 16.6. The CAPE has only crested or approached 27 three other times – 1929, 1997-2000, and 2007.

What it means – The CAPE is a poor predictor of short-term market movements (most everything is), but is much more reliable in speaking to the long term return horizon. Using Shiller’s own expected return formula (taken from value investing site GuruFocus), yields an expected return over the next 8 years of .3%. What is much more informative than a single prediction, however, is considering the range of possible distributions for the longer term, which are as follows:

Scenario Returns for next 8 years from today

Really Lucky 5.2%

Lucky 3%

Unlucky -3%

Really Unlucky -7.5%

It is certainly worth noting that even the “Really Lucky” scenario that might play out over the next 8 years vastly underperforms the market average.

  1. S&P 500 Price to Earnings Ratio

What it is – A simple measure of the price paid for every dollar of earnings among some of the best capitalized and most liquid US securities.

What it says – The current P/E ratio of the S&P 500 is 19.96, well above it’s historical mean of 15.53 and median of 14.57.

What it means – As with the Shiller CAPE, greatly elevated levels of price to earnings have signaled a much lower return environment in the years to come. Ned Davis research has done the math on times when the market has been over or undervalued relative to fundamentals and has discovered the following:

Returns of S&P 500 Percentage Over/Under Valued (3-31-1926 to 5-31-2014)

More than 20% Overvalued (parentheses denote negative returns)

6 months – (.2)

1 year – (3.6)

2 years – (1.6)

3 years – 6.8

More than 20% Undervalued

6 months – 14

1 year – 19.4

2 years – 30.1

3 years – 47.3

Market Performance

6 months – 3.9

1 year – 8

2 years – 16

3 years – 23.6

According to Ned Davis and company, we are now well over 30% overvalued, comfortably above the threshold for the paltry “Overvalued” returns you see above.

*** future***

  1. Wilshire 5000/GDP – aka, “Buffett Valuation Indicator”

What it is – A sort of price to sales marker for the broader economy, once mentioned by Buffett as his favorite measure of market valuation.

What it says – The current market cap/GDP ratio sits at 127.3%, which is more than two standard deviations from the mean value of 68.8%.

What it means – Given historical returns from this significantly elevated level of market cap to GDP, the predicted return for ’15 is .7%, which includes dividends. Drawing on Buffett’s comments, GuruFocus considers a 75 to 90% ratio fair value, with 90 to 115% modestly overvalued and anything over 115% significantly overvalued. The only other time since 1950 that this indicator has broken past two standard deviations of overvaluation is, you guessed it, in the run up to the 2000 crash.

  1. Crosby Irrationality Index

What it is – A measure of market sentiment that is comprised of sub-measures of volatility, valuation, fund flows, momentum and interest rate spreads.

What it says – The CII has spent all of 2014 at a level of elevated optimism just short of mania. While valuations have driven the score up, it has not reached “manic” levels, largely as a result of this having been “the most hated bull run in history.”

What it means – The CII provides one and three year projections based on the current levels of market sentiment. These projections should be understood less as specific predictions and more as headwinds or tailwinds to growth. The current projections are for slightly negative (-1.001) returns this year that persist even three years down the road (-2.6266).

Caveats

As with any measure, those listed above are subject to a number of failings. The CAPE includes data from the Great Recession that skew the results, a number of the measures fail to account for the interest rate environment, and so on. While no single measure is flawless, when so many measures point in the same direction, I believe it is worth taking note.

This information in and of itself is meaningless but should take on meaning as you discuss your individual needs with your advisor (you DO have an advisor, right?).

More:

For very long-term investors, even profound hiccups in the market may be little more than a contrarian buying opportunity. After all, there are more fun and important things to do in life than obsess over financial footnotes.

Assessment

But for those nearing retirement, an unambiguous picture seems to be emerging that returns for the next 8 to 10 years are likely to be depressed in light of the eye-popping returns of the more recent past. Do not act in haste or deviate from your plan if one is in place, but please accept this gentle warning from a concerned party who knows that “this time is never different.”

Even More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

Psychopathy and the Medical Profession

Join Our Mailing List 

Psychopathy Everywhere?

A SPECIAL ME-P REPORT

By Michael Lawrence Langan MD

Psychopathy is present in all professions.

In The Wisdom of Psychopaths: What Saints, Spies, and Serial Killers Can Teach Us About Success, Kevin Dutton provides a side-by-side list of professions with the highest (CEO tops the list) and lowest (care-aid) percentage of psychopaths.

Interestingly surgeons come in at #5 among the professions with the highest percentage of psychopathy while doctors  (in general) are listed among the lowest [more ……>]

Psychopathy and the Medical Profession

 holloween

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

On Hospital Endowment Fund Management

Join Our Mailing List

A Case Model Example

[By Dr. David Edward Marcinko MBA]

http://www.CertifiedMedicalPlanner.org

DEM at Wharton

Just as the field of medicine continuously changes, so too does the field of endowment management.

Endowment managers continue to increase their knowledge of the science and expand their skill in the art.

However, successful endowment managers will continue to focus on the areas that they can control in order to minimize the risk of the areas they cannot.

***

So, here is a case model to show you how it is done.

[Case Model]

Endowment Fund

***

hospital

Invite Dr. Marcinko

***

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

***

“Crowd-Sourced” Health Predictions for 2015

Join Our Mailing List

The “Gift of Wonder” Flip Book

A SPECIAL ME-P REPORT

[Download and share your free copy]

GG_HiRes1

 By Gautam Gulati MD

Gosh. What a year it’s been!

2014 was a wild ride filled with the unexpected, unimaginable, and unusual. And you know what? I wouldn’t have had it any other way.

So what’s in store for 2015?

All the healthcare futurists and pundits are taking stabs at predictions with the odds of a poorly played roulette table.  In reality your guess is as good as mine. So I decided to have some fun with it this year and opened up predictions to the community-at-large.

The results are finally in

So, to all those who have inspired me over the years to do the unimaginable, the impossible, and the unusual, I say thank you and offer you a small token of appreciation to stir your sense of wonder and curiosity into the New Year.

Please accept this “Gift of Wonder” – a crowdsourced flip book of the community’s wildest predictions for health in 2015.

I hope you enjoy it and I wish you all an unusual new year full of hope, wonder, and curiosity! Please pass-it-on and pay-it-forward!

With sincere admiration for all my readers and supporters who inspire me everyday.

***

Giving a Gift of Wonder

Crowdsourced Health Predictions for 2015 (download and share your free copy)

***

About the Curator

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

 Product DetailsProduct Details

Product Details

How employees can acquire hospital securities without cash activity

Join Our Mailing List 

On discounted stock-purchase programs

[By Dr. David Edward Marcinko MBA CMP™]

DEM blueTo alleviate cash-flow problems of their employees, hospitals who want them to take part in a discounted stock-purchase program may lend the money to the employees to pay any taxes due and any purchase price for the stock.

Full recourse liability

However, it is important that any such loan be subject to a full recourse liability; if the loan is secured by the stock on a non recourse basis, the transaction may be treated as if it were a grant of an option, and thus there would be no transfer of property until the loan is paid.

The rationale for treatment as an option is that if the property drops in value below the amount of the debt, the employee will not pay the debt and walk away from the property, as he would an option. Thus, until the note is paid, no transfer has occurred. This could negate the effect of a Section 83(b) election.

Example:

The following example demonstrates how the use of employer loans, in connection with a Section 83(b) election, can be used to great advantage to an employee.

The employer in the example on Section 83(b) election (above) lends the employee the cash necessary to meet the income tax liability of the $10,000 grant at 30%, or $3,000. The employee gives the employer a promissory note for $3,000, bearing interest at 8%.

Thus, the employee acquires $100,000 worth of employer stock ownership after five years with no out-of-pocket cost at the date of the grant and an interest cost of approximately $1,300, payable over five years.

***

Hospital

***

Assessment

Of course, in lieu of making a loan to the employee, the employer can simply agree to give the employee, as a bonus, sufficient cash to cover the tax liability. This is obviously more costly to the employer, as it results in the employee acquiring stock at no out-of-pocket cost.

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

Foreword Dyken MD MBA

Some Academic Views of Financial “RISK” Tolerance

Join Our Mailing List 

The Psychological Studies

[By Staff Reporters]

Understanding risk tolerance should not be a guessing game especially when dozens of academic studies can point us in the right direction. Below are 2 important academic studies in the field of risk tolerance.

  1. Measuring the Perception of Financial Risk Tolerance: A Tale of Two Measures – John Gilliam, Swarn Chatterjee and John Grable – 2010

This study compares the explanatory power of a simple question about risk versus a multi-dimensional 13-item questionnaire when trying to understand someone’s risk tolerance. Unsurprisingly the multi-dimensional questionnaire showed better results. The research helps explain why advisors should not be using boilerplate questionnaires.

Link to paper

  1. Insights from Psychology and Psychometrics on Measuring Risk Tolerance – Michael Roszkowski, Geoff Davey, John Grable – 2005

This paper re-enforces previous studies that show risk tolerance can be measured as long as the questionnaire is long enough and asks good questions (doesn’t mix in questions about risk capacity and risk needs).

Link to paper

More:

***

Risk[RISK TOLERANCE v. RISK AVERSION]

***

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

Doctor – What Do You Say When People Ask, “What Do You Do?”

Join Our Mailing List

The Lesson of Magnets?

VR MD

[By Vicki Rackner MD]

http://www.CertifiedMedicalPlanner.org

Whether you’re a clinic employee or a private practitioner, you reap the greatest career satisfaction when you see more of your best-fit patients. How do you attract them?

Magnets

Magnets offer an important lesson.

Depending on the orientation, two magnets will either attract or repel each other.  The strength of the magnetic force is called the magnetism.

The way you present yourself to would-be patients, referring physicians and other SENDERS–people who send you patients– will either attract them or repel them.

Your goal is to optimize your magnetism so you will attract the attention of people you want to engage.

It begins with hello. They say you only have one chance to make a first impression.

One of the first questions people ask you at a social event is, “What do you do?”  To generate referrals, answer in a way that increases the chances of attracting your best-fit patients to your practice. You want your listener to say, “Wow!  I know someone who needs to see you!”

***

Magnets

***

The Three Answers

There are three ways of answering this question:

  1. By title: You could say, “I’m a rheumatologist” or “I’m a pediatrician.”

The problem with this approach is that your title brings an image to the mind of the listener over which you have little control.

I was at a wedding when a budding Barbara Walters-type  started interviewing me.  This child said to me, “You’re a doctor.”  I nodded.  She asked , “What kind of doctor?”  I told her, “I’m   a surgeon.”  She asked “What kind of surgeon?”  I told her,  “A   general surgeon.”  Her eyes got big as saucers as she said, “Oh, you’re the person who puts those warning labels on the cigarette packs!”

  1. By diagnostic and therapeutic activity: You could say, “I treat orthopedic injuries.”  or “I treat diseases of digestion.”

The problem with this approach is that you’re asking your listener to become a diagnostician. Is their mother’s sub-sternal burning angina or acid reflux?

  1. By result:  You could say, “I help women make a gracious transition through menopause.”  Or , “I help parents set their kids up for a life of health.”  This is the approach with the highest magnetism score.

The most attractive positioning statement answers these three questions:

  • Whom do you help?
  • What results do you help people get?
  • Why is this result important ?

Ideally you craft a simple, memorable, repeatable sound bite.  You and your staff members use it.  People calling your office repeat it.

Assessment

The most magnetic positioning statements are deceptively simple.  Keep working at it.  You’ll know when you’ve found yours.  You pique the curiosity of your listener.  They want to learn more

About the Author

Vicki Rackner MD, author, speaker, ME-P thought-leader and President of Targeting Doctors, helps financial advisors accelerate their practice growth by acquiring more physician clients. She calls on her experience as a practicing surgeon, clinical faculty at the University of Washington School of Medicine and nationally-noted expert in physician engagement to offer a bridge between the world of medicine and the world of business.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Laudable Physicians and Shameful Doctors of 2014

Join Our Mailing List

Physicians of the Year [Best and Worst‏]

[From Medscape]

Which physicians made us proud this year and which made us cringe? See who made the list and what they did to make the hall of fame (or shame).

Physicians of the Year

[Of Saints and Sinners]

Here is the list according to Medscape.

ImageProxy

Link: https://login.medscape.com/login/sso/getlogin?urlCache=aHR0cDovL3d3dy5tZWRzY2FwZS5jb20vZmVhdHVyZXMvc2xpZGVzaG93L3BoeXNpY2lhbnMtb2YtdGhlLXllYXIyMDE0P3NyYz13bmxfZWRpdF9zcGVjb2w=&ac=402&uac=193200AX

More:

OIG Most Wanted Fugitives: https://oig.hhs.gov/fraud/fugitives/index.asp?ref=widget

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Where There’s Smoke?

Join Our Mailing List

Cytisine versus Nicotine Replacement Therapy

[By staff reporters and Rena Xu]

Doctors and financial advisors know that motivation is often half the battle of behavior change.  In the battle against nicotine addiction however, motivation alone may not be enough.  Mass media campaigns have helped to raise awareness about the dangers of smoking. We’ve even mentioned them on this ME-P

But, for the majority of smokers who already want to quit, the question remains: how?

smoke

Where There’s Smoke: Cytisine versus Nicotine Replacement Therapy

Assessment

We thought the non-healthcare readers of this ME-P might enjoy seeing how a practicing doctor is “detailed”; or informed about a new drug or treatment. In the past, drug “reps” accomplished this task in the office; “eye-2-eye” with folders and flip-charts, etc.

Today; not so much in the digital era!

And, insightful FAs realize the similarity to “wholesalers” in the financial services industry.

More:

Chest pain

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

About Crowd-Med [Case Review Service]

***
CMP logo
***
DR. DAVID EDWARD MARCINKO MBA
[By ME-P Staff Reporters]

CrowdMed Company Background

CrowdMed purports to harnesses the wisdom of crowds to collaboratively solve even the world’s most difficult medical cases quickly and accurately online.

The company offers individuals, insurance providers, and self-insured corporate customers the ability to more quickly diagnose medical conditions and reduce healthcare costs without compromising care.

***

152_1

***

The results speak for themselves?

Since launching publicly in April 2013, CrowdMed has helped solve hundreds of medical cases for patients around the world, and this number is quickly growing as word spreads of the new service. On average, these patients had been sick for 8 years, seen 8 doctors, and incurred more than $50,000 in medical expenses. Despite the difficulty of their cases, more than half of these patients tell us that the crowd successfully brought them closer to a correct diagnosis or cure.

Anyone can submit a case on the CrowdMed website for free (with a $50 refundable deposit), or along with a cash compensation offer to draw more attention to their case. They use incentives to increase participation, and the overall quality and confidence levels of suggested diagnoses. Thousands of people with diverse backgrounds in medicine, health care, education and research have already joined the crowd, and they are continually recruiting new medical and disease experts to help solve cases.

During early testing of the CrowdMed platform, the founder [Jared] submitted his own sister’s [Carly] anonymous case information to the crowd to test the system. More than 300 people participated, evaluating the same symptoms that had been provided to Carly’s original doctors. In just three days, the crowd gave Jared their answer: Fragile X-associated primary ovarian insufficiency

Founded by veteran technology entrepreneur Jared Heyman and based in San Francisco, CA, CrowdMed has received more than $2.4 million in funding from some of Silicon Valley’s top venture capital firms including NEA, Andreessen Horowitz, Greylock Partners, SV Angel, Khosla Ventures and Y Combinator. The company’s advisors have founded and run some the world’s most successful online healthcare companies including WebMD. CrowdMed graduated from Y Combinator’s Winter 2013 class, and was officially launched during the TEDMED 2013 conference in Washington DC.

You can read more about CrowdMed’s leadership team click here.

More:

  1. Will Future Doctors Need a Medical License?
  2. Is Medical Licensing Really Necessary?
  3. On Replacing Doctors with Computers and Smart Phones 

Assessment

Check em’ out today: http://blog.crowdmed.com

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

The Resurgence of Polygraph “Lie-Detection” in an age of Evidence-Based Medicine

Join Our Mailing List

On Junk-Science in the Medical Profession

A SPECIAL ME-P REPORT

By Michael Lawrence Langan MD

***

If you are ever asked to take a polygraph test–don’t do it. Those involved in the criminal justice system, including lawyers, are largely uneducated in the realm of scientific scrutiny and experimental methodology.

They may not separate science and pseudo-science, and erroneously believe that the polygraph is an accurate scientific instrument. Their interactions are with polygraph examiners who proselytize its use, and they have little or no interaction with scientists, psychologists, and physicians who refute its use.

Refuse to take the test and educate them. Cite the Frye Doctrine, go to the medical library, copy the scientific articles which belie its validity, and present them to whomever requested you to take the test. State that the principles and assumptions underlying polygraphy are not supported by our understanding of psychology, neurology, and physiology.

*** Polygraph_Test_-_Limestone_Technologies_Inc***

Junk-Science in the Medical Profession: The Resurgence of Polygraph “Lie-Detection” in an age of Evidence-Based Medicine.

Assessment

Then, put the burden of proof on their heads. Tell them to present you with scientific evidence that corroborates the validity of the test. There is simply no rational basis for a machine to detect liars.

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

poly

About the Author

Dr. Langan graduated from Oregon Health Sciences University School Of Medicine, Portland Oregon with an MD 21 years ago. He had his residency training of Geriatric Medicine-Internal Medicine at Beth Israel Deaconess Medicine Center and Internal Medicine at St Vincent Hospital Medicine Center.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product Details

On Happiness and Discretionary Spending

Join Our Mailing List 

Can Money But Happiness? [The age old question]

By Rick Kahler MS CFP® http://www.KahlerFinancial.com

Rick Kahler MS CFPGiving away money makes people happy; especially during this holiday season.

Spending money on others makes people happier than spending money on themselves. Spending money on experiences makes people happier than spending money on things.

Does that mean it’s okay to max out your credit card to take all 37 members of your extended family on a cruise for Christmas? Not exactly.

The Research

Yes, research shows that some kinds of spending are linked to happiness. Andrew Blackman cites some of that research in an excellent article, “Can Money Buy Happiness?“, published online November 10 in The Wall Street Journal.

Before you pull out the plastic and start shopping, though, there’s one important point to keep in mind: Any spending to create happiness must come from your discretionary money. This is money we have available to spend for our lifestyle, after we’ve paid all our fixed expenses like rent, loan payments, utilities, retirement contributions, building emergency reserves, insurance premiums, etc.

Discretionary spending can include luxuries or extras like eating out, vacations, gifts, entertainment, and gadgets of all types. But it also can include items that may be necessities or fixed expenses like housing, vehicles, clothing, and food. For example, owning a car is a necessity for most South Dakotans.

However, a 10-year-old Toyota Avalon with 90,000 miles on the odometer, well maintained, can transport you just as effectively as a new model. The older model costs around $10,000; the new one costs around $35,000. The $25,000 difference is discretionary spending.

So, if you want more discretionary money for happiness spending, like giving or experiences, you might choose to spend more frugally on necessities. The other option, borrowing for happiness spending, generally doesn’t work. Research finds that borrowing and debt creates unhappiness that pretty much cancels out the happiness created by the spending.

***

UnHappiness

***

The Psychologist

Elizabeth Dunn, associate professor of psychology at the University of British Columbia and co-author of the book Happy Money, puts it this way in The Wall Street Journal article: “Savings are good for happiness; debt is bad for happiness. But, debt is more potently bad than savings are good.”

In a series of studies, Professor Dunn found that the spending producing the highest amount of happiness was spending on others. She found it wasn’t the dollar amount given but the perceived impact of the gift that mattered. Seeing your money make an impact in someone’s life will produce happiness, even though the gift is very small.

Life Experiences

The impact experiences have on our lives may be the reason we gain more happiness from experiences than from material things. Even though we tend to see tangible things as offering more value, the memories and learning we gain from experiences actually provide more happiness.

Creating experiences can involve the purchase of some stuff. Buying baseball equipment with the intention of playing with your children is one example. Buying a camper or a boat for shared family experiences is another. Of course, buying stuff to be used in creating experiences only creates happiness if you use it. We don’t gain much happiness from sports equipment gathering dust in the basement or a camper abandoned in the back yard.

Pro-Bono Medical Care?

More:

Assessment

After reading this research on the value of spending on giving and experiences, I came up with what might be the ultimate happiness spending scenario: Giving the gift of an experience that includes both the recipient and the giver. While I haven’t found any research validating that hypothesis, I am guessing this may be the perfect happiness two-for-one.

Maybe, if you can afford it out of discretionary money, taking the family on that cruise isn’t such a bad idea after all.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Why You’re Probably Using the Wrong [Medical] Dictionary [er…ah…Tchotchkes?]

About the iMBA Inc, Health Glossary and Administration Dictionary Series … with Book Reviews

[By Staff Reporters]

HDS

***

The Health Dictionary Series of Administrative Terms and Definitions

According to James Somers, the way we use an ordinary [medical] dictionary is to look up words, acronyms or initialisms we’ve never heard of; or whose sense we’re unsure of, or need more clarification or spelling direction. Makes sense!

http://jsomers.net/blog/dictionary

But, you would never look up health administration industry specific words or terms in an ordinary medical dictionary — words like HL7, “meaningful-use”, “skinny networks”, managed care organization, hospital cloud computing, patient portal, stop-loss ratio, economic externality, PHO, MPT, SAR-BOX, Fama-French, US Patriot Act, the Treynor index, Asset Pricing Theory, PP-ACA, or ACOs — because all you’ll learn is nothing about what they mean.

Extreme Utility – Not just tchotchkes! 

You would need an industry specific dictionary of health administration terms and definitions, right? And, preferably designated as a Doody’s Core Title for credibility, and written by leading experts.

So; try these 3 dictionaries for 10,000 health 2.0 administration terms and definitions, EACH.

  1. Dictionary of Health Insurance and Managed Care
  2. Dictionary of Health Economics and Finance
  3. Dictionary of Health Information Technology and Security

Product DetailsProduct DetailsProduct Details

Dictionary Forewords

More:

Forget the Paper Weights

According to Wikipedia, a tchotchke (/ˈtʃɒtʃkə/ CHOCH-ka) is a small bauble or miscellaneous item. The word has long been used by Jewish-Americans and in the regional speech of New York City and elsewhere. Tchotchkes are often given at Chanukkah as part of a game.

The word may also refer to free promotional items dispensed at financial services trade shows, medical conventions, and similar large events. They can also be sold as cheap souvenirs which are sometimes called “tchotchke shops”.

***

paperweights

***

Not a Throw-Away

But, if you want to give your hospital, medical clinic or physician clients an advertising item that’s both useful and handy at the same time, try using these dictionaries. Make an IMPACT, and forget those paper-weights.

As a Financial Advisor [FA], or drug rep, you can represent your eagerness to be there for clients and prospects anytime they need your service by having the dictionaries engraved or placing your business card, inside. Plus, they serve as a great addition to a wonderfully decorated medical office or home library. It is an item they will refer to again and again; not just throw-away.

Give one … or all three … they are so reasonably priced.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

Retirement Planning and Physicians [An Oxymoron]?

Join Our Mailing List 

Confidence Eluded

By Shikha Mittra MBA CFP® AIF® http://www.feeonlynetwork.com/Shikha-Mittra

Shikha-MittraAccording to a survey from the Employee Benefit Research Institute [EBRI] and Greenwald & Associates; nearly half of workers without a retirement plan were not at all confident in their financial security, compared to 11 percent for those who participated in a plan, according to the 2014 Retirement Confidence Survey (RCS).

Retirement Money

In addition, 35 percent of workers have not saved any money for retirement, while only 57 percent are actively saving for retirement. Thirty-six percent of workers said the total value of their savings and investments—not including the value of their home and defined benefit plan—was less than $1,000, up from 29 percent in the 2013 survey. But, when adjusted for those without a formal retirement plan, 73 percent have saved less than $1,000.

Debt

Debt is also a concern, with 20 percent of workers saying they have a major problem with debt. Thirty-eight percent indicate they have a minor problem with debt. And, only 44 percent of workers said they or their spouse have tried to calculate how much money they’ll need to save for retirement. But, those who have done the calculation tend to save more.

Shifting Demographics

The biggest shift in the 24 years has been the number of workers who plan to work later in life. In 1991, 84 percent of workers indicated they plan to retire by age 65, versus only 9 percent who planned to work until at least age 70. In 2014, 50 percent plan on retiring by age 65; with 22 percent planning to work until they reach 70.

***

z93

*** 

Physician Statistics

Now, compare and contrast the above to these statistics according to a 2013 survey of physicians on financial preparedness by American Medical Association [AMA] Insurance.

The statistics are still alarming:

  • The top personal financial concern for all physicians is having enough money to retire.
  • Only 6% of physicians consider themselves ahead of schedule in retirement preparedness.
  • Nearly half feel they were behind
  • 41% of physicians average less than $500,000 in retirement savings.
  • Nearly 70% of physicians don’t have a long term care plan.
  • Only half of US physicians have a completed estate plan including an updated will and Medical directives.

Assessment

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

About Peer-to-Peer Lending [P2PL]

Join Our Mailing List 

What it is – How it works?

big_picBy TIMOTHY J. McINTOSH; MBA, MPH, CFP®, CMP™ [Hon]

Similar to private equity or venture capital, peer-to-peer lending [aka person-to-person lending, peer-to-peer investing and social lending] is the practice of lending money to unrelated individuals without the benefit a traditional financial intermediary like a bank or financial institution. P2P lending takes place online using various platforms and credit checking tools.

And, it has been in existence for about a decade.

Here are some important characteristics:

  • P2PL offers a chance to get a lower interest rate than a bank, and gives investors a chance to receive higher returns. Of course, more rewards means more risk.
  • The two largest P2PL companies are Prosper.com and LendingClub.com.  Prosper is older, Lending Club is bigger.  Prosper allows bidding on the interest rates you’re willing to provide a loan. Lending Club sets the rates.
  • Initial returns on Prosper were disappointing because default rates were high; today it is better. For loans originating in the last six months of 2009, both Lending Club and Prosper have a default rate (including currently late loans) of about 13.5%. Using loans from that same time period, Prosper had overall returns of 8.3% and Lending Club had returns of 4.3%.
  • Since avoiding defaults is an important part of P2PL, investors should buy many lots of notes – for as little as $25 each – which make it relatively easy to achieve broad diversification.  Compared to buying index funds and rebalancing once a year, P2PL is more time-consuming as you must pick the loans to invest in individually.  Filtering through the offered loans is time-consuming, but can be rewarding. Some investors sell off their notes at a discount once the borrower goes late on a payment for instance, or just because they need their money out of the investment before the term is up.
  • No matter how closely watched there will be a drag on returns from the cash in your portfolio.  It takes time to choose loans acceptable and then for them to be approved.  Just as with a mutual fund, this will lower your returns, perhaps as much as 1%.
  • One of the real benefits of P2PL is a low correlation with other investments, as it is different than other asset classes and ought to perform differently from equity and fixed income investments.

я74

More:

Assessment

The Author

Timothy J. McIntosh is Chief Investment Officer and founder of SIPCO.  As chairman of the firm’s investment committee, he oversees all aspects of major client accounts and serves as lead portfolio manager for the firm’s equity and bond portfolios. Mr. McIntosh was a Professor of Finance at Eckerd College from 1998 to 2008. He is the author of The Bear Market Survival Guide and the The Sector Strategist.  He is featured in publications like the Wall Street Journal, New York Times, USA Today, Investment Advisor, Fortune, MD News, Tampa Doctor’s Life, and The St. Petersburg Times.  He has been recognized as a Five Star Wealth Manager in Texas Monthly magazine; and continuously named as Medical Economics’ “Best Financial Advisors for Physicians since 2004.  And, he is a contributor to SeekingAlpha.com., a premier website of investment opinion. Mr. McIntosh earned a Bachelor of Science Degree in Economics from Florida State University; Master of Business Administration (M.B.A) degree from the University of Sarasota; Master of Public Health Degree (M.P.H) from the University of South Florida and is a CERTIFIED FINANCIAL PLANNER® practitioner. His previous experience includes employment with Blue Cross/Blue Shield of Florida, Enterprise Leasing Company, and the United States Army Military Intelligence.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners(TM)

How to Protect Your Vehicle During Long-Term Storage

 Join Our Mailing List

Hibernation and Your Luxury Car

silver balls on snow with snowfall - blue heaven

[By Dr. David Edward Marcinko MBA]

[By Nalley-Lexus Roswell, GA]

An ME-P Special Winter Report

***

DEM at Univ of Pittsburgh

***

I was speaking at a seminar in Pittsburgh PA recently, and I realized how cold it gets there. Moreover, I just learned of an impeding Christmas Eve storm this year.

Hence this ME-P.

***

Many car drivers use their vehicle every day, but from time to time – and during the winter – it’s necessary to consider long-term storage. Some physicians however, don’t use their car over the winter months, or need to leave the country for a while on vacation, and this means that it’s time to store away that luxury automobile.

The Storage Steps:

So, if you need to put your car into long-term storage, use the following tips to make sure that your vehicle remains in excellent working order.

Find a good place to store the car

You probably won’t want to leave your car exposed to the elements if you’re not going to use it. Find a sheltered place to keep the car like a garage, shed, or outhouse that can protect the vehicle from the rain. Search local ads for reasonably priced accommodation if you don’t have your own garage. If there’s nothing available, invest in a high-quality weatherproof car cover which will at least protect your car from the weather.

Thoroughly clean the car

Dirt and debris on your car may cause damage, so give the car a thorough clean before storing it. Remove bird droppings or tree sap, which can both damage paint work, and get rid of mud or oil from the wheels and fenders. Apply a good quality wax or sealant to the exterior, as this will protect the paint from any dirt or dust that accumulates in storage.

Fill up your gas tank

Some doctors and other drivers make the mistake of emptying the gas tank when they put their cars into storage.

Follow your car dealer recommendations but use premium if you can. Topping off your gas tank stops moisture from accumulating inside the tank, and will also make sure the seals don’t dry out. Gas is cheap currently, so do not forget this step.

And, consider adding a fuel stabilizer, which may protect the engine from rust and ensure the fuel doesn’t deteriorate [debatable issue].

Charge the battery

Even though you aren’t going to drive the car for a while, it’s a good idea to make sure the battery charge doesn’t run out. If you can’t get somebody to come and visit the car, charge and disconnect the battery completely.

Otherwise, you can buy a battery tender [not trickle charger] that plugs into the electricity supply and continuously gently charges the battery. I have one for my vintage 2000 Jaguar XJ-V8-XL and they are great.

Inflate your tires

It’s always a good idea to inflate your tires to the manufacturer’s recommended pressure. While the car is stationary, the weight of the vehicle pressing on the tires can cause damage, particularly in cold temperatures.

Another solution to consider is removing all four wheels and jacking the car up on all four corners. This is hard work, but it’s worth it for cars that will be stored for a month or more.

***

My Jaguar XJ-V8

***

My Jaguar***

JaguarBoot

***

Protect the car from pests

Cars give rats and mice lots of places to hide and keep warm and these creatures can cause damage if they gnaw at wires. Plug obvious places (like the exhaust pipe) where rodents could get in, and consider laying traps or poison. Make sure you close all the car windows tightly and remove any food or trash from the car that may attract pests.

Don’t cancel your insurance

Your car is a valuable asset. Even though it’s not on the road, it could still suffer damage in storage. If you cancel your insurance, you may have to pay more when you decide to start driving it again. Talk to your insurance company about the options available to you.

More:

Assessment

It’s important to prepare your car properly for long-term storage. Your vehicle is probably worth a lot of money, so protect your investment and make sure your car is just the way you left it when you come back.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

Product DetailsProduct Details

Product Details

***

A Video Presentation by Political Economic Strategist Greg R. Valliere

Join Our Mailing List

Chief Political and Economic Strategist at Potomac Research Group Holdings, LLC

Video Pod-Cast Sponsored By

  • Sharkey, Howes & Javer
  • 720 S Colorado Blvd – So. Tower, Suite 600
  • Denver, CO 80246

Dear David,

We thoroughly enjoyed our time with those of you who were able to attend our annual Client and Friends Appreciation Event.

Since then, many of you have been requesting to see Greg R. Valliere’s presentation from the event. So, we recently posted the video on our website and would like to invite you, your family and friends to view it. If you missed the event, Greg’s speech was thought provoking, insightful and is well worth a watch.

Enjoy!

SHJ

***

Watch

< Click here to watch now >

SHJ

***

About Greg R. Valliere

Greg R. Valliere is a Chief Political Strategist at Potomac Research Group Holdings, LLC. He coordinates political and economic research. Mr. Valliere focuses on how Congress and the White House shape fiscal policies and monitors the Federal Reserve Board’s interest rate policies. He has over 30 years of experience in covering Washington for institutional investors. 

Prior to joining the firm, Mr. Valliere served as Chief Policy Strategist for Soleil Securities Group Inc. He was also employed at Stanford Group Company, Research Division. He previously held key strategy roles at Charles Schwab’s Washington Research Group and The Washington Forum. 

Mr. Valliere co-founded The Washington Forum in 1974, serving as Chief Political Analyst and Editor of the group’s publications, and ultimately as Research Director. He began his career in 1972 at F-D-C reports, monitoring the pharmaceutical industry. Mr. Valliere is an exclusive commentator for CNBC, appearing regularly on network programs such as ‘Squawk Box,’ ‘Power Lunch,’ ‘The Closing Bell,’ and ‘Kudlow & Company.’ He earned his Bachelor’s degree in Journalism from The George Washington University.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants

Pitfalls with Health Care Provider Data

Join Our Mailing List

Physician Licensure and Medical Care Quality?

By http://www.MCOL.com

Data

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

A Frank Look at Physician Suicide

Join Our Mailing List

Staring Down the Enemy

[By Staff Reporters]

We have skirted around this issue before on the ME-P; as well as our related physician-executive leadership, risk-management and career development essays in our books and print publications.

But now, we look directly into the face of the terminal demon/beast.

So, her is a powerful look at the growing problem of physician suicide by two leading physicians and expert-bloggers Michael Lawrence Langan MD; an ME-P “thought-leader” – as well as a video by Pamela Wible MD.

***

suicide

***

Physician Suicide

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

 Product DetailsProduct Details

Product Details

Product Details  Product Details


About the INSTITUTE OF MEDICAL BUSINESS ADVISORS, Inc.

Join Our Mailing List

About

INSTITUTE OF MEDICAL BUSINESS ADVISORS, Inc.

  ***

The Institute of Medical Business Advisors, Inc provides a team of experienced, senior level consultants led by iMBA Chief Executive Officer Dr. David Edward Marcinko MBA CMP™ MBBS [Hon] and President Hope Rachel Hetico RN MHA CMP™ to provide going contact with our clients throughout all phases of each project, with most of the communications between iMBA and the key client participants flowing through this Senior Team.

Product Details

iMBA Inc., and its skilled staff of certified professionals have many years of significant experience, enjoy a national reputation in the healthcare consulting field, and are supported by an unsurpassed research and support staff of CPAs, MBAs, MPHs, PhDs, CMPs™, CFPs® and JDs to maintain a thorough and extensive knowledge of the healthcare environment.

Product Details

The iMBA team approach emphasizes providing superior service in a timely, cost-effective manner to our clients by working together to focus on identifying and presenting solutions for our clients’ unique, individual needs.

Product Details

The iMBA Inc project team’s exclusive focus on the healthcare industry provides a unique advantage for our clients.  Over the years, our industry specialization has allowed iMBA to maintain instantaneous access to a comprehensive collection of healthcare industry-focused data comprised of both historically-significant resources as well as the most recent information available.  iMBA Inc’s specific, in-depth knowledge and understanding of the “value drivers” in various healthcare markets, in addition to the transaction marketplace for healthcare entities, will provide you with a level of confidence unsurpassed in the public health, health economics, management, administration, and financial planning and consulting fields.

 Product DetailsProduct DetailsProduct Details

iMBA Inc’s information resources and network of healthcare industry textbook resources enhanced by our professional consultants and research staff, ensure that the iMBA project team will maintain the highest level of knowledge regarding the current and future trends of the specific specialty market related to the project, as well as the healthcare industry overall, which serves as the “foundation” for each of our client engagements.

Product Details  Product Details

Ann Miller RN MHA

www.MedicalBusinessAdvisors.com

Financial Advisor Education Letterhead CMP™

Solicitation Letterhead.iMBA, Inc

Sample iMBA Engagements

iMBA Seminar Topics

***

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

***

Understanding “Meaningful Use” Attestation Numbers for 2014

Join Our Mailing List

Providers versus Hospitals

By CMS

ME121014_PAGE_16

Assessment

So, what do the hospitals know –  that the doctors do not?

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

Product Details

Introducing the International Institute of Research Against Counterfeit Medicines

Join Our Mailing List

Launching an e-learning program on the counterfeiting of medicines

[By staff reporters]

Because with every passing day, men, women and children, your loved ones, even yourself, can be victims of counterfeit medicines.

Thousands of lives are at stake; especially with drugs produced in China. That is why the International Institute of Research Against Counterfeit Medicines (IRACM) is launching an electronic learning program on the counterfeiting of medicines.

***

IRACM

***

OBJECTIVES OF THE CAMPAIGN

• To promote and support the fight against trafficking in counterfeit medicines.
• To protect the health of patients by training and informing people.

Today, to fulfil these front line health objectives, IRACM needs you and your network to disseminate this e-learning on your digital media.

Why Counterfeit Medicines?

Check out the image below; need we say more?

***

benjamin-bills3

***

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit.

And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Assessment

Check em’ out today.

Tell us what you think?

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details


Do You Have a Taxable Investment Account – Doctor?

Join Our Mailing List

Is it Time to Harvest?

[By Lon Jefferies MBA CFP®]

Lon JeffriesTax harvesting is the process of selling assets for the purpose of creating either long-term capital gains or losses to minimize your tax bill. This procedure is usually conducted near the end of a calendar year.

While many people are familiar with the concept of tax loss harvesting, fewer physicians or clients are familiar with the more recently developed process of tax gain harvesting. Between these two procedures, virtually everyone with a taxable (not tax-advantaged) investment account should make adjustments to their portfolio before the year ends.

Who Qualifies For the 0% Capital Gains Rate?

First, it is important to understand that capital gains (the growth on investments within a taxable, non retirement investment account) are taxed differently than ordinary income (wages, pensions, Social Security, IRA distributions, etc.). While short-term capital gains (recognized on the sale of assets held less than a year) are essentially considered ordinary income, long term capital gains, or recognized gains on assets held more than a year, are taxed at advantageous tax rates. While ordinary income tax rates range from 10% to 39.6%, capital gains tax rates range from 0% to 20%.

Second, it is crucial to understand what enables a taxpayer to qualify for the 0% capital gains rate. If a taxpayer is in the 10% or 15% ordinary income tax bracket, they qualify for the 0% long-term capital gains rate.

For a married couple filing jointly, the 15% tax bracket ends at $73,800 of taxable income ($36,900 for single taxpayers). Thus, if a married taxpayer has a taxable income (which includes long-term capital gains but is also after deductions and exemptions) of less than $73,800, all their long-term capital gains will be tax free. If the taxpayer is in a tax bracket anywhere between 25% and 35% (taxable income of $73,800 and $457,600, or between $36,900 and $406,750 for single tax filers), they will pay long-term capital gains taxes at 15%. Only those in the top tax bracket of 39.6% (married taxpayers with a taxable income over $457,600 and single taxpayers with taxable income over $406,750) will pay capital gains taxes at 20%.

Tax Loss Harvesting

During the calendar year, assets have been purchased and sold in most taxable investments accounts. The sale of an asset creates a net gain or loss, both having tax implications. Investors should have an understanding of what their long-term capital gains tax rate will be so they can determine whether a taxable gain or loss is preferable.

For instance, an individual who does not qualify for the 0% capital gains tax rate may wish to minimize the amount of taxable gains they recognize during the year, which would reduce their tax bill. If the investor currently has a net long-term capital gain (which is probable after the strong year the market had in 2013), then it is likely worthwhile to sell any assets in the portfolio that are currently worth less than the investor’s purchase price. This tax loss harvesting would reduce the net gain recognized during the year and lower the investor’s tax bill.

In some cases, by taking advantage of all potential losses within a portfolio an investor has the ability to negate all capital gains created during the year, completely eliminating their capital gains tax bill. Further, the IRS will allow investors to recognize a net capital loss of up to a -$3,000 per year. This -$3,000 loss can be used to lower the taxpayers ordinary income. This is particularly advantageous in that the capital loss reduces a type of income that is taxed at higher tax rates.

Harvesting Gains

Harvesting gains from a taxable portfolio is a more recently developed concept. Once the 0% long-term capital gains tax rate became a permanent part of the tax code with the passing of the American Taxpayer Relief Act of 2012 (signed January 2nd, 2013), in some scenarios it began making sense to recognize long-term capital gains on purpose to potentially avoid a larger tax bill in the future.

Suppose a taxpayer’s taxable income is consistently $65,000 a year. Additionally, suppose our hypothetical taxpayer won’t withdraw funds from his taxable account during the next few years, but may need a large lump sum distribution five years down the road. Recall that the 0% capital gains rate ends when a married taxpayer’s taxable income (which includes long-term capital gains) exceeds $73,800. Consequently, this hypothetical taxpayer has the ability to recognize $8,800 ($73,800 – $65,000) in long-term capital gains every year without increasing his tax bill. If this $8,800 in gains is recognized every year by simply selling and immediately repurchasing appreciated assets, he would raise the cost basis of his investment by $44,000 ($8,800 gain recognized annually for five straight years). He could then sell and withdraw that $44,000 without creating a tax liability.

Alternatively, if the investor does not harvest gains during the years when no distributions are taken, withdrawing $44,000 of gains five years down the road would create a sizable tax bill. He would still be able to recognize $8,800 of gains tax free in the year of distribution, but the remaining $35,200 of gains would cause his taxable income to be over the $73,800 limit, eliminating access to the 0% capital gains rate. That $35,200 would be taxed at the 15% capital gains rate, creating a federal tax bill of $5,280. With proper planning, this significant tax bill can be avoided.

***

Portfolio analysis

***

The Bottom Line

Tax harvesting has no purpose in tax-advantaged retirement accounts such as IRAs and 401ks because all distributions from these accounts are taxed as ordinary income. However, taxable individual or trust investment accounts can almost certainly benefit from tax harvesting. Speak to your accountant and financial planner to understand whether capital gains or losses are desirable for you this year and determine the amount of taxable gains already recognized. This will help you determine what type of harvesting should take place.

Tax harvesting can be a difficult and confusing concept. However, a competent financial planner who utilizes this procedure within your taxable investment account can significantly lower your tax bill. Speak to your adviser to ensure you are reaping the tax benefits available to you.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants

About “OOP” National Health Care Expenses

Join Our Mailing List

Detailing “Out-Of-Pocket” Expenses not included in Federal NHE Calculations

By http://www.MCOL.com

Expenses

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

My Stock Market Forecast for 2015

Join Our Mailing List 

All Forecasts Will Be Wrong

[By Lon Jefferies MBA CFP®]

Lon JeffriesThe investment media is a rare industry in which professionals are rewarded for making bold projections but never punished for being wrong. The more outlandish a pundit’s forecast the more attention it receives.

Yet, surprisingly little consideration is given to how accurate the prediction turns out to be.

At the beginning of 2014, there were some widely-accepted expectations regarding the investment environment.

Let’s review those predictions and analyze how precise they really were.

Interest Rates

In a study conducted by Bloomberg at the beginning of the year, all 72 economists surveyed predicted higher interest rates and falling bonds prices in 2014. Consequently, investors were questioning whether they should reduce or eliminate the bond portion of their portfolios until the rate increase occurred.

So, have we experienced this rise in interest rates?

On January 1st, 2014, the yield on the 10-year Treasury note was 3 percent. On November 13th, the yield on the same note was 2.35 percent. That’s right — interest rates actually decreased significantly during the year. As a result, intermediate U.S. government bonds (ticker – IEF) produced a return of 7.38% during the year. Not bad for the conservative portion of your portfolio!

Quantitative Easing

The most widely promoted fear among forecasters was that the phasing out of the Federal Reserve’s quantitative easing (QE) program would diminish stock returns. Prognosticators worried that the Fed would lower the amount of loans the government would buy from commercial banks, thus reducing the amount of money available for new businesses to borrow leading to less innovation and the creation of fewer jobs.

But, was the reduction of quantitative easing a legitimate fear? In fact, this possibility came to fruition. In December of 2013, the Federal Reserve was buying $85 billion of financial assets from commercial banks each month. The Fed reduced this amount during every meeting it held this year, finally eliminating the action completely in October.

However, the elimination of Quantitative Easing did not have a negative impact on the unemployment rate, which declined from 6.7% in January to 5.8% in October. Further, the S&P 500 has gained 12.31% year-to-date (as of 11/13/14). Clearly, fading out the Quantitative Easing program didn’t have the negative impact on stocks that many pundits expected.

Increased Volatility

Another widely held viewpoint at the beginning of the year was that 2014 was likely to be more volatile than anything experienced in 2012 or 2013. There was talk about valuations and P/E ratios being too high, concern about the war in Ukraine (ISIS wasn’t even in the headlines yet), and endless noise about unfavorable weather patterns impacting the market.

So, has 2014 been a wild ride? Since 1929, the S&P 500 has experienced either a rise or a decline of more than 1% during 23% of trading days. In 2014, the S&P 500 moved more than 1% only 15% of the time. Less movement equates to less volatility, so again forecasters were inaccurate.

2015 Forecasts

Bloomberg News recently published a story titled Predictors of ’29 Crash See 65% Chance of 2015 Recession, in which the grandson of a prognosticator who luckily forecasted the Great Depression is still getting attention for a guess his grandfather made 85 years ago. If giving credence to forecasters isn’t ridiculous enough, suggesting there is a gene for forecasting is insane!

The article doesn’t mention that the same grandson made similar headlines with the same forecast in both 2010 and 2012; of course, those predictions did not work out so well. You will start hearing many 2015 projections soon, so pay no heed.

***

glasses

***

Ignore the Pundits

The most significant lesson inherent in these numbers is that market expectations are essentially useless. Despite their abysmal track record, the news media loves forecasters because they capture attention and fill space. Unfortunately, pundits making projections are rarely held to their inaccurate forecasts and are allowed to continue making a living showing they have no greater knowledge than the average investor.

Of course, this is not to say that interest rates will never rise, that bond values will never decline, and that the market won’t return to the roller coaster it is. In fact, all those things are certain to happen. Unfortunately, anyone who contends to know “when” likely doesn’t actually know anymore than you or me. For this reason, having and sticking to a diversified investment strategy that coincides with a detailed financial plan is the most probable path to financial success.

More: 

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants

2014 – A Near Record Year for IPOs

Join Our Mailing List

A 2014 Wrap-Up 

[By Inside the Ticker]

***

1

***

2

***

3

***

More:

Assessment

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants

***

On Health Care Fraud Detection Analytics

Join Our Mailing List

On the Intersection of Data and Linking Analytics

By http://www.MCOL.com

fraud

More:

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct DetailsProduct Details

The Economic Impact of Alzheimer’s Disease

Join Our Mailing List

Economic Projections 

By http://www.MCOL.com

economics Az

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

 Product DetailsProduct DetailsProduct Details


Physician Couples and Money Management

Join Our Mailing List 

On Cash Management Techniques

By Rick Kahler MS CFP® www.KahlerFinancial.com

Rick Kahler MS CFPMoney is just one of many challenges to becoming part of a couple; especially for physicians. Probably the most common question couples ask me concerns the best way to handle their cash management.

Specifically, they wonder if they should combine all their cash flow into one joint checking account, keep everything separate, or have some combination of both.

Stock Answers

My stock answer is “yes.” It seems that, the older I become, the fewer right answers there are and the more often I say, “It depends.” This is one of those situations where there is no one best method.

Future Physicians

Let’s consider the advantages and disadvantages of each approach.

  1. Combining everything in one joint account

The plus side of this scenario is that there is total financial transparency as to where the money comes from and goes to. Each party has full access to and opportunity to be fully aware of the money flow. It’s easy to track. There are no secrets.

Which brings us to the downside: there are no secrets, no autonomy. Each party can see the other’s spending and spend the other’s money. This works well in some relationships where the shared belief is, “My money is your money and your money is my money.” It doesn’t work well absent that philosophy. I find this scenario is often problematic when one or both of the parties want autonomy over how they spend their money without the watchful (often critical) eye of the other. Often this arrangement doesn’t work well in second marriages or where both parties have careers.

  1. Keeping everything completely separate

The positive of this scenario is that each party has complete autonomy and control over his or her money. This often works well for two-career couples or second marriages where both partners came into the union with significant pensions or assets. It may also be a good fit for unmarried couples. If one partner is a spendthrift, it can protect the other partner from unauthorized purchases.

The negatives are that it can be more difficult to manage joint expenses like housing costs and that neither party has any specifics into the spending of the other. If a partner has any type of addiction, separate accounts can serve to enable the addiction by hiding the extent of the problem from the other partner.

  1. Combination of joint and separate accounts

The advantage to this scenario is that it provides more autonomy than putting everything into a joint account, yet it offers an easier way to manage joint expenses. It can often result in a clear agreement on what is mine, yours, and ours. Some couples have a system where each one’s earnings are their own, and they each contribute put fixed amounts into joint account. Another method is to deposit all the income into the joint account and give each partner a periodic allowance.

The disadvantages to this are the need to manage three accounts and to decide who writes the checks from the joint account.

Spouses

Case Example:

Personally, my wife and I use the third option. As the major breadwinner, I deposit most of my income into the joint account, from which she pays all the family bills. A smaller amount of my income goes into my separate account that I use to pay for private schooling, funding 529 plans, and personal care like massages and haircuts.

Assessment

Problems often arise when partners assume the money should be managed (or is being managed) in a certain way. No matter which approach couples use, the most important factor is to discuss it and agree, as equal partners, to a system that works for them.

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

More:

  1. Physician Cash Maximization Rules
  2. On Emergency Funds for Physicians
  3. Essential Insights on Successful Physician Budgeting

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Integrity and Accountability [The Declining State of Physician Health and the Urgent Need for Ethical and Evidence-Based Leadership]

Join Our Mailing List

SPECIAL ME-P REPORT

[By Michael Lawrence Langan MD]

Integrity and Accountability—The Declining State of Physician Health and the Urgent Need for Ethical and Evidence-Based Leadership.

***

gag

***

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

The Financial Planner’s Responsibility?

Join Our Mailing List 

Are Consumers Losing Ethical Ground?

By Rick Kahler MS CFP™ http://www.KahlerFinancial.com

Rick Kahler MS CFPSuppose one of my clients has his heart set on using half of his retirement account to buy each of his grandchildren a new car.

Or, a physician-client in a panic over falling markets wants to sell all her stocks and buy gold. What is my responsibility as their financial planner? How far should planners go to try to keep clients from making serious financial mistakes?

Just as with the patient engagement, it’s important for planners to respect clients’ competence and ability to make their own life decisions. Client-centered planners also need to remember that the goal is to help clients get what they want, not what the planner might want or think the client should want.

On the other hand, should a planner stand idly by and watch someone walk off what the planner perceives as the edge of a financial cliff?

Potential Answers?

Part of the answer to this dilemma stems from a planner’s legal obligation. Most advisors who sell financial products have no fiduciary duty and are not legally required to put their customers’ interests first. Fiduciary advisors, which include those who are fee-only, do have a legal obligation to act in their clients’ best interests.

Fiduciary Responsibility

Doctors, clergymen and attorneys are fiduciaries. But, what is the legal responsibility of a fiduciary financial planner who believes clients are about to do themselves financial harm?

Example:

Let’s say I have a client who is about to do something that may be viewed by a court of law as “extreme” or “imprudent.” (An example would be putting all his money into one asset class like gold, cash, penny stocks, etc.) At the minimum, I would need to protect myself by carefully fulfilling my legal responsibilities. This would include making certain I emphasized to the client that, given the research and data available, his actions could hurt him financially. I also would want to be sure the client fully understood and took responsibility for his actions.

***

comedy

***

In terms of the broader aspect of what financial planners owe to their clients, meeting this legal obligation is not enough. In my view, fiduciary planners’ obligation to put clients’ interests first includes an ethical responsibility to do no harm. Sometimes this ethical and legal responsibility requires planners to give clients information they may not want to hear.

As we focus on the clients’ goals and help them carry out their wishes, part of our role is to make sure they have all the information they need. This gives us a responsibility to educate ourselves so the advice we offer is as sound as we can make it. We also need to do whatever we can to help clients hear and understand that advice.

Clients who are hovering on the edge of a financial cliff are typically about to act out of strong emotions such as fear. They often can’t take in financial advice until they are able to move through that fear. It only makes things worse if financial advisors shame clients, bully them, or abandon them to their fears. The challenge for planners is to help clients reach a more rational place so they can gather additional information and make decisions that will serve them well.

Industry Update is Not Good – Give Up the ‘Fiduciary’ Fight

According to industry pundit Bob Veres, so-called Financial Advisors need to face a hard truth – Independent Registered Investment Advisors [RIAs] have lost this round.

But, we already told you so on this ME-P.

Fortunately, there are other better ways to set yourself in the medical ecosystem.

The Certified Medical Planner™ Designation

A Certified Medical Planner™ is a fiduciary at all times.

More:

Assessment

With the right kind of support, clients are almost always able to get past the fear that is pushing them to make imprudent decisions. Providing such support by working with clients’ emotions and beliefs about money, perhaps with the help of a financial therapist or financial coach, is well within a financial planner’s ethical responsibility. Our role is not merely to do no harm. It is also to use all the tools we have to help clients act in their own best interests.

Product Details  Product Details

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

The Medical Profession, Moral Entrepreneurship, Moral Panics, and Social Control

Disrupted Physician

IMG_9005The Medical Profession, Moral Entrepreneurship, and Social Control

Sociologist Stanley Cohen  used the term “”moral panic” to characterize the amplification of deviance by the media, the public, and agents of social control.1  Labeled as being outside the central core values of consensual society, the deviants in the designated group are perceived as posing a threat to both the values of society and society itself.   Belief in the seriousness of the situation justifies intolerance and unfair treatment of the accused.   The evidentiary standard is lowered.

Howard Becker describes the role of “moral entrepreneurs,” who crusade for making and enforcing rules that benefit their own interests by bringing them to the attention of the public and those in positions of power and authority under the guise of righting a society evil. 2

And according to cultural theorist Stuart Hall, the media obtain their information from the primary definers of social…

View original post 2,659 more words

Out-Look on Global Inflation Rates for 2015

Join Our Mailing List

A Mixed Picture

[By BNY Mellon]

inflation

[Click to Enlarge]

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™


12 Email Marketing Tips for MDs and FAs

Join Our Mailing List

To Ensure Your Campaign Isn’t a Waste of Time and Money

B

The success of your email marketing campaign will depend on a number of things, from how you grow your list, the times and days you send them, to the type of content you send.

To ensure your email marketing campaigns aren’t a waste of time and money make sure you read the tips in this infographic from Vertical Response.

***

eMail tips

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

***

Product DetailsProduct Details

2015 Health Plan Premium Increases

Join Our Mailing List

Projections

By http://www.MCOL.com

premium

Channel Surfing the ME-P

Have you visited our other topic channels? Established to facilitate idea exchange and link our community together, the value of these topics is dependent upon your input. Please take a minute to visit. And, to prevent that annoying spam, we ask that you register. It is fast, free and secure.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

The Impact of Gratitude on Financial Behavior

Overspending? Try a Little Thanksgiving Gratitude 

By Rick Kahler MS CFP® http://www.KahlerFinancial.com

Rick Kahler MS CFPDo you want to more easily change your over-spending behavior? According to research, maybe all you need is a bit of gratitude.

Gratitude

Before you brush this idea aside as just another “feel good” theory, you may want to consider a 2013 study that suggests practicing gratitude is a powerful way to increase your happiness and decrease temptations. Northeastern University’s David DeSteno led the research project, which was published in June 2014 in the journal Psychological Science.

Logic versus Emotions

Many of us believe we ought to make decisions, especially financial ones, logically rather than emotionally. We assume emotions get in the way of decision-making, so we try to set them aside. We may think the best way to resist temptation, such as wanting to buy something we can’t afford, is to use self-control to clamp down our emotions.

The Research?

Yet research has shown that emotions play a significant role in all our decision-making. Some of that research is discussed in an article by Ray Williams published September 25, 2011, in Psychology Today.

Trying to ignore our emotions and make cold and calculating decisions is fear-based behavior. The gratitude research, however, suggests that emotions can be used instead to help us resist temptation. Perhaps being less fearful and more grateful can actually produce better decisions.

The Study

DeSteno’s study gave 75 participants a classic test of their financial self-control. They were told they could have either $54 right now or $80 in 30 days. Before they made their decision, the researchers put the participants into one of three emotional states: grateful, happy, or neutral.

The Results

Those who were either happy or neutral showed a strong preference for taking the $54 now. The fact that by waiting 30 days and getting $80 they would receive a one-month return of 48%, which is equal to an annualized return of 576%, wasn’t even a consideration. Behavioral economists tell us this is normal. Our brains are generally wired to “kill and eat.” Having something now, even though it’s less, is better than having more later, even if it will be much more. That is some strong wiring!

***

mind-investing-behavioral-finance

***

The Surprise

However, the surprise was that the people in the state of gratitude were much more likely to wait 30 days to receive the $80. Results also showed that the more gratitude the participants reported feeling, the more willing they were to wait for the larger gain.

The Grateful Difference

One conclusion of the study is that just cultivating the emotion of happiness isn’t enough to make wise financial decisions. It is specifically the emotion of gratefulness that makes a difference. According to one of the study’s authors, Professor Ye Li, this research “. . . opens up tremendous possibilities for reducing a wide range of societal ills from impulse buying and insufficient saving to obesity and smoking.”

We don’t know why gratitude has this effect. Psychologist Dr. Jeremy Dean, in a June 18 post at PsyBlog about the research, says, “. . . it may be because it makes us feel more social, co-operative and altruistic. In other words: gratitude may make us feel less selfish, which gives us more patience.”

Personally, I wonder whether another possibility may be that feeling gratitude reminds us of how much we already have, which tends to reduce our desire to get something more.

Assessment

If you’d like to do some experimenting of your own, consider practicing some gratitude exercises. Dr. Dean describes some at PsyBlog. These may be as simple as making daily lists of things you have to be grateful for. It’s possible that fostering gratitude could do more than just promote happiness. It might even change the way you spend and invest.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Employee Health Benefits for Same Sex Domestic Partners

Join Our Mailing List

Regional Distribution

http://www.MCOL.com

same

More:

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details

Medical Claims Payment Data Differences

Join Our Mailing List

Between Price Transparency Platform Users and Non-Users

By http://www.MCOL.com

ImageProxy

data

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product DetailsProduct Details

How Financial Advisors Build Trust with Physician Prospects and Clients

Join Our Mailing List 

A SPECIAL ME-P REPORT

Niche Career Development for Financial Advisors

VR MD

[By Vicki Rackner MD]

Attention Physician Focused Financial Advisors

If you are a financial advisor who would like to acquire more physician clients, consider these facts:

  • Fact: Half of physicians are behind where they would like to be in retirement planning.
  • Fact: About half of physicians work with professional financial advisors.
  • Fact: Physicians who work with financial advisors are better prepared for retirement.

The Survey

How can YOU build trust and be found by more physician prospects? Here are some steps. Trust is an abstract concept. It begs the question: Trust to do what? I asked my physician colleagues and friends, “When you say you trust your financial advisor, what do you mean?”

Here are some of the answers:

  • You may trust your hairdresser to give you a great look, but you would not trust her to take out your gallbladder.
  • Ask, “Trust to do what?”
  • A recent survey offers insights. Almost half of physicians said that they do not work with advisors because they cannot find someone they trust.
  • This leads to an obvious question: Why would physicians–smart professionals who spend their days identifying problems and fixing them–fail to take action and get on track for retirement?
  1. I trust that she cares about me.
  2. I trust he puts my best interests before his own.
  3. I trust he knows what he’s doing.
  4. I trust he understands the challenges I face.
  5. I trust that she’s honest and direct. A person of integrity.
  6. I trust that he’ll challenge me if I’m about to make a dumb financial move.
  7. I trust the person who gave me his name.
  8. I trust that I’ll keep more money than I spend in fees.

***

Product Details  Product DetailsProduct Details

***

Take steps to build rapport and trust – Be authentic

Tell the story of how and why you came to offer financial advice to physicians.

Here are a few examples from my own clients:

  • Show you care. A famous quote among physicians is, “For the secret in the care of the patient is caring for the patient.” Your first step in building trust with physician prospects and clients is demonstrating you care about them.
  • You can survey your clients and Identify how they how they see your trust-building strengths.
  • An advisor tells the story of his surgeon father who outlived his money. That inspired him to help other surgeons enjoy true financial security.
  • A cancer survivor tells physicians he’s giving back to the doctors who helped his kids grow up with a father.
  • An advisor tells the story of always wanting to be a cardiologist. Now he’s using his real gift–making money grow–to help cardiologists build wealth.

More Tips:

Keep your promises

As my grandmother said, “Keep every promise you make, and only make promises you can keep.”

Conduct yourself like a physician

What does your personal physician do to win your trust? Do the same!

Be consistent

Conservative physicians may need to be exposed to you and your message six to ten times before they take action. Do you have lists of prospects and clients? Have you built an automated way of delivering something of value to them on a regular basis?

Quote other physicians

The most influential person in a physician’s life is another physician. If a physician offers a great idea or a best practice, ask permission to share this pearl of wisdom with other physicians. You want to be known as the financial advisor who rubs shoulders with physician leaders.

Regularly ask

Ask MD prospects and clients, “How can I do better?”

Take steps to be found

Physicians find financial advisors in much the same way you find a personal physician. You begin with someone you trust. Like me, most physicians turn to their own colleagues for names of financial advisors.

Address painful problems that need to be fixed TODAY

Busy people tend to put off problems that are asymptomatic today, even when they know the neglected problems will lead to pain in the future. Retirement is years away for most physicians. However, they seek relief from the acute financial pain of ObamaCare today.

Partner with experts and offer solutions to the problems of falling reimbursements, rising practice costs and heavier tax burdens. When physicians have more money to invest, they build wealth more quickly.

Interview key physician opinion leaders

Ask top physicians how ObamaCare impacts their day-to-day practice and their plans for the future. Uncover specific active problems. These are all opportunities for you. A key physician could introduce you to many physicians.

Listen to physicians

Active listening builds trust. Further, when you express true curiosity in others, they will want to learn about you.

Go to places physicians gather

Offer to speak at medical meetings about topics that the key physician opinion leaders identify. Submit articles for association publications. Join conversations on social media if that’s where your physician prospects gather.

What this means for you

Here’s why you may want to build trust and be found among physicians: you can mine the treasures in the medical market.

  • Fact: Doctors make up 9 of the top 10 earners in the US.
  • Fact: 500,000 US practicing physicians and dentists are financial do-it-yourself’ers.
  • Fact: 40% of practicing physicians are age 55 or older.Physicians’ acute financial pain is your business opportunity. Someone will offer financial leadership to physicians. Why not you?
  • Assessment
  • Every physician is actively developing a personal ObamaCare plan; this is complex personal financial plan for which physicians solicit expert opinions.

Assessment

Enter the Certified Medical Planners

About the Author

Vicki Rackner MD, author, speaker and President of Targeting Doctors, helps financial advisors accelerate their practice growth by acquiring more physician clients. She calls on her experience as a practicing surgeon, clinical faculty at the University of Washington School of Medicine and nationally-noted expert in physician engagement to offer a bridge between the world of medicine and the world of business.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Understanding the “Least” Important Issues for Physician-Investors

Join Our Mailing List 

A Dimensional Fund Advisors Survey

By Rick Kahler MS CFP® http://www.KahlerFinancial.com

Rick Kahler MS CFPIn this ME-P, I will focus on the three least important things investors want to know. The rankings came from a survey of investors, funded by Dimensional Fund Advisors, conducted in March 2014 by Advisor Impact.

All three deserved to be much higher on the list. In my experience, they are what most physicians and all investors really need to know.

The factors

These three factors are:

  • What are the chances the investment will lose money? Only 10% of investors thought it was important to ask about factors that contributed to historic performance. Just one-third thought it important to even ask about historical performance in general.
  • What type of volatility can they expect? Only 17% of investors considered this important.
  • How and why did the advisor select the investment for their portfolio? Only 21% of survey respondents thought this was important, and just 8% asked about the investment managers chosen.

Drilling Down and Going Granular

Some of these factors may seem difficult to understand, but they do matter. Give your financial advisor a chance to explain them; it can help you become a more informed investor.

ME-P Physicians

  1. Chances of losing money

This factor could be better addressed by asking about the specific factors that influenced historic performance of the security over various long-term economic climates. True, looking at the past performance of an investment is never a guarantee of future performance.

Yet, if the historical periods evaluated contain a variety of economic conditions (high inflation, various economic cycles, various political influences, etc.) and long-term holding periods (at least 10 years or more), looking backward may give you a reasonable idea of what future performance might look like.

  1. Volatility

Most investors will cognitively agree they fully understand that most investments that carry any chance of real (after inflation) significant long-term return will fluctuate. I say “cognitively” because, once that fluctuation happens on the downside, all cognitive understanding sometimes goes out the window and the emotional brain takes control.

One way of internalizing the potential fluctuation of an investment is to ask about its volatility. Specifically, it’s standard deviation. This measure of the amount of variation from the average is something an advisor can easily find out for almost every bond, stock, and mutual fund. Take the standard deviation times three, then subtract that number from the average return. This is the amount of value over one year your investment could drop (or rise) in 99% of all years. Stated conversely, there is only a 1% chance your investment would drop further in any one year.

  1. Portfolio Fit

I recently sent back a shirt that hung on me like a tent. While it would have been perfect for a larger guy, it was not a fit for me. Investments are similar. While some are perfect matches for one portfolio, they can be lethal in another. An over-allocation to emerging market stocks may make perfect sense for a newborn, but it could be a retirement disaster for a 90-year-old.

Pensive Financial Advisor for Physicians

Assessment

It’s important to ask why an investment belongs in your portfolio. You want investments (asset classes) that complement one another by tending to fluctuate independently of each other.

In an ideal balance of investments, when some decrease in value the other half increase an equal or greater amount, and all of them earn a real return over time.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

 Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

How Physicians Prepare for Retirement?

 Join Our Mailing List 

ME-P SPECIAL REPORT

On Physician DIY’s

[By Vicki Rackner MD]

VR MD

Dear ME-P Readers and Subscribers,

Employed physicians who use professional financial advisors v.s. physician financial do-it-yourself-ers):

Did you know the following:

  • Feel better prepared for retirement
  • Have more in emergency savings
  • Have more diverse financial investments and
  • Feel more confident about their personal financial decisions?

Did you also know:

Here are some other key survey findings:

  • 60% of practicing physicians are employed by hospitals, groups and medical schools.
  • 42% of of employed physicians are behind where they would like to be in retirement planning.
  • Employed physicians” #1 financial goal is to enjoy a comfortable retirement. Other top concerns include funding long-term care, minimizing losses and ensuring an inheritance for children/ grandchildren.
  • Half of employed physicians believe they have unique or more complex financial needs than other professionals.These finding affirm the intuitively obvious: experts get better results than dabblers.
  • Patients get the best medical outcomes when they work with physicians whom they trust; physicians get the best financial results when they work with financial advisors whom they trust.

***

Product Details  Product Details

***

What this means for you

These finding affirm the intuitively obvious: experts get better results than dabblers.

Patients get the best medical outcomes when they work with physicians whom they trust; physicians get the best financial results when they work with financial advisors whom they trust; as a fiduciary advisor.

Assessment

Enter the Certified Medical Planners

About the Author

Vicki Rackner MD, author, speaker and President of Targeting Doctors, helps financial advisors accelerate their practice growth by acquiring more physician clients. She calls on her experience as a practicing surgeon, clinical faculty at the University of Washington School of Medicine and nationally-noted expert in physician engagement to offer a bridge between the world of medicine and the world of business.

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

On The Next Stock Market Correction?

Join Our Mailing List

Remember the Ace Up Your Sleeve!

By Lon Jefferies MBA CFP® CMP®

Lon JeffriesAfter the historic growth the stock market has experienced since early 2009, many physician investors have felt that a healthy pullback may not be a completely negative thing.

After all, we certainly don’t want another bubble, or stock prices that are clearly out of line with the earning potential of the underlying companies.

Unfortunately, market corrections never feel healthy when they occur. Physicians, investors and almost all people get uncomfortable when the market declines, the media fans the flames by giving investors reason after reason to be afraid, and worries that this is the beginning of the next crash begin to develop.

While many investors admit that a 5% pullback is manageably unpleasant, concerns expand when the market decline hits 10% — right when the media can officially throw around the word “correction.”

Of course, we have no idea when the next drop will occur, but why not mentally prepare ourselves by exploring what has traditionally happened to stock prices once that 10% decline is crossed?

The Data

Ben Carlson, an institutional investment portfolio manager, looked at the S&P data going back to 1950, and found that there have been 28 instances when stocks fell by 10% or more. Thus, on average, the market has entered an official correction every 2.25 years. The last market correction occurred in 2011, so another 10% drop at this time would correlate pretty close to the average amount of time between corrections.

Obviously, the market has done pretty well since that last temporary correction in 2011. Clearly, such a drop is quite normal and far from historically concerning.

  • S&P 500 Losses of 10% or More Since 1950
  • Total Occurrences: 28 Times
  • Average Loss: -21.6%
  • Median Loss: -16.5%
  • Average Length: 7.8 Months
  • Greater Than 20% Loss: 9 Times
  • Greater Than 30% Loss: 5 Times

Your Advantage

Are you thinking “I don’t think I can stomach that median loss of 16.5%?” Then it’s time to pull out the ace up your sleeve. Remember that the data above represents the historical performance of the S&P 500 – an index that is composed of 100% stocks. A capable financial planner would ensure you have an asset allocation mix between stocks, bonds, and cash that represents your tolerance for risk.

Consequently, your portfolio likely isn’t 100% stocks. In fact, the appropriate allocation for an average investor approaching or already enjoying retirement might be closer to only 50% stocks. This means that on average, your portfolio should decline only half as much as the S&P 500 during market downturns.

This ace may bring the loss endured by our sample investor with a 50% stock portfolio down to around 8.25% during the median decline. Are you now back in the “manageably unpleasant” range? If so, you likely have an appropriately constructed portfolio. If not, your risk tolerance may need to be reevaluated to ensure you are not exposing your nest egg to a larger loss than you can endure.

Avoid Harmful Reactions to the Market

Although the recent market pullback produces what seems like a foreign feeling, we’ve been here before. The S&P 500 declined in value by 18.64% over a 5 month period in 2011. However, an investor with a 50% stock portfolio likely only saw their account values drop around 9%-10% — still not fun, but manageable.

Assessment

Of course, we don’t know whether the market will continue to bounce back or again drop into official correction territory. If you continue to hear about the broad markets declining, remember that the average historical correction has been far from catastrophic, and that you have the ace of an appropriate asset allocation up your sleeve.

Financial Planning MDs 2015

Comprehensive Financial Planning Strategies for Doctors and Advisors: Best Practices from Leading Consultants and Certified Medical Planners™

Conclusion

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

Speaker: If you need a moderator or speaker for an upcoming event, Dr. David E. Marcinko; MBA – Publisher-in-Chief of the Medical Executive-Post – is available for seminar or speaking engagements. Contact: MarcinkoAdvisors@msn.com

OUR OTHER PRINT BOOKS AND RELATED INFORMATION SOURCES:

Product Details  Product Details