
COMPENSATION: Physicians, Dentists, Podiatrists and Chiropractors

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***
***

The healthcare sector comprises a diverse ecosystem of professionals, each dedicated to diagnosing, treating, and managing human ailments. Among these, allopathic and osteopathic physicians (MDs/DOs), dentists (DDS/DMDs), podiatrists (DPMs), and chiropractors (DCs) represent distinct pathways of specialized care. While all these professionals undergo rigorous doctoral-level training, their economic realities diverge significantly. The differences in their average annual salaries, starting compensation, and lifetime earning potential are shaped by a complex interplay of educational investment, clinical specialization, practice ownership models, insurance reimbursement structures, and market demand.

Physicians consistently command the highest compensation within this cohort, reflecting their extensive training and broad clinical responsibility. After completing four years of medical school, physicians must undergo three to seven years of residency training, and often additional fellowships. This massive investment of time yields substantial financial returns. Primary care physicians, including family medicine and pediatric specialists, typically earn highly competitive six-figure salaries. However, the true divergence in medical compensation appears within surgical and procedural specialties. Specialists such as orthopedic surgeons, cardiologists, and neurosurgeons often command salaries that double or triple those of their primary care peers. This premium is driven by the high complexity of their procedures, the intense nature of their on-call responsibilities, and the heavy reliance on hospital-based reimbursement systems.

Dentists occupy a unique and highly lucrative niche within healthcare economics. Graduating after four years of dental school, general dentists have the option to enter private practice immediately without mandatory residency training. General dentists earn robust salaries that position them firmly in the upper echelons of high-earning professionals. The financial trajectory climbs even higher for dental specialists, such as oral and maxillofacial surgeons, orthodontists, and periodontists, who complete additional years of residency. A major driver of dental compensation is the business model; a high percentage of dentists own or partner in private practices. This allows them to capitalize on business equity and profit margins, rather than relying solely on a fixed salary. Furthermore, dentistry benefits from a more favorable insurance environment, featuring higher cash-pay rates and less administrative friction than traditional medical billing.

***

***

Podiatrists, specialized physicians focusing exclusively on the foot, ankle, and lower extremity structures, earn salaries that generally align comfortably with primary care medical doctors. Their training paradigm is remarkably similar to traditional physicians, requiring four years of podiatric medical school followed by a mandatory three-year surgical residency. Despite this intensive surgical training, average podiatric compensation tends to lag behind mainstream medical specialties like orthopedic surgery. This disparity is often attributed to a narrower scope of practice and historical differences in how healthcare systems and insurance providers value podiatric services compared to general orthopedic care. Nevertheless, podiatrists who establish successful private surgical practices or integrate into large, multidisciplinary orthopedic groups can significantly outpace average salary benchmarks.

Chiropractors, who focus on non-invasive, neuromusculoskeletal care through spinal adjustments and holistic therapies, occupy a markedly different economic tier. Completing a four-year doctor of chiropractic program, these professionals typically do not undergo mandatory post-graduate residency. The average salary for chiropractors is notably lower than that of physicians, dentists, and podiatrists. Chiropractors operate heavily within a cash-pay or limited-insurance reimbursement framework, as major health insurance plans and government programs provide more restricted coverage for chiropractic care compared to medical or dental procedures. Because the vast majority of chiropractors are solo practitioners or independent contractors, their income is directly tied to patient volume, marketing efficacy, and local competition, leading to a much wider variance in earnings from low-income earners to highly successful clinic owners.

***

***

The foundational driver of these salary differences is the structure of insurance reimbursement. Physicians and podiatrists rely heavily on complex insurance networks, Medicare, and Medicaid, where reimbursement rates are strictly regulated and heavily favor procedural or surgical interventions over diagnostic care. Dentists operate on a hybrid model, utilizing specialized dental insurance that frequently requires significant out-of-pocket patient co-pays, granting providers greater pricing flexibility. Chiropractors face the most stringent insurance limitations, forcing them to adopt retail-style business models where income is generated directly from consumer wallets.

Ultimately, while all four professions demand a high level of dedication and doctoral education, their financial landscapes are far from uniform. Physicians and dentists remain the financial anchors of the healthcare industry, leveraging deep systemic integration and ownership models to secure top-tier compensation. Podiatrists maintain a steady, highly specialized mid-to-high income tier, while chiropractors experience the highest income volatility, dependent on entrepreneurial skill rather than institutional salary structures. Each field presents a distinct trade-off between the years of training required, the autonomy of practice, and the ultimate financial reward.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Speaker’s Bureau

****

***

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner.

All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

EDUCATION: Books

***

***

THEORY: Economic Relativity

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The theory of economic relativity is a conceptual lens that treats economic behavior, value creation, and market outcomes as dependent on the observer’s position, incentives, and temporal perspective. It borrows the spirit—not the mathematics—of Einstein’s relativity to explain why economic truths shift across individuals, institutions, and nations. In this framework, there are no absolute economic constants. Instead, every economic variable—growth, scarcity, productivity, even rationality—changes depending on who is measuring it, when they are measuring it, and what constraints shape their world.

Relativity of Economic Perspective

Economic relativity begins with a simple premise: economic reality is not uniform. A policy that benefits one group may burden another. A price change that signals opportunity for one business may signal crisis for another. The same economic environment produces different lived experiences depending on the observer’s position within it.

A household earning $40,000 interprets inflation as a direct threat to survival. A corporation with global supply chains interprets inflation as a strategic variable to be hedged or exploited. A government interprets inflation as a macroeconomic force to be managed through policy. Each observer is responding to the same phenomenon, but their conclusions differ because their frames of reference differ.

Economic relativity argues that these differences are not noise—they are the system. To understand any economic outcome, one must first understand the observer’s position.

***

***

Time as an Economic Dimension

In physics, relativity reshapes our understanding of time. In economics, time is the most powerful determinant of value, cost, and opportunity. Every economic decision is shaped by the time horizon of the decision-maker.

Short-term actors—day traders, gig workers, small businesses—experience the economy as volatile, fragile, and dominated by immediate constraints. Long-term actors—governments, pension funds, multinational corporations—experience the economy as cyclical, structural, and governed by slow-moving forces.

The same investment can be reckless for a short-term actor and prudent for a long-term one. The same policy can be painful in the short run but beneficial over decades. Economic relativity asserts that time does not merely influence economic outcomes; it defines them.

Relativity of Scarcity and Abundance

Scarcity is often treated as an objective condition, but economic relativity reframes it as contextual and observer-dependent. What is scarce for one group may be abundant for another.

A developing nation may experience capital scarcity, while a wealthy nation experiences capital surplus. A rural community may experience labor scarcity, while an urban center experiences labor oversupply. A startup may experience attention scarcity, while a celebrity brand experiences attention abundance.

Scarcity is not a universal constant. It is relative to geography, technology, institutions, and social structure. This relativity explains why economic strategies that succeed in one environment fail in another.

Incentives as Economic Gravity

In Einstein’s universe, gravity bends space-time. In economics, incentives bend behavior. They shape how individuals and institutions interpret information, allocate resources, and respond to uncertainty.

Workers respond to wage incentives. Firms respond to profit incentives. Governments respond to political incentives. Investors respond to return incentives. These incentive structures create “economic gravity wells” that pull decisions in predictable directions.

Economic relativity argues that no economic model is complete without mapping these incentive fields. They distort economic space just as gravity distorts physical space.

***

***

Information and the Observer Effect

Economics is filled with feedback loops. Expectations influence behavior, and behavior influences outcomes. In this sense, the theory of economic relativity incorporates an observer effect: the act of observing or predicting economic conditions changes those conditions.

If consumers expect prices to rise, they buy more today, causing prices to rise. If investors expect a recession, they reduce risk, increasing the likelihood of recession. If businesses expect demand to fall, they cut production, causing demand to fall.

Economic systems are not passive—they react to observation. This relativity of expectation explains why forecasting is both essential and inherently destabilizing.

Relativity of Value and Productivity

Value is often treated as intrinsic, but economic relativity argues that value is relational. It depends on the observer’s needs, alternatives, and constraints.

A piece of land may be valuable to a farmer but worthless to a software company. A patent may be priceless to a pharmaceutical firm but irrelevant to a restaurant. Productivity itself is relative: a worker’s output depends on tools, training, environment, and institutional support.

Economic relativity reframes value as a dynamic relationship rather than a fixed property.

Implications for Economic Decision-Making

The theory of economic relativity encourages a more nuanced approach to economic analysis:

  1. Identify the observer’s frame of reference. Economic behavior cannot be understood without understanding the actor’s incentives, constraints, and time horizon.
  2. Recognize that economic truths are not universal. What is rational, efficient, or optimal depends on the observer’s position.
  3. Avoid one-size-fits-all policies. Policies must be tailored to the relative conditions of different groups and regions.
  4. Embrace dynamic interpretation. As conditions change, economic truths shift. Flexibility is essential.

Conclusion

Economic relativity reframes the economy as a system without absolute constants. Value, scarcity, risk, and opportunity shift depending on the observer’s position, just as time and space shift in Einstein’s universe. This perspective does not replace traditional economics—it enriches it. It reminds us that economic systems are human systems shaped by differing goals, incentives, and constraints. To understand the economy, we must first understand the observer.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

DE-BANKING: Defined

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Debanking is the practice where banks close accounts of individuals or organizations they perceive as posing financial, legal, regulatory, or reputational risks. This can lead to significant consequences, including loss of access to essential financial services.

Understanding De-Banking

Debanking refers to the closure of bank accounts by financial institutions that perceive the account holders as posing various risks. These risks can be financial, legal, regulatory, or reputational. The practice can have severe consequences for individuals and organizations, often leading to a loss of access to essential financial services.

Types of Debanking

Debanking can be categorized into two main types:

TypeDescription
Operational DebankingThis occurs when a bank decides to close an account based on its internal policies or customer behavior, such as repeated overdrafts or contract violations.
Governmental DebankingThis happens when banks are pressured by government entities to close accounts, either through direct orders or regulatory pressures.

Consequences of Debanking

The impact of debanking can be significant:

  • Loss of Access: Individuals may suddenly find themselves unable to make payments or receive funds.
  • Reputational Damage: Being debanked can harm an individual’s or organization’s reputation, making it difficult to secure banking services elsewhere.
  • Financial Exclusion: Those affected may struggle to access basic banking services, leading to broader financial instability.

Recent Developments

In recent years, there has been increased scrutiny of debanking practices, particularly regarding accusations of discrimination based on political or religious beliefs. For instance, investigations in the UK revealed that banks were closing accounts at an alarming rate, prompting calls for regulatory reforms to ensure fair treatment of all customers.

In the United States, an executive order was issued to protect individuals from being debanked for their political affiliations, aiming to curb what is seen as politicized debanking practices. This order mandates that banks provide clear reasons for account closures and prohibits using reputational risk as a justification.

Understanding debanking is crucial as it highlights the balance between risk management for banks and the need for fair access to financial services for all individuals.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

PARADOX: Money Stress

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The Money Stress Paradox suggests that 70% of participants believe not having to stress out and be anxious over money is more important than having more money than most people they know.

Example: The long-term median saving rate in America is only 5%. If Americans truly believed wealth is not having be anxious and to stress over money, Americans would save a greater percentage of their income. All prospecting must understand this dilemma.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Kevin Warsh Speaks

***

***

  • Fed Chair Kevin Warsh, in his speech Friday in Bangkok, declined to offer clues on whether there will be an interest rate hike again this month.
  • He acknowledged a “synchronous tightening” by central banks around the world, saying there are “no free riders.”
  • He expressed optimism that artificial intelligence will make economies that use it well more productive and wealthier, warning the road there will be “very bumpy.”

COMMENTS APPRECIATED

EDUCATION: Books

***

INVESTING: Don’t Make These Financial Mistakes

By Dr. David Edward Marcinko; MBA MEd

***

SPONSOR: http://www.MarcinkoAssociates.com

***

Don’t make these top ten investing mistakes

The days of fat profit margins for physicians are over. Medical cost containment policies in some form or another are here to stay. You’re working harder than ever, so there’s more at stake now in ensuring you don’t make investment mistakes. And, of course, physicians do make them.

Case in point: the sad tale of Debasis Kanjilal, a New York pediatrician who put more than $500,000 into the dot-com company InfoSpace upon the advice of Merrill Lynch’s star analyst Henry Blodget. The company crashed, the analyst was sued, and Merrill settled out of court. Other analysts were involved in similar public fiascos.

Kanjilal committed two common investing mistakes — trusting Wall Street and trusting one’s financial adviser implicitly. They are among the 10 most common investment mistakes made by physicians, according to Eugene Schmuckler, PhD, director of behavioral finance for the Institute of Medical Business Advisors, Inc. They are outlined here, with a treatment plan for preventing each one.
 
Not having an Investment  Policy Statement

Just as we physicians wouldn’t think of treating a patient without a careful history and physical examination, you should not invest your hard-earned capital without an Investment Policy Statement (IPS).

An IPS details what you want your money to do for you, and who is responsible for achieving those goals. It may be three to five pages for an individual physician, 10 to 15 pages for a small medical group retirement plan, or dozens of pages for a clinic or hospital endowment fund.

A properly written IPS should contain the following parts:

  • Statement of purpose
  • Statement of responsibilities
  • Investment goals and objectives
  • Proxy voting policy
  • Trading and execution guidelines
  • Asset mix guidelines 
  • Social policies or other restrictions
  • Portfolio limitations
  • Performance review benchmarks
  • Administration and fee policy
  • Communication policy
  • Reporting policy

Most stockbrokers, insurance salesmen, full service, discount, or Internet brokerage firms do not create IPSs. This is a document you can develop with your financial adviser.

Recommendations tailored to you

Not diversifying/losing sight of portfolio objectives

Although the media frenzy of a few years ago has subsided with the more recent slowdown on Wall Street, anecdotes of easy money are still out there and doctors may forget that investment portfolios serve a specific purpose (e.g., retirement, college funding, etc.) within the context of a broader financial plan. Moreover, a single investment may become too large or too small a portion of the portfolio as a result of market growth in one component or slack in another.

Diversify, monitor your holdings, and select components with your risks and goals in mind. Diversification can reduce portfolio risk. Consider investing in sectors such as basic materials, capital goods, communications and services, technology, consumer cyclicals and noncyclicals (such as pharmaceuticals, alcohol, and cigarettes), healthcare, energy, financial services, and utilities. Do not forget about cash equivalents, treasuries, zero coupon and municipal bonds, and international securities.

Forgetting the investing risk/return tradeoff

Some physicians fall into the trap of chasing “hot” investment products promising the highest returns.

Beware of projecting forward historical averages. The stock market is inherently volatile and, while it is easy to rely on past historical averages, there are long periods of time when returns regress from their long-term historical mean. But don’t let that discourage you. Slumps eventually self-correct, so you should continue a prudent investing plan.

Also, do not confuse investing with trading or speculation. There are momentum-driven market periods when investors start to believe that profits are easy and that there is always a “greater fool” to buy at a higher price. Such trading and speculation are high-risk propositions that have more in common with gambling than investing. Avoid market timing and the urge to jump in or out of the market at every economic hiccup.

Failure to recognize the effect of taxes

An attractive investment and a slick sales pitch sometimes hide the underlying tax costs of the investment. Pay your taxes and do not let the “tax tail wag the investing dog.” Strive for legitimate tax reductions and avoidance.

Failure to recognize the effect of fees and expenses

Front-end loads, back-end loads, disappearing loads, commissions, advertising, and sales expenses can all have significant impact on your investment program.

Monitor the costs of your investment program to ensure that total costs are known, reasonable for the services provided, and are not consuming a disproportionate amount of the investment returns. Carefully consider full-service versus discount brokerages.

Take care using so-called discretionary “Assets Under Management” (AUM) accounts where you pay some percentage for personalized money management. More often than not, these one-size-fits-all accounts are aggregated under a larger umbrella to automatically harvest economies of scale, so the notion that the adviser is sitting on the same side of the investment table as you begins to deteriorate upon critical reflection.

For example, in a 2 percent AUM program of $1 million, you may pay $20,000 annually that is automatically deducted from the account. So are these “perks” worth, say, $200,000 over the course of a single decade? During the “golden age of medicine” in the ’80s, or the raging bull market of the ’90s, some doctors may have said yes. But what about during a bear market, or the projected market of lower-than-average returns that may be upon us?

Avoiding appropriate risk-management techniques/equating insurance products with investment vehicles

Traditionally, physicians protected their families and practices with whole life, disability, malpractice, and business interruption insurance. But insurance products are not investment vehicles; they merely indemnify against catastrophic economic losses that typically are extinguished over time.

Behavioral economists suggest we tend to experience financial losses more intensely than gains. Physicians might prefer vehicles like the guaranteed minimum death benefit of variable annuities, the certainty that comes with disability or long-term care insurance, or traditional cash-value life insurance policies. But be alert to the associated higher costs, huge commissions, and lower returns. And beware of fear-mongering insurance salesmen.

Be open to new ideas that identify and provide solutions to the insurance problems of physicians. One chilling thought suggested by Yale University economist Robert J. Shiller, PhD, in his classic book, The New Financial Order: Risk in the 21st Century, is protection from the “gratuitous random and painful inequality” of selecting the wrong profession. The solution? “Livelihood insurance,” framed as a risk management contract.

Trusting Wall Street

Some stockbroker salesmen and big brokerage houses that underwrite and recommend stocks may have credibility problems, and physicians can get burned with the adrenaline rush of “self-directed” portfolios. Think tech stocks, Enron, WorldCom, HealthSouth. But for some previously “burned” physicians, it is almost as difficult to go it alone as it is to secure professional advice.

Be aware of the four most dangerous words on Wall Street: “This time it’s different.” We recommend using an independent financial adviser, fee-based, or fee-only adviser who charges by the hour, engagement, or pro re-nata for advice.

***

***

Not developing a comprehensive financial plan

While many doctors have an investment portfolio, few have a comprehensive personal financial plan, especially one designed for medical professionals. Typically such plans consider the risk-tolerance and timeframe of several standard components, such as insurance, taxation, investing, retirement, and estate planning. For today’s practicing physicians however, attention should also be directed toward medical practice enhancement activities, contemporaneous risk management concepts, practice appraisal determinations, and medical practice succession planning. All should be interrelated in an economically sound manner not counterproductive to individual components of the plan.

Trusting your financial adviser carte blanche

Just as the prime duty of a physician is to his patients, the prime duty of a financial adviser should be to clients. Yet the very terms financial adviser, financial planner, or investment adviser have no real academic or consistent meaning in the industry. The only hurdle to becoming one is passing a simple securities industry, or state insurance sales licensing examination. Commissioned stockbrokers are fine to use if their fees and intentions are transparent, and they offer value to you.

If you receive advice from a stockbroker, he should be responsible for it, just as we physicians are liable for our medical diagnosis and treatment plan. Perhaps the ancient medical motto omnia pro aegroto should become the new financial services credo omnia pro doctor (all for the doctor-client)?

Selecting the wrong financial or investment adviser

Worry and depression from high management fees, poor investing results, unreturned phone calls, generic advice and sales forms, cold-calls and seminars, high-pressure sales tactics, rapid financial adviser turnover, etc. You deserve better.

Select a financial adviser who takes pride in his fiduciary responsibility, knows the medical profession, and eschews product sales commissions whenever possible. To determine if your current adviser is working for you, just ask to see the documents below:

  • Form ADV Parts I and II for state and/or SEC registration and cost transparency.
  • Sample Investment Policy Statement.
  • Registered Investment Advisor or Series # 65 investment advisory license, which shows fiduciary responsibility.
  • Certified Financial Planner license number, which will show completion of a 24-month course of study at an accredited institution and successful passage of the two-day, comprehensive Certified Financial Planner Board of Standards Examination. This test encompasses all aspects of the financial planning process, including economics, insurance, taxation, investments, and retirement benefits planning. For more information, go to www.FPANet.org.
  • Certified Medical Planner license number, which will show completion of a 500-hour program that integrates healthcare-specific financial planning material with medical practice management principles like leadership skills and organizational behavior; valuations and succession planning; office expense analysis, profit augmentation and benchmarking; HR and recruitment; marketing; and a host of other medical management topics. Like the CFP designation, an ethics and continuing education requirement is also mandated for this charter designation.

Certified Financial Planners, Certified Medical Planners, some fee-based and fee-only financial advisers, and some independent financial advisers possess these licenses and certifications, as required. Stockbrokers, salesmen, intermediaries, insurance agents, or other financial “consultants” and “advisers” may not. All monikers suggest, but do not guarantee, impartiality and a lack of bias.

Often, successful investing is simply a matter of avoiding mistakes, rather than possessing investing acumen. A good rule of thumb is to pursue fundamentals over fads, seek wise counsel when required, and always remember, caveat emptor.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

MEDICINE: Social-Psychiatric Aspects

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Psychiatry is the branch of medicine concerned with prevention, diagnosis and treatment of mental disorders. Its domain includes disorders of thought, emotion, intellect and conduct. The overall prevalence of psychiatric illness is one-fourth to one-third of the total population, and 30-60% of general hospital patients. A percentage of patients may thus be expected to display a variety of mental difficulties associated with, or independent from, their primary complaints.

For example, in 1984, Marcinko documented a report that stated that one-third of all surgical patients encountered difficulty with psychological adjustments before and after surgery. Therefore, understanding human behavior can contribute to the medical practitioner’s success

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Urban Consumer Price Index

***

***

In September, the Consumer Price Index for All Urban Consumers rose 0.6 percent, seasonally adjusted (SA), and rose 3.7 percent over the year, not seasonally adjusted (NSA). The index for all items less food and energy rose 0.3 percent in September (SA), up 2.6 percent over the year (NSA).

Next Release

The Consumer Price Index for October 2026 is scheduled to be released on November 10, 2026, at 8:30 A.M. Eastern Time.

COMMENTS APPRECIATED

EDUCATION: Books

***

***

CHAOS THEORY: In Micro-Economics

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

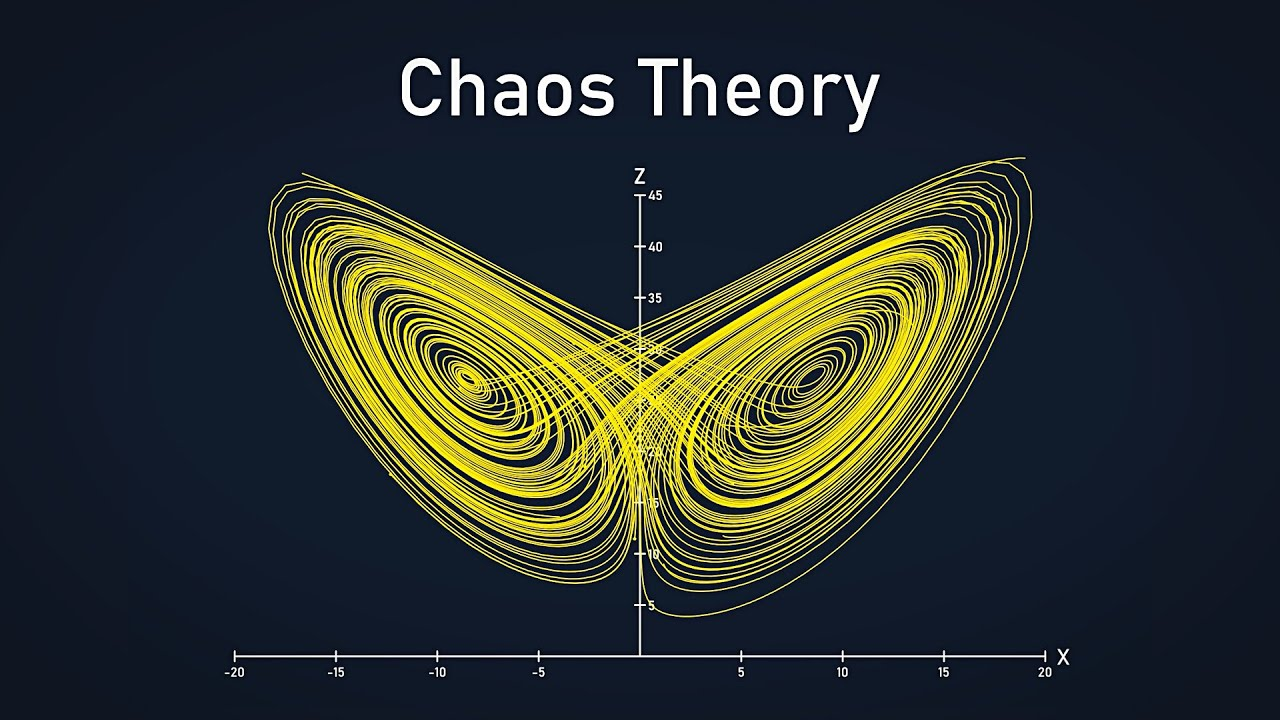
Chaos theory in microeconomics is ultimately a way of seeing markets not as tidy, predictable machines but as living systems where small actions by individual agents can cascade into large, unexpected outcomes. Microeconomics traditionally focuses on how consumers, firms, and workers make decisions under constraints. It often assumes rational behavior, smooth curves, and stable equilibria. Chaos theory disrupts that picture. It argues that even when individuals follow simple, deterministic rules, their interactions can produce nonlinear, unstable, and highly sensitive dynamics. In other words, micro-level decisions can generate macro-level unpredictability.

The foundation of chaos theory is sensitivity to initial conditions—the idea that tiny differences at the start can lead to dramatically different outcomes later. In microeconomics, this plays out in markets where individual choices interact through feedback loops. A slight change in consumer preference, a small shift in a firm’s pricing strategy, or a minor adjustment in expectations can ripple outward. These ripples can amplify, collide, and transform into large market movements. The classic supply-and-demand diagram suggests smooth adjustments, but real markets often behave more like turbulent ecosystems.

Consider consumer behavior. Traditional microeconomic models assume stable preferences and predictable responses to price changes. Chaos theory suggests something more dynamic. Preferences evolve, are influenced by social networks, and can shift suddenly. A small trend—say, a handful of consumers adopting a new product—can explode into widespread demand if social feedback loops kick in. Conversely, a tiny reputational shock can collapse demand. These nonlinear patterns resemble chaotic systems where outcomes depend heavily on initial conditions and interactions rather than simple price signals.

Firms also operate within chaotic dynamics. A slight change in cost structure, a small innovation, or a minor strategic adjustment can set off competitive cascades. One firm’s price cut may trigger retaliatory cuts, shifting the entire market equilibrium. A small technological improvement can destabilize established industries. Chaos theory helps explain why industries sometimes experience sudden shakeups, why dominant firms can fall quickly, and why competitive landscapes evolve unpredictably. Even when firms behave rationally, their interactions can produce chaotic outcomes.

Market competition itself often resembles a chaotic system. In models where firms repeatedly adjust prices or quantities based on competitors’ actions, the resulting dynamics can oscillate, diverge, or behave unpredictably. Instead of converging to a stable equilibrium, markets may cycle endlessly or shift abruptly. Chaos theory shows that even simple strategic rules—like adjusting output based on last period’s profits—can generate complex patterns. This challenges the assumption that markets naturally gravitate toward stability.

Chaos theory also reshapes how economists think about supply chains. Microeconomics traditionally treats supply chains as linear sequences of production. In reality, they are networks of interdependent agents. A small disruption at one node—a delayed shipment, a minor shortage, a slight increase in demand—can propagate through the network. These ripples can amplify, producing large swings in inventory, pricing, and production. The “bullwhip effect,” where small changes in consumer demand cause large fluctuations upstream, is a classic example of chaotic dynamics in microeconomic systems.

Expectations play a central role in microeconomic chaos. Individuals and firms make decisions based not only on current conditions but on beliefs about the future. These beliefs are influenced by limited information, heuristics, and social cues. A small rumor or a slight shift in sentiment can alter expectations, which then alter behavior. This feedback loop can generate chaotic patterns in markets. For example, a minor concern about future prices can trigger hoarding, which then drives actual price increases. Chaos theory helps explain why expectations-driven markets—like housing, cryptocurrency, or collectibles—often behave unpredictably.

Labor markets also exhibit chaotic dynamics. A small change in hiring practices, a slight shift in worker preferences, or a minor technological adjustment can reshape job flows. Workers respond to wages, working conditions, and expectations, while firms respond to productivity, costs, and competition. These interactions can produce nonlinear outcomes: sudden shortages, rapid wage spikes, or unexpected declines in labor participation. Chaos theory highlights how sensitive labor markets are to small changes and how difficult it is to predict their evolution.

Even bargaining and negotiation reflect chaotic principles. In microeconomic models of bargaining, small differences in information, timing, or expectations can lead to vastly different outcomes. Chaos theory suggests that negotiation dynamics may not converge smoothly but may jump between equilibria depending on subtle shifts in strategy. This helps explain why seemingly minor details—tone, timing, or framing—can dramatically influence economic outcomes in real-world negotiations.

***

***

Chaos theory also intersects with behavioral microeconomics. Human decision-making is nonlinear, emotional, and context-dependent. Small psychological triggers can produce large changes in behavior. When millions of individuals behave this way simultaneously, the aggregate effects can be chaotic. Herd behavior, fads, and sudden shifts in sentiment all reflect nonlinear micro-level dynamics. Chaos theory provides a framework for understanding why markets sometimes behave irrationally and why small nudges can produce large outcomes.

Ultimately, chaos theory in microeconomics is not about rejecting traditional models. It is about enriching them. It acknowledges that individual agents operate within complex networks of interactions, feedback loops, and evolving expectations. It teaches that micro-level decisions can produce macro-level unpredictability and that stability is often an illusion. Chaos theory encourages economists to embrace complexity, recognize the limits of prediction, and design policies and strategies that are robust to uncertainty.

In practice, this perspective fosters humility and creativity. It reminds us that markets are not mechanical systems but dynamic human environments. It encourages economists, policymakers, and businesses to pay attention to small details, subtle signals, and emerging patterns. Chaos theory does not offer simple answers, but it provides a powerful lens for understanding why microeconomic systems behave the way they do—and why small actions can matter enormously.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

MEDICAL EDUCATION: High Tuition Costs

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The cost of medical education in the United States has climbed to a level that forces students, families, and even institutions to confront uncomfortable questions about who can realistically pursue a career in medicine. While the profession carries prestige, purpose, and the promise of financial stability, the path to becoming a physician is increasingly defined by staggering tuition bills, years of lost income, and long‑term debt obligations that shape graduates’ lives for decades. The price tag has grown so large that it is no longer just an economic issue; it is reshaping the demographics, motivations, and mental health of future physicians, and ultimately influencing the healthcare system itself.

Medical school tuition alone often exceeds what many Americans earn in a year. Students routinely face annual costs that can surpass $60,000 to $70,000, and that figure does not include housing, food, transportation, exam fees, or the cost of applying to residency programs. When the full journey is tallied—undergraduate education, medical school, and the years of training that follow—many new physicians emerge with debt loads well above $200,000. Some carry balances closer to $300,000. These numbers are not abstract; they shape every decision a student makes, from where they apply to school to what specialty they choose.

The financial pressure begins even before medical school acceptance. The application process itself is expensive. Prospective students pay for standardized tests, primary applications, secondary applications, and travel for interviews. For many, this phase alone costs several thousand dollars. Students from lower‑income backgrounds often struggle to compete in this early stage, not because of academic ability, but because the financial barrier is already too high. The pipeline narrows before training even begins.

Once enrolled, the intensity of medical education makes it nearly impossible for students to work part‑time to offset costs. The curriculum demands long hours, constant studying, and clinical responsibilities that leave little room for supplemental income. As a result, most students rely heavily on loans. Interest accumulates quickly, and because medical school lasts four years—followed by residency training that can stretch from three to seven years—many graduates watch their balances grow even as they work full‑time caring for patients.

The burden of debt influences career choices in ways that ripple across the healthcare system. Students who might otherwise pursue lower‑paying specialties such as primary care, pediatrics, or psychiatry often feel compelled to choose fields with higher salaries to manage their financial obligations. This dynamic contributes to shortages in essential specialties and exacerbates disparities in access to care. The country needs more primary care physicians, yet the economics of medical education push students away from these roles. In this way, the cost of training does not just affect individuals; it shapes national healthcare outcomes.

The psychological toll is equally significant. Medical school is already known for its demanding workload and high stress levels, but financial anxiety adds another layer of pressure. Students worry about every dollar they borrow, every interest payment, and every future bill. This chronic stress can affect academic performance, personal relationships, and mental health. For some, the weight of debt becomes a defining feature of their medical journey, overshadowing the excitement and purpose that initially drew them to the profession.

The high cost also affects diversity within medicine. Students from wealthy families can navigate the financial landscape more easily, while those from lower‑income backgrounds face barriers that are often insurmountable. This creates a profession that does not fully reflect the population it serves. Diverse physicians bring cultural insight, language skills, and lived experiences that improve patient care. When the cost of education limits who can enter the field, the entire healthcare system loses these valuable perspectives.

***

***

Institutions often justify high tuition by pointing to the expense of running medical programs. Teaching hospitals, laboratories, simulation centers, and faculty salaries require substantial funding. While these costs are real, the escalation of tuition has outpaced inflation and income growth for decades. Students are left wondering whether the financial structure of medical education is sustainable or whether it is drifting toward a crisis that will eventually force reform.

Despite these challenges, many students continue to pursue medicine because they feel called to the work. They want to heal, to serve, and to contribute to society in a meaningful way. But passion alone cannot erase the financial realities. The question is not whether medical education should be rigorous or resource‑intensive—it must be both. The question is whether the current model is fair, accessible, and aligned with the nation’s healthcare needs.

The high cost of medical education is more than a personal burden; it is a systemic issue with far‑reaching consequences. It shapes who becomes a doctor, what specialties they choose, where they practice, and how they experience their training. It influences the availability of care in underserved communities and contributes to workforce shortages in critical fields. Addressing this challenge will require creativity, commitment, and a willingness to rethink long‑standing assumptions about how physicians are trained.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

THEORY: Financial Relativity

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***.

***

Financial Relativity as a Perspective-Based Framework

At its core, financial relativity argues that value, risk, and opportunity are not fixed properties. They change based on the observer’s circumstances. A pension fund with a 40‑year horizon experiences volatility as background noise; a day trader experiences the same volatility as existential threat. A government views inflation as a macroeconomic variable; a household views it as a direct assault on purchasing power. The underlying reality is the same, but the interpretation—and the resulting decisions—are relative.

This relativity of perspective explains why financial debates often feel circular. Two people can look at the same data and reach opposite conclusions because their frames of reference differ. The theory suggests that instead of searching for universal financial truths, we should analyze the observer’s position first. Only then does the behavior of markets make sense.

Time as the Central Variable

In physics, relativity reshapes our understanding of time. In finance, time is the most important dimension. Every financial decision—investing, borrowing, saving, hedging—depends on how much time the observer has and how they perceive it.

  • Short-term observers (traders, speculators, leveraged investors) experience markets as chaotic, fast-moving, and dominated by noise.
  • Long-term observers (retirement savers, endowments, sovereign wealth funds) experience markets as slow-moving systems governed by cycles, mean reversion, and structural trends.

The same asset can be “risky” in one frame and “safe” in another. A volatile stock may be dangerous for a trader but ideal for a long-term investor who sees volatility as the price of future growth. Financial relativity argues that time doesn’t just influence risk—it defines it.

Relativity of Risk and Reward

Traditional finance treats risk as measurable and objective. The theory of financial relativity challenges this by asserting that risk is always relative to goals, constraints, and psychology.

For example:

  • A retiree holding cash sees risk in market downturns.
  • A young investor holding cash sees risk in inflation eroding future wealth.
  • A corporation sees risk in credit spreads and refinancing windows.
  • A policymaker sees risk in systemic instability.

Each observer is correct within their own frame. Financial relativity helps explain why universal risk metrics—like volatility or beta—often fail to capture lived financial experience. They measure movement, not meaning.

***

***

Incentives as Gravitational Forces

In relativity, gravity bends space-time. In finance, incentives bend behavior. They shape how individuals and institutions interpret information, allocate capital, and respond to uncertainty.

  • Analysts paid for short-term performance emphasize quarterly results.
  • CEOs compensated with stock options emphasize share price.
  • Regulators emphasize stability.
  • Venture capitalists emphasize growth.

These incentive structures create “financial gravity wells” that pull decisions in predictable directions. The theory of financial relativity argues that markets cannot be understood without mapping these incentive fields. They distort financial space just as gravity distorts physical space.

Information and the Observer Effect

Financial relativity also incorporates an observer effect: the act of observing or acting on information changes the system itself. Markets react to expectations, forecasts, and sentiment. A rumor can move prices; a central bank statement can reshape global capital flows. Information is not passive—it is an active force.

This explains why markets often behave irrationally or overshoot fundamentals. Observers influence the system, and the system influences observers, creating feedback loops that resemble the curvature of space-time.

Relativity of Value

Value is often treated as intrinsic, but financial relativity argues that value is contextual. It depends on:

  • liquidity needs
  • tax considerations
  • regulatory constraints
  • alternative opportunities
  • personal or institutional priorities

A bond yielding 4% may be unattractive to a hedge fund but essential to an insurance company. A startup may be worthless to a bank but priceless to a venture capitalist. Value is not a universal constant; it is relative to the observer’s world.

Implications for Financial Decision-Making

The theory of financial relativity encourages a shift in thinking:

  1. Understand your frame of reference. Your time horizon, incentives, constraints, and goals define what is risky or valuable.
  2. Recognize that others operate in different frames. Market movements often reflect conflicting perspectives rather than irrationality.
  3. Avoid universal prescriptions. What is “good” or “bad” financially depends on who you are and what you need.
  4. Embrace dynamic interpretation. As your circumstances change, your financial truths should change with them.

Conclusion

The theory of financial relativity is a conceptual framework that treats financial behavior, market dynamics, and economic outcomes as dependent on the observer’s position, incentives, and time horizon—much like Einstein’s relativity treats measurements of space and time as dependent on the observer’s frame of reference. It isn’t a formal academic doctrine, but it’s a powerful way to understand why markets behave differently for different participants, why risk is never absolute, and why financial truths often shift depending on who is looking and when.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

NOBEL PRIZE: Economics

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Robert E. Hall and Michael Woodford win Nobel memorial prize in economics

American economists Robert E. Hall and Michael Woodford won the 2026 Nobel Memorial Prize in Economic Sciences for research that has helped governments and central banks manage economic shocks and stabilise economies during crises.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Columbus Day Stock & Bond Markets

***

***

Monday, October 12th 2026

  • Today is a federal/bank holiday in observance of Columbus Day.
  • U.S. equity, options, and futures markets will be open but it’s a non-settlement day. 
  • All trades placed on Friday, October 9th 2026, will settle on Tuesday, October 13th, 2026.
  • All fixed income and bond markets will be closed.
  • Requests to move money received after the standard cut-off times on Friday, October 9th 2026, will not be processed until Tuesday, October 13th 2026.

Global Markets 

  • All Canadian markets will be closed in observance of Canadian Thanksgiving. Dually listed Canadian stocks will trade in the U.S. markets on Monday, October 12th 2026.

COMMENTS APPRECIATED

EDUCATION: Books

***

CAR LOANS: Interest Deductions 2025-2028

***

***

The Treasury Department and IRS have finalized regulations regarding the deduction of up to $10,000 in personal car loan interest by individuals for tax years 2025 through 2028. This includes regulations on information returns required to be filed by a lender or other person engage in a trade or business who receives $600 or more of qualified interest during the calendar year.

The final regulations adopt the proposed regulations published in January 2026 (NPRM REG-113515-25) with some changes in response to public comments.

COMMENTS APPRECIATED

EDUCATION: Books

***

PARADOX: Financial Health?

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

FINANCIAL HEALTH PARADOX

Classic Definition: Research from Ernst-Young [Nikhil Lele and Yang Shim] uncovered a chasm between how consumer patients think they’re doing financially, and the actual state of their finances. Even more striking, their study suggested that improving consumers’ financial health will become one of the top imperatives in reframing consumer financial services.

Modern Circumstance: For example, the study asked consumers to rate their own financial health, and 83 percent rated themselves “good,” “very good” or “excellent.”  Now, contrast this figure with what is known about their actual situation:

  • 60 percent of Americans say they are financially stressed.
  • 56 percent of Americans have less than $10,000 saved for retirement.
  • 40 million American families have no retirement savings at all.
  • 40 percent of Americans are not prepared to meet a $400 short-term emergency.

Paradox Example: Fortunately, even though the vast majority of consumers rate themselves as financially healthy, the study found that most still want to improve. Importantly for health economists, the attractive 25-34 and 35-49 year-old age groups were most likely to be extremely or very interested in improving their financial and economic health.

Paradox Example: Massively affluent consumer patients are even more interested in improving this paradox than their mass market counterparts.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Nobel Prize in Chemistry

***

***

STOCKHOLM — Scientists Henri B. Kagan and Kenso Soai just won the Nobel Prize in chemistry for untangling mysterious mirror images in molecules, a discovery that has been used to develop countless drugs and transformed modern medicine.

COMMENTS APPRECIATED

EDUCATION: Books

***

ELTON MAYO: Human Relations Management Theory

By Dr. David Edward Marcinko; MBA MEd

By Eugene Schmuckler; PhD MBA MEd CTS

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Human Relations Theory is an important approach to management that emphasizes the role of people, social relationships, communication, and employee satisfaction in an organization. It developed as a reaction to earlier management theories that mainly focused on productivity, efficiency, rules, and financial incentives. One of the most important contributors to this approach was Elton Mayo, an Australian-born psychologist and sociologist who became closely associated with the Human Relations Movement. Mayo argued that workers are not simply economic beings motivated by money; they are also influenced by social relationships, recognition, group belonging, morale, and the attitudes of managers.

Elton Mayo’s ideas became particularly influential through the Hawthorne Studies, conducted at the Western Electric Company’s Hawthorne Works in Chicago during the 1920s and early 1930s. These studies helped draw attention to the importance of informal groups and human factors in the workplace. Human Relations Theory subsequently became an important foundation for modern organizational behavior and management.

Meaning of Human Relations Theory

Human Relations Theory refers to an approach to management that recognizes employees as social and psychological beings. According to this approach, organizational performance depends not only on physical working conditions and financial rewards but also on how employees feel about their work and their relationships with colleagues and supervisors.

Traditional management approaches tended to view employees primarily in terms of productivity and economic rewards. Human Relations Theory introduced a different perspective. It suggested that employees have social needs, such as the need for friendship, recognition, acceptance, respect, and a sense of belonging. When these needs are addressed, employees may develop greater commitment to their work and organization.

The theory therefore emphasizes the importance of communication, leadership, teamwork, employee participation, morale, and informal social groups. Managers are encouraged to understand employees and create working environments in which people feel valued and respected.

Elton Mayo and the Hawthorne Studies

Elton Mayo’s contribution to management is strongly associated with the Hawthorne Studies. The studies were initially designed to examine whether changes in physical working conditions affected worker productivity. Researchers examined factors such as lighting, working hours, rest periods, and other workplace conditions.

An important observation emerged from these experiments: changes in productivity could not always be explained simply by physical conditions. Workers’ attitudes, relationships, group behavior, and the attention they received from researchers appeared to influence their behavior.

Mayo and his colleagues concluded that workers were influenced by social factors within the workplace. Employees formed informal groups, developed their own standards of acceptable behavior, and responded to group expectations. This demonstrated that organizations contain both formal structures, created by management, and informal structures, created naturally through relationships among employees.

The Hawthorne Studies therefore helped shift attention from purely mechanical explanations of productivity toward the social and psychological aspects of work.

Main Principles of Human Relations Theory

One of the central principles of Human Relations Theory is that employees are social beings. People seek interaction with others and want to feel that they belong to a group. A workplace that ignores these needs may experience dissatisfaction and poor cooperation.

Another important principle is the importance of informal groups. Employees naturally form friendships and social groups, and these groups can influence attitudes and productivity. Informal group norms may sometimes be more influential than formal organizational rules.

Employee morale is also important. When workers feel respected, recognized, and valued, they may show greater enthusiasm toward their responsibilities. Managers therefore need to consider employee satisfaction alongside productivity.

The theory also emphasizes communication. Open and effective communication between managers and employees can reduce misunderstandings and improve cooperation. Employees are more likely to feel involved when managers listen to their opinions and explain organizational decisions.

Another principle is participative management. Employees can contribute useful knowledge about their jobs and working conditions. Giving workers opportunities to express their views can strengthen their sense of involvement and responsibility.

Finally, Human Relations Theory stresses the importance of leadership and supervision. Managers are not merely controllers of work; they also influence employee attitudes and relationships. Supportive leadership can encourage cooperation, trust, and commitment.

***

***

Importance of Human Relations Theory

Human Relations Theory made a significant contribution to management because it broadened the understanding of employee motivation. It showed that productivity cannot be understood entirely through wages, physical conditions, or formal rules. Human emotions and social relationships can also affect workplace behavior.

The theory also influenced the development of modern approaches to organizational behavior. Contemporary organizations pay attention to teamwork, employee engagement, organizational culture, leadership, communication, and workplace relationships. These areas reflect many of the concerns first emphasized by the Human Relations Movement.

The theory also changed the role of managers. Instead of seeing management only as the process of planning, organizing, and controlling work, it encouraged managers to develop interpersonal skills. A manager is expected to communicate effectively, understand employees, resolve conflicts, encourage teamwork, and create a positive working environment.

Furthermore, the theory highlighted the importance of informal organization. Every workplace has relationships and social networks that exist alongside its official hierarchy. Understanding these informal relationships can help managers improve cooperation and address workplace problems.

Criticism of Human Relations Theory

Although Human Relations Theory made important contributions, it has also been criticized. One criticism is that it may place too much emphasis on social relationships while giving insufficient attention to economic and structural factors. Employees are influenced by wages, job security, working conditions, career opportunities, and organizational policies as well as social relationships.

Another criticism concerns the interpretation of the Hawthorne Studies. Later scholars questioned some of the conclusions traditionally associated with the experiments and argued that the relationship between attention, workplace conditions, and productivity was more complicated than early accounts suggested.

The theory can also be criticized for assuming that greater employee satisfaction will automatically result in higher productivity. A satisfied employee is not necessarily a highly productive employee. Productivity can depend on technology, skills, resources, organizational structure, incentives, and many other factors.

Despite these limitations, Human Relations Theory remains significant because it introduced a more human-centered perspective into management.

Conclusion

Elton Mayo and the Human Relations Movement played an important role in changing the way organizations understand employees. Through the Hawthorne Studies, Mayo drew attention to the influence of social relationships, informal groups, communication, morale, and leadership on workplace behavior. His work challenged the idea that employees could be understood only through economic incentives and physical working conditions.

Human Relations Theory established that organizations are social systems as well as economic and technical systems. Employees have psychological and social needs, and these needs can influence their attitudes and behavior at work. Although the theory has limitations and some of the conclusions drawn from the Hawthorne Studies have been debated, its influence on management remains considerable. Modern ideas about teamwork, employee participation, communication, leadership, organizational culture, and employee engagement continue to reflect the central insight of the Human Relations approach: effective management requires attention not only to work and productivity but also to the people who perform the work.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Nobel Prize Winners 2026

***

****

The Nobel Prize in Physiology or Medicine 2026 was awarded jointly to Karl Deisseroth, Peter Hegemann and Georg Nagel “for their discoveries concerning light-gated ion channels and optogenetics.”

COMMENTS APPRECIATED

EDUCATION: Books

***

HEALTHCARE: Propensity to Pay

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The propensity to pay in healthcare refers to an individual’s willingness and ability to spend money on healthcare services, medicines, treatments, and other health-related needs. It is an important concept because healthcare decisions are influenced not only by medical needs but also by financial circumstances, personal preferences, perceptions of quality, and expectations about future health. Understanding the propensity to pay can help healthcare providers, policymakers, and organizations better understand how people make decisions about accessing and purchasing healthcare.

One of the main factors influencing a person’s propensity to pay is income. Individuals with higher incomes generally have greater financial flexibility and may be more willing to pay for private consultations, specialist services, advanced treatments, preventive care, or shorter waiting times. In contrast, people with lower incomes may postpone treatment, rely more heavily on publicly funded services, or choose less expensive alternatives. However, income alone does not determine healthcare spending. People may prioritize healthcare differently depending on their circumstances and personal values.

The perceived importance of a healthcare service also affects willingness to pay. When individuals believe that a treatment is essential or could significantly improve their health or quality of life, they may be willing to spend more. For example, someone experiencing severe pain may place a higher financial value on immediate treatment than on other types of expenditure. Similarly, parents may be particularly willing to pay for services that they believe will protect the health of their children. Preventive services, however, can be more difficult to value because their benefits may occur in the future rather than immediately.

Trust and perceived quality are also important. Patients are more likely to pay for healthcare when they believe that a provider is competent, trustworthy, and capable of delivering good outcomes. Reputation, communication, professional qualifications, facilities, and previous experiences can all influence this perception. A patient who has confidence in a particular doctor or hospital may be willing to pay more for its services than for an unfamiliar provider. Conversely, poor experiences or concerns about unnecessary treatment can reduce willingness to pay.

***

***

Insurance and the structure of healthcare financing can substantially change individual behavior. When insurance covers a large proportion of healthcare costs, patients may face relatively small direct payments and therefore be less sensitive to the full price of services. Deductibles, copayments, and other forms of cost sharing can increase price sensitivity. At the same time, high out-of-pocket costs may discourage people from seeking necessary care, particularly when their income is limited. Consequently, the relationship between price and healthcare utilization is more complicated than in many ordinary consumer markets.

Cultural, social, and demographic factors can also influence propensity to pay. Age, education, family responsibilities, health status, and attitudes toward medicine may affect healthcare spending decisions. Some individuals may place considerable emphasis on preventive care and wellness, while others may seek medical attention primarily when symptoms become serious. Social expectations can also influence choices, particularly when healthcare decisions involve family members or dependents.

The propensity to pay is also relevant to healthcare businesses. Providers need to understand what patients value when designing services and pricing strategies. Convenience, accessibility, personalized care, technology, and shorter waiting periods may increase the perceived value of a service. Nevertheless, healthcare organizations must balance financial considerations with ethical responsibilities. Unlike many consumer products, healthcare can involve essential services that people cannot reasonably avoid purchasing.

Overall, propensity to pay in healthcare is shaped by a combination of economic, medical, psychological, and social factors. Income and price are important, but willingness to pay also depends on perceived need, expected benefits, trust, quality, insurance coverage, and individual circumstances. Understanding these factors can help healthcare providers design accessible services and help policymakers consider how financing systems affect access to care. Ultimately, examining propensity to pay provides insight into the complex relationship between healthcare needs, financial resources, and individual decision-making.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

BREAKING NEWS: Unemployment Rate Ticks Up

***

***

WASHINGTON (AP) — U.S. employers added a disappointing 29,000 jobs and the unemployment rate ticked up last month, the government reported Friday, a month before voters go to the polls in pivotal midterm elections at a time of discontent over the high cost of living and the state of the economy.

Hiring dropped from a revised 133,000 in August, the Labor Department said. The unemployment rate rose to a still-low 4.2% from 4.1% in August.

Economists had expected September payrolls to come in around 90,000!

Labor Department revisions also shaved 60,000 jobs off combined July and August payrolls.

COMMENTS APPRECIATED

EDUCATION: Books

***

GUYTON-KLINGER: Equation

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

The Guyton–Klinger equation, more accurately described as the Guyton–Klinger decision rules, is a set of mathematically defined withdrawal‑rate adjustments designed to guide retirees in determining how much they can safely withdraw from an investment portfolio each year. Unlike fixed‑percentage or inflation‑adjusted withdrawal strategies, the Guyton–Klinger framework introduces a dynamic system that responds to market performance. Its purpose is to preserve the longevity of a retirement portfolio while still allowing the retiree to enjoy a stable, predictable income. The “equation” is not a single formula but a set of interlocking rules that operate like a feedback system. These rules—commonly known as the inflation rule, the capital preservation rule, and the prosperity rule—form a mathematical structure that adjusts withdrawals up or down depending on portfolio conditions.

At its core, the Guyton–Klinger system begins with an initial withdrawal rate, often around 4–5 percent of the portfolio’s starting value. This initial rate is then subjected to annual adjustments based on the rules. The inflation rule governs whether the withdrawal amount should be increased to keep pace with rising prices. Unlike a simple inflation‑adjusted strategy, the Guyton–Klinger method restricts inflation adjustments during years when the portfolio has declined. This creates a built‑in stabilizer: the retiree does not automatically increase spending when the portfolio is under stress. Mathematically, this rule can be expressed as a conditional statement: if the portfolio’s real return for the year is negative, the inflation adjustment is skipped. This conditionality is the first component of the broader Guyton–Klinger equation.

The second component, the capital preservation rule, introduces a lower guardrail. It compares the current withdrawal rate—defined as the withdrawal amount divided by the portfolio’s current value—to the initial withdrawal rate. If the current rate rises too far above the initial rate, typically by more than 20 percent, the rule triggers a spending cut. This can be expressed as a ratio: if (current withdrawal ÷ portfolio value) > (initial withdrawal rate × 1.20), then the withdrawal amount is reduced by a fixed percentage, often 10 percent. This is the mathematical heart of the system: a dynamic ratio that signals when the portfolio is at risk of depletion. The rule ensures that withdrawals do not become unsustainably large relative to the shrinking portfolio.

The third component, the prosperity rule, acts as the counterpart to the capital preservation rule. When the portfolio grows significantly, the retiree is allowed to increase withdrawals. The rule is triggered when the current withdrawal rate falls below a lower guardrail—typically 20 percent below the initial rate. In mathematical terms, if (current withdrawal ÷ portfolio value) < (initial withdrawal rate × 0.80), then the withdrawal amount is increased by a fixed percentage, again often 10 percent. This rule allows retirees to enjoy the benefits of strong market performance without jeopardizing long‑term sustainability.

Together, these rules form a dynamic system that resembles a thermostat. When the portfolio overheats—meaning the withdrawal rate becomes too high relative to the portfolio’s value—the system cools spending. When the portfolio is performing well, the system allows spending to warm up. The inflation rule adds a third dimension by moderating spending increases during downturns. The interplay of these rules is what people often refer to as the “Guyton–Klinger equation,” even though it is more accurately a set of conditional equations.

One of the most important features of the Guyton–Klinger framework is that it balances two competing goals: income stability and portfolio longevity. Retirees typically want predictable income, but they also want assurance that their savings will last. Fixed‑percentage withdrawal strategies can cause income to fluctuate dramatically, while fixed‑inflation strategies can cause withdrawals to become unsustainable. The Guyton–Klinger system attempts to strike a middle ground by allowing adjustments only when necessary and by basing those adjustments on mathematically defined thresholds.

Another key aspect is that the system is forward‑looking but rule‑based. It does not attempt to predict market performance. Instead, it reacts to actual portfolio changes. This makes it adaptable across different market environments. During prolonged bull markets, the prosperity rule allows retirees to increase spending without fear of overshooting. During bear markets, the capital preservation and inflation rules work together to slow spending and protect the portfolio.

The Guyton–Klinger equation also implicitly acknowledges behavioral realities. Retirees often struggle with cutting spending, and the system’s guardrails help make those decisions objective rather than emotional. The rules provide a clear rationale for when spending must be reduced, which can make difficult adjustments easier to accept. Similarly, the prosperity rule encourages retirees to enjoy their savings when conditions allow, countering the tendency to underspend out of fear.

In summary, the Guyton–Klinger equation is a structured, mathematically grounded approach to retirement withdrawals that uses conditional rules to adjust spending based on portfolio performance. It replaces rigid withdrawal strategies with a flexible, responsive system that aims to preserve both income stability and long‑term financial security. By defining clear thresholds for when to increase or decrease withdrawals, the framework offers retirees a disciplined yet adaptable method for navigating the uncertainties of retirement finance.

COMMENTS APPRECIATED

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

FINANCE: Propensity to Pay

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

****

***

The propensity to pay is an important concept in finance that describes the likelihood and willingness of an individual, business, or organization to make a financial payment when it becomes due. It is closely related to financial behavior, creditworthiness, liquidity, and the ability to meet financial obligations. Financial institutions, businesses, and investors consider payment behavior when making decisions about lending, credit management, investment, and risk. Understanding the propensity to pay therefore helps financial decision-makers evaluate whether expected payments are likely to be made on time and in full.

In personal finance, propensity to pay can be influenced by income, employment stability, existing debt, spending habits, savings, and financial priorities. An individual with a stable income and manageable debt is generally more capable of meeting regular obligations such as loan installments, credit card balances, rent, and utility bills. However, the ability to pay does not always guarantee the willingness to pay. A person may have sufficient financial resources but choose to delay a payment because of competing priorities or expectations about future income. This distinction between ability and willingness is important when assessing financial risk.

For businesses, propensity to pay is particularly significant in managing accounts receivable and extending credit to customers. Companies frequently allow customers to purchase goods or services before making payment. While this practice can encourage sales and strengthen business relationships, it also creates the possibility of late or unpaid invoices. Businesses therefore evaluate customers’ previous payment records, financial condition, industry circumstances, and credit terms. A strong propensity to pay can support more flexible credit arrangements, whereas uncertainty about payment behavior may lead a company to require deposits, shorter payment periods, or additional security.

Banks and other financial institutions also rely heavily on payment behavior when assessing borrowers. Credit scores, repayment histories, debt-to-income ratios, and other financial information can help lenders estimate the probability that borrowers will meet their obligations. A borrower who has consistently made payments on time may be viewed as presenting less repayment risk than someone with a history of missed or late payments. These assessments influence lending decisions, interest rates, credit limits, and other terms. In this way, propensity to pay is an important component of credit risk management.

Economic conditions can also affect propensity to pay. During periods of economic growth, employment and business revenues may increase, making it easier for borrowers and customers to meet their obligations. During economic downturns, unemployment, declining sales, inflation, and higher interest rates can place pressure on household and business finances. Even financially responsible borrowers may experience difficulties when their income decreases or expenses rise unexpectedly. Consequently, financial institutions must consider broader economic conditions rather than relying solely on an individual’s or company’s past payment behavior.

Technology has made the assessment of payment propensity increasingly sophisticated. Financial institutions and businesses can analyze large amounts of transaction and credit data to identify patterns in payment behavior. Automated systems can monitor missed payments, changes in account activity, and other indicators of financial stress. These tools can improve risk assessment and allow organizations to respond more quickly to potential repayment problems. At the same time, responsible use of financial data is important because inaccurate information or inappropriate assessment methods can unfairly affect access to credit.

Propensity to pay also has implications for financial planning and business strategy. Individuals can improve their payment behavior by maintaining budgets, building emergency savings, reducing unnecessary debt, and organizing payment schedules. Businesses can improve collections by establishing clear credit policies, communicating payment expectations, monitoring outstanding invoices, and maintaining good relationships with customers. These practices can reduce financial uncertainty and improve cash flow.

In conclusion, propensity to pay is a fundamental concept in finance because it helps explain whether financial obligations are likely to be fulfilled. It reflects both the ability and willingness to make payments and is influenced by personal financial circumstances, business conditions, economic developments, and payment history. By understanding these factors, lenders, businesses, and individuals can make more informed financial decisions, manage risk, and maintain healthier financial relationships.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

Hospitals Have a Little-Known Tool To Prevent Medical Debt

Here’s How It Works

By Melanie Evans, Tradeoffs

October 1st, 2026

If you have medical debt, there’s a good chance you owe money to a hospital.

One way patients can avoid medical debt is through hospital financial assistance, also known as charity care. Most of the nation’s hospitals offer free or discounted medical care to patients with very high medical debt or low incomes.

Getting financial assistance, however, can be challenging. Many patients don’t know that hospitals offer financial help, surveys show, and complex application forms leave others stymied.

Hospitals often demand that applicants turn over bank statements, pay stubs, tax returns, divorce filings, or other materials, and submit their applications in person, by mail, or by fax.

“They don’t make it easy,” said Neale Mahoney, a Stanford University economist who studies medical debt.

Such hurdles leave many patients with unpaid bills they should never have had to pay in the first place. In a single year, hospitals and health systems billed patients for at least $2 billion that they likely didn’t owe, one analysis found.

As healthcare costs climb and more people lose their coverage, states and hospitals are testing an emerging approach to fix this problem: automatically screening patients to see if they qualify for assistance and proactively wiping out debt when they do. This is known as “presumptive eligibility.”

Under this approach, patients may have the cost of their care wiped out before they see any bills — but not always. Hospitals differ on when, how, and for whom they use auto-enrollment, potentially impinging on patients’ finances.

Here’s what you need to know about how auto-enrollment works.

What is hospital financial assistance?

In many states, hospitals set their own criteria for whom they provide financial aid. Eligibility is typically based on income for the patient’s entire household. The closer patients are to poverty, the less they have to pay. Patients with middle incomes and insurance are sometimes eligible for discounts, especially if their bills would gobble up a big chunk of what they earn.

At least 11 states require hospitals to wipe out bills for low-income patients, though income cutoffs vary. Georgia, for example, mandates free care for anyone with income slightly above the federal threshold for poverty. In several states — including Oregon, North Carolina, and Maryland — patients can earn double that amount and still get free care.

But in most states, many patients must complete applications to receive assistance.

Several states in recent years have launched investigations and passed legislation designed to make it easier for people to get help. Research into medical debt, however, suggests gaps persist.

***

***

How many hospitals use auto-enrollment?

Nearly all nonprofit hospitals say they screen and automatically reduce bills for certain patients.

Under the Affordable Care Act, nonprofit hospitals must make reasonable efforts to find people who are eligible for help before they take patients to court, sell their debt to collection agencies, or ding their credit over bills. Presumptive eligibility is one way hospitals can comply with the regulation, which took effect in 2016.

In the first year under the new rules, about 70% of tax-exempt hospitals nationwide said they screened patients and proactively reduced bills, according to an analysis of federal data for Tradeoffs by the independent research institute RTI International. As of 2022, that figure was nearly 90%.

The federal law doesn’t apply to for-profit and public hospitals, which don’t have to report the actions they take before going after patients for unpaid bills.

In six states, policymakers require hospitals to use presumptive eligibility and skip applications for certain patients. Those states are California, Delaware, Illinois, Maryland, North Carolina, and Oregon.

Who is eligible to be automatically enrolled in financial assistance?

In most states, hospitals decide which patients can skip the application.

Common groups automatically screened include people who are homeless, deceased, or already enrolled in state or federal programs to help low-income households with housing, food, or prescriptions. Other hospitals have more unique criteria, like Christus Health, which will write off bills for anyone in a religious order who took a vow of poverty.

Eligibility criteria are often buried in official policies and hard to find or decipher. Some hospitals share little to no public information about whom they will proactively screen. Thirteen hospitals owned by Ascension, one of the nation’s largest Catholic health systems, state only that they may screen patients “with a sufficient unpaid balance.”

Across the half-dozen states with presumptive eligibility mandates, eligibility rules vary. Maryland, for example, requires hospitals to proactively wipe out bills only for patients who already get government help for food or utilities but are ineligible for Medicaid. In Illinois, lawmakers created less-stringent requirements for rural hospitals compared with urban facilities.

In Oregon, starting in 2024, hospitals had to screen anyone who owed more than $500 and every patient on Medicaid or who is uninsured. In 2025, roughly 80% of Oregon patients who got financial help with bills never filled out an application, based on data shared publicly by the first 26 hospitals to do so. The state’s legislature this year raised the screening threshold to include patients who owe at least $1,500 for a single visit.

***

***

Without an application, how do hospitals figure out who gets help?

Hospitals have several ways to find patients eligible for financial assistance.

Typically, hospitals turn to public records, any information patients have previously volunteered, or tools from consumer credit companies to estimate whether patients qualify to have bills reduced.

For example, if a hospital sees that a patient lives in a high-poverty ZIP code or has no address listed, that could be enough to deem them eligible. Many pay companies to run employment and credit checks on patients to determine whether they qualify for free care.

Hospitals may also consider how likely patients are to pay bills, regardless of how much they earn. This is called “propensity to pay.” California and Oregon prohibit its use, concerned that hospitals may try to collect more often from people who dutifully pay their bills even though their incomes qualify them for financial assistance.

When do hospitals screen patients for financial aid?

It depends.

Illinois, North Carolina, and Oregon require hospitals to screen certain patients before they send any bills. California hospitals will have to do the same starting in 2027.

Some hospitals voluntarily screen patients before sending bills; others try to collect money from patients first. As long as they screen patients before suing them for very overdue bills, hospitals can stay within the letter of the federal law that pushed many of them to embrace presumptive eligibility.

For example, the policy of Christus Health is to screen patients only “after all other eligibility and payment sources have been exhausted.”

Anna Stelter, vice president of policy for the Texas Hospital Association, said hospitals want to investigate other options for payment — like Medicaid or county safety net programs — before they give out financial assistance.

“We do want to make sure that whoever is financially responsible for that care is identified and pays,” Stelter said. “Charity care is the relief of last resort.”

Hospitals’ publicly posted policies may also be fuzzy about when they will screen for patients likely eligible for help. For example, Cook Children’s Health Care System in Fort Worth, Texas, says its goal is to determine a patient’s eligibility “as soon as sufficient information is available.”

Who pays the bills when patients get free care?

In one sense, we all do. Taxpayers cover some or all of the cost of financial assistance, though the amount varies by hospital.

About half the nation’s hospitals are nonprofit and legally get a pass on paying most taxes. KFF estimates that nonprofit hospitals pocketed $24 billion in 2020 that they would otherwise have paid as income, sales, or property taxes.

Government-owned and for-profit hospitals have their own sets of tax benefits to help offset costs for low-income patients. Government hospitals often get additional taxpayer support, and for-profit hospitals generally receive smaller government subsidies, like additional payments for caring for high numbers of uninsured and Medicaid patients.

Whether taxpayer dollars fully cover hospitals’ costs for financial assistance depends on the amount of government support they receive — information often not publicly available. It also hinges on how many patients need help, how many meet hospitals’ criteria for assistance, and how many get through an application. Research shows hospitals spend widely different amounts on financial assistance, from less than 1% of yearly expenses to more than 7%.

Philanthropy and hospitals’ income cover costs not absorbed by tax dollars.

This article is part of “Hidden Help,” an investigative series from Tradeoffs and KFF Health News about how hospitals can protect their patients from the life-altering harms of medical debt.

Melanie Evans is a reporter for Tradeoffs, a nonprofit newsroom reporting on healthcare’s toughest choices. Sign up for the weekly newsletter to get the latest stories every Thursday morning.

Tradeoffs’ reporting for this series was supported, in part, by the California Health Care Foundation, the National Institute for Health Care Management Foundation, and the Solutions Journalism Network.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe

Your thoughts and comments on this ME-P are appreciated. Feel free to review our top-left column, and top-right sidebar materials, links, URLs and related websites, too. Then, subscribe to the ME-P. It is fast, free and secure.

SEND IN YOUR TOPIC IDEAS, TODAY!

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***

From Artificial Intelligence to Super Intelligence

By Dr. David Edward Marcinko; MBA MEd

SPONSOR: http://www.MarcinkoAssociates.com

***

***

Artificial intelligence (AI) has developed from a largely theoretical idea into a technology that is increasingly part of everyday life. AI systems can now understand language, recognize images, generate content, assist with scientific research, and perform complex tasks. As these systems become more capable, researchers and society are beginning to consider a possible future transition from artificial intelligence to artificial superintelligence. This development could transform human civilization, creating extraordinary opportunities while also raising serious questions about safety, control, and responsibility.

Artificial intelligence refers to computer systems designed to perform tasks that normally require human intelligence. These tasks include learning from information, solving problems, understanding language, recognizing patterns, and making decisions. Modern AI can already perform some tasks at a level comparable to or beyond humans. However, most existing AI systems remain specialized or limited in important ways. They depend on human-designed objectives, training data, computing resources, and environments in which they operate.

The concept of artificial general intelligence (AGI) describes a potential future system with broad intellectual abilities. Rather than being designed for one particular task, an AGI would theoretically be able to learn and perform a wide range of intellectual activities. It could potentially transfer knowledge between different subjects, adapt to unfamiliar problems, and improve its abilities through experience. Whether and when AGI will be achieved remains uncertain, and there is no universally accepted definition or test for it.

Artificial superintelligence represents a further hypothetical stage. It generally refers to an AI system whose intellectual capabilities substantially exceed those of humans across most or all areas of cognitive activity. Such a system could potentially conduct scientific research, develop technologies, analyze enormous amounts of information, and solve problems far more rapidly than individual humans or existing institutions. If achieved, superintelligence could accelerate progress in areas such as medicine, energy, transportation, education, and scientific discovery.

At the same time, the development of increasingly powerful AI could create significant challenges. One concern is the problem of ensuring that highly capable systems reliably pursue goals that are consistent with human intentions and values. A system that is extremely capable but misunderstands its objectives could produce harmful consequences even without intending to cause harm. Other concerns include cybersecurity, economic disruption, concentration of technological power, privacy, misinformation, and the possibility that advanced AI could be used irresponsibly by individuals or organizations.

The transition from AI to superintelligence should therefore not be viewed simply as a race to create increasingly powerful machines. It also involves developing methods for testing, monitoring, controlling, and governing advanced systems. Researchers are exploring areas such as AI alignment, interpretability, robustness, evaluation, and safety. Governments, businesses, researchers, and the public may all have roles in determining how increasingly powerful AI technologies are developed and used.

Ultimately, the path from artificial intelligence to superintelligence is uncertain. Some experts believe highly advanced systems could emerge relatively soon, while others believe major technical challenges remain. Regardless of the timeline, the possibility deserves careful consideration. AI has the potential to expand human capabilities enormously, but realizing its benefits will require thoughtful development and responsible decision-making. The central challenge is not simply creating machines that become more intelligent, but ensuring that increasing technological power contributes to human well-being and remains subject to appropriate human oversight.

EDUCATION: Books

SPEAKING: Dr. Marcinko will be speaking and lecturing, signing and opining, teaching and preaching, storming and performing at many locations throughout the USA this year! His tour of witty and serious pontifications may be scheduled on a planned or ad-hoc basis; for public or private meetings and gatherings; formally, informally, or over lunch or dinner. All medical societies, financial advisory firms or Broker-Dealers are encouraged to submit an RFP for speaking engagements: CONTACT: Ann Miller RN MHA at MarcinkoAdvisors1738@outlook.com -OR- http://www.MarcinkoAssociates.com

Like, Refer and Subscribe!

SEND IN YOUR TOPIC IDEAS, TODAY

HOSPITALS: http://www.crcpress.com/product/isbn/9781466558731

CLINICS: http://www.crcpress.com/product/isbn/9781439879900

ADVISORS: www.CertifiedMedicalPlanner.org

FINANCE:Financial Planning for Physicians and Advisors

INSURANCE:Risk Management and Insurance Strategies for Physicians and Advisors

Dictionary of Health Economics and Finance

Dictionary of Health Information Technology and Security

Dictionary of Health Insurance and Managed Care

***